

CCSD code G5100: Bypass of duodenum billing guide
CCSD code G5100 bills a bypass that leaves the duodenum in place CCSD code G5100...

Last Updated: Oct 16, 2026
38221 is the CPT code for diagnostic bone marrow; biopsy(ies). It covers a needle or trocar core biopsy of the marrow on its own, with any number of cores taken from the same site.
When an aspiration is also taken at the same session, the procedure is reported as 38222 instead. An aspiration alone is 38220, so the procedure note decides which of the three codes applies.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CPT code 38221 covers a diagnostic bone marrow biopsy on its own, with any number of cores taken from the same site.
A biopsy and an aspiration at the same site and session are reported as 38222, never as 38221 plus 38220.
38220 and 38221 appear on one claim only for separate sites or encounters, with modifier XS or 59 on 38220.
CMS gives 38221 a global indicator of XXX. Some payers still expect modifier 25 on a separately identifiable same-day E/M service.
In the CY2026 Medicare fee schedule, 38221 carries 5.00 total RVUs in the office and 1.73 in a facility.
CPT code 38221 is the code for a diagnostic bone marrow biopsy performed on its own, with no aspiration taken at the same site. The descriptor in the American Medical Association’s CPT code set reads “Diagnostic bone marrow; biopsy(ies)”. The plural matters, because one unit of 38221 covers every core taken from that site.
The physician advances a biopsy needle or trocar through the cortical bone, most often at the posterior iliac crest. A solid core of marrow is then removed. That core keeps the marrow architecture intact. Pathologists use it to judge cellularity, fibrosis and infiltration, which a liquid aspirate cannot show.
38221 sits in the Surgery section of CPT, within the hemic and lymphatic systems codes (38100-38999). Since January 1, 2018, it has been one of three diagnostic bone marrow codes. 38220 covers aspiration, 38221 covers biopsy, and 38222 covers both at the same session.
The deciding question is which specimens the procedure note documents, and from where. A core alone is 38221, and an aspirate alone is 38220. A core and an aspirate from the same site in one session are 38222, reported as a single line. The chart below maps each documentation pattern to its code.
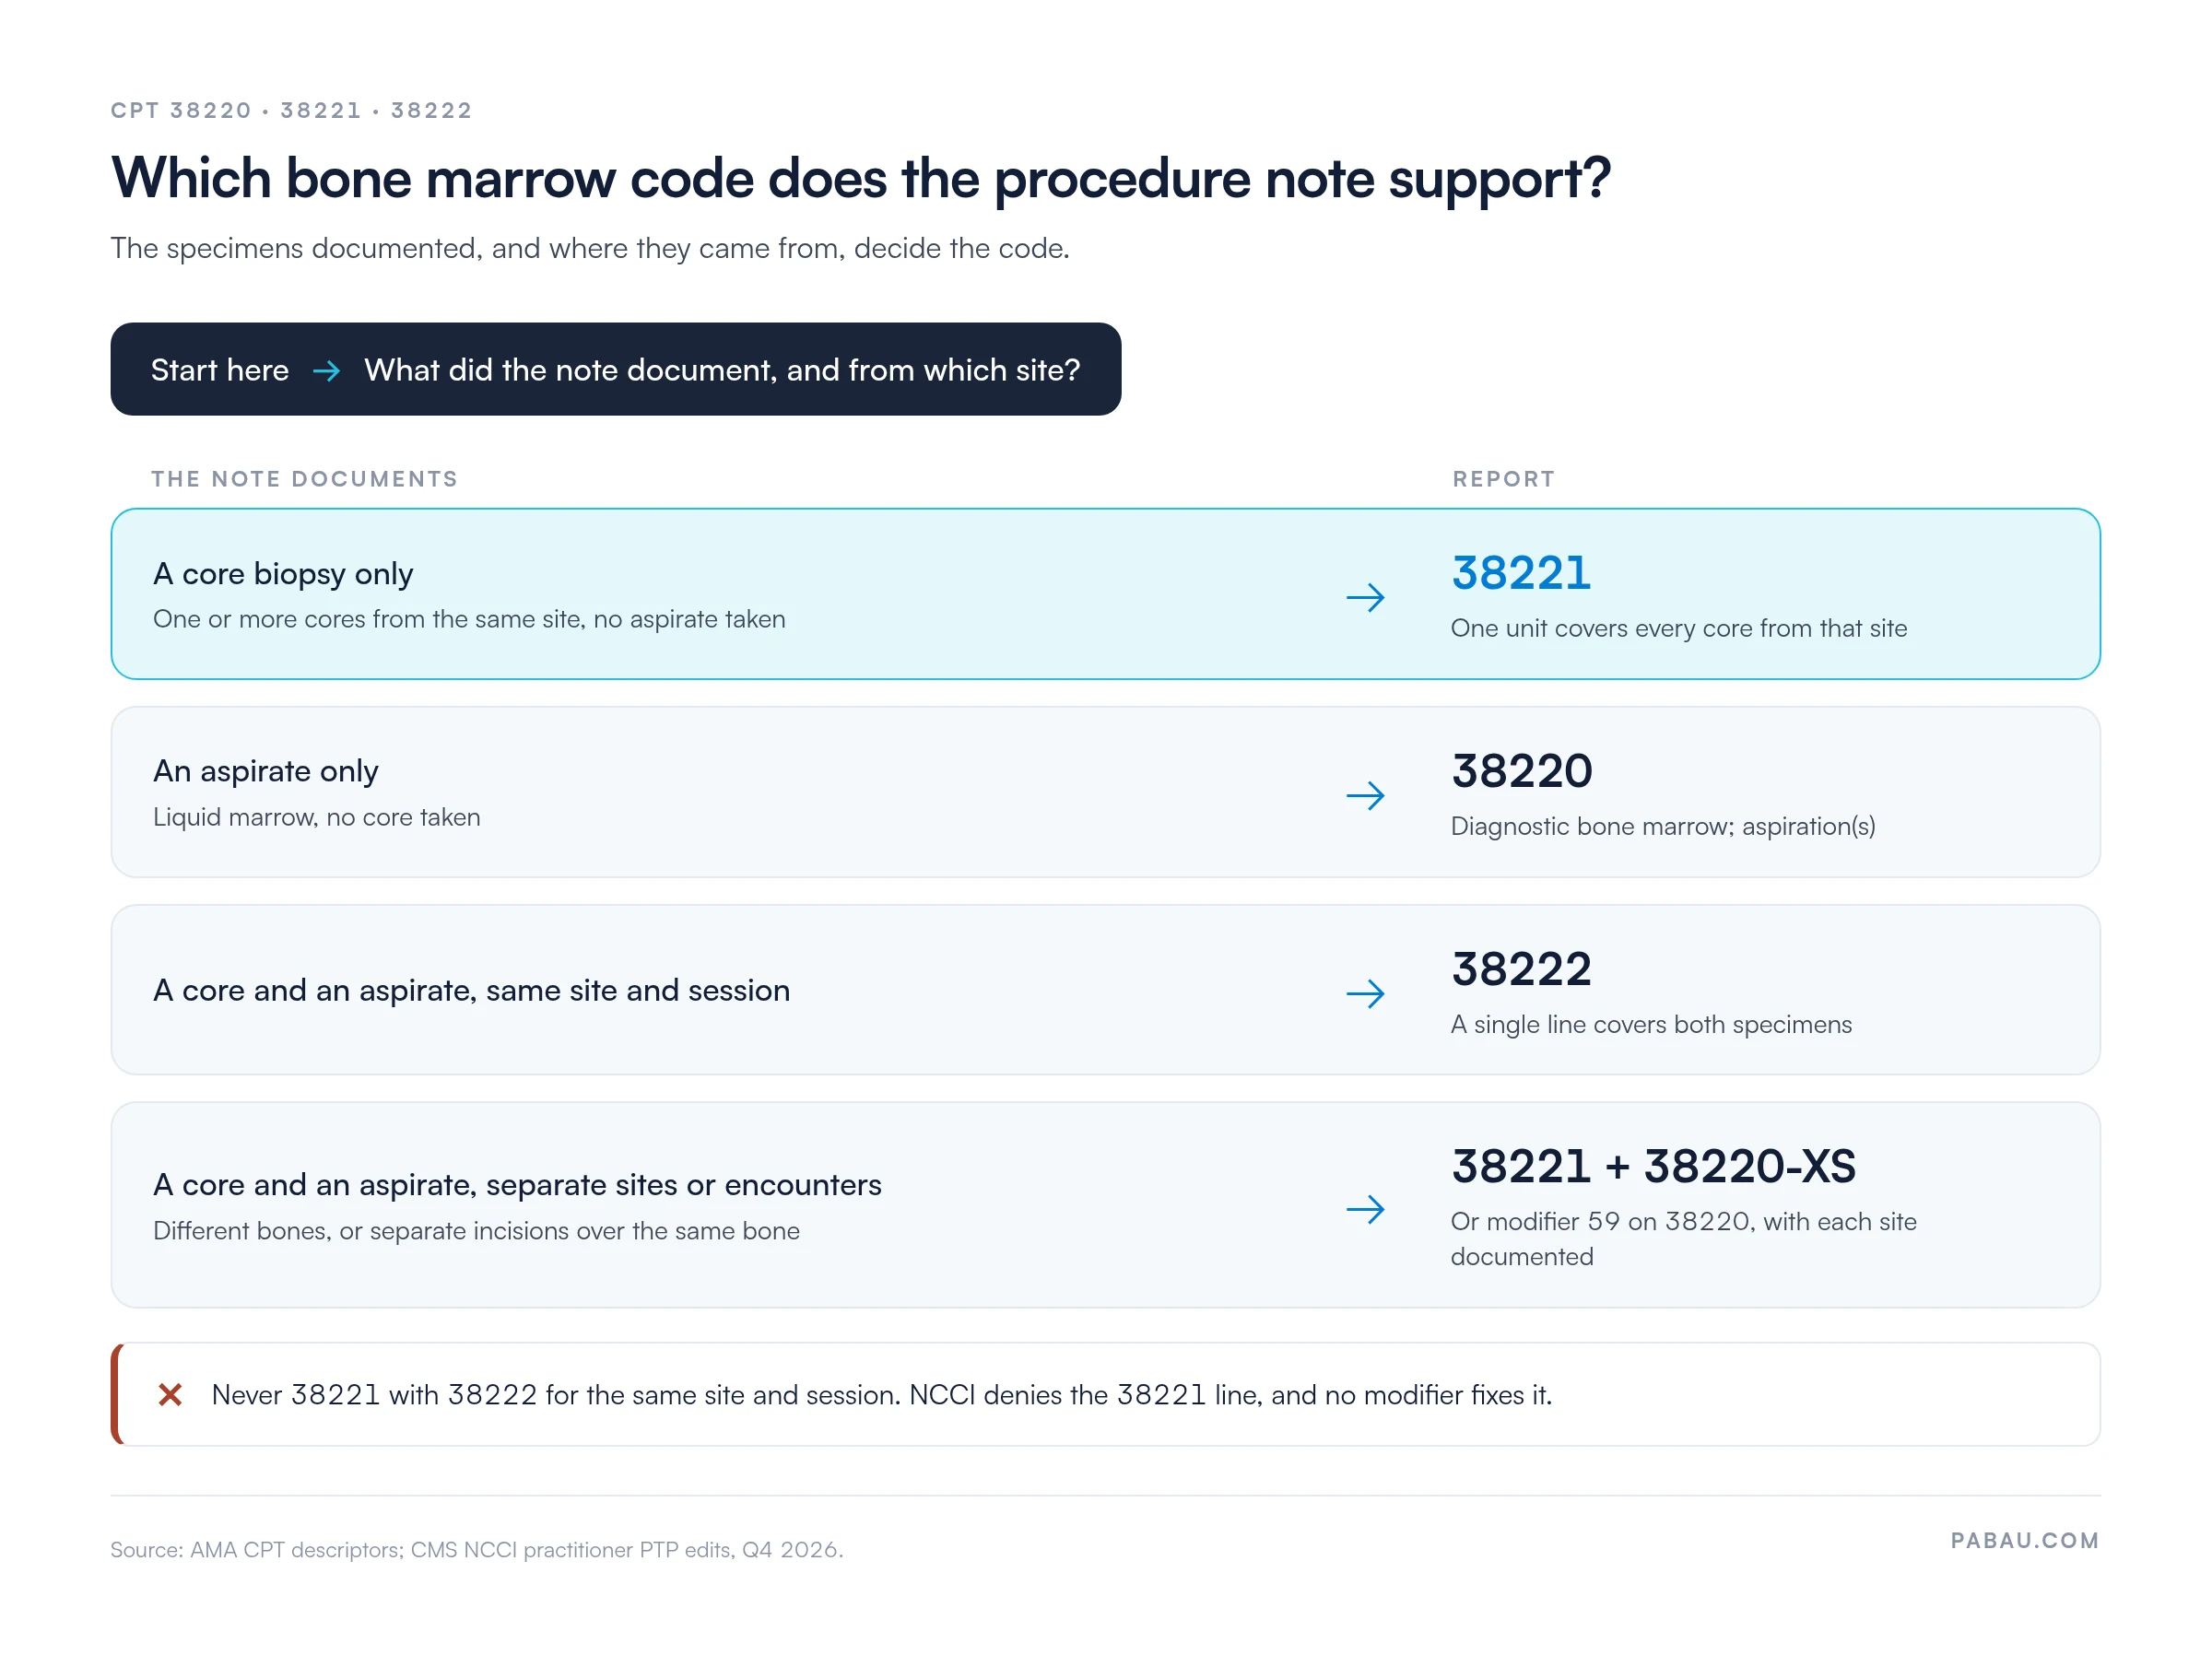
RVUs and global indicators come from the CMS CY2026 Physician Fee Schedule relative value file (July 2026 release). Edit positions come from the Q4 2026 NCCI practitioner procedure-to-procedure (PTP) file, where every pair in this family carries modifier indicator 1.
38221 is not billed with 38222 for the same site and session, because 38222 already includes the biopsy. NCCI lists 38221 as a column 2 code to 38222, so the payer denies the 38221 line. No modifier fixes that claim. The correct coding is 38222 alone.
38220 and 38221 can appear on the same claim only when the aspiration and the biopsy come from separate sites or separate encounters. NCCI treats different bones, or two separate skin incisions over the same bone, as separate sites. Append modifier XS or 59 to 38220, the column 2 code, and document each site.
Record the site and the specimen for each pass, for example: left posterior iliac crest, one core, no aspirate attempted. A note that only says bone marrow procedure performed leaves the coder guessing between 38220, 38221 and 38222.
The performing physician reports 38221 and any imaging guidance they provide. Pathology codes for the core, such as 88305, are reported by whoever interprets it. The AMA’s CPT coding resources explain how add-on codes attach to a primary procedure.
The Q4 2026 NCCI practitioner file carries no PTP edit between 38221 and either 77002 or 77012. NCCI policy still allows one unit of imaging guidance per encounter, however many needle placements are made. Edits change every quarter, so check the current NCCI file before you submit.
Most modifier errors on 38221 come from the aspiration pairing or a same-day visit. The table below maps each modifier to its trigger and the error that causes denials.
CMS created XE, XP, XS and XU as more specific alternatives to modifier 59. For bone marrow procedures at separate sites, XS (separate structure) is the closest match. Some payers still prefer 59, so check the payer’s billing guidelines before you switch.
Medical necessity for CPT code 38221 rests on the ICD-10-CM diagnosis on the claim. A core biopsy is easiest to defend when the clinical question is about marrow cellularity, fibrosis or infiltration. The table lists common pairings and what each one signals to a reviewer.
Using D64.9 alone as the supporting diagnosis raises the risk of a medical necessity denial. If the indication is unexplained cytopenia, document the peripheral blood findings, the prior workup, and why marrow evaluation is the next step. Payers want to see that less invasive tests came first.
A clean claim submission for 38221 depends on a procedure note that meets both AMA documentation standards and the payer’s medical necessity criteria. Reviewers expect to find the elements below.
For medical billing compliance, keep the procedure note separate from the pathology report. One combined document makes it harder for reviewers to confirm that the billing provider performed the biopsy described in 38221.
Prior authorization requirements for CPT 38221 vary by payer, plan type and clinical urgency. No single rule applies, so verify with each payer before scheduling a non-urgent biopsy.
Medicare: Traditional Medicare (Parts A and B) does not require prior authorization for 38221. Medicare Advantage plans follow their own policies and may require it, especially for outpatient settings.
Commercial payers: Many commercial plans require prior authorization for non-urgent bone marrow procedures. The request usually needs the ICD-10 diagnosis, recent CBC and differential results, prior workup, and the hematologist’s clinical summary. Urgent cases such as suspected acute leukemia are often exempt, but the urgency must be documented.
Medicaid: Requirements vary by state. Some Medicaid managed care organizations require prior authorization for all hematology procedures, while others exempt inpatient settings. Check each state plan’s policy directly.
Medicare pays CPT code 38221 under the Medicare Physician Fee Schedule (MPFS). In the CY2026 file, it carries 1.25 work RVUs, 5.00 total RVUs in the office and 1.73 total RVUs in a facility. CY2026 has two conversion factors: $33.4009 for most clinicians and $33.5675 for qualifying APM participants.
That gives a national unadjusted rate of about $167.00 in the office ($167.84 for qualifying APM participants). The facility rate is about $57.78 ($58.07). Your MAC adjusts both for your locality, so check the CMS Physician Fee Schedule lookup tool for your area.
Where the biopsy is performed changes what Medicare pays the physician. The MPFS uses facility and non-facility rates to account for differences in overhead.
Using the wrong POS code is a common administrative denial. A biopsy done in a hospital outpatient department but reported with POS 11 creates a mismatch. Most clearinghouses catch it, but some claims pass through and become a post-payment audit issue.
CMS assigns CPT code 38221 a global indicator of XXX, which means the global surgery concept does not apply. No preoperative or postoperative days are bundled into the payment. Some payers expect modifier 25 on a separately identifiable same-day E/M service. The routine assessment before the biopsy and the check afterward are part of 38221 and are not billed separately.
Most 38221 denials fall into five predictable categories, and knowing them in advance is the fastest way to cut rework. The denial codes in medical billing reference covers the common CARC codes and their corrective actions. Practices with systematic denial management workflows catch these patterns before they turn into write-offs.
Audit your 38220, 38221 and 38222 claims by denial reason each quarter. Repeated bundling denials usually trace back to notes that do not say whether an aspirate was taken. A required aspiration-status field in the note template fixes the problem at the source.
Many hematology billing teams read each procedure note line by line to work out whether a core, an aspirate or both were taken. When the note is vague, the claim waits while someone queries the physician.
In Pabau, the practice management platform we build, treatment note templates can capture the site, the number of cores and the aspiration status. The coder sees which specimens were documented before choosing 38220, 38221 or 38222. Pabau’s claims management software then pulls the details already on the patient record into a pre-filled claim and submits it through Claim.MD.
Eligibility checks run before the appointment, and claim status and remittances come back into the same system. Fewer bone marrow claims go out on the wrong code, so fewer come back for rework.

Pabau keeps procedure notes, eligibility checks and Claim.MD claim submission in one system. Your billing team codes 38221 from a complete note instead of chasing the physician.

CPT 38221 is the right code only when the note documents a core biopsy with no aspirate from the same site. Once an aspirate joins it in the same session, the claim belongs to 38222. An aspirate from a separate site goes on its own line as 38220, with modifier XS or 59.
The practices that avoid rework on these claims fix the note rather than the claim. Make the site and the aspiration status required fields, and the code choice follows from the documentation. Book a demo to see how Pabau keeps bone marrow procedure notes and claims in one place.

Need a reference for what happens when claims are denied? Denial management in healthcare covers the full workflow from identification to appeal resolution.
Want to understand how clearinghouses fit into the revenue cycle? Medical claims clearinghouse explains how electronic claims are routed, validated, and returned to practices.
Looking for the full picture on revenue cycle management? Medical billing fundamentals walks through every stage from patient registration to payment posting.
CPT code 38221 covers a diagnostic bone marrow biopsy, a needle or trocar core taken without an aspirate from the same site. It includes every core from that site, local anesthesia and specimen handling. Imaging guidance and pathology interpretation are reported separately.
38221 is a bone marrow biopsy alone. 38222 is a biopsy plus an aspiration at the same session, reported as one code. If the note documents both specimens from one site, report 38222 and do not add 38221.
CMS assigns CPT code 38221 a global indicator of XXX, so the global surgery concept does not apply and no follow-up days are bundled. Some payers expect modifier 25 on a separately identifiable same-day E/M service.
Yes. Traditional Medicare covers CPT code 38221 when it is medically necessary for the diagnosis on the claim. Typical examples are a suspected hematologic malignancy or unexplained cytopenias. Medicare Advantage plans set their own prior authorization rules.
The bone marrow biopsy CPT code is 38221 when the biopsy is done alone. When a biopsy and an aspiration are done together at the same session, report 38222 instead. An aspiration alone is 38220.



