







HCPCS Code G0151: Physical therapy services in home health
What is HCPCS Code G0151? HCPCS Code G0151 is a G-code in the Level II HCPCS cod...

Last Updated: Oct 1, 2026

A4617 is the HCPCS Level II code for a mouthpiece used with a nebulizer or inhalation device. DMEPOS suppliers bill it as a supply, separately from the nebulizer itself.
Most denials on this code have three causes: the wrong companion equipment code, frequency limits exceeded without documentation, or a missing physician order. The DME Medicare Administrative Contractor (DME MAC) requires that order before approving the supply. Understanding those failure points upfront is faster than reverse-engineering a remittance after the fact.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

HCPCS Code A4617 is the supply code for a nebulizer mouthpiece, billed separately from the nebulizer equipment itself.
Medicare Part B covers A4617 when the beneficiary qualifies for nebulizer therapy under the applicable DME MAC Local Coverage Determination.
A4617 and A7015 (aerosol mask) are not interchangeable, and billing the wrong one for the interface delivered is a common audit trigger.
Billing A4617 alongside A7005 risks unbundling, because the A7005 administration set already includes a mouthpiece.
Checking the interface, replacement date and proof of delivery before submission prevents most A4617 denials.
HCPCS Code A4617 is the Level II code for a mouthpiece, the supply a patient breathes through when a nebulizer or inhalation device delivers medication.
It sits in the A4000-A8999 range for medical and surgical supplies. The Centers for Medicare and Medicaid Services (CMS) maintains it as part of the annual HCPCS Level II update cycle.
The code sits within the broader HCPCS Level II framework that CMS uses to capture services and supplies not described by a CPT code. According to CMS’s HCPCS overview, Level II codes are updated annually. Check the current code file before submitting claims in a new plan year.
A4617 covers a mouthpiece designed for inhalation therapy when delivered via a small volume nebulizer (SVN) or aerosol nebulizer. The device connects the nebulizer cup to the patient’s mouth, allowing the medicated mist to be inhaled directly without a mask.
Within scope:
Excluded from A4617:
The exclusion that causes the most audit problems is the mask-versus-mouthpiece distinction. If the patient uses an aerosol face mask, billing A4617 instead of A7015 misrepresents the item delivered. That holds however minor the difference looks on the claim form. The table below maps each nebulizer item to its code and shows which ones can share a delivery with A4617.
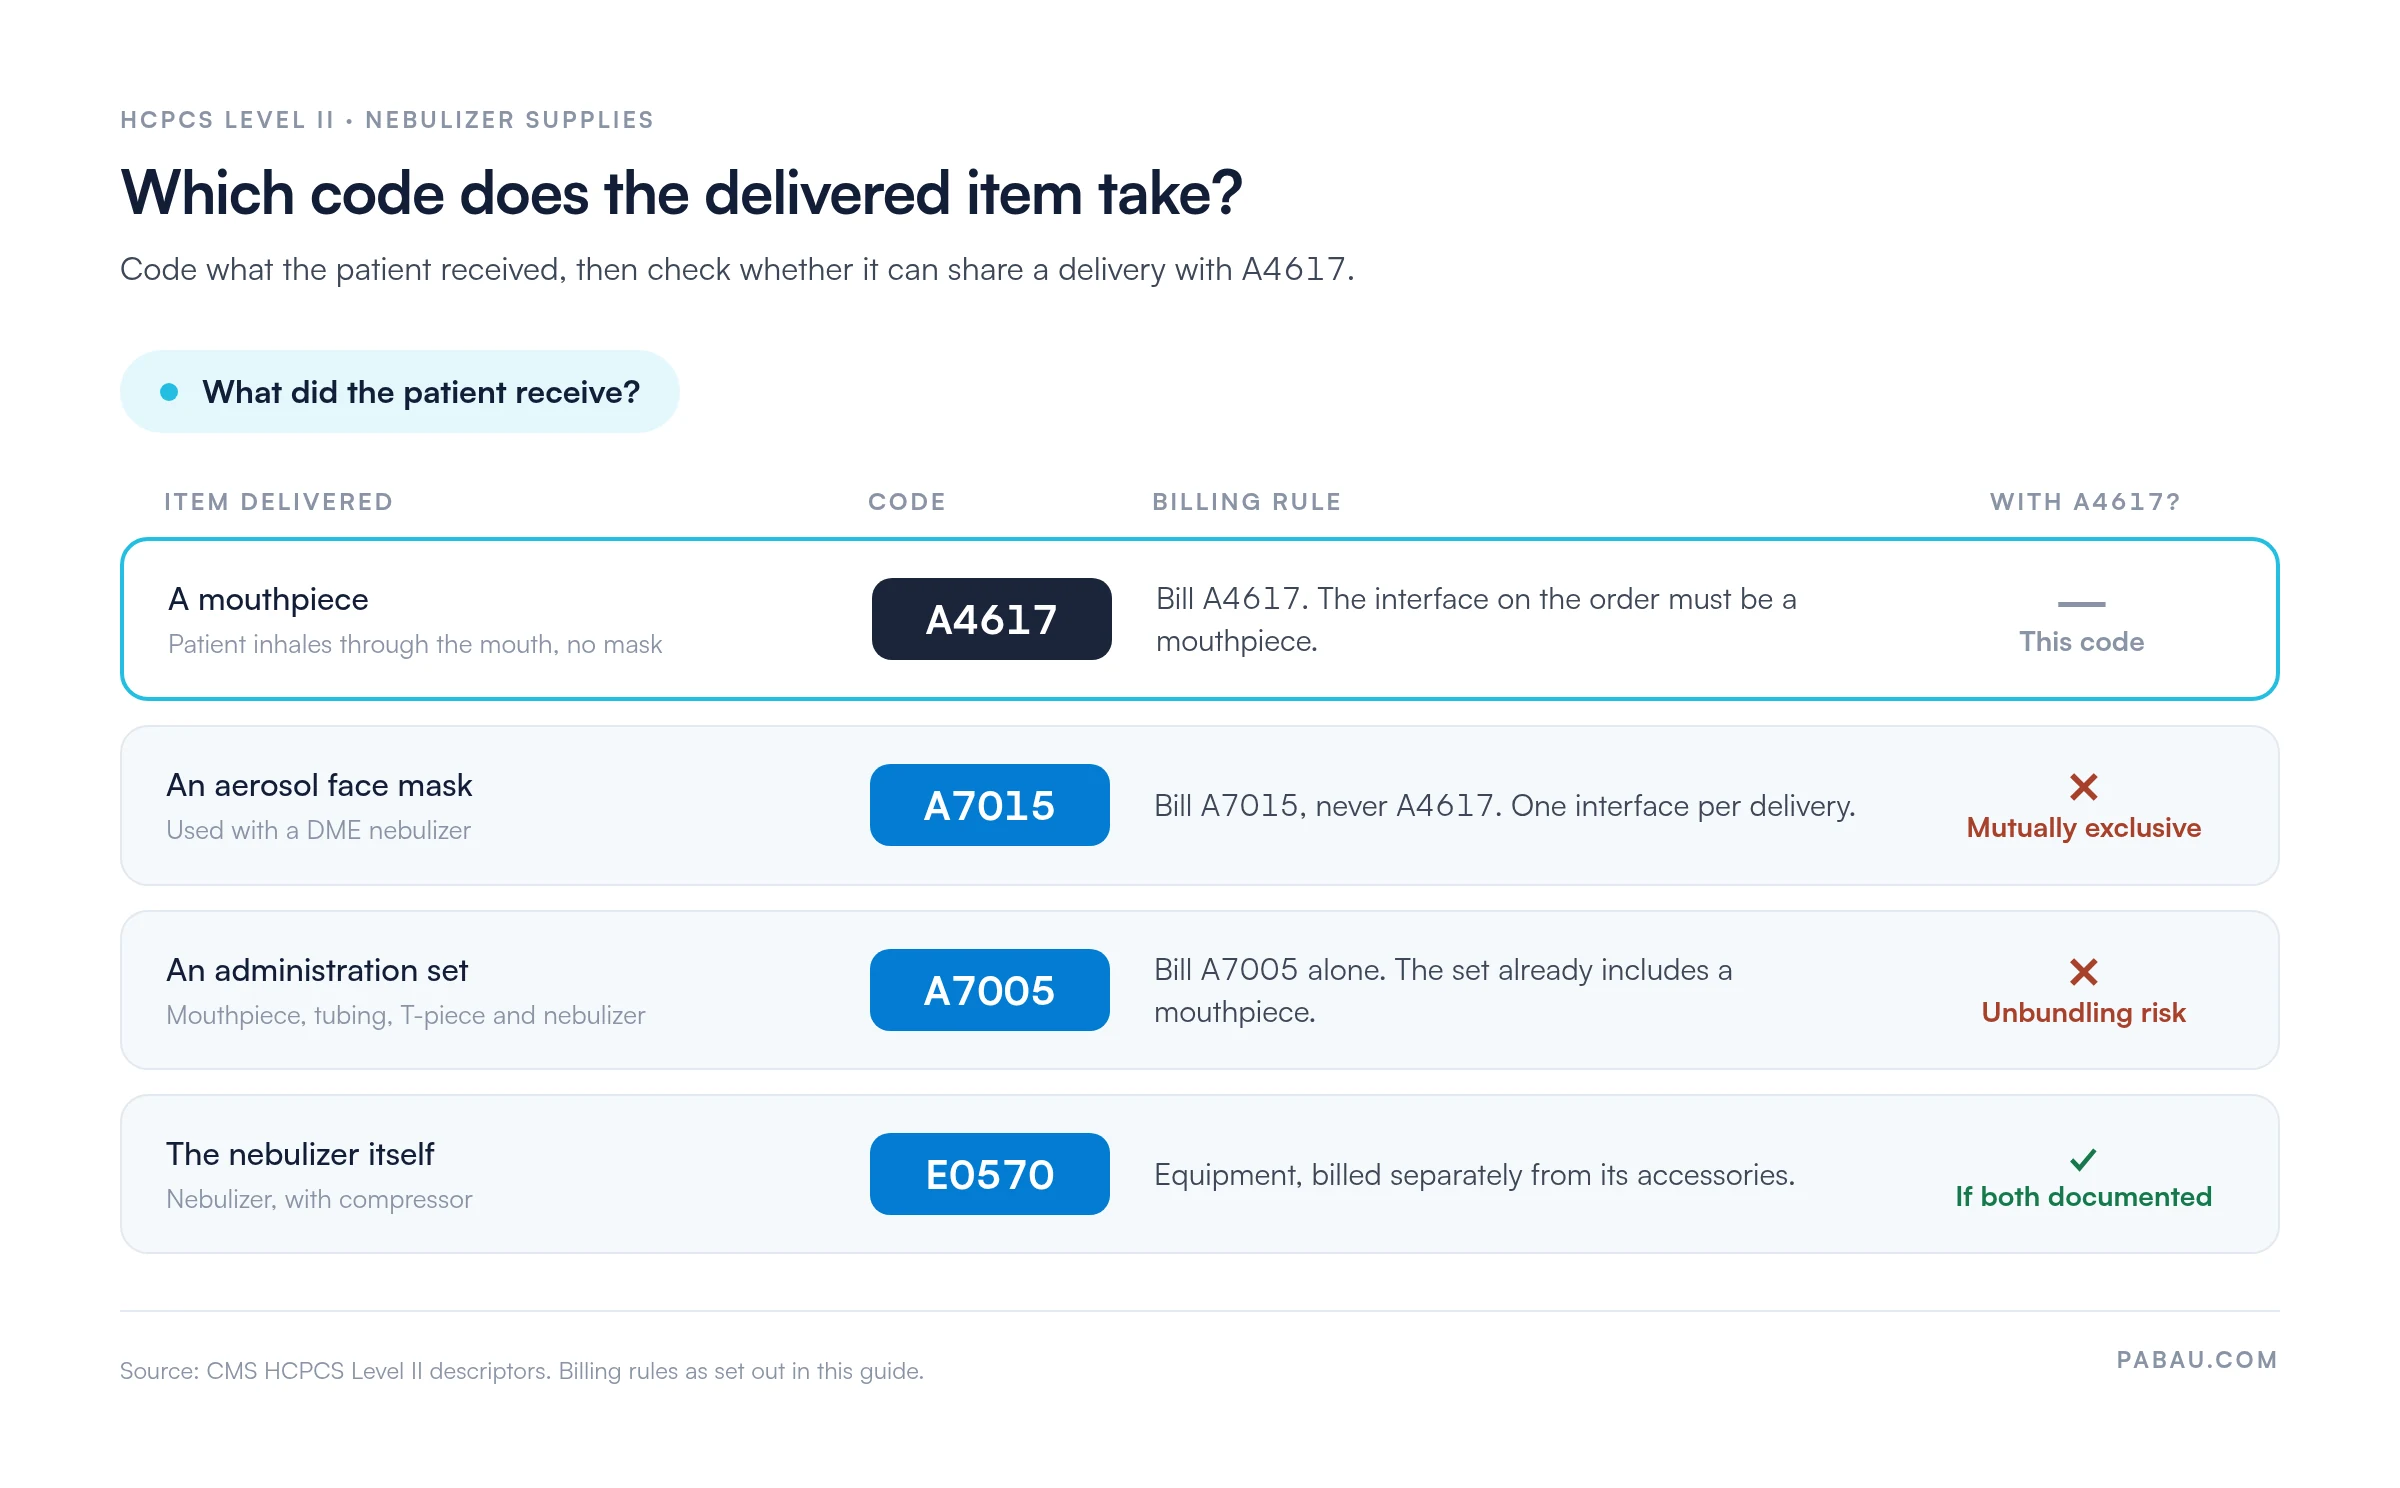
Nebulizer accessory coding uses several overlapping A-codes and E-codes. The table below shows the three codes most commonly confused with A4617, what each covers, and when each is correct.
Billing A4617 on top of A7005 is the bundling error to watch. The two codes look separately billable, but the A7005 set already contains a mouthpiece. DME MAC policy articles for nebulizer supplies often address this combination directly. Check the current article for your jurisdiction before billing both on one claim.
Medicare Part B covers A4617 as a DME supply when the beneficiary has a documented need for nebulizer therapy. That need is judged against the applicable Local Coverage Determination (LCD). The DME MACs that process Medicare DME claims across the four US jurisdictions publish LCDs for nebulizer equipment and supplies. Suppliers must verify which DME MAC holds jurisdiction for the beneficiary’s state before submitting.
Coverage requirements that DME MAC LCDs typically impose for A4617 include:
Run insurance eligibility verification before delivery. If a beneficiary’s Medicare Part B is not active on the date of service, the A4617 claim will deny. Clinical appropriateness doesn’t change that. Suppliers billing commercial plans should also check plan-specific benefit manuals, because coverage for nebulizer accessories varies widely outside Medicare.
A4617 does not have its own standalone CMN form under current CMS policy. However, the companion nebulizer, usually billed as E0570, may require a CMN depending on the DME MAC’s policy article for that jurisdiction. Suppliers should confirm whether a CMN is on file for the companion equipment before billing accessories against it.
Medicare does not currently require prior authorization for A4617 as a standalone supply code. However, CMS’s prior authorization program for certain DMEPOS items evolves, and some commercial plans do impose prior authorization requirements for nebulizer accessories. Verify with the specific payer before delivery when billing under a commercial benefit plan.
Thorough documentation is the primary defense against a DME MAC audit. Solid medical billing compliance practice requires keeping these records on file for each A4617 claim:
A missing or incomplete record in any of these five areas is what DME MAC post-payment audits cite most often for nebulizer supply codes.
CMS and the DME MACs set replacement frequency limits for nebulizer accessories in the LCD and its companion policy article. These limits specify how often a given supply may be furnished and billed to Medicare within a defined period. The exact replacement frequency for A4617 mouthpieces depends on the beneficiary’s DME MAC jurisdiction. Frequencies can change in annual updates, so always consult the current policy article.
General principles that apply to HCPCS supply replacement billing under Medicare DME policy:
Always verify the current replacement frequency in the applicable DME MAC policy article before submitting. A frequency from a prior plan year may no longer apply.
Most A4617 denials fall into five categories. Each has a specific fix that can be addressed at claim creation rather than after a remittance arrives. Effective denial management workflows treat these as pre-submission checkpoints rather than post-payment problems.
Reading the denial codes on the remittance advice tells coders which of these categories triggered a rejection. CO-119 (benefit maximum reached) typically flags frequency issues. CO-4 can flag a modifier or procedure-code inconsistency, and CO-97 (bundled into another service) can flag unbundling. A clean claim submission for A4617 has the correct diagnosis, delivery date, quantity, and interface type aligned before it leaves the billing system.
Run a monthly audit of all A4617 claims submitted in the prior 90 days. Filter by denial code CO-119 (frequency exceeded) and cross-reference your delivery logs. If the same beneficiary appears more than twice, flag the account for a replacement-schedule review before the next order is placed.
Medicare only covers A4617 when the underlying condition qualifies under the applicable DME MAC LCD for nebulizer supplies. The following ICD-10-CM codes appear most frequently on covered claims. Coders should verify against the specific LCD in effect for the beneficiary’s jurisdiction before submission, as covered diagnoses can change with LCD revisions.
Using an ICD-10 code that is not on the LCD’s covered diagnosis list is one of the cleanest ways to generate a non-covered denial. When the treating physician’s records document a covered condition, the claim’s diagnosis code should map precisely to that documentation. Avoid defaulting to an unspecified code.
Wrong interface codes, early replacements and missing documentation can all be caught before submission when the order, diagnosis and claim sit in one place. Integrated claims software for practices keeps those details together, so billing staff check them once instead of across three systems.

Pabau, the practice management and billing platform we build, stores each patient’s insurer and policy on the patient record. Invoices then route to the right payer without re-keying. In the US, Pabau connects to Claim.MD for electronic claim submission and real-time eligibility checks. Claim status and electronic remittance advice (ERA) postings land in the same dashboard.
Before a claim goes out, Pabau runs validation checks to confirm required details such as membership numbers and authorization codes are filled in. The A4617 checks in this guide, such as interface type and replacement date, still belong in your pre-submission review. Because the order, diagnosis and invoice already sit on the patient record, that review doesn’t mean opening a second system.

Pabau keeps insurer details, invoices and claims on the patient record and checks required claim details before each submission. Your billing team fixes errors before the payer sees them.

Code A4617 from the delivery record every time. If the order says mouthpiece and the delivery ticket says mask, correct the order before billing, because the claim must describe the item furnished.
The bigger win comes from moving checks earlier. A replacement date checked at order entry takes seconds, while a CO-119 denial costs a resubmission and, in an audit, a recoupment.
The trade-off is a slightly slower intake for each DME supply order, and it pays back the first time an audit request arrives. Book a demo to see how Pabau keeps claims, invoices and patient records together for your billing team.

Need guidance on reducing claim rejections system-wide? Denial management in healthcare walks through the workflows that catch billing errors before they reach a payer.
Want a cleaner submission process for DME claims? Clean claim best practices covers the pre-submission checklist that reduces first-pass denial rates.
Looking to understand the full billing cycle behind supply codes? What is revenue cycle management explains the end-to-end process from order creation to payment posting.
New to the billing side of DME supplies? What is medical billing walks through the steps a claim takes from charge entry to payment.
HCPCS Code A4617 covers a mouthpiece for use with a nebulizer or inhalation device. It is billed as a DME supply when a patient needs a replacement mouthpiece as part of prescribed aerosol therapy. Masks, tubing and the nebulizer itself have separate HCPCS codes.
Yes. Medicare Part B covers A4617 when the beneficiary qualifies for nebulizer therapy under the applicable DME MAC Local Coverage Determination. The claim needs a physician order, a covered ICD-10-CM diagnosis and proof of delivery. Coverage is not automatic, because the supplier must be enrolled as a DMEPOS supplier and the claim must comply with the active LCD.
A4617 covers a mouthpiece for a nebulizer, while A7015 covers an aerosol mask used with a DME nebulizer. The two codes are mutually exclusive for a single delivery. Bill the interface the patient received, based on the physician order and delivery documentation. Billing A4617 when a mask was delivered misrepresents the item furnished.
The most common reason is a replacement billed before the permitted frequency date. Other frequent causes are a diagnosis missing from the DME MAC’s covered list and no proof of delivery on file. Billing A4617 alongside A7005 also triggers denials, because the administration set already includes a mouthpiece. Each cause can be fixed at claim creation with a pre-submission checklist.
A4617 itself has no standalone CMN requirement under current CMS policy. However, the companion nebulizer equipment code, such as E0570, may require a CMN depending on the DME MAC jurisdiction’s policy article. Confirm whether a CMN is on file for the companion equipment before submitting accessory claims against it.
Yes. A4617 and E0570 are separately billable when both are provided and each is documented. E0570 covers the nebulizer with compressor, and A4617 covers the mouthpiece accessory. Unlike the A4617 and A7005 pairing, billing the equipment and the mouthpiece separately creates no unbundling risk when each item is documented as furnished.





