

CPT Code 69610: Tympanic membrane patch repair (myringoplasty)
CPT code 69610: official descriptor and procedure overview CPT code 69610 descri...

Last Updated: Oct 19, 2026
G7100 is the CCSD code for bypass of ileum. The surgeon joins healthy bowel above a blocked or diseased stretch of ileum to bowel below it. Intestinal contents then flow around the segment, which stays in place.
That detail decides the claim. If the segment is removed, the operation is a resection and G7100 is the wrong code. The code sits in section 11.4.0 (jejunum/ileum) of the CCSD schedule, and several small bowel codes can't be billed with it. Insurers expect pre-authorization and an operation note that explains why the surgeon chose a bypass.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD code G7100 reports bypass of ileum, where the surgeon routes bowel contents around an ileal segment that stays in place.
If the surgeon removes the segment, the operation is a resection, and G7100 is the wrong code.
CCSD bars G7100 from the same claim as several neighboring codes, including G6100, G6080, G7250 and G7402.
CCSD maintains the code and its descriptor, while each insurer sets its own fee for it.
Pabau’s claims management software pre-fills each claim from the invoice and flags missing details, such as the authorization code, before you submit.
CCSD code G7100 is the private billing code for bypass of ileum, a small bowel operation. The surgeon joins healthy bowel above a problem stretch of ileum to healthy bowel below it. Intestinal contents then flow around that stretch, which stays in the abdomen.
That last detail decides the claim. If the segment comes out, the operation is a resection, and G7100 no longer fits.
The code belongs to the schedule kept by the Clinical Coding and Schedule Development (CCSD) Group. UK private medical insurers use that schedule to recognize procedures on consultant and hospital invoices. Our guide to CCSD codes explains how it works.
The descriptor covers the ileum only. A bypass of the jejunum, the upper part of the small bowel, takes its own code, G6100.
An ileal bypass relieves a blockage without cutting out the diseased bowel. Surgeons usually choose it when resection would carry more risk than leaving the segment in place.
Typical reasons recorded in the indication include:
Partial ileal bypass was once used to lower cholesterol. Drug treatment has since replaced it, so a G7100 claim with a lipid diagnosis will draw questions from the insurer.
Insurers read the operation note to confirm the code matches the surgery. For G7100, one question matters most. Did the surgeon bypass the ileal segment, or remove it?
A note that supports a clean claim records:
Watch for any mention of a specimen sent to pathology. A removed segment points to a resection, so query the surgeon before you code. Otherwise the pathology report will contradict the G7100 claim.
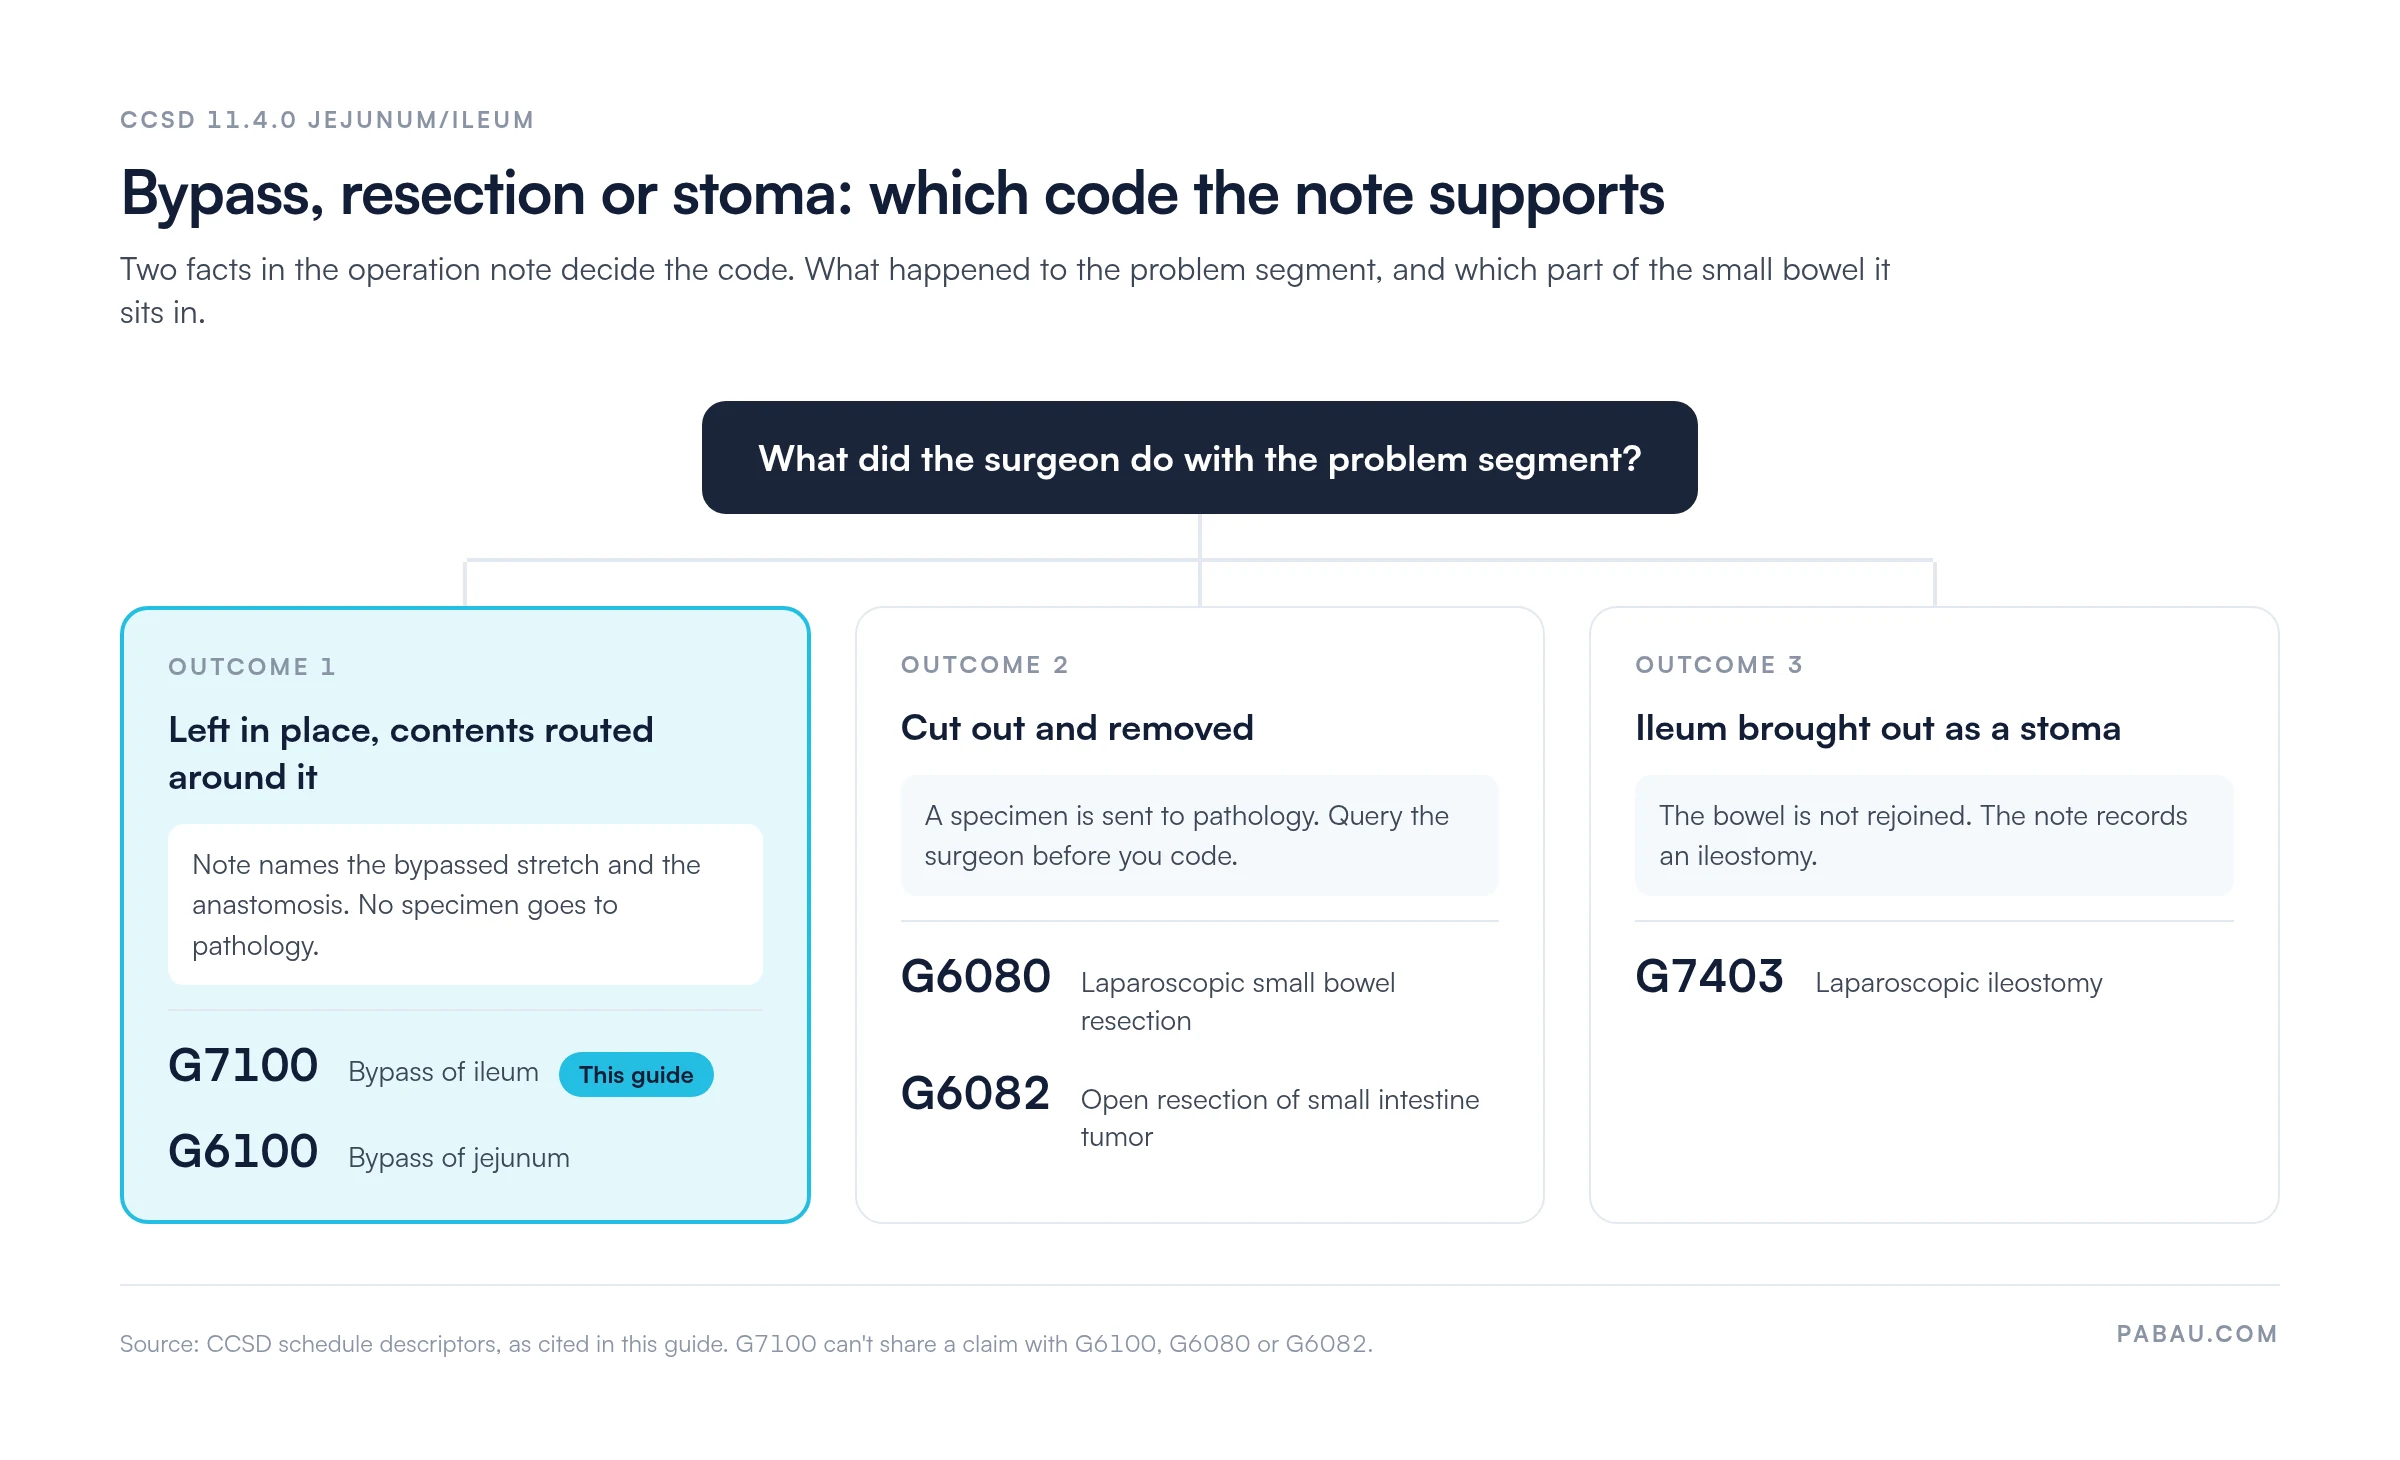
The code turns on two facts in the note. One is what happened to the segment, and the other is where it sits. The diagram below maps each outcome to its code.
CCSD lists the codes below as unacceptable combinations with G7100. Each one either overlaps the bypass or describes a different operation on the same bowel.
Read the operation note before choosing between these codes. A keyhole resection under G6080 can look like a bypass in a short theater summary. A laparoscopic ileostomy also has its own code, G7403.
One ileal bypass admission produces several invoices. Each one follows the same path to the insurer.
Each invoice should quote the same procedure date and pre-authorization number. One mismatched detail can hold up every claim for the admission. Insurers also decide case by case whether they pay an assistant, so check that rule first.
Insurers treat ileal bypass as inpatient surgery, so the consultant should secure pre-authorization before booking theater time. Each treatment episode needs its own reference. Never reuse one from an earlier claim.
Emergency cases are the exception. When a patient needs surgery the same day, notify the insurer as soon as possible afterward. Rules differ by payer and policy year, so check each insurer’s current position. Our guide to Bupa CCSD codes covers one large insurer’s approach.
If the plan changes during surgery, contact the insurer. Approval for a resection does not cover a bypass, and approval for a bypass does not cover a resection.
Every G7100 claim needs an ICD-10 diagnosis that explains why the bowel was bypassed. These diagnoses commonly fit the operation:
Code the diagnosis the operation note supports. A vague obstruction code on a planned tumor bypass invites a query.
Each error below can stall a G7100 claim. Each one also has a fix your team can apply before resubmitting.
Run through this checklist before the invoice leaves your practice:
Surgical billing often means retyping details from the operation note into an insurer invoice. Each retyped field is a chance for a wrong date or a missing authorization code.
Pabau, the practice management platform we build for private practices, keeps the note, the patient record and the claim together. Its claims management software pre-fills each claim from the invoice. It also checks each claim for missing or invalid details before you submit.
Through the Healthcode integration, your team submits CCSD claims and tracks their status without leaving Pabau.
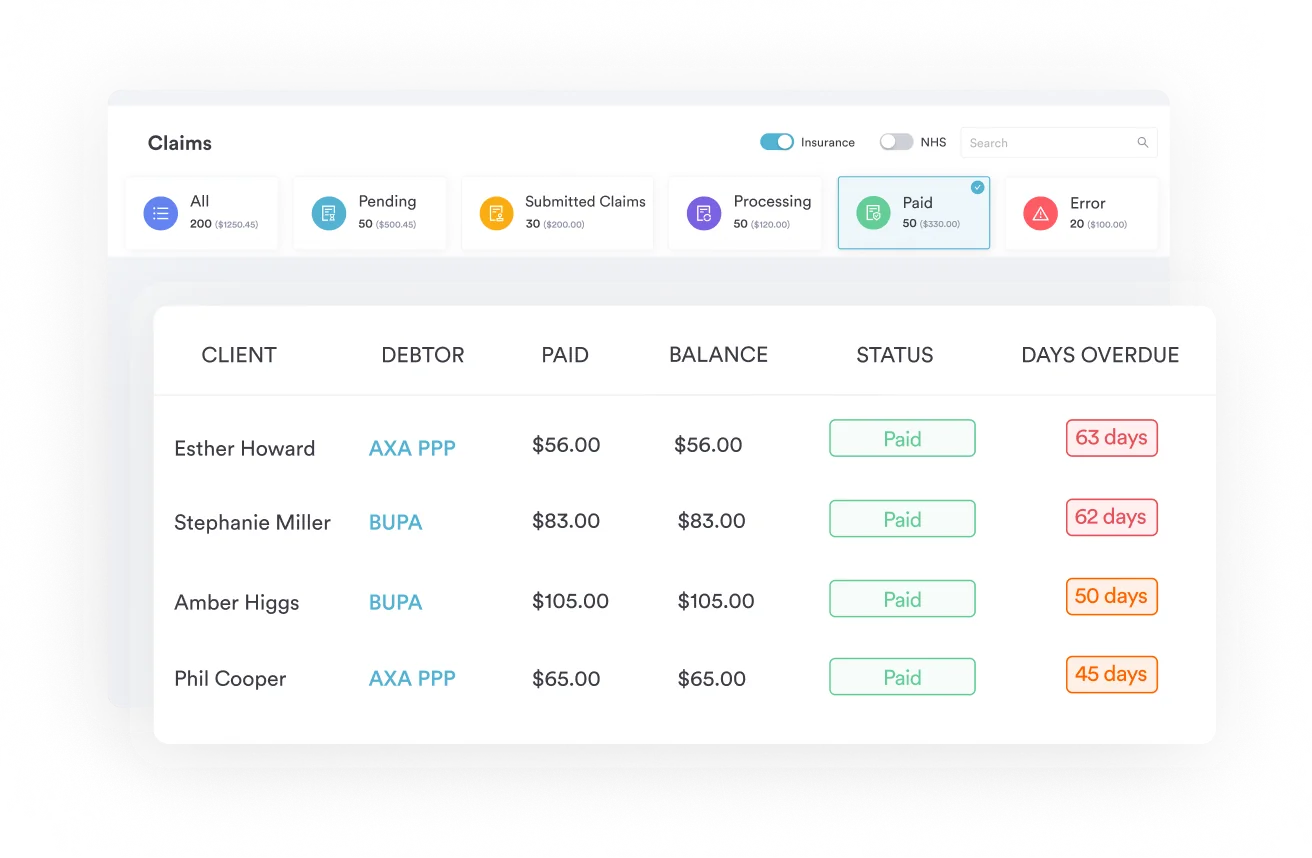

Pabau pre-fills CCSD claims from the invoice and checks required fields before sending them through Healthcode. Your team spends less time correcting rejected surgical invoices.

A G7100 claim rests on a single sentence in the operation note. The ileal segment stayed in place. With that written down, the code choice, the pre-authorization and the combination checks all fall into line.
So read the note before you pick the code, and query any mention of a specimen. Then match every invoice for the admission to the same date and authorization number. Book a demo to see how Pabau keeps private surgical claims accurate from the note to Healthcode.

Was the jejunum bypassed instead? CCSD code G6100 covers bypass of jejunum and what its operation note must show.
Billing the keyhole alternative? CCSD code G6080 explains laparoscopic small bowel resection and how it differs from a bypass.
Was a stoma formed? CCSD code G7403 covers laparoscopic ileostomy billing.
Working with Bupa patients? Bupa CCSD codes sets out how Bupa uses the CCSD schedule for surgical claims.
New to private surgical coding? CCSD codes explained walks through how the schedule is structured and maintained.
CCSD code G7100 covers bypass of ileum. The surgeon joins bowel above a problem stretch of ileum to bowel below it. The bypassed segment stays in place.
Both codes describe a small bowel bypass. G7100 covers the ileum and G6100 covers the jejunum. CCSD does not allow the two codes on the same claim.
CCSD lists G6100, G6080, G6082, G6083, G7250 and G7402 among the unacceptable combinations with G7100. Remove any of them from the claim before submission.
No. CCSD maintains the codes and their descriptors, and each insurer sets its own fee. Check the payer’s current fee schedule before you invoice.
No. An ileostomy brings the ileum out as a stoma, which is a different operation. Open formation of ileostomy is G7402, and a laparoscopic ileostomy is G7403.
CCSD added G7100 to its schedule on 20 January 2010. Check the current schedule before billing, because descriptors and combination rules can change.




