

HCPCS Code E0272: Foam rubber mattress billing guide
HCPCS Code E0272: official descriptor and code overview HCPCS Code E0272 is the ...

Last Updated: Nov 6, 2026
E5702 is the CCSD code for thoracotomy lung volume reduction – unilateral. It covers open surgery through a thoracotomy to remove the most damaged, over-inflated emphysematous tissue from one lung.
Open surgery on both lungs is coded E5700. Thoracoscopic (VATS) lung volume reduction has its own codes, E5592 for one side and E5593 for both. E5702 cannot be claimed with T0320, exploratory thoracotomy.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

E5702 is the CCSD code for open thoracotomy lung volume reduction on one side, used for UK private insurer billing.
Bilateral open surgery is E5700, while thoracoscopic (VATS) lung volume reduction is E5592 for one side and E5593 for both.
The CCSD schedule lists E5702 as an unacceptable combination with exploratory thoracotomy, T0320, so the access incision is never claimed separately.
CCSD sets the codes, not the fees, so check each insurer’s own fee schedule and get pre-authorisation before surgery.
Practice software such as Pabau keeps the authorisation reference, operative note and Healthcode claim together, so the claim matches the approved procedure.
CCSD Code E5702 is the UK private healthcare code for open lung volume reduction surgery on one lung. The official descriptor reads: Thoracotomy lung volume reduction – unilateral. The code was added to the schedule on 20 January 2010.
The CCSD Group (Clinical Coding and Schedule Development) maintains the schedule for UK private medical insurers, including Bupa, AXA Health, Aviva, Vitality and WPA. CCSD defines the codes and their rules but sets no fees. Each insurer applies its own fee schedule to the code.
E5702 sits in Chapter 8 (Thorax and intra-thoracic organs). Two words in the descriptor decide whether it is the right code: thoracotomy, meaning open surgery, and unilateral, meaning one lung. For the wider coding rules, see the guide to CCSD codes.
The CCSD schedule codes lung volume reduction on two axes: the surgical approach and the number of sides treated. That gives four codes in total.
When both lungs are treated in the same operation through open surgery, the claim uses E5700, not two lines of E5702. When the operative note describes port incisions and a thoracoscope, the case belongs under E5592 or E5593. A planned VATS case converted to open surgery should be coded from what the operative note records, as the grid below sets out.
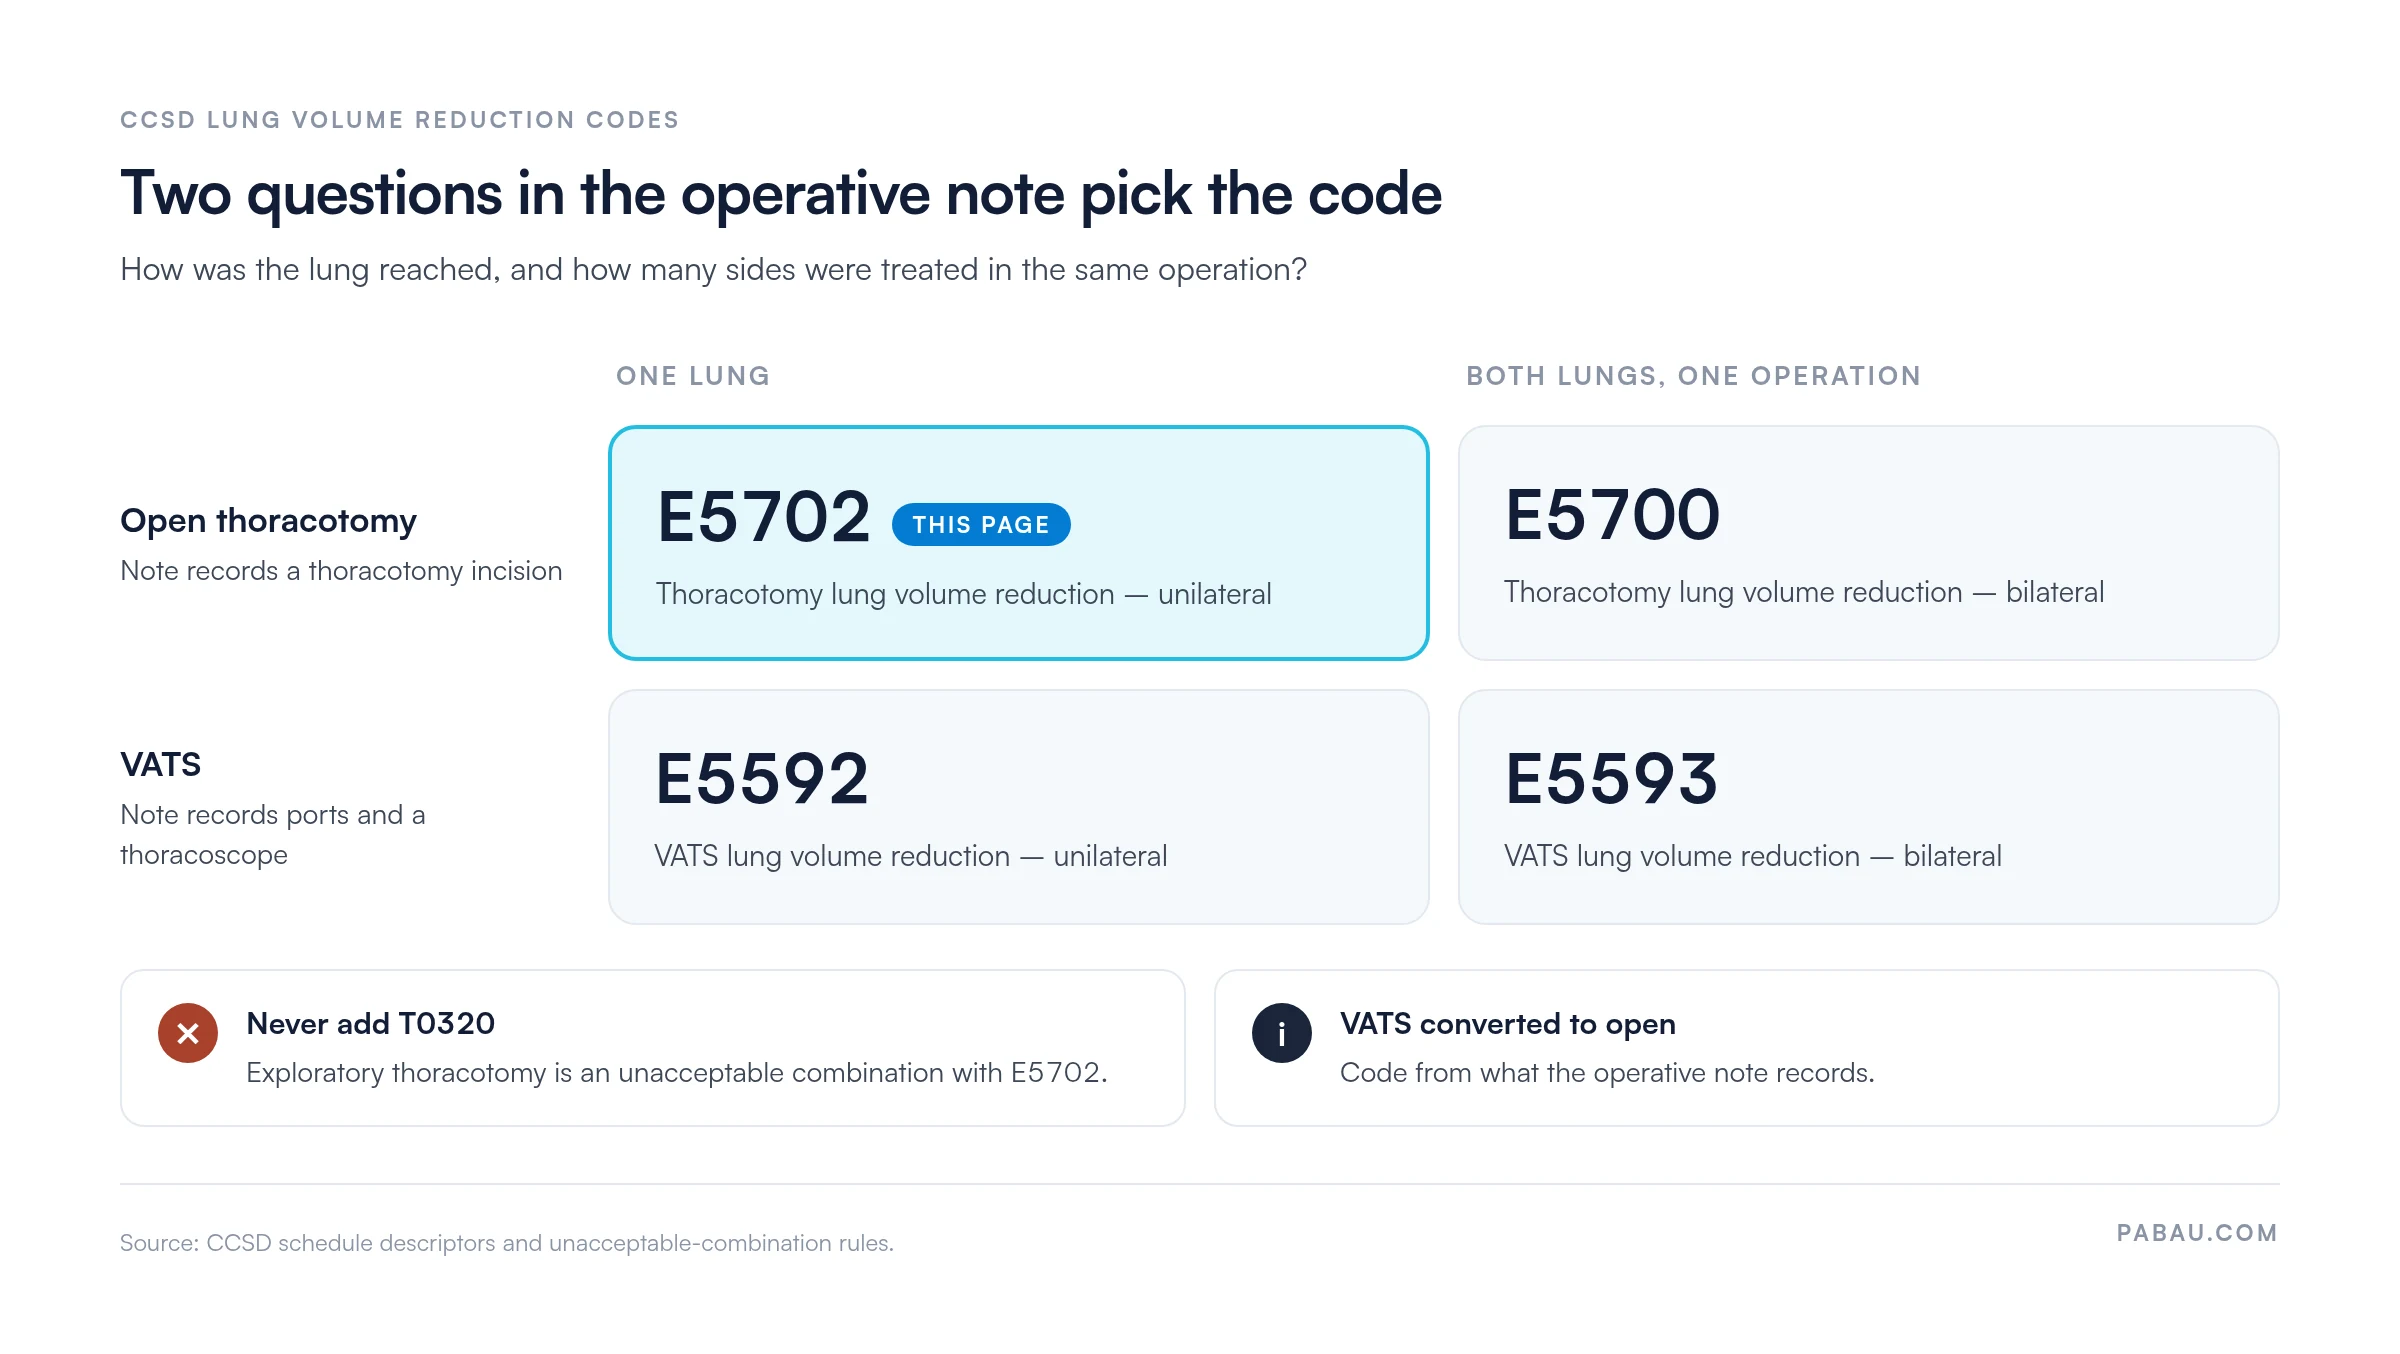
The schedule also lists E5702 as an unacceptable combination with T0320, exploratory thoracotomy. The thoracotomy is the access route for E5702, so it is never billed as a second procedure. If both sides are treated in separate admissions, confirm the coding with the insurer before the second operation.
Lung volume reduction surgery removes the most damaged, over-inflated areas of an emphysematous lung. The remaining tissue can then expand, and the diaphragm can return to a more effective position. Under E5702, the surgeon reaches one lung through a thoracotomy incision rather than through thoracoscopic ports.
The operative note should record each step that supports the code:
An operative note that describes port placement instead of a thoracotomy does not support E5702. Insurers compare the note with the claim on audit, so the approach and side need to be stated in words.
In the UK, the NICE guideline on COPD (NG115) sets out who should be referred for a lung volume reduction assessment. Most surgical thresholds come from the National Emphysema Treatment Trial (NETT). Fishman et al. published its results in the New England Journal of Medicine in 2003.
Insurers judge each pre-authorisation request against their own clinical criteria, which can differ from these thresholds. Send the full lung function report rather than a summary letter, because reviewers check the raw values.
State the planned approach and side in the request for pre-authorisation. Insurers authorise a specific code, so an E5702 approval will not cover a bilateral or VATS operation. If the plan changes, update the insurer before surgery.
UK private claims carry an ICD-10 diagnosis code from the WHO classification, the edition the NHS uses. It is not the US ICD-10-CM set. For E5702, the primary diagnosis comes from the emphysema category, J43. Check descriptors in the WHO ICD-10 browser before submission.
Use J43.1 or J43.2 wherever the CT report names the pattern of emphysema. An unspecified code on a high-cost elective claim invites the insurer to ask for the clinical records.
Insurers can ask for any of these records before or after they pay an E5702 claim. Keeping them together in the patient record means the file is complete when the claim goes out.
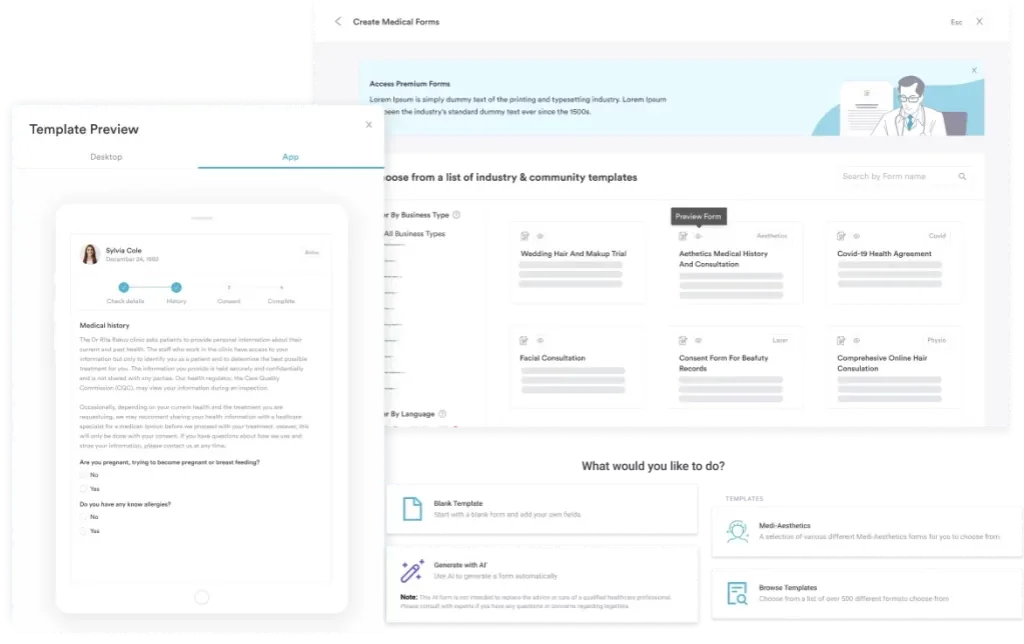
Building the work-up as a digital form means each item is captured in a fixed field.
UK private medical insurers expect pre-authorisation for elective major thoracic surgery such as E5702. A claim sent without a valid authorisation reference is very likely to be rejected. Each insurer publishes its own process, so check the current provider guidance before every request. For Bupa cases, the Bupa CCSD codes guide shows how to look up the code before you ask for approval.
Most requests need the same core evidence:
Some policies exclude or limit cover for certain conditions or procedures. Confirm the patient’s cover with the insurer at the same time as the authorisation.
CCSD has no two-character modifiers of the kind used in US billing. Laterality and approach are written into the code itself, which is why E5702, E5700, E5592 and E5593 exist as separate codes.
Lung volume reduction is a high-cost elective operation, so insurers review E5702 claims closely. Most denials trace back to a mismatch between the claim and the records.
Healthcode is the main electronic clearing house for UK private healthcare claims. Most CCSD claims to the large UK insurers pass through it.
An E5702 claim relies on three records agreeing: the authorisation, the operative note and the claim. When those live in email, insurer portals and spreadsheets, a claim can leave with the wrong code or no reference.
Pabau, the practice management platform we build, keeps those records in one patient file. Its claims management software pulls patient, insurer, policy and authorisation details into each claim. Validation checks flag a missing membership number or authorisation code before the claim is sent.
UK practices submit claims through the Healthcode integration without leaving Pabau. Operative-note templates built in Pabau’s forms prompt the surgeon to record the approach and the side, so the note supports E5702.

Pabau keeps authorisation references, operative notes and claim status together, so E5702 claims leave the practice coded to the right approach and side.

E5702 is the right code only when one lung is reduced through an open thoracotomy. Read the operative note for the approach and the side before anything else on the claim. Both sides in one open operation is E5700, and a thoracoscopic case is E5592 or E5593.
The work that protects the claim happens before surgery. An authorisation for the exact code, and a call to the insurer when the plan changes, take minutes. A denied lung volume reduction claim can take weeks to resolve.
Book a demo to see how Pabau keeps authorisation references, operative notes and claim status together for every CCSD claim your practice submits.

Coding another thoracic procedure under CCSD? CCSD codes collects every CCSD billing guide in one place, chapter by chapter.
Billing the thoracoscopic version on both sides? CCSD code E5593 covers bilateral VATS lung volume reduction and how to claim it.
Treating a pneumothorax through a thoracotomy? CCSD code E5705 explains open pleurectomy and pleurodesis claims.
Submitting to Bupa? Bupa CCSD codes walks through the code lookup for Bupa procedure submissions.
CCSD Code E5702 covers open lung volume reduction surgery on one lung, performed through a thoracotomy. The surgeon removes the most damaged, over-inflated emphysematous tissue. It is part of the CCSD schedule used by UK private medical insurers.
E5702 is open lung volume reduction on one side. E5700 is the same open operation on both sides. When both lungs are treated in one open operation, the claim uses E5700 rather than two lines of E5702.
No. E5702 applies only to the open thoracotomy approach. Thoracoscopic lung volume reduction is coded E5592 for one side and E5593 for both sides. The operative note decides which approach is billed.
No. The CCSD schedule lists T0320 as an unacceptable combination with E5702. The thoracotomy is the access route for the operation, so it is not claimed as a separate procedure.
Most UK insurers want the specialist referral, a full lung function report and a CT report describing the emphysema. They also expect the multidisciplinary team recommendation and the planned code with the side stated. Check each insurer’s current guidance.
No. CCSD maintains the codes and their rules but does not set fees. Each UK insurer applies its own fee schedule to E5702, so check the patient’s insurer before you invoice.




