









Family medical leave form
A family medical leave form is the paperwork employers use to request, certify, ...

Last Updated: Sep 29, 2026

The Puranen-Orava test is a standing pain-provocation test used to diagnose proximal hamstring tendinopathy (PHT) by reproducing the patient’s familiar deep buttock or posterior thigh pain through a loaded hamstring stretch.
According to the Journal of Orthopaedic & Sports Physical Therapy, PHT is consistently under-diagnosed in active adults, with clinicians frequently misclassifying it as a lumbar referral or general hamstring strain.
This guide explains how to perform the puranen-orava test step by step, how to interpret a positive result, and how it fits into a broader clinical assessment battery for sports medicine and physiotherapy practitioners.

The puranen-orava test reproduces pain at the ischial tuberosity to identify proximal hamstring tendinopathy, not general hamstring strain.
A positive result requires pain reproduction at the sit bone during a standing, hip-flexed, knee-extended stretch, not merely discomfort.
Sensitivity values vary by study; always use the test alongside clinical history and at least one other provocation test before concluding.
Pabau’s patient record system and digital assessment forms let physiotherapists log test findings, track outcomes across sessions, and generate SOAP notes automatically.
The puranen-orava test is a standing clinical provocation test developed by Finnish surgeons Puranen and Orava in 1988 to identify pathology at the proximal hamstring tendon insertion on the ischial tuberosity.
It is named after the two authors of the original case series, who observed that applying a stretched load to the hamstring in a weight-bearing position reliably reproduced the sitting pain their athletes reported. The test targets proximal hamstring tendinopathy specifically, distinguishing it from mid-belly strains or referred sciatic pain.
For a deep dive into how physiotherapy clinics can structure their assessment workflows, see our guide on physiotherapy clinic management.
Proximal hamstring tendinopathy is a degenerative condition affecting the common hamstring tendon at its attachment to the ischial tuberosity, the bony prominence you sit on. It differs from an acute hamstring strain, which involves tearing of the muscle belly, and from a complete avulsion, which requires imaging confirmation.
The three hamstring muscles, biceps femoris, semitendinosus, and semimembranosus, all originate at the ischial tuberosity. When compressive and tensile loads repeatedly stress this insertion point, collagen disorganisation develops over time rather than an acute inflammatory response. PHT is most common in:
The hallmark of PHT is pain that worsens with sitting, particularly on hard chairs, and improves with standing or walking. This distinguishes it clinically from lumbar disc pathology, where sustained sitting often brings temporary relief.
Before applying any provocation test, confirm that the patient’s symptom pattern is consistent with PHT. The puranen-orava test is most informative when the following features are present.
If a patient describes sharp radiating pain down the posterior thigh to the calf with paresthesia, consider neurodynamic testing before concluding the source is tendinopathic. The clinical decision rules principle of ruling out red flags first applies equally here: a first presentation of buttock pain in someone over 50 warrants excluding lumbar pathology before labelling it PHT.
The puranen-orava test is performed in a standing, weight-bearing position with the hip loaded into flexion and the knee extended. This creates combined tensile and compressive load at the ischial tuberosity, the mechanical stimulus most likely to reproduce PHT pain.
A positive puranen-orava test requires reproduction of the patient’s familiar pain at the ischial tuberosity, not merely a sense of stretch or mild discomfort. Discomfort during a hamstring stretch is normal in most people; it is the quality and location of the pain that determines clinical significance.
A positive puranen-orava test result indicates that loading the proximal hamstring insertion in a weight-bearing position reproduces the patient’s familiar buttock or posterior thigh pain, which is suggestive of proximal hamstring tendinopathy at the ischial tuberosity. It does not confirm the diagnosis in isolation.
Published psychometric data for the puranen-orava test is limited. Physiotutors and several clinical education sources cite the test as having moderate sensitivity for PHT, meaning it will detect a meaningful proportion of true cases, but a negative result does not confidently rule out the condition. Specificity figures vary between studies, and the research base remains smaller than for commonly used lumbar or shoulder provocation tests.
Cacchio and colleagues have published on PHT provocation test accuracy, and their data should be consulted directly for exact confidence intervals rather than relying on secondary sources. The key clinical implication is that the puranen-orava test performs best as part of a cluster, not in isolation.
The modified bent knee stretch test is a variant of the standard puranen-orava test that alters the knee position to change the tensile load on the proximal hamstring.
In the standard version, the knee is fully extended, placing maximum stretch on all three hamstring muscles simultaneously. The modified bent knee stretch test reduces knee extension, which partially offloads the distal hamstring and shifts more relative stress toward the proximal tendon attachment.
Clinicians use the modified variant when the full straight-leg version cannot be performed because of acute pain, limited hamstring flexibility, or neural tension that confounds the result.
If the patient reports sharp radiating pain down the leg rather than localised ischial tuberosity pain during the standard test, the modified version can help differentiate between a tendinopathic response and a neurodynamic response.
The modified bent knee stretch test is less well-studied than the original, so interpret its results with additional caution and corroborate with palpation findings.
Flag equivocal results in your clinical notes immediately after testing, before you move to treatment. Document the exact pain location, NRS score, and which variant (standard or modified) was used. This protects your clinical reasoning trail if the diagnosis evolves over multiple sessions.
No single test rules in or rules out PHT definitively. The puranen-orava test is most useful when combined with at least one other provocation test and direct palpation. Here is how the four most commonly used hamstring assessment tests compare.
The Askling H-test differs from the puranen-orava test primarily in the dynamic loading mechanism: the patient performs a controlled stiff-leg hip hinge rather than holding a static stretch. Both tests load the proximal hamstring, but the H-test introduces an eccentric component that better mimics the injury mechanism in sprinters.
Use the puranen-orava test first for PHT screening; use the Askling H-test when you suspect an acute proximal strain in an athlete who recently felt a “pop” during sprinting or kicking.
A positive puranen-orava test is suggestive of proximal hamstring tendinopathy, but several other conditions can produce overlapping posterior hip pain. Ruling these out protects both the patient and your clinical reasoning.
For clinicians working within physiotherapy compliance frameworks, documenting your differential reasoning process in clinical notes is not optional. Our overview of physiotherapy clinic compliance covers the documentation standards that apply in most UK and Australian practice settings.
The puranen-orava test belongs in your assessment battery when a patient presents with any combination of deep buttock pain, pain on sitting, and posterior thigh pain that is aggravated by hip-loaded activities. It is appropriate for physiotherapists, sports medicine physicians, and musculoskeletal-trained osteopaths working with athletic or active adult populations.
Use it at the following clinical decision points:
Sports medicine and physiotherapy clinicians using sports medicine software can build PHT assessment templates directly into their intake workflow, ensuring the puranen-orava test is prompted automatically for any patient presenting with posterior hip or buttock pain.

Pabau lets sports medicine and physiotherapy practices document PHT test findings, track outcomes across sessions, and generate clinical notes automatically. See how it works for your clinic.

Consistent documentation of special test results is one of the areas where physiotherapy practices lose the most time. Most clinicians record the puranen-orava test result somewhere in free-text notes, but without a structured field, the finding becomes difficult to retrieve, compare, or hand over to a colleague covering the patient.
A patient record system that supports structured clinical assessment fields allows you to record the test result (positive, negative, equivocal), the NRS pain score, the variant used (standard or modified), and the provocation position.
When the same fields appear at every appointment, progress tracking becomes straightforward: a clinician reviewing session three can immediately compare the week-one and week-six puranen-orava scores without reading through paragraphs of narrative notes.
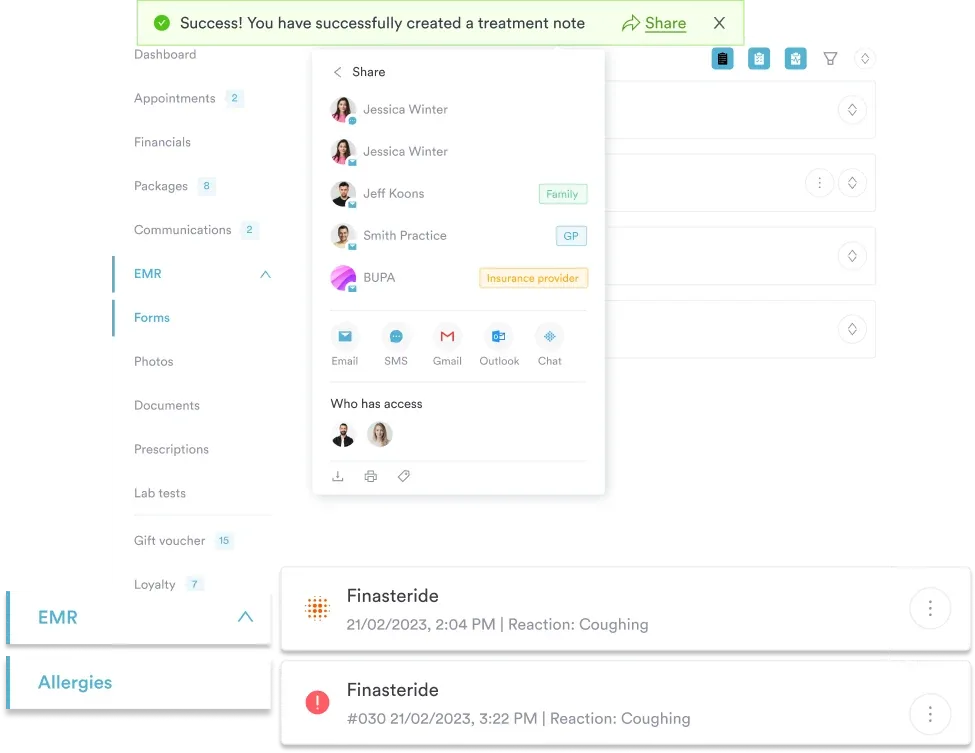
For practices using physical therapy EMR platforms, structured outcome tracking is especially valuable when managing caseloads across multiple practitioners or clinic locations. If a patient’s primary physio is unavailable, a covering clinician can see at a glance whether the provocation test is trending positive or negative across recent sessions.
Two practical documentation habits that reduce risk and improve continuity of care:
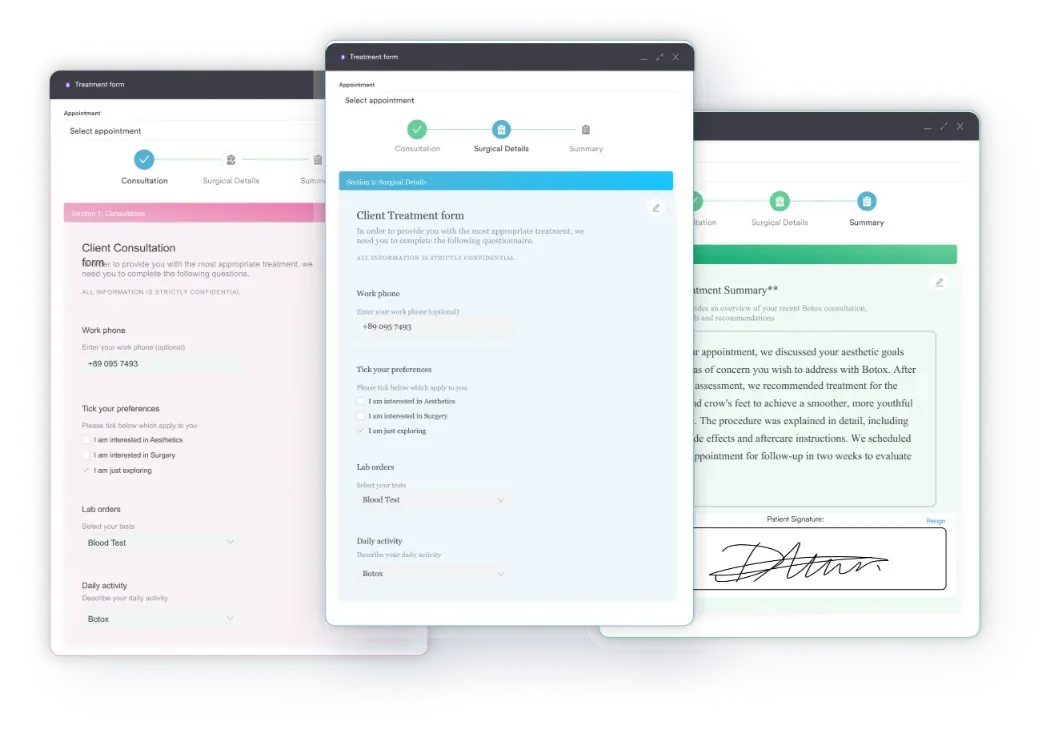
Pabau’s digital assessment forms can be configured with custom fields for special test results, so clinicians never rely on memory or free-text workarounds.
For guidance on reducing documentation errors more broadly, our resource on writing safer clinical notes covers the key principles that apply to MSK assessment records. You can also review the outcome tracking across sessions feature to see how sequential test data is surfaced in the patient timeline.
Proximal hamstring tendinopathy is consistently under-diagnosed, and the puranen-orava test remains the most practical standing provocation test available to clinicians who need to screen for it in a busy outpatient or pitch-side setting.
Used correctly, alongside palpation and at least one other PHT-specific test, it gives you a reliable, reproducible finding you can track across the rehabilitation journey.
Pabau’s structured clinical record and automated workflows make it straightforward to build PHT assessment batteries into your intake process and track test results session by session. If you want to see how it fits your clinic’s workflow, see how Pabau handles this.

The puranen-orava test is a standing pain-provocation test used to identify proximal hamstring tendinopathy by reproducing the patient’s familiar pain at the ischial tuberosity. It is not designed to diagnose general hamstring strains, lumbar referral pain, or neural tension conditions.
A positive result means the patient’s familiar deep buttock or posterior thigh pain was reproduced at the ischial tuberosity during the standing, hip-flexed, knee-extended position. This is suggestive of proximal hamstring tendinopathy but does not confirm the diagnosis without corroborating clinical findings.
The test has moderate sensitivity for PHT based on published data, meaning it detects a meaningful proportion of true cases but may miss some. Specificity data is variable across studies. Always combine it with palpation and at least one other provocation test rather than relying on it alone.
The puranen-orava test uses a static standing stretch with the hip at 90 degrees flexion and knee extended; the Askling H-test uses a dynamic stiff-leg hip hinge that introduces an eccentric load. The H-test is better suited to sprinters with acute proximal strain; the puranen-orava test is the preferred first-line PHT screen in outpatient physiotherapy.
Yes. Repeating the test at 4 to 6 week intervals and recording the NRS pain score and how long the patient holds the position before pain onset gives a measurable outcome metric. A reducing score and longer pain-free hold time indicate improving tendon load tolerance.
No. A positive result is a clinical screening finding, not a surgical indication. The vast majority of proximal hamstring tendinopathy cases are managed successfully with progressive tendon loading rehabilitation. Surgery is rarely considered before 6 to 12 months of correctly structured conservative management.




