


Health appraisal form
A health appraisal form is a record a licensed provider signs to document someon...

2
Last Updated: Oct 13, 2026
Patient scheduling is how a practice books, confirms, reschedules and tracks appointments so every provider, room and device is used without long waits. Good appointment management comes down to two decisions. The first is the scheduling method that fits your visit mix. The second is the automation that keeps those slots filled once patients have booked.
The six methods are time-specified, wave, stream, cluster, open hours and double booking. Most outpatient practices run time-specified scheduling as the default and borrow a second method for the visits that break it. Below, the method-fit matrix matches each method to a practice type. Then come nine best practices that cut no-shows, plus the math on what a no-show costs.

Patient scheduling is the process of booking, confirming, rescheduling and tracking appointments so providers, rooms and equipment stay busy without long waits.
Time-specified scheduling is the most common method, while wave, stream, cluster, open hours and double booking each solve a narrower problem.
The method-fit matrix matches each method to a practice type and shows where it breaks, so you can mix methods by visit type.
In an illustrative example, 20 bookings a day at $150 with a 10% no-show rate loses $300 a day, or $75,000 a year.
Realistic appointment templates, online self-scheduling, reminders, deposits and a waitlist do most of the work of keeping a schedule full.
Review no-show rate, utilization, third next available appointment and lead time every month to see which practice to fix next.
Patient scheduling is the process of booking, confirming, rescheduling and tracking patient appointments so each provider’s time, rooms and equipment are used without long waits.
Patient appointment scheduling covers the whole life of a booking. That runs from the first request and slot choice through confirmation, reminders and check-in, to the reschedule and the follow-up booked at checkout.
Scheduling in healthcare is harder than booking a haircut because one slot has to line up several resources. A Botox appointment needs a prescriber or an injector working under one, a free treatment room, product in stock and a signed consent form. A post-op physical therapy evaluation needs a longer slot and the surgeon’s notes on file.
Manual scheduling, with a paper diary, a phone and a shared spreadsheet, can hold up for a solo practitioner. Once two or more providers share rooms, double bookings and forgotten reminder calls start to creep in. Scheduling software checks provider, room and device availability at the moment of booking, so conflicts are caught before the patient hangs up.
A well-built schedule protects revenue, provider time and the patient’s experience at the same time. Here’s where a weak one costs you:
Take an illustrative practice with 20 bookings a day, an average visit value of $150 and a 10% no-show rate. That’s two empty slots and $300 of lost revenue every day.
These inputs are an example, not an industry benchmark, so swap in your own three numbers. The math gets steeper in aesthetics, where one missed 90-minute laser session can be worth several short consults. That’s why deposits and waitlists, covered below, matter more there than in a practice running 15-minute follow-ups.
There are six main types of scheduling in outpatient care: time-specified, wave, stream, cluster, open hours and double booking. Each one decides how patients arrive across an hour. That’s why most practices pick one as the default and use a second for the visits that break it.
Time-specified scheduling gives each patient a specific appointment time, with slot length set by visit type, and it’s the most common outpatient method.
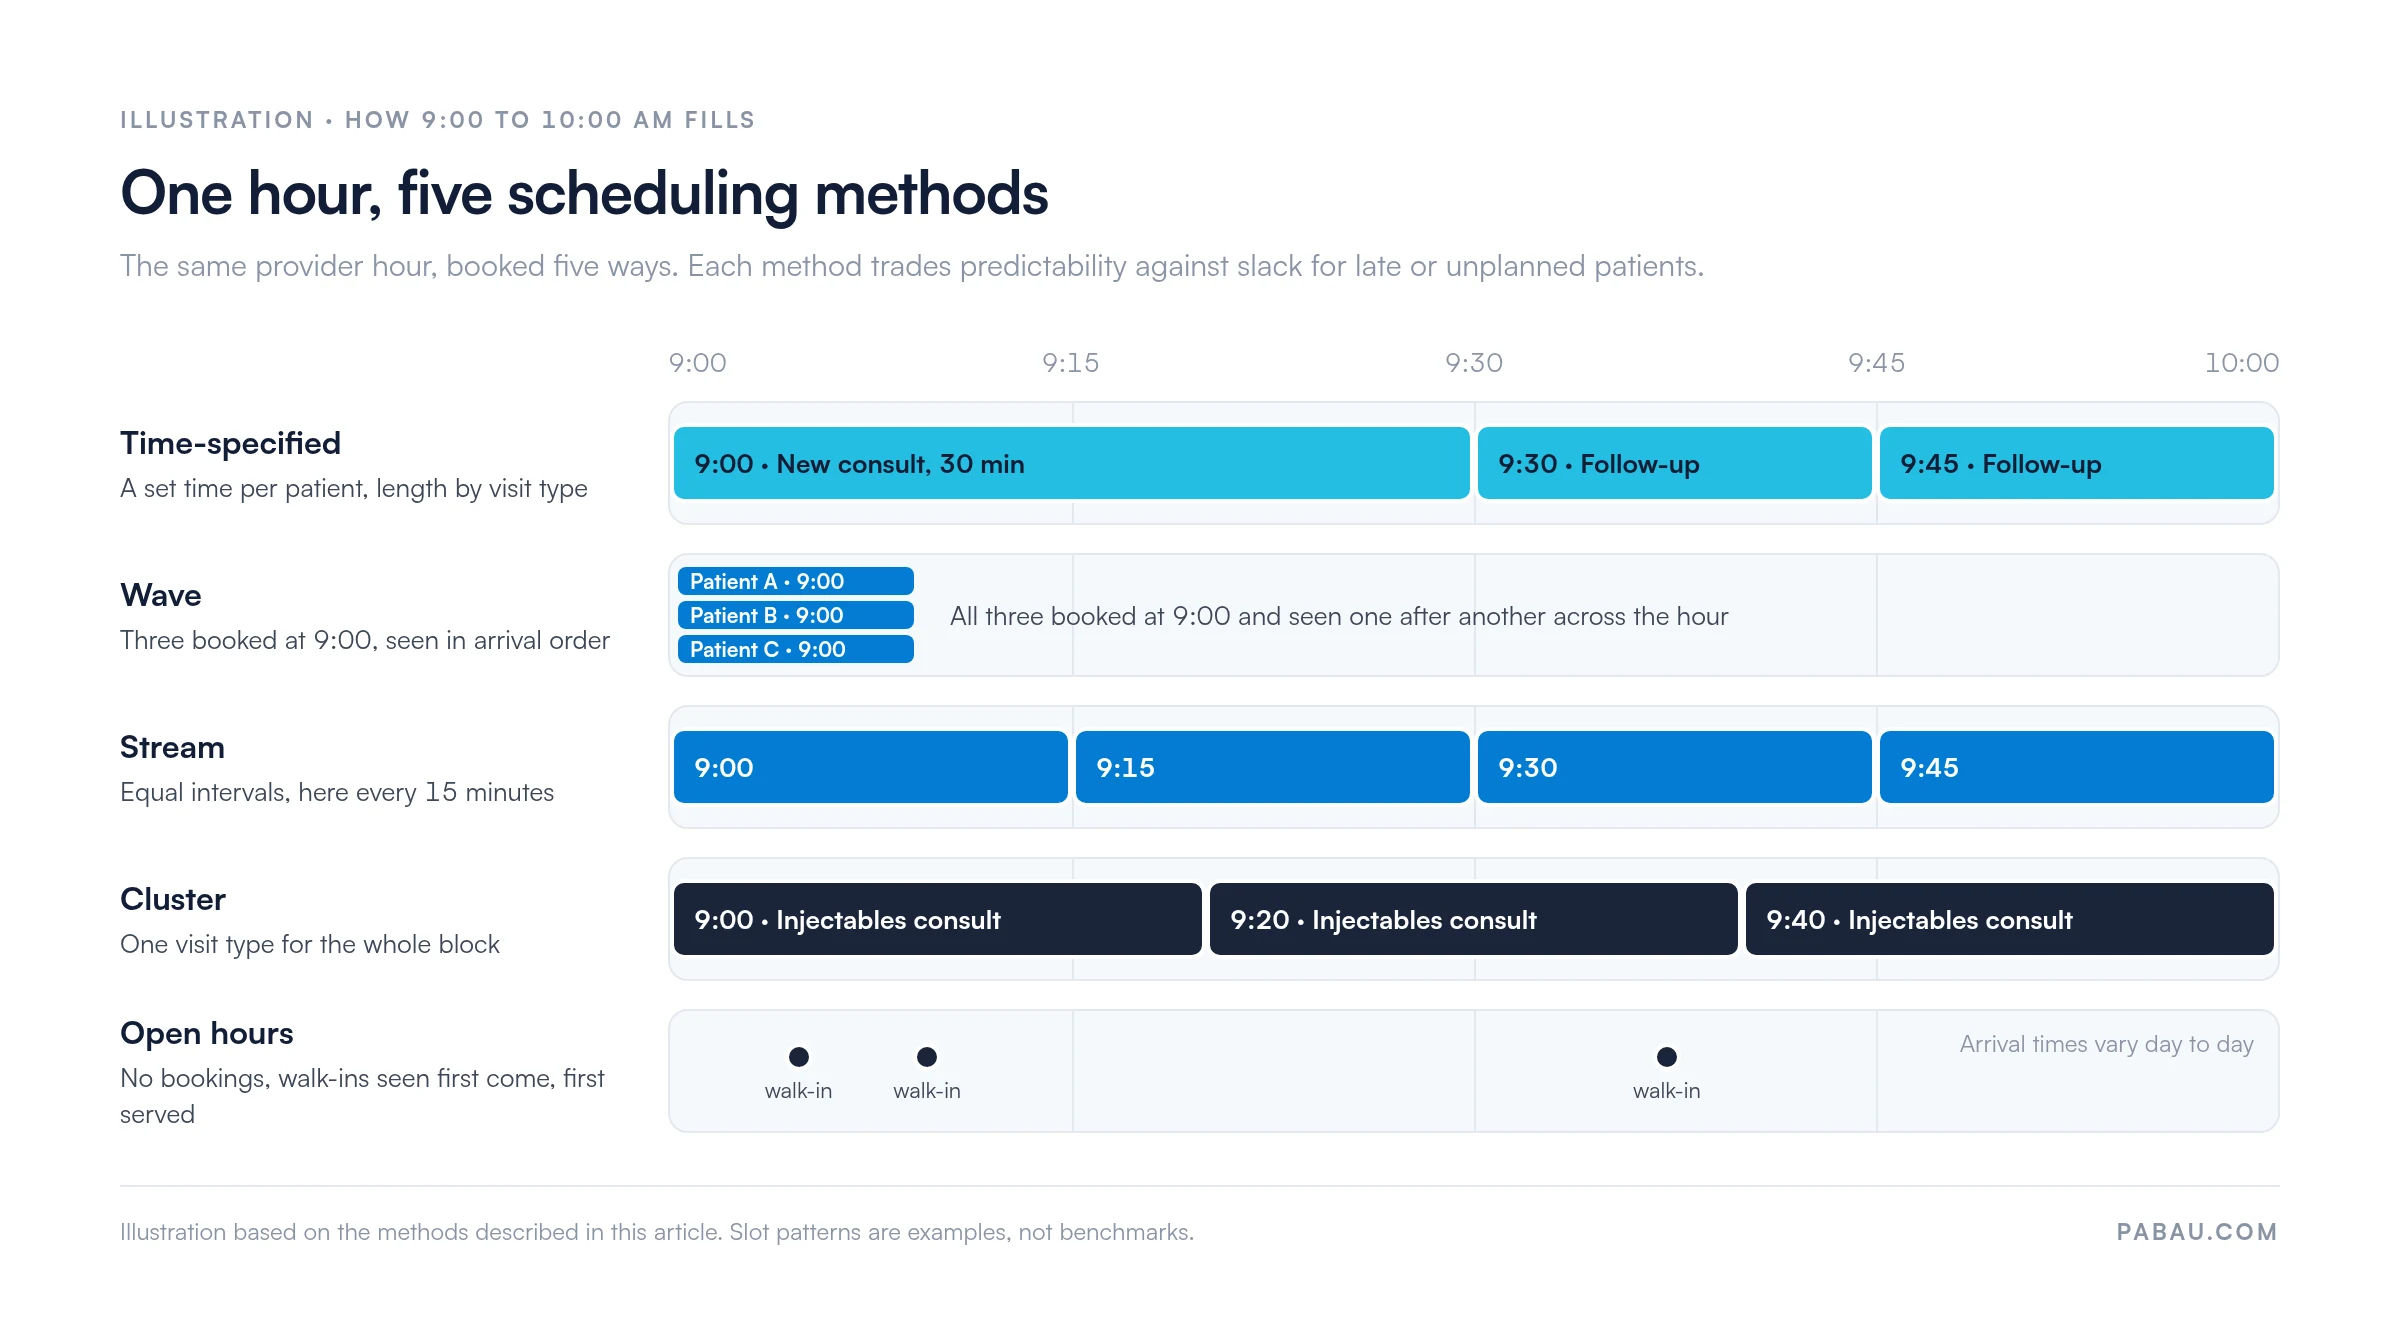
You’ll also see it called specified time scheduling or time-slot scheduling. A typical hour might hold a 30-minute new-patient consult at 9:00, then 15-minute follow-ups at 9:30 and 9:45. Patients who arrive on time wait the least under this method.
The weakness is that it has no slack. One late patient or one consult that overruns pushes every later booking back. Time-specified scheduling only holds up when durations are realistic and a little buffer time is protected each day.
Wave scheduling books several patients at the start of each hour and sees them in arrival order, so one late patient doesn’t stall the hour.
In a pure wave, three 20-minute visits might all be booked at 9:00. Short visits free up time that the occasional long visit then uses. The trade-off is waiting time, because the patient seen third arrived at 9:00 and goes in around 9:40.
Modified wave scheduling softens that. The American Medical Association suggests booking two established patients on the hour and one on the half-hour. The physician starts with whichever patient staff have ready first.
Stream scheduling books patients at regular, equal intervals through the day, such as every 15 or 20 minutes, to keep a continuous flow of patients.
Unlike time-specified scheduling, the interval doesn’t change with the visit type. That suits high-volume, uniform work such as vaccination clinics, blood draws and quick injectable top-ups. Stream scheduling breaks down when visit lengths vary, because every overrun stacks onto the next slot.
Cluster scheduling groups similar appointment types into dedicated blocks, such as all injectables consultations on Tuesday morning, so one team, room and device cover them.
Cluster scheduling fits work tied to one device or one specialist. A med spa might run laser hair removal on Mondays, so the laser is set up once and the trained provider stays in one room. A physical therapy practice might cluster post-op evaluations into one afternoon.
The cost falls on patients who can’t make the block day, who may wait a week for the next one.
Open hours scheduling sets aside a window with no booked appointments, where patients walk in and are seen on a first come, first served basis.
Open hours scheduling is the default in urgent care and walk-in clinics. Its risk is demand you can’t predict, so staff stand idle one morning and are overwhelmed the next. In a booked practice it works best as a capped window, such as a walk-in hour on weekday mornings, rather than an all-day model.
Double booking places two patients in one slot on purpose, usually when one visit needs little provider time or the slot often goes unfilled.
A nurse-led injection paired with a provider follow-up is a common example. When both patients show up, one of them waits. Use double booking sparingly, and only on the visit types your own data says patients skip.
Before you pick a method, pull a month of no-show data broken down by appointment type. One or two visit types, often new-patient consults or same-day requests, usually drive most of the empty slots. Give those an open-hours window or a lightly double-booked slot, and keep time-specified scheduling for your predictable, reliable appointments.
The timeline below shows how the same 9:00 to 10:00 AM hour fills under five of these methods.
The most effective scheduling method is the one that fits your visit mix. For most outpatient practices, that’s time-specified scheduling plus a second method for exceptions.
The method-fit matrix below matches each method to the practice type it suits. It also shows where each breaks and what your system must do to run it.
| Method | How slots fill | Best-fit practice type | Where it breaks | What your system must do |
|---|---|---|---|---|
| Time-specified | One patient per set time, length by visit type | Primary care, specialty, med spa treatments, therapy and telehealth sessions | Late arrivals and overruns push the rest of the day back | Store a duration per appointment type and protect buffer slots |
| Wave | Several patients at the top of the hour, seen in arrival order | Busy primary care and family practice with frequent late arrivals | Patients booked on the hour can wait most of it | Allow several bookings per slot and show arrival order at check-in |
| Stream | Equal intervals, such as every 15 minutes | Vaccination clinics, blood draws, quick follow-ups | Visits of different lengths stack up delays | Run fixed-interval slot templates per provider |
| Cluster | One visit type grouped into a block | Med spa and aesthetics device or injector days, specialty, physical therapy | Patients who can’t make the block day wait longer | Book against room, device and practitioner skill, not only a provider |
| Open hours | No bookings in a window, first come, first served | Urgent care and walk-in clinics | Demand swings leave staff idle or swamped | Run a walk-in queue at check-in and cap the window |
| Double booking | Two patients in one slot, on purpose | Short follow-ups and visit types with high no-show rates | When both patients show, one of them waits | Flag deliberate double bookings and limit how many a day |
Use the visit mix to decide. If most visits run a predictable length, start with time-specified scheduling and add a wave block only where late arrivals are common. If a device, room or specialist limits capacity, cluster those visits into blocks. Keep open hours to a defined walk-in window, and double-book only the visit types your data shows patients skip.
The patient scheduling best practices that move the numbers most are realistic templates, online self-scheduling, automated reminders, deposits, waitlist backfill and monthly measurement.
Give every appointment type its own duration, buffer and resource rules, so each booking reserves the time that visit takes, not a generic 30 minutes.
A patient scheduling template sets those rules per provider for the week. A med spa might hold 30 minutes for a consult, 60 to 90 minutes for a laser treatment and 15 minutes for a review. Add a 10 to 15 minute turnover buffer after longer treatments so the room is reset before the next patient.
Hold back some time for same-day demand as well. The AMA guidance linked above suggests about an hour a day with no appointments, which staff can fill when urgent requests surge. If you’re still working on paper, start from an appointment schedule template and move it into software later.
When we set up calendars for new practices, the most common fix is the consult slot. Consults booked at 15 minutes that routinely run 25 push every later appointment back, so we lengthen the slot before changing any other rule.
Online self-scheduling lets patients book, reschedule or cancel at any hour, and booking rules stop them taking slots you can’t staff.
Patient self scheduling captures demand your phone line misses. Relatient reports, citing an Accenture report, that 43% of self-scheduled appointments are booked after business hours.
Set the rules before you switch online booking on:
Send a confirmation at booking, a reminder 24 to 48 hours ahead and a same-day nudge, each with a one-tap confirm or reschedule link.
Reminders are the cheapest fix on this list. A systematic review of patient reminders found they cut missed appointments by 41% on average. SMS reminders outperformed phone calls, and multiple reminders worked better than one.
Timing matters as much as channel. The 48-hour reminder gives a patient time to move the slot and gives you time to refill it. The reschedule link turns a quiet no-show into a moved appointment. For wording by specialty, borrow from these reminder text samples.
Take a deposit when a missed slot would waste a long treatment, a reserved device or prepared product, then credit it to the bill. Keeping the deposit after a late cancellation or no-show depends on the terms the patient signed, which your patient refund policy should spell out.
Deposits matter most in aesthetics, where a 90-minute laser session or a filler appointment ties up a room, a device and a trained injector. Many med spas keep consults deposit-free and take a deposit on the treatment itself. Deposits fit self-pay visits best, so insurance-billed practices should check payer contracts first.
Keep the policy wording short and put it in the booking flow. For example: “A deposit of [amount] secures your appointment and comes off your treatment price. Reschedule at least 48 hours ahead and we’ll move it to your new date. Within 48 hours, the deposit is kept.”
Keep a waitlist of patients who want an earlier slot, and offer each cancellation to them at once so the time gets rebooked, not lost.
Patients cancel for illness, work and family reasons you can’t prevent. What you control is how fast the slot is offered again. Waitlist software texts the cancellation to waiting patients automatically, so the front desk isn’t phoning down a list.
A clear cancellation policy makes the waitlist work, because earlier notice leaves more time to refill. State the notice window and any fee in the online booking flow, the confirmation and every reminder. If you need starting wording, adapt this appointment cancellation policy template.
Reserve protected slots each day for urgent and same-day needs, and give front-desk staff a short triage script to decide who gets them.
Block the day by appointment type: urgent, routine, follow-up and non-urgent consult. Release unused urgent slots to routine bookings at a set cut-off, such as noon the day before, so they don’t go empty. Some callers only need a short phone consult, and a clear protocol lets staff route them there instead of into a full slot.
Book the next appointment at checkout, while the patient is still in front of you, rather than relying on a recall message weeks later.
The AMA recommends scheduling follow-up visits at the end of each visit, and it matters even more for courses of treatment. A patient starting a course of laser sessions can have every session booked at the right interval on day one. Patients who won’t commit to a date should get a recall reminder set against their record before they leave.
Move consultations, results reviews and progress check-ins that need no hands-on exam to telehealth, and keep treatment rooms for treatments.
Weight loss check-ins and pre-treatment consults are good candidates. Telehealth slots can also sit in early mornings or evenings without opening the building. Give telehealth its own appointment type so the video link goes out with the confirmation. To protect patient data, run it on one of the HIPAA-compliant telehealth platforms.
Track no-show rate, provider utilization, third next available appointment and booking lead time every month, then fix the practice tied to whichever slips.
| Metric | How to calculate it | What to change when it slips |
|---|---|---|
| No-show rate | No-shows ÷ booked appointments | Tighten reminders (practice 3) and add deposits (practice 4) |
| Utilization | Booked provider hours ÷ available provider hours | Fix templates (practice 1), open online booking (practice 2) and backfill (practice 5) |
| Third next available appointment (TNAA) | Days until the third open slot for an appointment type | Rebalance templates and protect same-day slots (practice 6) |
| Lead time | Days between booking and appointment | Add a second reminder and a waitlist for long-lead bookings |
Third next available appointment is a measure used by the Institute for Healthcare Improvement (IHI). It skips the first two open slots because one-off cancellations distort them. To set your baseline, start by learning to calculate your patient no-show rate by appointment type.
Scheduling patient appointments takes six steps: identify the patient, choose the visit type, offer two times, confirm details, send the confirmation, then log it.
Most medical appointment scheduling guidelines come down to that same sequence. On the phone, a short script keeps it polite and quick:
A medical scheduling system should book against providers, rooms and devices at once, automate reminders and waitlists, take deposits, and report on no-shows and utilization.
Moving off manual scheduling is mostly about these eight capabilities:
If you’re comparing tools, our roundup of the best scheduling app options scores them against these capabilities.
Pabau, the practice management platform we build, keeps the calendar, online booking, reminders and the patient record in one system. Each appointment type carries its own duration, room and service, so a 90-minute IV drip can’t land in a room that’s already taken.
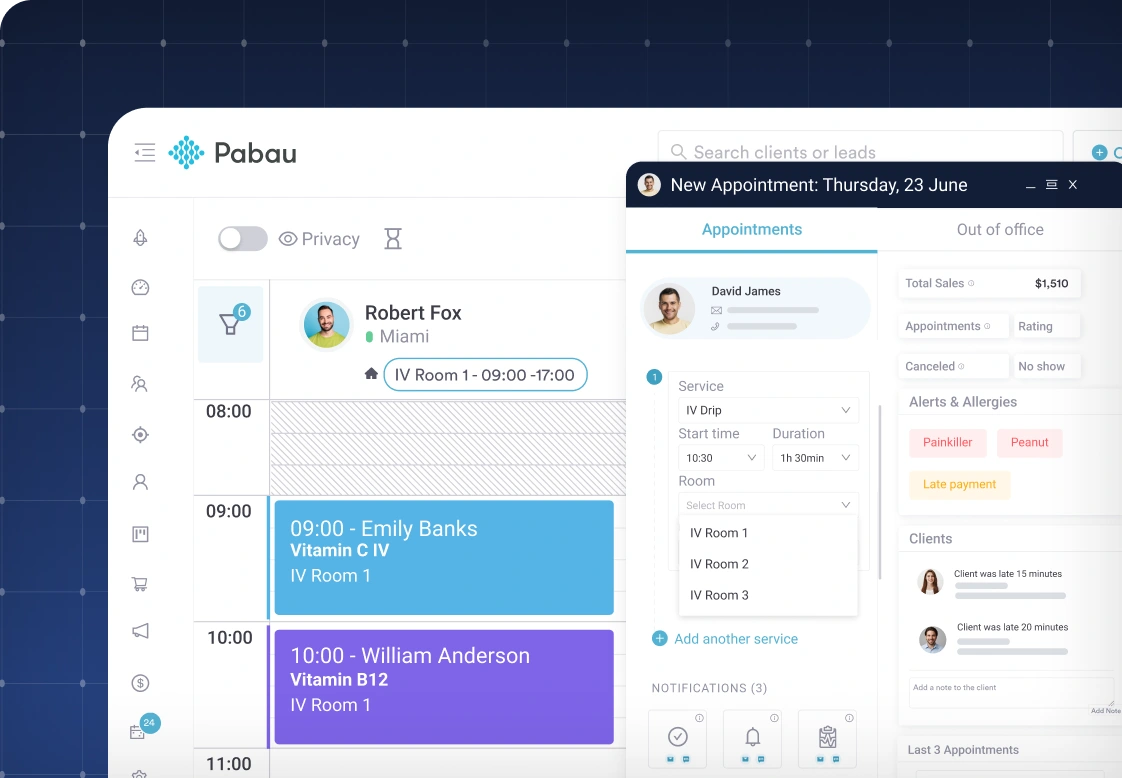
Patients book through online booking or the Client Portal, where they can also reschedule or cancel without calling. Pabau sends confirmations, reminders and intake forms on the schedule you set. Pabau’s online booking can also take a deposit at the point of booking for the treatments you choose.
Each patient’s card shows their cancellations and no-shows, so the front desk knows who to ask for a deposit next time. Cancellations can go straight to the waitlist. During setup, our team configures your appointment types and booking rules with you, and every subscription to Pabau’s practice management app includes every feature.

Pabau’s calendar, online booking, deposits and automated reminders work from one patient record, so fewer slots go empty and your front desk stops chasing confirmations.

Choose the method before you shop for software. A schedule built on the wrong method stays fragile however many reminders you send. The right one leaves automation only the odd empty slot to fill.
Start with this month’s no-show data by appointment type, fix the one template that overruns most, and add deposits where a missed slot hurts. The trade-off worth remembering is that every buffer costs a bookable slot, so size it from your own data. Book a demo to see how Pabau keeps your patient schedule full from first booking to follow-up.

Choosing reminder software? Best appointment reminder software for practices compares seven tools on SMS sequences, reschedule links and pricing.
Comparing full scheduling platforms? Best medical practice scheduling software weighs five systems that book providers, rooms and reminders together.
Need a weekly rota to start from? Practice schedule template gives you a free layout for planning provider hours and shifts.
Still seeing too many empty appointment slots? How to calculate your patient no-show rate shows how to measure the problem and cut missed appointments.
Medical scheduling is the work of matching each patient request to a provider, time, room and any equipment the visit needs. It also covers confirming, reminding and rescheduling those appointments. Scheduling in healthcare differs from general booking because each slot depends on qualified staff and completed forms.
In a medical practice, wave scheduling means booking several patients at the start of each hour and seeing them in arrival order. Short visits absorb long ones, and a late arrival doesn’t stall the hour. The modified version books two patients on the hour and one on the half-hour.
In clinical settings, cluster scheduling groups appointments of the same type into one block of time. A med spa might book all laser treatments on one day so a single device and trained provider cover them. It saves setup time but limits patient choice.
For most outpatient practices, the strongest choice is time-specified scheduling with a second method for the exceptions. Add a wave block where late arrivals are common, and cluster visits that depend on one device or specialist. Match the method to your visit mix, not the other way round.
Make rescheduling easier than skipping. Send a reminder 48 hours out with a one-tap reschedule link, publish a clear notice window, and offer each canceled slot to a waitlist automatically. A deposit on long or high-value treatments gives patients a reason to give notice.
The most frequent errors are generic 30-minute slots for every visit type and no buffer for same-day demand. Another is one reminder sent too late to refill the slot. Booking follow-ups by recall letter instead of at checkout is another costly one.
Telehealth scheduling can be fully HIPAA compliant when appointments, reminders, and consultations run through a secure platform built to protect patient health information. Confirm your telehealth and scheduling software explicitly supports HIPAA requirements before rolling it out.




