Wellness planner: Free template for weekly tracking
A free two-page wellness planner with weekly goals, four health areas, daily not...

3
Last Updated: Sep 23, 2026

Measuring patient satisfaction means turning survey scores, loyalty metrics, wait times, reviews and complaints into one readable picture of your practice. No single number gets you there. Most practices watch four or five signals at once, then fold them into a score they track month to month.
Getting this right protects revenue. Satisfied patients rebook and refer, while unhappy ones write the review your next prospective patient reads.
The harder part comes after the survey closes. Below are the eight metrics worth tracking and the formulas behind them. A four-stage loop then routes a poor rating to a named owner, inside the same week.

Patient satisfaction drives revenue, retention and staff morale, while unhappy patients leave poor reviews or seek legal advice.
The eight metrics run from satisfaction surveys and Net Promoter Score to wait times, reviews, complaints and repeat visits.
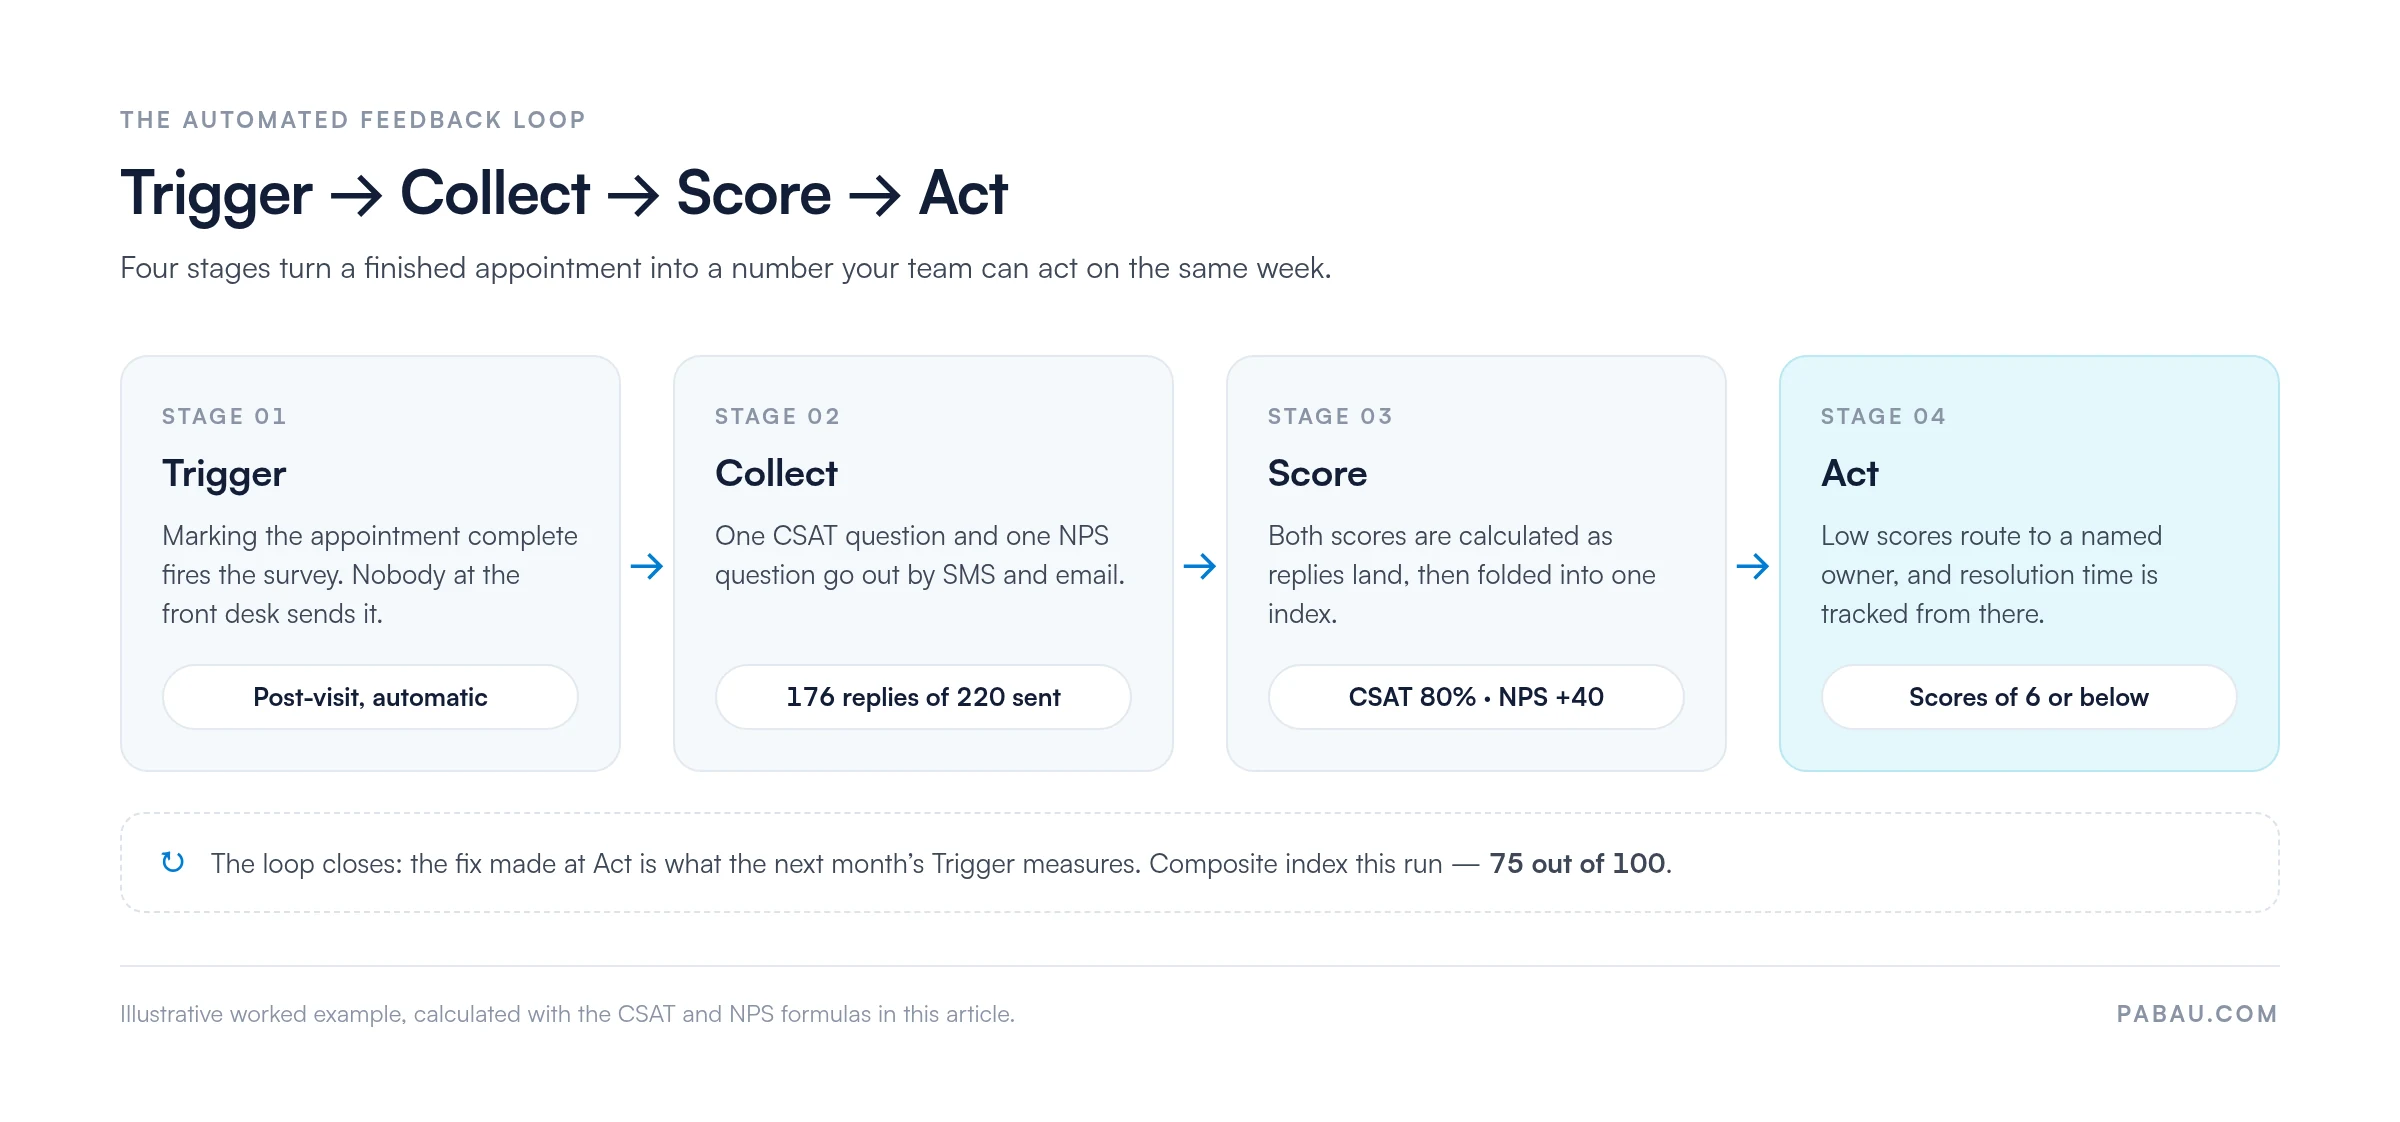
The automated feedback loop, Trigger → Collect → Score → Act, turns a finished appointment into a survey, a score and a follow-up task.
CSAT and NPS answer different questions, so combining both into one index gives a fairer reading than either score alone.
Satisfaction improves most from clear communication, shorter waits, easier online booking, and software that automates forms and reminders.
Satisfaction decides whether patients rebook, what they write online, and how long your staff stay. That puts it alongside equipment and hiring on the planning list.
Four drivers do most of the work:
Almost every metric below is a different way of reading one of those four.
Measuring tells you which of the four is costing you money. Guess instead, and you end up fixing whichever one you already suspected. Research published on PubMed also links higher patient satisfaction to better job retention among staff.

Patients who find the experience straightforward take better care of themselves after they leave. They also tell you more, because they trust what they hear back.
In practice that shows up as fewer missed appointments, fewer late cancellations, and more honest answers on the intake form. Care matched to what the patient reported produces better outcomes.
Roughly two-thirds of patients have reported an unsatisfactory experience with a healthcare professional. Those experiences rarely stay private.
A December 2024 patient choice survey found 84% of patients check online reviews before picking a new provider, and over half read at least six. So a short run of poor reviews moves prospective patients to a competitor. Building patient retention strategies around satisfaction protects that pipeline.
Patients who feel dismissed are more likely to reach for legal advice when a treatment disappoints them. Trust changes that response, because someone who trusts their practitioner comes back and asks first.
Patient satisfaction is measured by combining several signals: survey scores, loyalty metrics like NPS, wait-time data, online reviews and complaint tracking.
No single number tells the whole story, so read them as a set. The eight below start with a two-question survey you could send tomorrow. They end with the standardized instruments hospitals are scored on.
A patient satisfaction survey is a short structured questionnaire sent after a visit, turning subjective impressions into numbers you can track.
Questions should differ for inpatients and outpatients, and be tailored to the service, whether that is a routine check-up or a procedure like eyelid surgery. A workable question reads: “How well did your practitioner explain what to expect after today’s treatment?”, answered on a 1-to-5 scale.
A standardized questionnaire borrowed from a validated instrument keeps your wording consistent. A patient feedback survey you run in March then compares cleanly with September’s, because the question has not quietly changed underneath you.
Form builders let you build a satisfaction questionnaire per service. Send it by email and SMS right after the visit, while the experience is still fresh. Our guide to capturing patient feedback covers the wording in more depth.
To design effective patient satisfaction questionnaires:
Net Promoter Score measures loyalty with one question: would you recommend this practice to a friend or family member?
Patients answer on a patient satisfaction scale of 0 to 10, then fall into three groups:
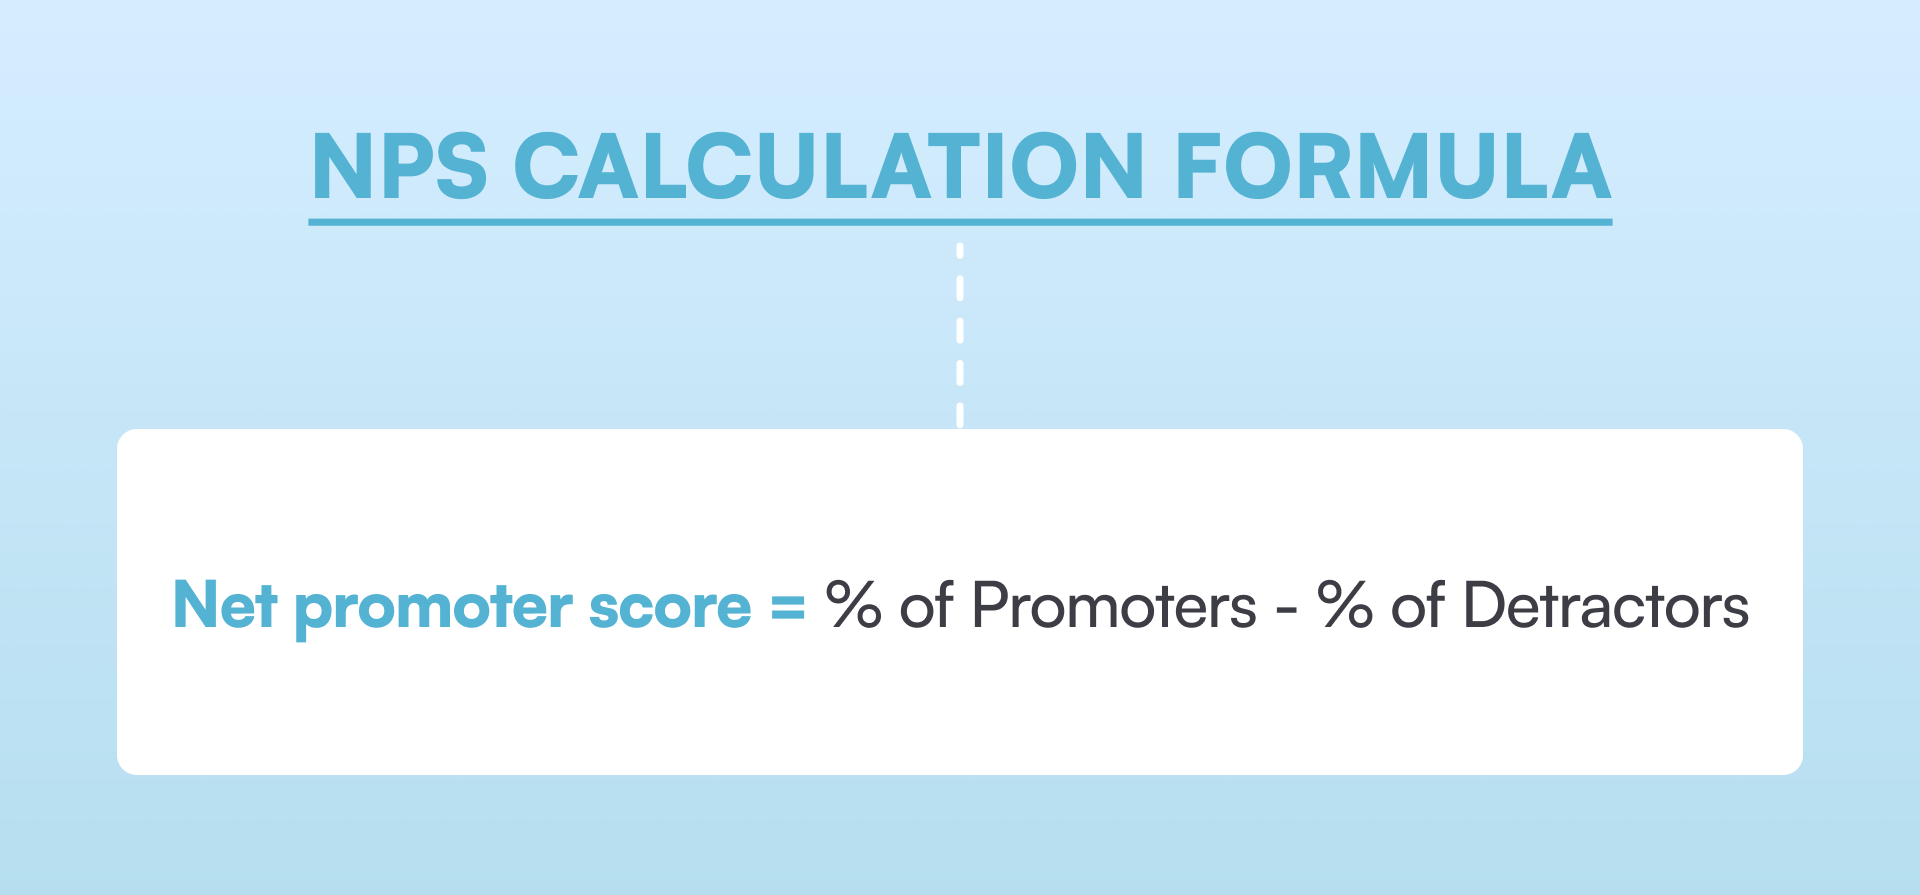
Calculate NPS by subtracting the percentage of detractors from the percentage of promoters. The result runs from -100 to 100, and anything above 0 means more promoters than detractors.
Time in the waiting room has a well-documented effect on the overall patient experience. As wait times climb, satisfaction falls, and patients who wait too long start looking at other practices.
Track the difference between the booked time and the time the patient was seen, by practitioner and by day. The pattern usually points at one session of the day rather than at the whole schedule. To close it, you can:
Response rate is the share of surveyed patients who reply, and it decides whether the score above it is trustworthy.
A score built on nine replies is an anecdote. Chase the response rate first, because a shift in CSAT only carries information once enough patients have answered.
The follow-up itself is a measurement and an intervention at once. Phone, email or SMS after a visit gives you first-hand feedback, and it reassures patients who are unsure whether a side effect is normal.
Follow-ups matter more where care spans several sessions. A physical therapy practice can check progress and exercise adherence between visits, and catch a patient who has quietly stopped doing the work.
Reviews are the one satisfaction metric your prospective patients read before you do. Ratings on Google, Yelp and Healthgrades give you a running read on how the practice is perceived from outside.
Give one person the job of monitoring them. Recurring themes surface quickly that way, and a reply within a day or two often turns a two-star review into a conversation.
Track the average rating and the volume of new reviews separately. A stable average with falling volume usually means the practice stopped asking, not that patients stopped caring.
Complaint rate and resolution time are the two numbers that show whether feedback leads to a fix.
Complaint rate compares complaints to appointments over a period. Resolution time measures how long a complaint sits before someone closes it. Both are worth logging by source and by type, because a named team member or a repeated wait-time gripe is a fixable pattern.
Complaint routing is also the Act stage of the Trigger → Collect → Score → Act loop further down. A survey score of 6 or below creates a task for a named owner, and resolution time starts counting from that moment.
Repeat appointments, referrals and membership renewals are patient engagement metrics that measure satisfaction by behavior rather than by opinion.
Repeat visits say a lot on their own, but the useful detail is why. Same treatment or a different one? Same practitioner or a different one? That answer tells you what patients are coming back for.
Ask new patients how they heard about you. If referrals or one marketing channel dominate, you know which part of the experience is doing the selling.
Loyalty and membership programs give you a second behavioral read. Track the renewal rate and ask leavers why they stopped, because a patient who lets a membership lapse is telling you something the survey missed.
Standardized surveys are validated questionnaires used across many providers, so hospital patient satisfaction surveys can be benchmarked rather than read in isolation.
The best known is HCAHPS, the Hospital Consumer Assessment of Healthcare Providers and Systems.
HCAHPS became a 32-item survey on January 1, 2025, with 22 core questions on communication, responsiveness, cleanliness, medicines and discharge. The outpatient siblings sit in the wider CAHPS family, developed by the Agency for Healthcare Research and Quality.
The scores carry money. CMS withholds 2% of each participating hospital’s Medicare base operating payments and pays it back on performance under Hospital Value-Based Purchasing. HCAHPS makes up the entire Person and Community Engagement domain, a quarter of that score.
Vendors such as Press Ganey administer these surveys and report against national percentiles. A Press Ganey patient satisfaction survey report shows a provider where it ranks, rather than only its own raw average.
Smaller practices have a validated option too. RAND’s PSQ-18 is the short form of its Patient Satisfaction Questionnaire. The PSQ-18 runs to 18 items, takes roughly three to four minutes, and is free for non-commercial use.
The wider PSQ family goes deeper. The PSQ-18 was cut down from the 50-item PSQ-III, which came from an 80-item original.
The table below puts the four instruments side by side.
Two terms show up whenever you read standardized results:
A solo aesthetic or private practice does not need the full HCAHPS apparatus. Borrowing a handful of validated HCAHPS or PSQ-18 questions is enough to keep your own questionnaire consistent and comparable over time.
Patient experience asks what happened during care. Patient satisfaction asks how the visit felt, so the same questionnaire cannot carry both.
Patient experience metrics ask about facts. Did staff explain the medicine, was the room clean, how long was the wait? Satisfaction asks for a rating instead.
Measuring patient experience in practice means the wait-time tracking above plus the PREMs side of a standardized instrument. Track both, because a practice can run perfectly to time and still leave patients feeling unheard. Our guide to patient satisfaction vs experience pulls the two apart in more detail.
Calculate a patient satisfaction score with the CSAT formula: divide satisfied responses by total responses, then multiply by 100.
CSAT % = (satisfied responses ÷ total responses) × 100
Satisfied responses are the top two ratings on your scale. If 80 of 100 patients rate their visit a 4 or 5 out of 5, the CSAT score is 80%.
NPS works differently, subtracting the percentage of detractors from the percentage of promoters. Track both. CSAT captures how a single visit felt, while NPS predicts whether patients return and refer.
Take one month at a practice that sends a two-question survey to 220 patients after their visits. Of those, 176 reply.
On the CSAT question, 141 of the 176 rate the visit a 4 or 5. The CSAT comes out at 80%.
On the NPS question, 97 patients score 9 or 10, 53 score 7 or 8, and 26 score 6 or below. Promoters are 55%, detractors 15%, so NPS is +40.
Two numbers on two different scales are awkward to read side by side. Put NPS on the same 0-to-100 footing by adding 100 and halving the result, which turns +40 into 70.
Average that 70 with the CSAT of 80, and the practice has a patient satisfaction index of 75 out of 100. That single figure goes on the monthly report, with its two components underneath it.
The index is a house measure, not a published standard. The index earns its place by moving when either component moves, so one strong CSAT month cannot hide a falling referral rate.
Patient satisfaction scores are mostly useful against themselves. There is no national benchmark for a four-room aesthetic practice, so your own last quarter is the comparison that counts.
As a rough floor, a CSAT above 80% and any positive NPS are widely read as healthy. Use them as a sanity check rather than a target.
The scale you pick is not neutral either. A 1-to-5 Likert scale is easier for patients to answer, while the 0-to-10 NPS scale leaves more room at the top. Choose one per question and keep it, or your trend line ends up measuring the scale rather than the patients.
The table below compares the core patient satisfaction metrics at a glance:
Patient satisfaction tools are the software that sends the survey, collects replies, scores them and routes the poor ones to a named owner.
Those four jobs are the automated feedback loop: Trigger → Collect → Score → Act. The value sits in the last two. A survey that produces a folder of responses and no follow-up task has cost the practice time and changed no part of the visit.
The survey should fire off an event in the calendar, not off someone remembering. Marking the appointment complete is that event, and it happens anyway.
Practice management software like Pabau can send the survey automatically at that point, so timing never depends on how busy reception was at 6pm.
Send on two channels. SMS collects the quick rating, and email carries the longer form for patients who want to write something.
In practices we onboard, the survey that gets answered is the one that lands the same day. A patient asked a week later remembers the parking, not the consultation.
Scoring happens as replies arrive, not in a spreadsheet at quarter end. The worked example above turns 176 replies into a CSAT of 80%, an NPS of +40, and a composite index of 75.
Set the routing rule before the first survey goes out. Any score of 6 or below creates a task for a named person, with a target for how fast it closes.
Resolution time, from the complaints metric above, is how you check the rule is being followed. Without it, the routing rule quietly becomes a folder again.
Four questions separate patient satisfaction survey software that closes the loop from software that only opens it:
Standalone patient satisfaction survey companies handle the first three well. The fourth is harder for them, because the task has to land where the patient record already lives. Measuring satisfaction inside the patient experience software you already run the diary on avoids that handoff.
Measure client satisfaction the same way you would patient satisfaction: a post-appointment CSAT question, an NPS question, review monitoring and a complaint log.
The metrics do not change for a non-clinical business. The vocabulary does, and so does what a low score usually means.
A therapist, a coach, a salon or a wellness studio has clients, not patients. Those businesses also see the same client far more often than a medical practice does, which changes how the numbers read.
Three differences are worth building into the survey:
The CSAT and NPS formulas above apply without change. So does the Trigger → Collect → Score → Act loop, with a completed appointment as the trigger either way.
The tips that move a score are the ones tied to a metric you already track.
Measuring without acting is half the job. Each tip below maps to one of the eight metrics, so you can tell within a quarter whether it worked.
Communication starts before the patient arrives. Reception staff should be reachable by phone or email, ideally through one shared inbox rather than four personal ones.
Make sure patients leave understanding their diagnosis, their options and their care plan, and walk them through pre- and aftercare at each step. Inviting questions costs a minute and prevents the follow-up call.
Treat the problem the patient came in with, not only the diagnosis on the chart. Tailor care to their health status and preferences, and respect their cultural, religious and personal values.
Then ask what a good outcome looks like to them, and write the answer into the note. The next practitioner starts from the same place, which is what consistency feels like from the chair.
Long waits are the most common complaint, and some delay is unavoidable. A scheduling system that stops you overbooking removes most of the rest.
When a session runs behind, tell patients how long the delay will be. A stated 20-minute delay annoys people far less than an open-ended wait.
Online booking with a simple portal lets patients book in a few taps, from anywhere, at the hour they think about it.
Telehealth consultations add another route in. A patient with a short question gets an answer without a round trip to your practice.
A consistently clean environment helps prevent healthcare-acquired infections, and patients judge it long before they judge your clinical work.
Comfortable seating and a welcoming reception show up in satisfaction scores more than the fit-out budget suggests. So does privacy: make sure no patient is discussed within earshot of the waiting room.
Practice management software lets patients do for themselves what they currently phone you about. Booking, rescheduling, completing forms and reading aftercare all move off the front desk.
The same system stores medical history, allergies, intake forms, lab results and before-and-after photos against one record. The practitioner then stops reconstructing the picture mid-appointment.
Few patients can judge your clinical technique, so they judge consistency instead. A plan explained one way by the practitioner and another way at the front desk reads as poor care.
Write the treatment explanation and the aftercare once, store both against the treatment, and every practitioner sends the same version. Staying current with best practice matters, but consistency is the part patients can see.
Satisfaction usually gets measured in one tool while the practice runs in another, so the score and the patient record never meet. The follow-up then depends on someone reading a report and remembering.
Pabau runs the whole loop against the same record. Marking an appointment complete triggers the survey, and the reply is scored as it lands. A poor rating becomes a task on that patient’s file, with an owner and a due date.
The stages either side get easier too. Online booking and digital forms take phone calls and paperwork off your reception team. That moves the two drivers patients complain about most, waiting and access.
Every subscription includes every feature, so the survey, the scoring and the follow-up task are all there from day one. Structured onboarding gets them configured for how your practice actually runs.

Pabau triggers a survey when an appointment is marked complete, then scores CSAT and NPS as replies arrive. A low rating becomes a task on the patient record, with an owner and a due date.

The practices that improve satisfaction are rarely the ones measuring the most. They are the ones that decided in advance what a bad score would trigger.
So pick two questions and send them the day of the visit. Then write the rule down. Decide which score creates a task, who owns it, and how fast it closes. The index can come later.
The trade-off worth remembering is that every question you add costs you replies. A short survey that patients finish beats a long one they abandon halfway. Book a demo to see how Pabau turns a completed appointment into a scored survey and a follow-up task.

Need the survey questions themselves? Patient experience survey covers how to design one, run it, and act on what comes back.
Wondering which experience numbers to watch? Patient experience metrics sets out what to track and how to move each one.
Getting more complaints than you can log? Patient complaints walks through handling, documenting and preventing them.
Want the behavioral side of the picture? Measuring patient engagement covers the metrics, tools and workflows behind it.
Reviews pulling your rating down? Online reputation management for doctors is a practical guide to responding and recovering.
Send the survey after each completed appointment rather than on a calendar schedule. Practices that see the same patient weekly should ask after a course of care instead, or response rates drop. Run a longer questionnaire once a year if you need depth.
A survey response linked to a named patient is protected health information, so it belongs in a system built to hold PHI. Aggregate scores carrying no identifiers are not. Check that your survey tool signs a business associate agreement before you send anything through it.
Anonymous surveys get franker answers, but they stop you following up on a poor score. Most practices identify responses and say so up front. To get both, keep the rating identified and make the free-text comment optional.
No. Google’s review policies prohibit review gating, where you screen patients first and invite only the satisfied ones to post publicly. Invite everyone you survey, and use the private rating to catch problems before they reach a public page.
Give one named person the survey, the reviews and the complaint log. Splitting those three across reception, marketing and the front desk leaves a poor score unowned. In a small practice that owner is usually the practice manager.