


Medical office supplies list: Free checklist + reorder rules
A medical office supplies list is the checklist a practice uses to stock its exa...

1
Last Updated: Oct 2, 2026

Healthcare worker burnout solutions that fit a small practice remove work from the day rather than adding a wellness program.
Administrative load is the first thing to cut, because it is the driver an owner controls outright and the fastest to move.
Warning signs show up in your schedule and your clinical notes long before anyone says the word burnout.
When someone is already burned out, change the workload before the conversation, because a talk with no change behind it lands badly.
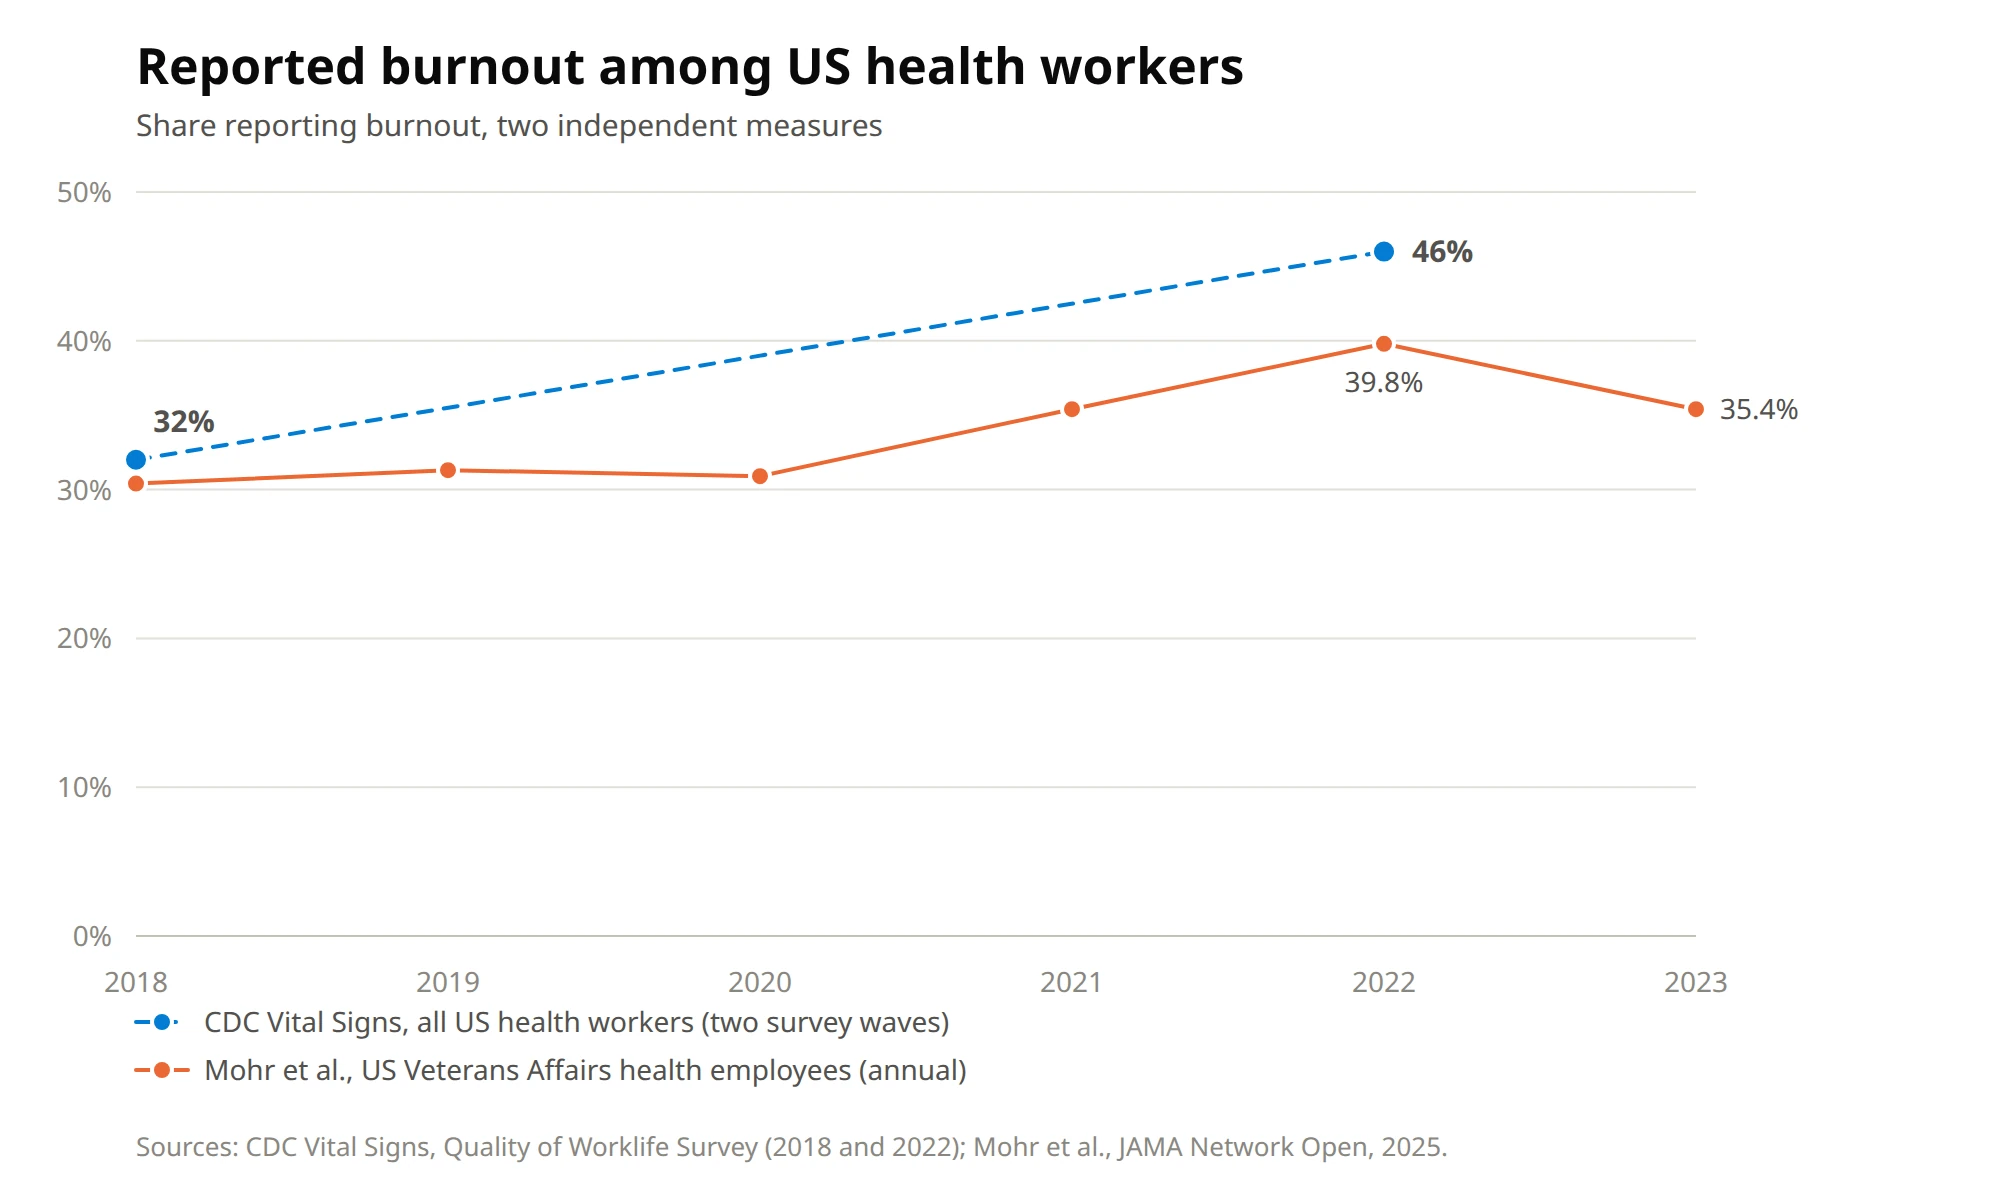
The World Health Organization classifies burnout as an occupational phenomenon, and the CDC found 46% of US health workers burned out in 2022.
The healthcare worker burnout solutions that hold up in a small practice all work the same way. They take work out of the day, rather than asking staff to cope better with the day they already have.
Healthcare burnout is produced by chronic workplace stress that never resets, so it surfaces first as emotional exhaustion. The fixes that last therefore change the conditions, starting with the administrative load.
Almost every guide on this subject is written for a hospital. It assumes a chief wellness officer, an annual engagement survey, and a budget line for staff well-being.
A large share of care is delivered somewhere else. It happens in practices of three, five, or twelve people, where the owner still sees patients and often carries the heaviest load in the building.
This guide leads with the fixes. After that it covers what burnout is, how common it is, what causes it, how to catch it early, and what it costs. It closes with what to do when someone is already burned out.
The healthcare worker burnout solutions below are the ones a practice of three to twelve people can run without an HR department. Each names who runs it, what it costs, and how quickly it shows.
They are ordered by what to do first. Administrative burden leads because a practice controls it outright, and because a change there shows within weeks.
A health system would answer the same five drivers with a staffing committee, a shared governance policy, and a chief wellness officer. Organizational responsibility still applies in a practice of six. It just has one name on it.
| Driver | What a small practice can do | Who runs it | Cost | How fast it shows |
|---|---|---|---|---|
| Administrative burden | Automate confirmations, intake, consent, and note drafting, so nothing is typed in twice. | Owner, plus whoever runs the front desk | Cost of the practice management software you already run | Weeks. Evening charting drops first. |
| Chronic work overload | Cap the daily list at what the thinnest safe schedule covers, and block admin time on the calendar. | Owner, about an hour to set up | No cost, though daily revenue dips before it recovers | Immediately, in the schedule. |
| Lost autonomy | Let each clinician own their note template, their schedule shape, and one process they may change unasked. | Owner, one conversation per clinician | No cost | One to two months. |
| Thin recognition | Name one specific thing each person did well every week, in front of the team. | Owner or lead clinician, 10 minutes weekly | No cost | Weeks. |
| Moral injury | State which constraint forced the compromise, and log the pattern for the next review. | Whoever ran the appointment, a minute each time | No cost | Slow, but it stops the blame landing on the clinician. |
Staffing shortages sit underneath the first two rows and take longest to move. Hire for the administrative hours before the clinical ones, and only after removing the repeat work, or you pay twice for the same tasks.

Burnout in healthcare is chronic exhaustion, cynicism toward the work, and a shrinking sense of competence, produced by working conditions rather than by personal weakness.
The measured version has exactly three domains:
The World Health Organization listed burn-out in ICD-11 in 2019, under code QD85. It sits there as an occupational phenomenon, which is the working definition of burnout in healthcare most research now uses.
Christina Maslach built that three-domain model in the 1970s. Studies of burnout in healthcare professionals still measure it with the Maslach Burnout Inventory.
Clinical burnout and depression overlap, and both deserve attention. Burnout is tied to the job and tends to ease when the job changes. Depression follows a person into every part of life and needs clinical assessment.
The three domains are easier to act on once you translate them into behavior you can watch for.
| Dimension | What it feels like | What it looks like day to day in a practice |
|---|---|---|
| Emotional exhaustion | Depleted before the day starts, with nothing left for the last patient. | Running behind by mid-morning, and dreading the afternoon list. |
| Depersonalization | Patients register as tasks rather than people. | Clipped consultations, fewer questions asked, notes that read like a checklist. |
| Reduced personal accomplishment | A sense that the work no longer makes any difference. | Audits and training get skipped, and nobody raises ideas in team meetings. |
The CDC found that 46% of US health workers felt burned out often or very often in 2022, up from 32% in 2018.
Two patterns hold steady in burnout among healthcare workers. The rate climbed sharply through the early 2020s, and burnout rates in healthcare sit above those for the wider workforce.
Beyond that, burnout statistics in healthcare swing wildly, and the reason is measurement rather than disagreement about severity.
Rotenstein and colleagues reviewed 182 studies in JAMA in 2018, covering 109,628 people across 45 countries. Reported prevalence of burnout in the medical field ranged from 0% to 80.5%.
The reason for that spread sits in the same paper. Those 182 studies used at least 142 different definitions of what met the criteria for burnout.
A headline percentage therefore tells you less than the instrument behind it. The table below names the year and the source for every figure.
| Group | Burnout rate | Year | Source |
|---|---|---|---|
| US health workers | 32% felt burned out often or very often | 2018 | CDC Vital Signs |
| US health workers | 46% felt burned out often or very often | 2022 | CDC Vital Signs |
| US physicians | 37.9% | 2012 | Shanafelt et al., Archives of Internal Medicine |
| US physicians | 62.8% reported at least one symptom of burnout | 2021 | Shanafelt et al., Mayo Clinic Proceedings, 2022 |
| US physicians | 45.2% reported at least one symptom of burnout | 2023 | Shanafelt et al., Mayo Clinic Proceedings, 2025 |
| US nurses (registered and licensed practical) | 45.1% felt burned out a few times a week or daily | 2022 | NCSBN, Journal of Nursing Regulation, 2023 |
| US physician assistants | 34.2% reported at least one burnout symptom | 2023 | NCCPA, Health Affairs Scholar, 2025 |
| US Veterans Affairs health employees | 30.4% | 2018 | Mohr et al., JAMA Network Open, 2025 |
| US Veterans Affairs health employees | 39.8% | 2022 | Mohr et al., JAMA Network Open, 2025 |
| Employed adults outside medicine | 27.8% | 2012 | Shanafelt et al., Archives of Internal Medicine |
Read down the rate column before comparing rows. Each study used a different instrument, so the near-identical physician and nurse figures reflect different measurements rather than an identical experience.
Burnout in healthcare is caused by the job’s conditions: sustained overload, lost control, administrative burden, thin recognition, and moral injury.
Employees get burned out in the healthcare industry faster than in most others because all five stack on the same person. The clinician absorbing the extra list is usually the one also chasing the paperwork it generates.
Personality plays a part too. The internal risk factor for burnout in healthcare named most often is perfectionism, and it multiplies the external load rather than replacing it.
Workload is the driver staff name first, and it is rarely just patient volume. It is volume plus every task that falls outside somebody’s role.
Tight schedules, too many patients, and work nobody was hired to do stack up quickly. It hits hardest for clinicians moving into private practice, who absorb administrative duties they never had before.
Staff-to-patient ratios are the sharp end of it. Nurses overworked across too many patients lose the minutes that make care feel like care, and they notice that loss before anyone measures it.
Chronic overload holds steady until it stops holding. People describe hitting a limit with little warning, and then leaving. The pattern feeds itself, because the remaining team absorbs the work.
The hiring market makes recovery slow. The AAMC projects a US shortage of up to 86,000 physicians by 2036, so a vacancy takes months to fill.
The fix: measure the load before you hire against it. Look at what time of day clinical notes are being written, because that number tells you how much of the job no longer fits. Then remove the repetitive work, since spreading the same admin across more people multiplies its cost.
Autonomy is the ability to influence how your own work runs. Losing it makes an identical workload feel considerably heavier.
Robert Karasek’s demand-control model puts the worst combination as high demand paired with low control. Healthcare sits in that quadrant more often than most industries.
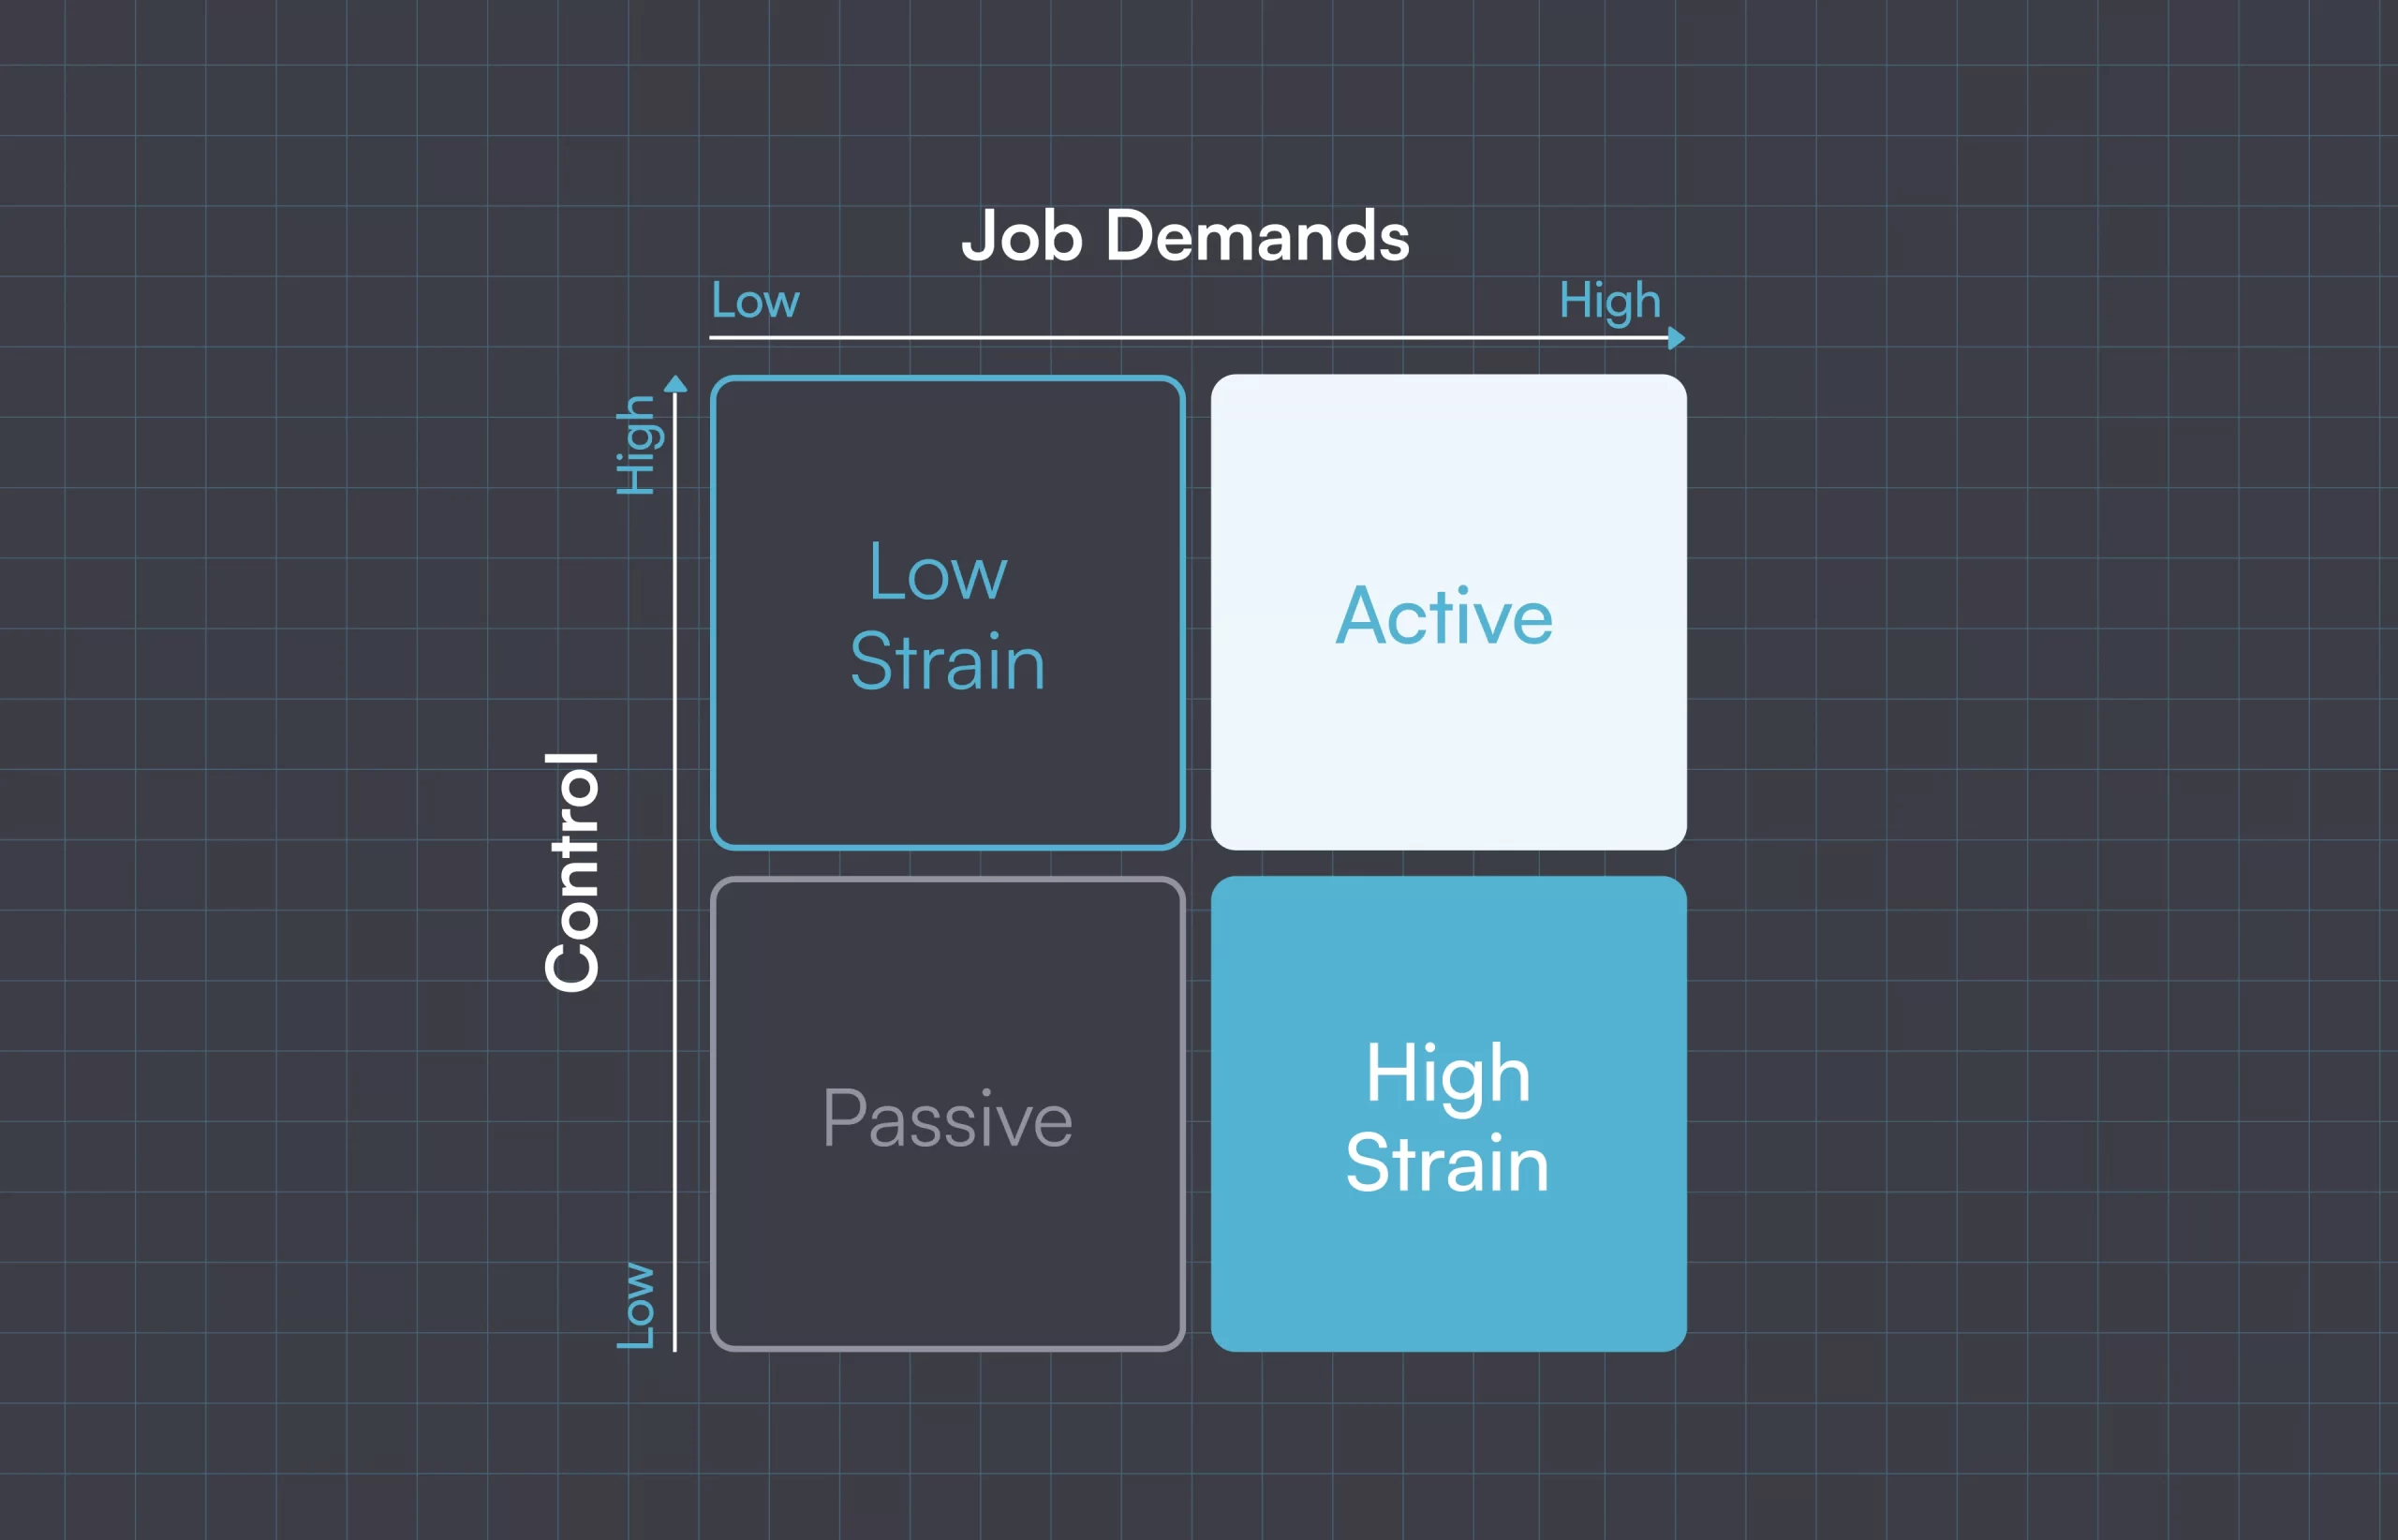
Lost control shows up in small forms. Protocols may leave no room for judgment, or every decision may need a supervisor’s approval first. Scheduling control is usually the first to go and the easiest to hand back.
Practice owners are a special case. On paper they control the whole operation. In practice they are the last line of cover, so their week is set by whoever called in sick.
The fix: give each person one process they can change without asking permission. Frontline staff hit the friction daily, so physicians, nurses, and medical assistants can usually name the three worst steps in any workflow. Let them adjust their own task mix and schedule shape within clinical guidelines, rather than issuing one template to everybody.
Administrative burden is the driver named most often and specified least. In a small practice it comes down to a short and very familiar list of jobs.
None of that work is optional. Records have to be accurate, and HIPAA sets rules for how patient information is stored and shared. Moving a record to another provider often needs a signed authorization for disclosure first.
What decides whether it burns people out is where the work ends up happening. Documentation that spills past the end of the day competes directly with rest, and it wins every time.
Duplicate data entry is the quiet multiplier. A patient writes their history on paper, then a receptionist types it into the record. The clinician reads it again somewhere else during the consultation.
Attention also drops as the day runs long, and that is when a note gets missed or a code gets mistyped. Provider burnout in healthcare is usually measured in evenings, not in patient numbers.
Left alone long enough, the charting queue rather than the clinical work becomes the reason the job feels heavy.
The fix: remove steps rather than reorganizing them, because organizing paperwork better leaves you with the same paperwork. Capture information once, so intake answers arrive in the record without a second round of typing.
Keep consent in the patient’s timeline, submit prior authorizations digitally, and draft notes from the consultation while it is happening. Each step removed is time returned to the working day.
Recognition costs almost nothing and protects more than most interventions a small practice can afford.
Linzer and colleagues found in JAMA Health Forum that clinicians who felt valued reported 37% burnout in late 2021. Among those who did not feel valued, it was 69%.
That 32-point difference tracks whether somebody says thank you and means it. Being chronically underappreciated erodes a sense of purpose, and purpose carries people through a demanding week.
A second problem sits underneath. Many clinicians will not say they are struggling, because they fear what a disclosure does to a license or a reputation.
Peer support is what usually breaks that silence first. Colleagues hear it before an owner does, so a team where people debrief after a hard appointment catches trouble earlier than any survey.
The fix: make recognition specific, regular, and safe to answer honestly. Generic praise reads as noise, so name the particular piece of work somebody did well, in front of the team.
Funding a course and protecting the time to attend it sends the same signal in a different currency. Then name one person staff can talk to before they reach crisis point.
If anyone is in crisis, the 988 Suicide and Crisis Lifeline takes calls and texts across the US at any hour. Say so out loud, before anyone needs it.
Moral injury is the distress of knowing what a patient needs and being unable to provide it, because of constraints outside your control.
The term came out of military psychiatry, where Jonathan Shay used it for the damage done when leadership betrays what is right. Surgeon Simon Talbot and psychiatrist Wendy Dean applied it to medicine in 2018.
Their argument was that calling clinician distress burnout hands the repair job to the individual. The two describe different wounds. Burnout is a depleted state, while moral injury comes from delivering care you know falls short.
In a small practice it sounds ordinary. An ADHD practice books months ahead because no earlier slot exists, and a skin practice turns someone away because a machine is broken.
Resilience training does not reach this. The distress is an accurate response to the constraint, so the constraint is what to work on.
The fix: split the list in two. Some constraints are yours to change, including slot length, equipment, referral routes, and how much of the day is unbookable. For the rest, say out loud which constraint forced the compromise, then log it. An unnamed compromise gets carried personally, and a logged pattern becomes an argument for changing something.
Staff burnout in healthcare shows up in your schedule and your clinical notes weeks before anyone says the word out loud.
The label arrives late because the early signs look like ordinary busyness. People who are coping badly still turn up, and they still get through the list.
The operational signals are the useful ones, because they are already recorded. You can watch all five without asking anyone to fill in a survey.
Behavior gives you the second read. Handovers get shorter, nobody volunteers for cover or training, and easy colleagues start irritating each other.
Intent to leave forms well before a resignation lands. By the time someone hands in notice, the schedule has been showing it for months.
Each question maps to one of Maslach’s three domains. Answer them for yourself first, then ask them of your team.
Two uncomfortable answers are worth acting on. Three means the conditions changed a while ago.
The Maslach Burnout Inventory turns the same three domains into a scored instrument. Our Maslach Burnout Inventory guide covers how it is scored and where it is appropriate to use.
Healthcare worker burnout costs a practice four ways: patient safety incidents, staff turnover, sick leave, and a quiet decline in care quality before anyone resigns.
Safety comes first because it is the one nobody can absorb. Tired clinicians make more mistakes, and those cluster in documentation and prescribing. A missed allergy note is usually the visible end of a long administrative day.
Turnover is the cost most owners feel. In a four-clinician speech therapy practice, losing one clinician removes a quarter of your capacity overnight. Cover then falls to the remaining three, whose own workload was already the problem.
Replacement is expensive even when it goes smoothly. Hamidi and colleagues costed recruitment and start-up for one departing physician at an academic medical center at between $268,000 and $957,000.
Nationally, Han and colleagues estimated in the Annals of Internal Medicine that burnout costs roughly $4.6 billion a year, or about $7,600 per employed physician. That estimate counts only turnover and reduced clinical hours, so treat it as a floor.
Employee burnout in healthcare is most expensive in the stage before any of that. Consultations get shorter, recalls stop going out, and the practice quietly stops doing the work that brings patients back.
Preventing burnout in healthcare without an HR department means picking the three or four changes one person can run. Then run them consistently for a quarter.
Ways to reduce burnout in healthcare usually arrive as programs. What follows is a sequence instead, in the order that makes each step cheaper than the one before it.
Step two carries most of the return, which is why it sits ahead of the cultural work. Recognition lands differently on a team that finished on time than on one still charting at nine.
Stress management for healthcare workers works best when it subtracts something. Most of the standard advice does the opposite, and adds a task to the person with the least time.
A mindfulness app, a resilience course, and a gratitude journal all ask for minutes that healthcare worker stress has already taken. A depleted team does none of them.
These five subtract instead, and each one can start this week.
Mindfulness and exercise do help people who already have room for them. Offer them, and do not count them as the practice’s answer to healthcare stress. Work-life balance is decided by what time the last note closes.
How to prevent burnout in healthcare when you own the practice comes down to removing yourself as the default cover for every absence.
This is the hardest version of the problem. There is nobody above you to approve a lighter schedule, and the income depends on your clinical hours.
If you fill in whenever someone is out, other people’s absences decide your workload. Build a short cover list, agree what it costs, and use it before you use yourself.
Then hand somebody else the authority to say no on your behalf. A named person who can decline an add-on protects the whole afternoon, and they only need one rule to apply.
Stepping back properly needs three conditions in place first. Someone else has to be able to run a normal day. The routine workflows have to be written down. The system has to hold the answers people currently ask you for.
With those in place, cutting clinical days while keeping ownership is a common middle step. It is far easier to reverse than a sale, and it is usually enough.
Register with your own physician as well. Owners are often the only person in the building whose health nobody is monitoring.
When someone is already burned out, change the workload first, because a conversation with no change behind it reads as a brush-off.
Take one duty off before you talk: the late list, the paperwork run, the on-call week. Say what you removed and for how long, so the change is visible and bounded.
Then have the conversation, and ask a better question than whether they are okay. “What is the worst part of your week?” gets an answer. “Are you okay?” gets “fine.”
Fix the schedule next, not the person. Reduce the list, protect the admin time, and move documentation back inside the working day. Recovery needs the conditions to have changed, not just a week off.
Boundaries need restating out loud at this point. Someone who has been the reliable one for two years will keep answering messages at ten unless you tell them to stop.
Know when it stops being a workload problem. Low mood, disturbed sleep, or loss of interest that persists away from work needs a doctor, not a schedule change.
Say that plainly, make the time available for the appointment, and point to whatever mental health support or counseling you can fund. If anyone is in crisis, the 988 Suicide and Crisis Lifeline is available at any hour.
Accept, finally, that some people are not coming back. A clean exit with a proper handover protects the rest of the team. A drawn-out one usually costs you two people instead of one.
Most of what makes a clinical day overrun is administrative, and most of that is repetitive. It is the part of burnout a small practice can move fastest.
Practice management software like Pabau is built to remove those steps rather than redistribute them. What follows is what that looks like on an ordinary Monday.
A patient reschedules through online booking at nine on Sunday evening. The calendar updates itself, the confirmation sends automatically, and nobody spends Monday morning on the phone about it.
Their intake form and consent went out ahead of the appointment and came back signed into the patient’s record. Nothing is re-keyed at reception, and nobody hunts for paper consent before the follow-up.
During the consultation, Pabau Scribe, our AI scribe, drafts the clinical note from the conversation itself. The draft lands in the record that already holds the appointment, so the note gets finished in the room rather than at home.
Their six-month recall then sends itself, so follow-up care stops depending on somebody remembering to chase it. That is six administrative steps removed from a single appointment.
Every subscription includes every feature, so none of this sits behind a higher tier. Setup runs through structured onboarding with a dedicated coordinator, and going paperless happens one workflow at a time.
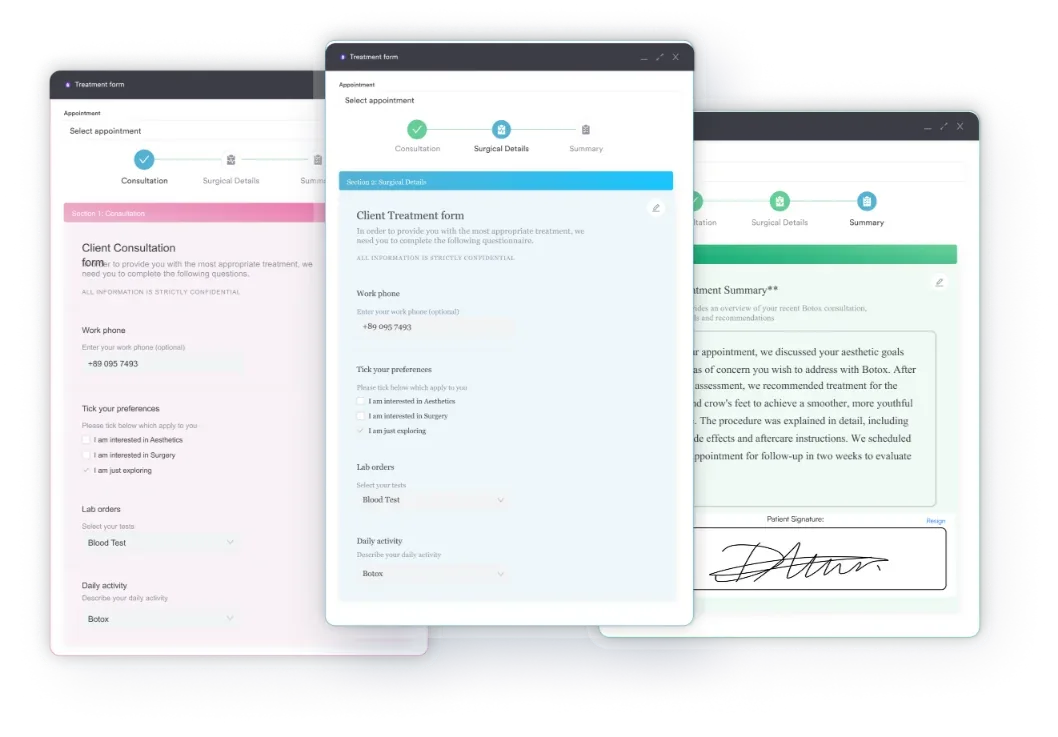

Pabau handles online booking, digital intake and consent, automated recalls, and clinical notes in one system. That keeps documentation inside the working day instead of following your team home.

Pick one driver and change something measurable this month. Log what time the last note closes, remove the admin that is pushing it late, then look at the number again in four weeks.
Doing that changes what the job feels like well before it changes what the practice earns. A team that finishes on time asks better questions, chases recalls, and stops quietly planning an exit.
The trade-off worth remembering is timing. Removing administrative work costs money now and returns clinical hours gradually, while turnover costs more and arrives without notice.
You will not solve this with a resilience course, and you do not need a wellness budget to start. Book a demo to see how Pabau cuts the administrative load that pushes clinical work into the evening.

Want to score burnout properly rather than guess at it? Maslach Burnout Inventory explains the three domains it measures and how the scores are read.
Running a therapy practice rather than a medical one? Therapist burnout: signs, causes, and prevention covers the caseload pressures specific to talking therapies.
Choosing a system that adds less admin? EHR selection walks practice owners through a five-step way to judge the options.
Due for a staff annual review? annual review template provides sample comments, SMART goal examples, and review questions for healthcare practices.
Coordinating shift tasks in a care facility? CNA daily assignment sheets template provides a structured framework for assigning patients and documenting care across shifts.
Stop being the default cover whenever someone is out, because that hands your workload to other people’s absences. Give one colleague authority to decline add-ons for you. Protect a weekly session that cannot be booked into. Cutting clinical days while keeping ownership is a reversible middle step.
Administrative load is one of the most consistently reported drivers, so reducing it treats a cause rather than a symptom. The result depends on where the freed hours go. Time returned to clinical work or to notes helps, and time absorbed by more appointments does not.
They are different problems. Burnout is tied to work and usually eases once the working conditions change. Depression affects every part of life and needs clinical assessment. The two overlap often, so a persistent low mood deserves a doctor’s opinion rather than a schedule change.
Clinical burnout is measured with the same three domains as any other occupation, so the construct itself is identical. The exposure is what differs. Clinicians carry emotional demands, high stakes, and a heavy documentation load at once, which is why their rates run above the general workforce.
The Maslach Burnout Inventory is the standard instrument, and it scores emotional exhaustion, depersonalization, and personal accomplishment separately. Our Maslach Burnout Inventory guide covers how it is scored and read. Cut-off scores differ between studies, which is why published rates vary so widely.
Psychologist Herbert Freudenberger described the pattern in 1974, in the Journal of Social Issues, after observing staff at a free clinic. Christina Maslach turned it into a measurable model soon after. The World Health Organization classified burn-out in ICD-11 as an occupational phenomenon in 2019.





