

HCPCS code E0198: Water pressure pad billing guide
HCPCS code E0198 is a water pad for a standard mattress HCPCS code E0198 is the ...

Last Updated: Oct 13, 2026
93459 is the CPT code for left heart catheterization with coronary angiography, catheter placement in bypass grafts, and bypass graft angiography. Left ventriculography is included when performed, along with imaging supervision and interpretation.
The code applies to patients with prior coronary artery bypass surgery whose grafts are imaged during the study. Without documented graft angiography, the correct code is 93458. Adding right heart catheterization to the same study moves the claim to 93461.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CPT code 93459 reports left heart catheterization with coronary angiography and bypass graft angiography, with left ventriculography included when performed.
Every code from 93454 to 93461 includes coronary angiography. What separates 93459 from 93458 is bypass graft angiography documented in the cath report.
The cath report must document arterial access, pressures, each native vessel injected, each bypass graft imaged, and whether a ventriculogram was performed.
Adding right heart catheterization moves the claim to 93461, not 93459 plus a second code. Supravalvular aortography (93567) and FFR (93571/93572) are separate add-ons.
Pabau’s claims management software builds CPT code selection into the documentation workflow, so coding errors surface before a claim is submitted.
CPT code 93459 is the AMA-maintained procedure code for coronary angiography with left heart catheterization and bypass graft angiography. It covers catheter placement in the native coronary arteries and in any bypass grafts, the contrast injections, and the imaging supervision and interpretation. Left ventriculography is included when the physician performs it.
In plain terms, 93459 is the diagnostic left heart cath for a patient who has had coronary artery bypass surgery. The descriptor names three graft types: Internal mammary, free arterial, and venous grafts. The code applies when the physician places a catheter in one or more of those grafts and images them.
The AMA licenses its descriptor text, so this page paraphrases it. Check the exact wording in your current CPT codebook.
Breaking the descriptor down shows what each element requires in the cath report. “Left heart catheterization” means the catheter crosses the aortic valve into the left ventricle, usually from a femoral or radial artery. “Coronary angiography” means selective contrast injections into the native coronary arteries.
Every code from 93454 to 93461 includes coronary angiography, so it never separates 93459 from its neighbors. “Bypass graft angiography” is the element that does. For ventriculography, “when performed” means the left ventricle injection is included in the code value if done, and skipping it does not change the code.
Billing errors on 93459 tend to happen at the bundling boundary. The code bundles several services that cannot be billed separately, and excludes others that are legitimate add-on or companion codes.
Right heart catheterization is the exception that trips coders up. It is not billed as a second code alongside 93459. When the physician also performs right heart cath in the same session, the whole study moves to 93461.
The “when performed” language for ventriculography is another common point of confusion. It does not mean a lower-paying code applies when the ventriculogram is skipped.
The same code, 93459, applies whether or not the ventriculogram was done, as long as the coronary and bypass graft angiography were performed. The report only needs to note whether it was done and, if not, give a brief clinical rationale.
CPT 93459 differs from CPT 93458 in one respect: 93459 adds catheter placement in bypass grafts and bypass graft angiography. Both codes include left heart catheterization, coronary angiography, and left ventriculography when performed. The common error is billing 93459 for a post-CABG patient when the report never documents graft injections.
The deciding question is whether the physician placed a catheter in a bypass graft and imaged it. A history of bypass surgery does not support 93459 on its own. If the grafts were not injected, or the report describes them only from a prior study, 93458 is the correct code.
The reverse error costs revenue. A graft study coded as 93458 loses the extra work value the grafts carry.
Neither code fits a left heart cath with no coronary angiography at all, such as a hemodynamic valve assessment. That study is reported with 93452.
CPT code 93459 sits within a structured family. Codes 93451-93453 cover heart catheterization without coronary angiography, while every code from 93454 to 93461 includes it. Within that group, the odd-numbered codes add bypass graft angiography. Ventriculography is included when performed only in codes that include left heart cath.
Use this reference table to select the code that matches what the cath report documents.
Read as a decision, the eight codes that include coronary angiography come down to two questions about the cath report.
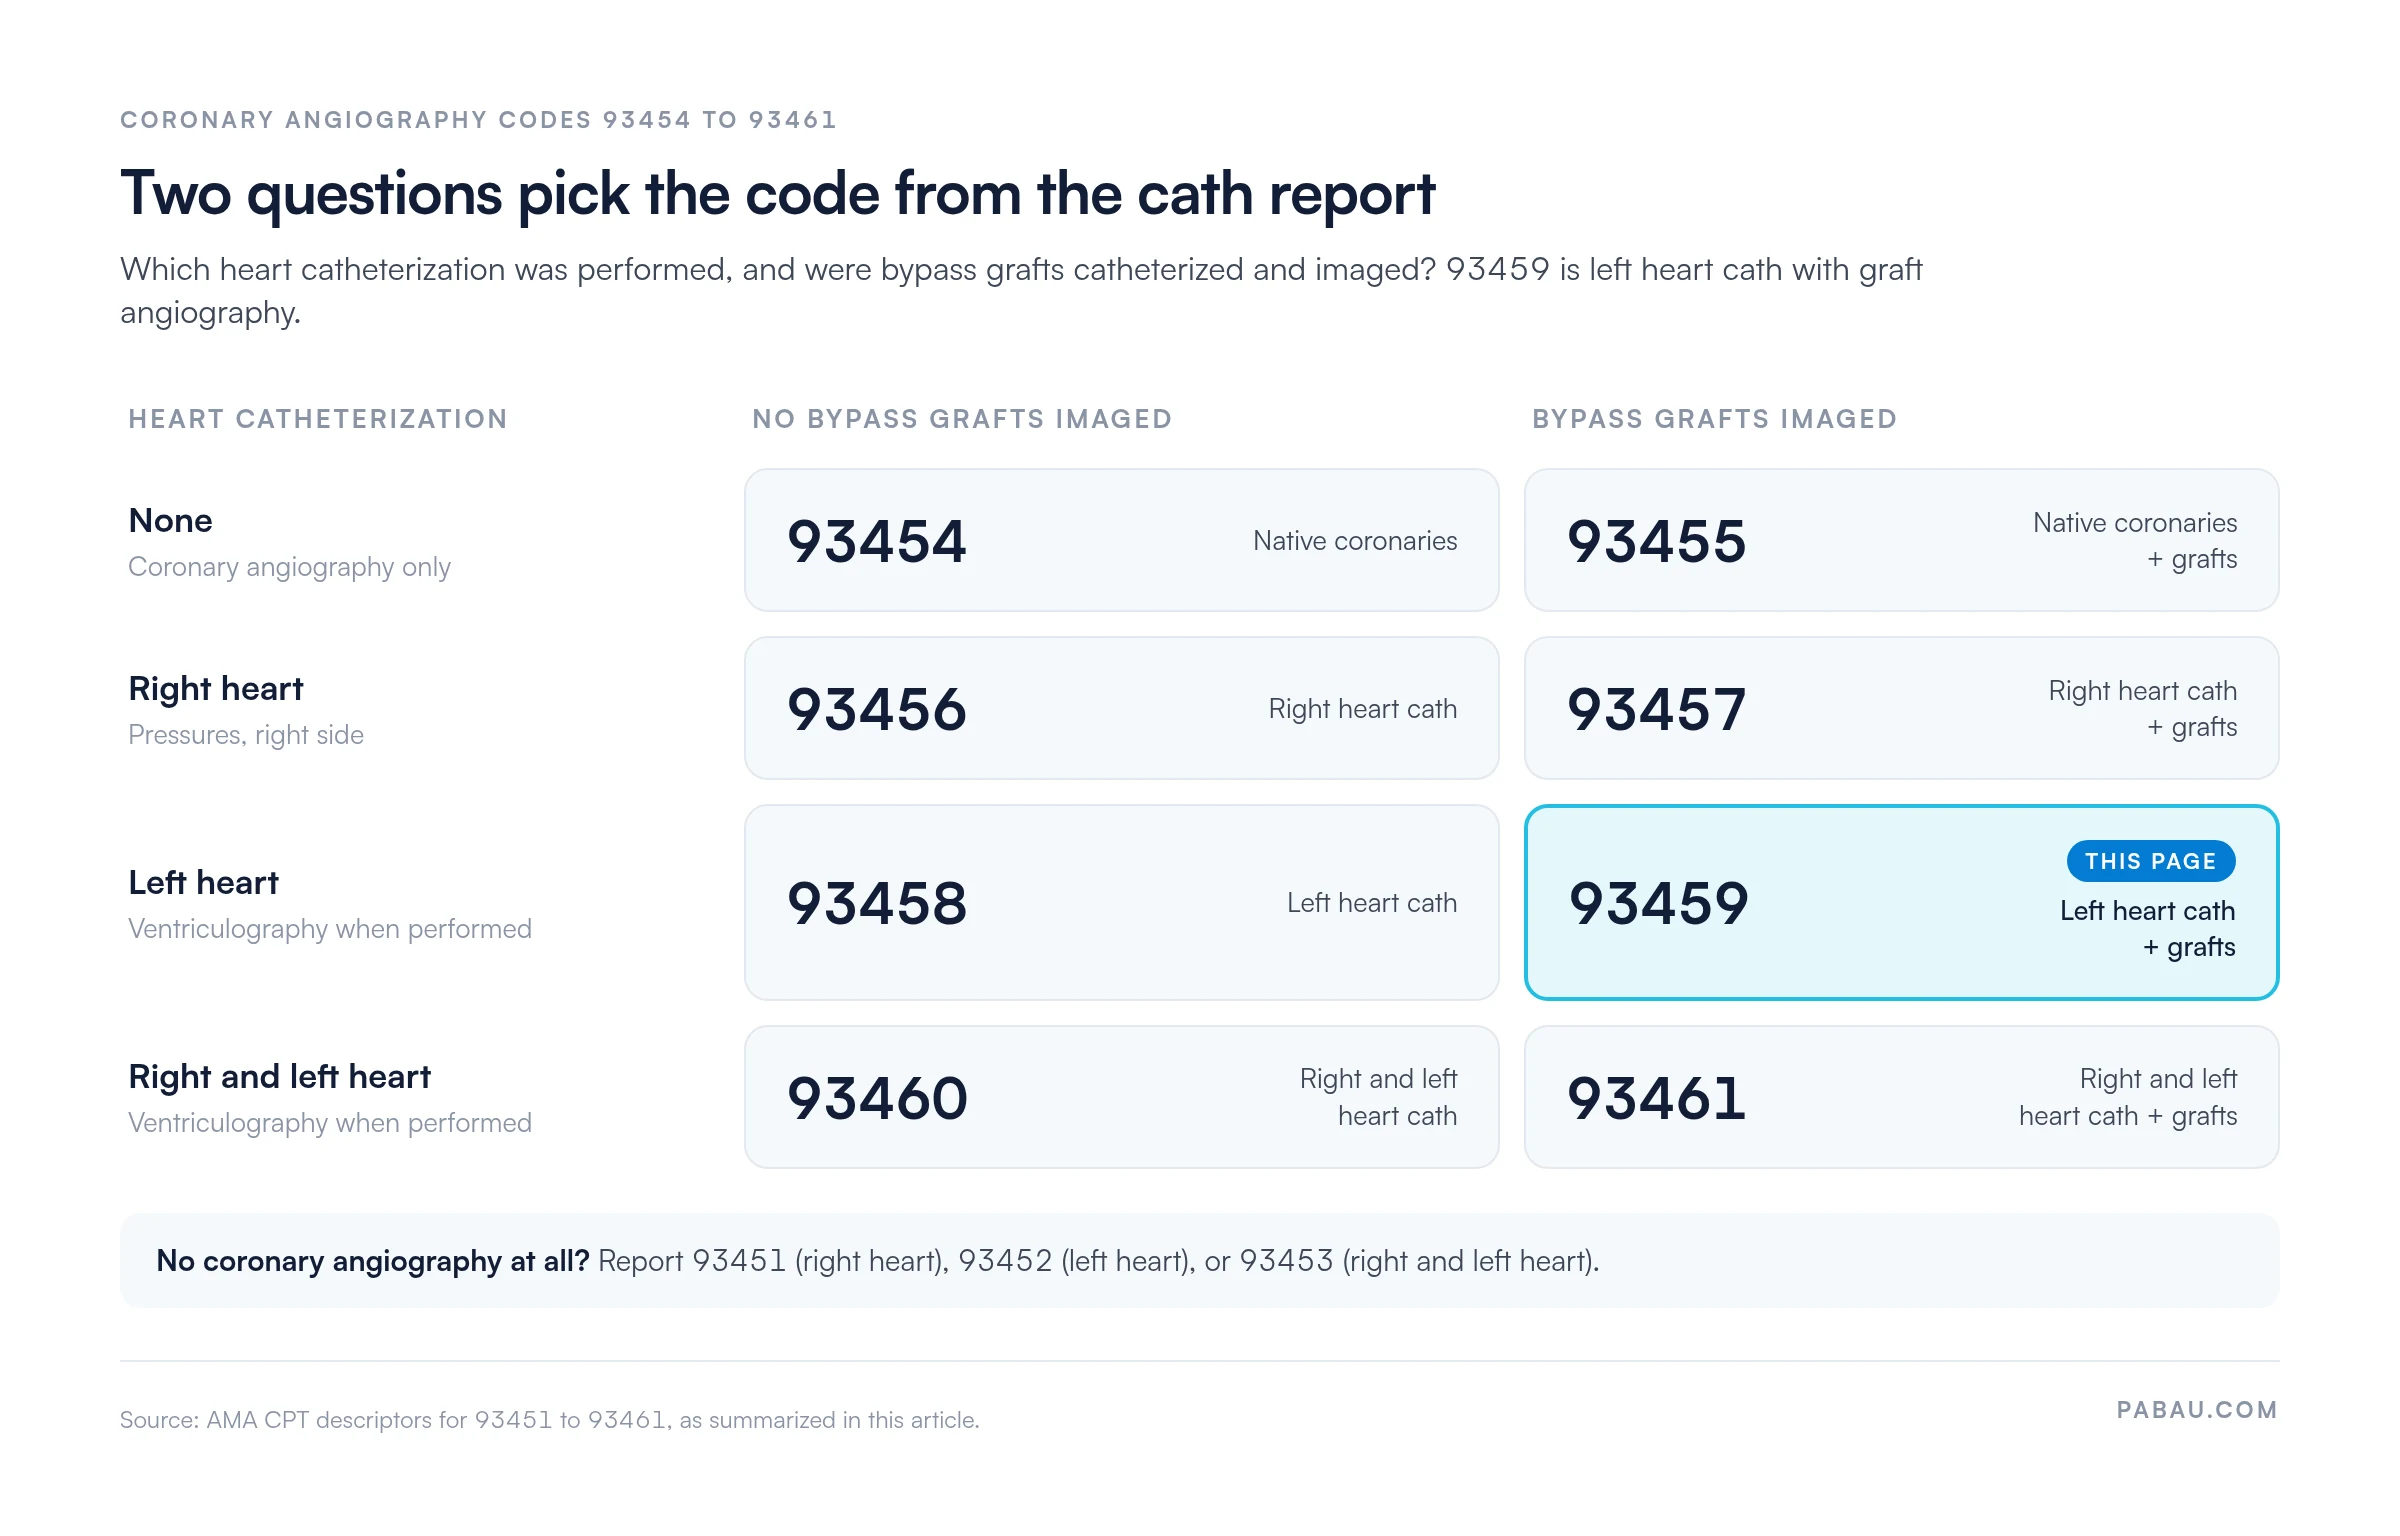
For descriptor lookups, the AAPC Codify CPT lookup provides a searchable index of the full 9345x series with crosswalk context.
The cath report is the only document that can defend a 93459 claim. A clean claim for this code requires specific elements that map directly to the descriptor’s components. Missing any one of them creates the conditions for a denial or audit exposure.
Run a pre-billing cath report checklist before submitting 93459 claims. Confirm the report names each native coronary artery and each bypass graft injected, and states whether a ventriculogram was performed. A post-CABG history with no graft injections documented is the most predictable denial trigger for this code.
Modifier selection for 93459 depends on the billing setting and whether the physician provided only the professional component, only the technical component, or both. Claims management software that checks modifier logic at the point of code selection catches these errors before the claim is submitted.

Modifier acceptance varies by payer and plan. Payer-specific modifier rules should be verified through each payer’s policy manual or provider portal before claim submission. No modifier is universally accepted across all commercial plans.
Medicare reimbursement for CPT code 93459 follows the standard Physician Fee Schedule two-rate structure, with separate allowed amounts for facility and non-facility settings. The CMS Physician Fee Schedule lookup tool provides the current national rates by code, modifier, and locality.
Practices should use the FastRVU 2026 RVU lookup to verify Work, Practice Expense, and Malpractice RVU values for the current year.
Medicare rates change annually with the Physician Fee Schedule update each January. Geographic Practice Cost Indices (GPCIs) apply locality-specific adjustments, so a high-cost metro area pays differently from a rural locality for the same code. Always verify the current-year rate from CMS data rather than relying on prior-year figures.
Commercial payer rates for CPT code 93459 vary widely, because individual contracts set them rather than the Medicare fee schedule. Check each payer’s contracted fee schedule before quoting a patient estimate.
Prior authorization requirements for CPT code 93459 are payer-dependent and cannot be stated as a universal rule. Many major commercial plans require pre-authorization for elective cardiac catheterization, while Medicare does not impose prior authorization for most diagnostic cardiac catheterization in standard settings. Check each payer’s policy before scheduling elective procedures.
Practices with established billing compliance requirements build payer-specific prior auth workflows into the scheduling step, well before the procedure date.
Systematic denial management workflows for 93459 should address these recurring patterns:
For the reason codes a payer returns on the remittance advice, see our guide to medical billing denial codes.
Several services are performed alongside left heart catheterization and carry their own CPT codes. Whether they can be billed separately from CPT code 93459 depends on NCCI edit pairs and payer-specific bundling policies. Use a medical claims clearinghouse with built-in edit checking to flag these combinations before they reach the payer.
The coronary flow reserve add-ons split by vessel count. The first vessel measured goes on 93571, and every further vessel in the same session adds one unit of 93572.
NCCI edit pairs for the 9345x series are updated quarterly by CMS. Verify current edit pairs through the CMS NCCI edits page before submitting claims with companion codes. Bundling rules can change between calendar years.
When a diagnostic left heart cath leads to same-day PCI, document the separate decision to proceed with intervention after reviewing diagnostic findings. Payers occasionally challenge same-day diagnostic and interventional billing as a single service. A clear documented decision point in the cath report supports both codes.
In many cardiology practices, a coder reads the dictated cath report days after the procedure and works out the code by hand. The 93458 versus 93459 call then depends on whether the coder spots a graft injection buried in the narrative.
Pabau, the practice management and billing platform we build, moves that decision closer to the procedure. Its clean claim workflow captures procedure elements at the point of charting, rather than reconstructing them from memory at billing time. Code selection, modifiers, and companion add-ons are then checked against what the record shows before the claim goes out.
Pabau submits claims electronically through Claim.MD, its US clearinghouse partner. That connection supports real-time eligibility checks and 837P claim submission for cardiac catheterization services across thousands of US payers. The result is fewer claims held for coding queries and fewer 93459 denials traced back to a missing graft note.

Pabau’s claims management workflow builds code selection, modifier logic, and documentation checks into charting. Cardiac catheterization claims reach the payer clean the first time.

CPT code 93459 comes down to one habit. Read the cath report for bypass graft injections before choosing the code. Coronary angiography sits inside every code from 93454 to 93461, so it cannot settle the choice. Graft angiography can.
Practices that build graft documentation into the report template stop guessing between 93458 and 93459. They also stop losing work value on post-CABG studies that were coded down. The trade-off is a few seconds of structured charting per case, which costs far less than one appeal.
Book a demo to see how Pabau’s claims management software supports accurate cardiac catheterization billing for your practice.

Need to understand how clearinghouse claim submission works end to end? Our Claim.MD clearinghouse guide covers 837P submission, real-time eligibility, and ERA processing for US cardiology practices.
Want to understand the full revenue cycle behind cardiac claims? What is revenue cycle management explains how each billing step from documentation to payment posting connects in a cardiac practice.
Looking for a reference on superbill setup for cardiology? Superbill documentation guide covers how to structure a superbill that captures cardiac cath codes, modifiers, and companion services accurately.
CPT code 93459 includes left heart catheterization, coronary angiography of the native vessels, catheter placement in bypass grafts, and bypass graft angiography. It also covers imaging supervision and interpretation, left heart pressure measurements, and left ventriculography when performed. Supravalvular aortography and FFR are reported with separate add-on codes.
Both codes include left heart catheterization, coronary angiography, and left ventriculography when performed. CPT 93459 adds catheter placement in bypass grafts and bypass graft angiography. Select 93459 only when the cath report documents graft injections, and 93458 when only the native coronary arteries were imaged.
Yes. Coronary angiography is a core component of CPT 93459, but it is also part of every code from 93454 to 93461. It is not what distinguishes 93459 from 93458. The distinguishing element is bypass graft angiography, which is also why 93459 carries a higher relative work value than 93458.
No. Moderate sedation is not bundled into CPT 93459, so it may be reported separately when documented. Use 99152 and 99153 when the physician performing the cath provides the sedation with an independent trained observer present. Use 99155-99157 when a different practitioner provides it. Confirm current NCCI edits and payer policy before billing.
Not as a separate code. When right heart catheterization is performed in the same session as a 93459 study, report CPT 93461 instead. That code covers right and left heart catheterization, coronary angiography, bypass graft angiography, and left ventriculography when performed. Billing 93459 alongside 93451 or 93453 risks an NCCI edit denial.
The most common modifier is -26 (professional component). Apply it when a cardiologist bills only the interpretation in a hospital outpatient cath lab, where the facility bills the technical component. Modifier -52 applies when the procedure is terminated before completion for clinical reasons, not merely because ventriculography was skipped. Modifier -59 marks a companion code that is genuinely a distinct procedural service. Payer acceptance varies, so verify modifier rules against each payer’s billing guide.



