HCPCS code L0638: Custom fabricated LSO billing guide
HCPCS code L0638 is a brace built for one patient HCPCS code L0638 is the Level ...

Last Updated: Nov 2, 2026
37224 was the CPT code for revascularization, endovascular, open or percutaneous, femoral, popliteal artery(s), unilateral; with transluminal angioplasty. The AMA deleted it effective January 1, 2026.
From January 1, 2026, femoral or popliteal angioplasty of the initial vessel is reported with 37263 or 37265. Code 37263 is for a straightforward lesion (stenosis), and 37265 is for a complex lesion (occlusion). Keep 37224 for corrected claims and appeals with earlier dates of service.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

The AMA deleted CPT code 37224 on January 1, 2026, along with the rest of the 37220–37235 lower-extremity revascularization family.
From January 1, 2026, report initial-vessel femoral or popliteal angioplasty with 37263 for a stenosis or 37265 for an occlusion.
Legacy 37224 covered angioplasty only, and the femoral/popliteal territory took one code per leg with no add-on codes.
The 2026 series adds one add-on code per leg for a second femoral/popliteal vessel, plus lithotripsy add-on 37279.
Keep 37224 for corrected claims and appeals with dates of service before 2026, using the descriptor that applied on that date.
CPT code 37224 no longer exists for current claims. The American Medical Association deleted it effective January 1, 2026, together with the whole 37220–37235 lower-extremity revascularization family.
For a femoral or popliteal angioplasty of the initial vessel on or after that date, the replacement depends on the lesion. Report 37263 for a straightforward lesion and 37265 for a complex lesion. SCAI’s 2026 guidance defines a straightforward lesion as a stenosis and a complex lesion as an occlusion. Under 2026 CPT coding guidance, that occlusion is a 100% total blockage.
The 16 deleted codes were replaced by 46 new codes, 37254–37299. They are organized by four vascular territories and by lesion complexity:
Claims for procedures performed before January 1, 2026 still use 37224 and its legacy family. That matters for late charges, corrected claims and appeals.
CPT code 37224 applied to dates of service through December 31, 2025. The AMA descriptor read: Revascularization, endovascular, open or percutaneous, femoral, popliteal artery(s), unilateral; with transluminal angioplasty.
The code described angioplasty as the only therapy in the femoral/popliteal territory of one leg. That territory took exactly one code per leg, chosen by the most extensive procedure performed there:
Unlike the iliac and tibial/peroneal territories, the legacy femoral/popliteal territory had no add-on codes. The tibial/peroneal territory used 37228–37231 for the initial vessel and add-on codes 37232–37235 for each additional vessel.
When you correct or appeal a 2025 claim, match the code to the most intensive service documented in the territory. A note that documents a stent supports 37226 or 37227, never 37224. Angioplasty with a drug-coated balloon and no other therapy was still reported as 37224. Good medical billing workflows read that one code from the operative note.
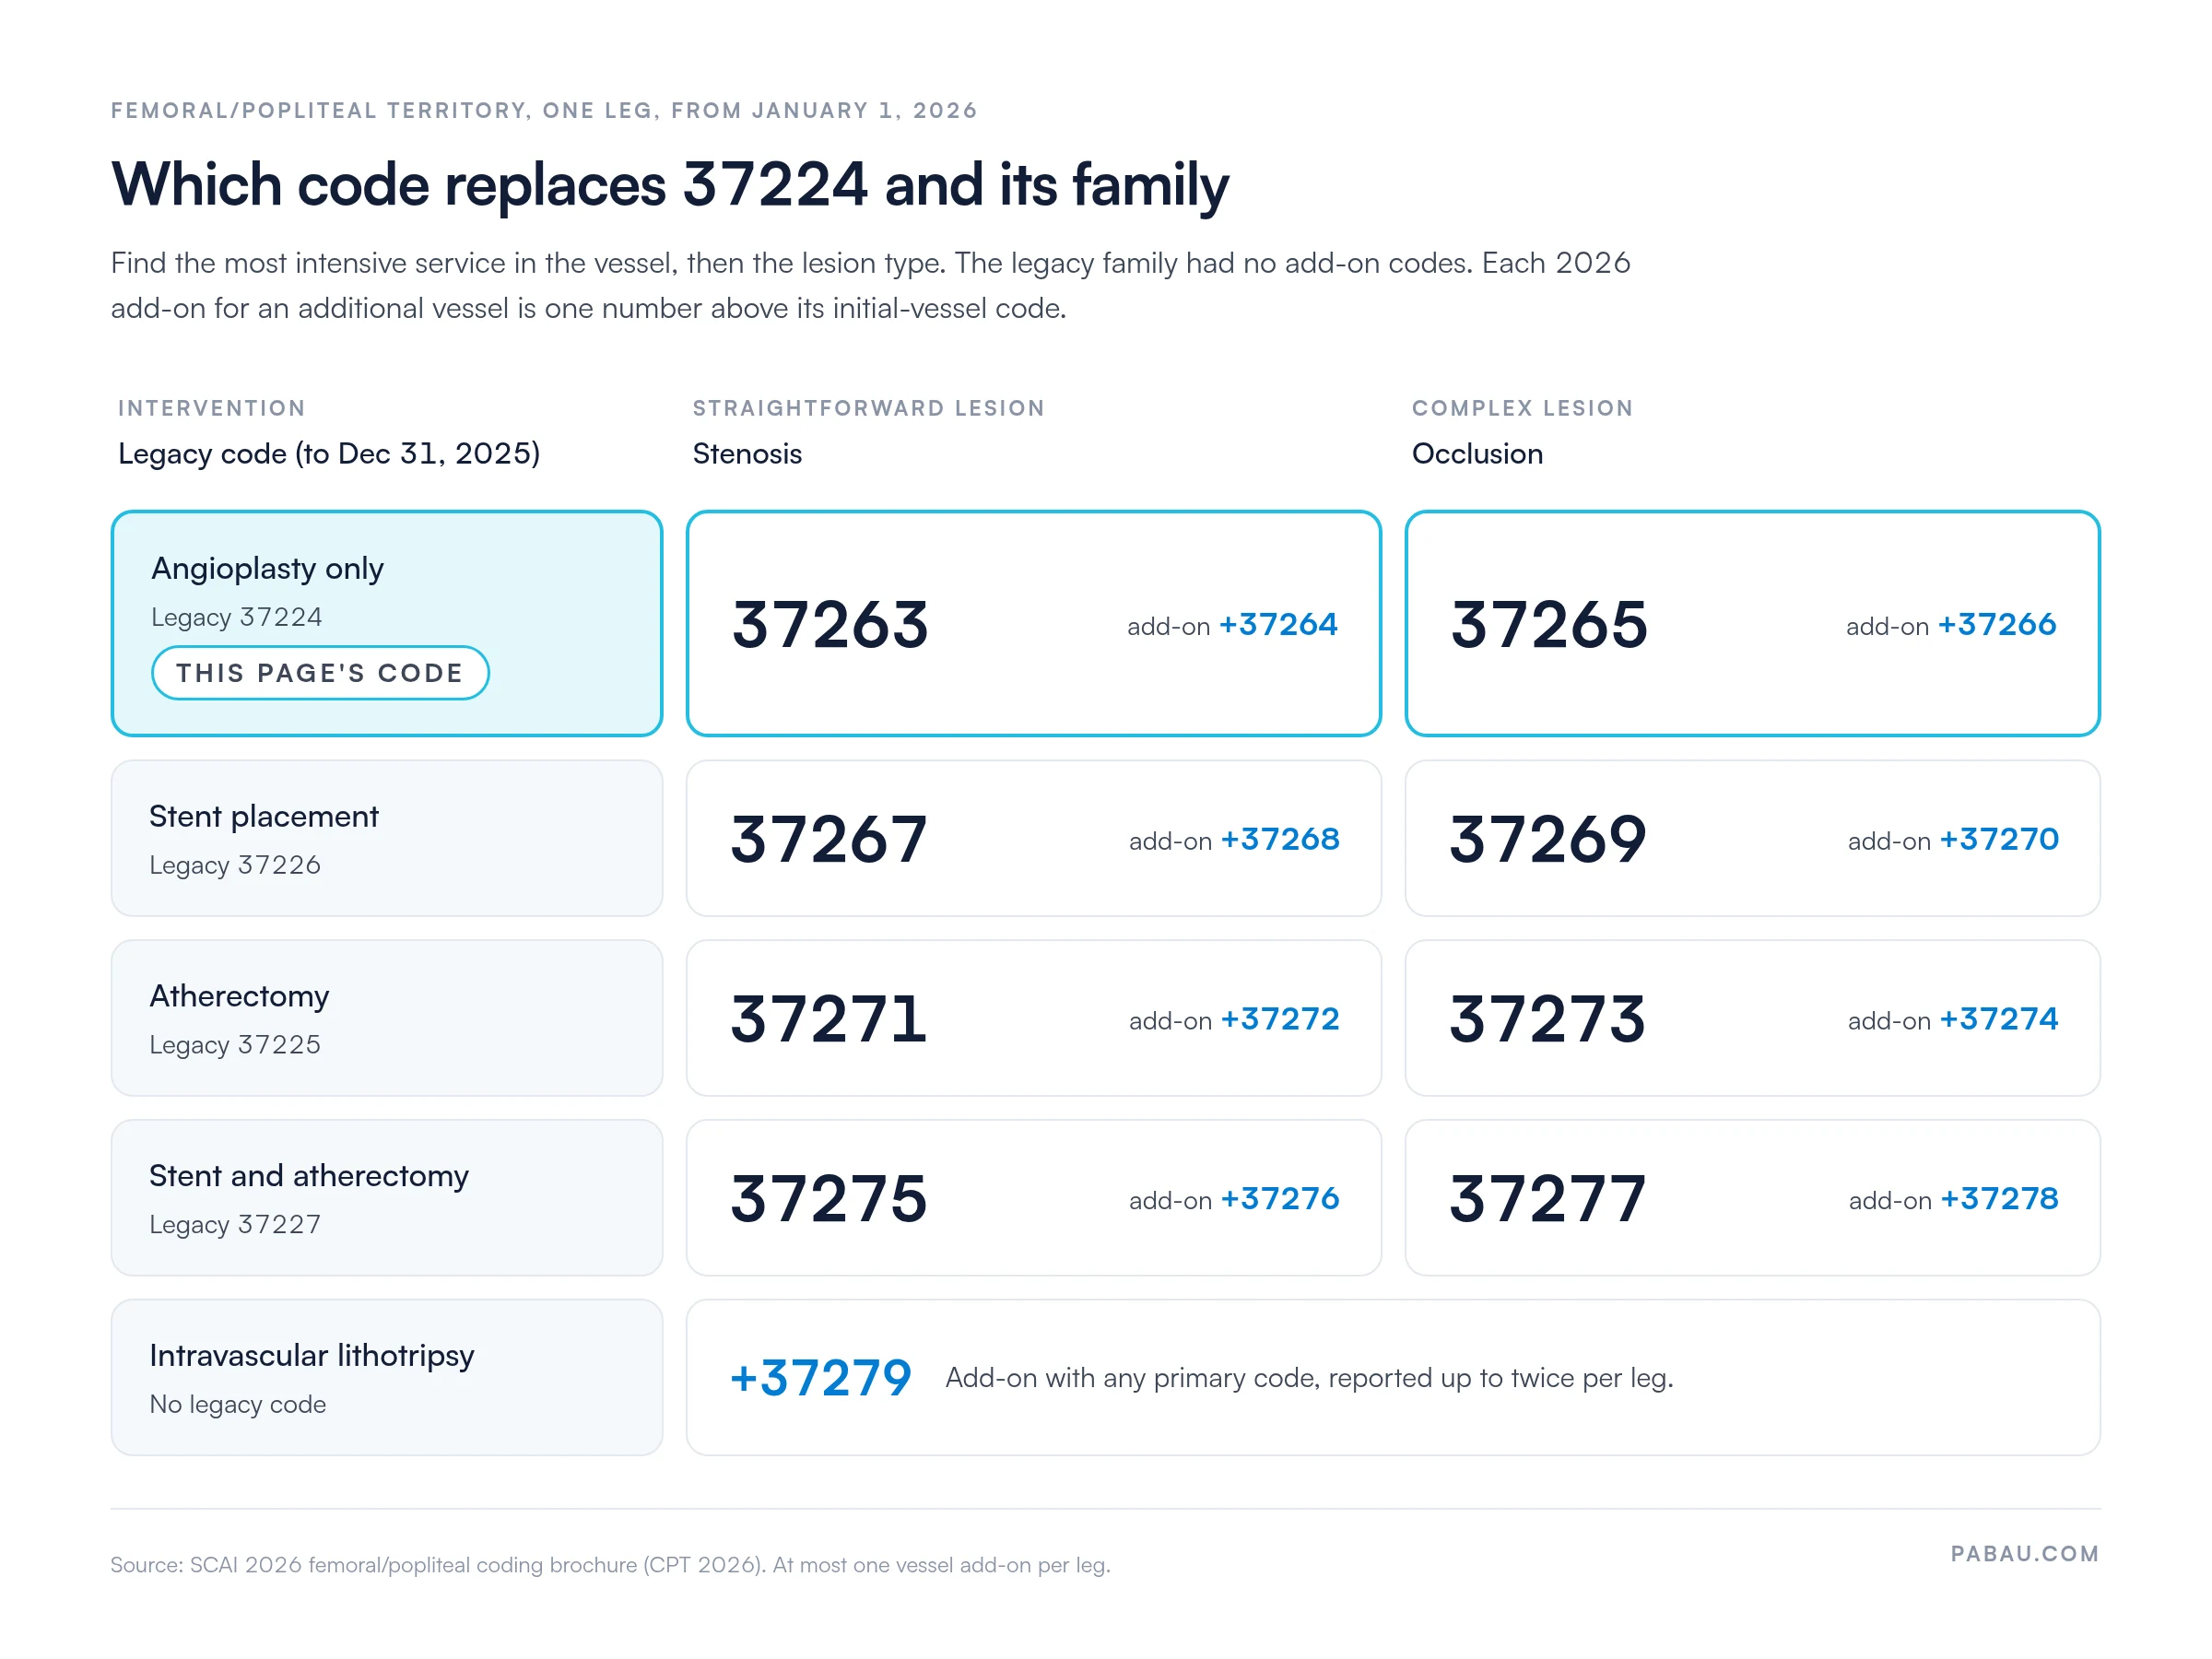
Each deleted femoral/popliteal code splits into two new codes, one for a straightforward lesion and one for a complex lesion. The crosswalk below follows SCAI’s 2026 femoral/popliteal code summary.
A plus sign marks an add-on code, which is reported with a primary code and never on its own. In the femoral/popliteal series, the odd-numbered codes 37263–37277 are initial-vessel codes and the even-numbered codes 37264–37278 are add-ons. The tibial/peroneal series runs the other way, so check the number against the territory.
The 2026 descriptor for 37263 covers unilateral transluminal angioplasty in the femoral and popliteal vascular territory, open or percutaneous. It includes every maneuver needed to access and selectively catheterize the artery and cross the lesion.
It also includes the imaging guidance and radiological supervision and interpretation for the angioplasty within the same artery. Code 37265 carries the same wording but ends in “complex lesion, initial vessel” instead of “straightforward lesion, initial vessel.”
Lesion complexity is the new decision point, and the operative note has to settle it. SCAI’s 2026 guidance sets the rule: a stenosis is straightforward and an occlusion is complex. Under 2026 CPT coding guidance, that occlusion is a 100% total blockage. Then apply the territory rules:
The grid below puts both choices on one page. Find the row for the most intensive therapy, then read across to the lesion type.
Billing the femoral/popliteal series for work done in a tibial or peroneal artery is a costly coding error. That work belongs in 37280–37295, and payers that compare the claim against the operative note will deny or recoup.
Treating the iliac or tibial/peroneal segment in the same session is a separate territory, so it takes its own primary code. A lesion that crosses territories and is treated with a single therapy is reported with one code.
The new descriptors fold access, catheterization and imaging into each code. Billing them separately on the treated vessel is a common unbundling denial.
Payers need a diagnosis that establishes medical necessity for the revascularization. Atherosclerosis of native arteries of the extremities, I70.2-, is the usual indication. Several payers also want the Rutherford or Fontaine classification recorded in the operative note.
Verify each code in the ICD-10-CM FY2027 tabular list before use. Always code to the highest level of specificity available, including laterality. An unspecified code when laterality and symptom class are documented is a common audit target.
Modifier choice depends on whether both legs were treated, or whether a separate procedure shares an NCCI edit with the revascularization code.
SCAI’s 2026 guidance reports interventions on each leg separately and allows no more than one add-on code per leg in the femoral/popliteal territory. For bilateral procedures, SCAI puts modifier 50 on the base codes and reports the add-on codes twice. Confirm bilateral handling and RT/LT or 59/XS line layout with each payer before you submit.
The operative report decides the code under the 2026 rules. Every element below should appear in the note to meet medical billing compliance requirements.
A note that says “SFA angioplasty performed” without the lesion type cannot support either 37263 or 37265.
Prior authorization rules for femoral and popliteal angioplasty vary by payer, plan type and setting. Elective outpatient cases are the most likely to need approval. Plans had to reload their policies with the 2026 codes, so check that an approval names 37263–37279 rather than 37224.
An authorization issued under 37224 for a 2026 date of service may not match the claim. Ask the plan to update it before the procedure, not after the denial.
Medicare does not pay 37224 on a 2026 date of service, because the code is no longer valid. Payment for femoral and popliteal angioplasty now flows through 37263–37279, valued in the CMS Physician Fee Schedule lookup tool.
Rates are adjusted by the geographic practice cost index for your locality, so the national rate is only a baseline. In a hospital outpatient department, the facility payment follows the APC assigned under OPPS instead. The FastRVU RVU lookup tool shows the RVU breakdown without a CMS account.
Check eligibility before the procedure date, while a coverage problem can still be fixed without a denial. Effective revenue cycle management puts that check inside the scheduling workflow.
Denials on these claims cluster around a handful of causes. Fixing each one before submission is where a denial management workflow pays off most.
Review the denial codes your practice receives most often, sorted by code family rather than dollar amount. That view shows which pattern costs you the most each quarter.
For legacy 37224 claims with 2025 dates of service, the usual fix is the intervention level. If the note documents atherectomy or a stent, correct the claim to 37225, 37226 or 37227.
Add a required stenosis-or-occlusion field to your operative note template. Coders then pick the straightforward or complex femoral/popliteal code from the note, without sending a query back to the physician.
A code deletion hits a vascular practice in three places at once: the charge, the authorization and the claim. Practices that enter charges by hand often find out from the first wave of denials.
Pabau, the practice management and billing platform we build, validates every claim for missing or invalid details before it leaves the practice. Its claims management software sends electronic CMS-1500 claims through Claim.MD and runs real-time eligibility checks.
Electronic remittance advice comes back matched to each claim, so your team sees what was paid and what was denied. Pair that with a clean claim checklist, and a stale 37224 charge gets corrected before it turns into an appeal.

Pabau checks every claim for missing or invalid details before submission and runs real-time eligibility checks through Claim.MD. Remittance advice comes back matched to each claim, so your team catches a deleted code before the payer does.

Treat 37224 as a historical code. It still matters for 2025 dates of service, corrected claims and appeals, and it should appear nowhere else.
The larger change is in the operative note. Under the 2026 codes, the difference between a stenosis and an occlusion moves the claim between 37263 and 37265. A second treated vessel now earns an add-on code that the legacy family never had.
A practice that records the vessel, the lesion type and the crossing in every note will code the new series correctly the first time. Book a demo to see how Pabau checks every claim for missing or invalid details before it reaches the payer.

Need a guide to claim denial resolution? Denial management in healthcare walks through how to structure an appeal workflow that reduces repeat denials across CPT code families.
Want to understand clearinghouse claim routing? Medical claims clearinghouse explains how electronic claim submission routes from your practice management system to the payer.
Looking for ERA and remittance guidance? Electronic remittance advice covers how to read 835 ERA files and match them to posted payments in your billing system.
Coding below the knee instead? CPT code 37228 maps the deleted tibial/peroneal angioplasty code to its 2026 replacements, 37280 and 37282.
No. The AMA deleted CPT code 37224 effective January 1, 2026. Use it only for claims with dates of service on or before December 31, 2025.
For femoral or popliteal angioplasty of the initial vessel, 37263 replaced it for a straightforward lesion and 37265 for a complex lesion. A second vessel uses add-on code 37264 or 37266.
Lesion complexity. SCAI’s 2026 guidance defines a stenosis as straightforward, coded 37263, and an occlusion as complex, coded 37265. Under 2026 CPT coding guidance, that occlusion is a 100% total blockage. The operative note must document which one was treated.
No. Legacy 37225 was femoral/popliteal atherectomy, and it already included any angioplasty in that territory. The territory took one code per leg, so 37225 was reported alone, or 37227 if a stent was also placed.
Yes. The even-numbered codes 37264–37278 cover an additional vessel, and only one may be reported per leg. Lithotripsy add-on 37279 may be reported up to twice per leg.
The I70.2- series for atherosclerosis of native arteries of the extremities is the usual category. Common pairings include I70.211 and I70.212 for claudication and I70.221 and I70.222 for rest pain. Code to the highest specificity, including laterality.
It depends on the payer and the setting. Traditional Medicare generally does not require it for covered procedures. Many Medicare Advantage plans and most commercial payers require PA for elective outpatient cases. Confirm with each plan before scheduling.