


CCSD code G5100: Bypass of duodenum billing guide
CCSD code G5100 bills a bypass that leaves the duodenum in place CCSD code G5100...

Last Updated: Oct 16, 2026

CPT code 11311 covers the shaving of a single epidermal or dermal lesion measuring 0.6 to 1.0 cm. The listed sites are the face, ears, eyelids, nose, lips, and mucous membrane.
Every code from 11300 to 11313 uses the same epidermal or dermal wording. Only the anatomic group and the measured diameter separate one code from another.
Measure the lesion before removal and never add surgical margins to reach a tier. Margins belong to the excision codes.
In 2026 the code carries 1.07 work RVUs and 3.96 total non-facility RVUs. That is about $132 nationally before any geographic adjustment.
Practice management software like Pabau keeps the site, the measurement, and the clinical indication in one patient record. Your coder and any reviewer then read the same note.
CPT code 11311 bills the shave removal of a single epidermal or dermal lesion measuring 0.6 to 1.0 cm. The listed sites are the face, ears, eyelids, nose, lips, and mucous membrane.
The American Medical Association (AMA) owns the CPT code set, and it splits the shaving family into three anatomic series. A lesion of this size on the scalp or the forearm belongs to a different series and pays a different amount.
Below you get the official descriptor, the full 11300 to 11313 selection grid, and the 2026 RVUs. Modifiers, ICD-10 pairings, documentation requirements, and common coding errors follow after that.
CPT code 11311 describes the shaving of a single epidermal or dermal lesion measuring 0.6 to 1.0 cm. Specifically, the listed sites are the face, ears, eyelids, nose, lips, and mucous membrane.
The code sits in the Integumentary System section of the CPT manual. Its subsection, Shaving of Epidermal or Dermal Lesions, runs from 11300 to 11313. Per the AMA CPT code set overview, shaving means sharp removal with a blade or razor, without a full-thickness dermal excision.
The lesion comes off at or just below the plane of the surrounding skin. The base is then left to heal by secondary intention, so no suture closure is involved.
Sending the specimen to pathology is optional and does not change the code. Intent does change it. If the clinician performed a tangential biopsy for diagnosis, the biopsy codes apply instead.
Two conditions must both be true before you can report 11311. The lesion has to sit in the facial anatomic group, and the measured diameter has to fall between 0.6 and 1.0 cm.
The 11300-11313 family is three anatomic series of four size tiers each, and nothing else. Codes 11300-11303 cover the trunk, arms, and legs. Codes 11305-11308 cover the scalp, neck, hands, feet, and genitalia, and codes 11310-11313 cover the face, ears, eyelids, nose, lips, and mucous membrane. Choosing a level means weighing problems addressed, data reviewed and risk, which is what MDM documentation covers. A superbill form is not a claim form, but it carries the same data the patient insurer will ask for.
Within each series the four tiers step up by size. They run 0.5 cm or less, 0.6 to 1.0 cm, 1.1 to 2.0 cm, then over 2.0 cm. CPT code 11311 is the second tier of the facial series.
One thing the descriptors never do is separate codes by tissue depth. All fourteen carry the identical phrase, epidermal or dermal lesion. A note that records how deep the shave went is useful clinically, but it cannot move you from one code to another.
The grid below carries the 2026 total non-facility RVU for every code in the family, taken from the CMS Physician Fee Schedule relative value files. Read it as a price list for getting the series wrong.
The facial series pays the most at every tier, which is why habit is expensive here. A 0.8 cm lesion on the cheek billed as 11306 gives up 0.43 RVU, or about $14 per claim at the 2026 national rate. Billed as 11301 it gives up 0.48 RVU, close to $16.
The size boundary below 11311 is worth the same kind of arithmetic. One millimeter separates a 0.5 cm lesion from a 0.6 cm lesion, and it separates 11310 from 11311. That millimeter is worth 0.62 RVU, or roughly $21 per claim.
Measure before you remove, not after. Specimens contract once they are off the patient, and the pre-procedure diameter is the figure that sets the code. The CMS billing article A57113 states that the measurement is made prior to removal.
Practices using an integrated measurements tracking tool can capture that number at the point of care. The alternative is reconstructing it from memory weeks later, which no reviewer accepts.
One rule separates this family from the excision codes. Shave removal is sized on the lesion diameter alone. Excision codes are sized on the lesion plus the narrowest margin, doubled, so adding margins to a shave measurement quietly overstates the tier.
Record the diameter to one decimal place in centimeters, as a required numeric field rather than free text. On the face, the 0.5 and 1.0 cm boundaries sit one millimeter from the next tier in either direction. A note reading around 1 cm cannot defend either 11311 or 11312, while 0.9 cm measured prior to removal defends 11311 on its own.
The facial series is the only one in this family that borders other CPT chapters. That is where most of its miscoding happens. Three boundaries are worth knowing before you report 11311.
Eyelids. Use 11310-11313 when the lesion involves mainly the skin of the eyelid. Once the removal takes in the lid margin, the tarsus, or the palpebral conjunctiva, the eyelid excision codes apply, and 67840 is the usual choice. The operative note has to say which structures came off.
Lips. A lesion on the skin of the lip stays in this family. A lesion on the vermilion border or the mucosal surface is a different anatomic target, and it also takes a different ICD-10 code.
Mucous membrane. The descriptor does include mucous membrane, so an intraoral shave can be reported here. If the documentation instead describes excision of mucosa and submucosa of the vestibule of the mouth, the 40810-40816 family is the accurate one.
Within that range, the repair performed selects the code.
Miscoding a shave removal as a biopsy or an excision is one of the steadier audit findings in dermatology. The three procedures differ by technique, depth, closure, and code family.
CMS article A57113 is explicit on the biopsy boundary, and it tells you not to report 11300-11313 when a tangential shave biopsy was performed. Each additional lesion sampled in that session takes the add-on code 11103.
Destruction is a fourth pathway that gets folded in by mistake. Freezing or curetting a premalignant lesion such as an actinic keratosis is destruction, and it belongs to 17000-17004. That family is sized by lesion count, not by diameter.
Debridement sits in the same chapter and is sized on a third basis again. Removing devitalized tissue down to muscle or fascia is muscle or fascia is 11043, measured in square centimeters of surface area.
Skin tags are a separate carve-out as well. They are reported with 11200 and counted rather than measured, however small the tag on the eyelid or neck happens to be.
Relative value units are the basis of Medicare payment under the Physician Fee Schedule. Work RVU covers clinician time and skill. Practice expense RVU covers overhead, and it splits by setting because office overhead differs from hospital overhead. Malpractice RVU covers professional liability.
The setting difference on this code is unusually wide. The non-facility total is more than two and a half times the facility total. The office absorbs the supplies, the room, and the staff time.
Verify the current year with the CMS Physician Fee Schedule search tool before you use these numbers in a compensation model.
Medicare payment is the total RVU multiplied by the annual conversion factor, then adjusted for your locality. For 2026 there are two conversion factors. Qualifying alternative payment model participants are paid at $33.5675, and everyone else at $33.4009.
Your actual payment will differ. Geographic practice cost indices move each locality up or down, and commercial payers set their own multiples of the Medicare rate. Treat these figures as the national baseline rather than as a quote.
Medicare covers shave removal when medical necessity is documented, and not otherwise. CMS billing and coding article A57113, which supports local coverage determination L34938, sets out the requirements for removal of benign skin lesions.
Cosmetic removal of a lesion that causes no symptoms and no functional problem is not a covered service. That line gets tested more often on the face than anywhere else, since a facial lesion a patient dislikes may be entirely asymptomatic.
CPT 11311 carries a multiple procedure indicator of 2, so the standard reduction applies. The highest valued procedure of the session pays in full, and each additional one pays at 50 percent. That reduction is expected and correct, so it is not a denial to appeal.
The code also has a 000-day global period. There is no postoperative window, which is why a separately identifiable visit on the same day can still be billed with modifier 25. The bilateral surgery indicator is 9, so the bilateral payment rule does not apply to this code at all.
Modifiers add context about how a procedure was performed without changing the code itself. Which ones you need depends on the scenario and the payer. Medicare rules and commercial payer rules diverge here more than coders expect, so confirm before you submit.
Every CPT claim needs a diagnosis code that establishes medical necessity. On the face this is a specificity problem more than a selection problem. Several of the relevant codes are category headers rather than billable codes.
The diagnosis also has to sit in the same anatomic region as the procedure. A scalp and neck code such as D22.4 contradicts an 11311 claim. A reviewer reads that mismatch as evidence the wrong CPT code was chosen. The pairings below reflect the FY2026 ICD-10-CM code set.
Pick the code that matches the documented finding for that encounter. A generic code where a specific one exists is a standing audit flag, and on the eyelid it is also a straightforward denial.
Documentation decides whether an 11311 claim survives review. The procedure note has to let a reviewer who has never seen the patient confirm the code without asking a question.
Digital clinical forms help here, because they capture the required fields at the point of care instead of leaving them to be reconstructed afterward. A note reading lesion removed from face supports nothing.
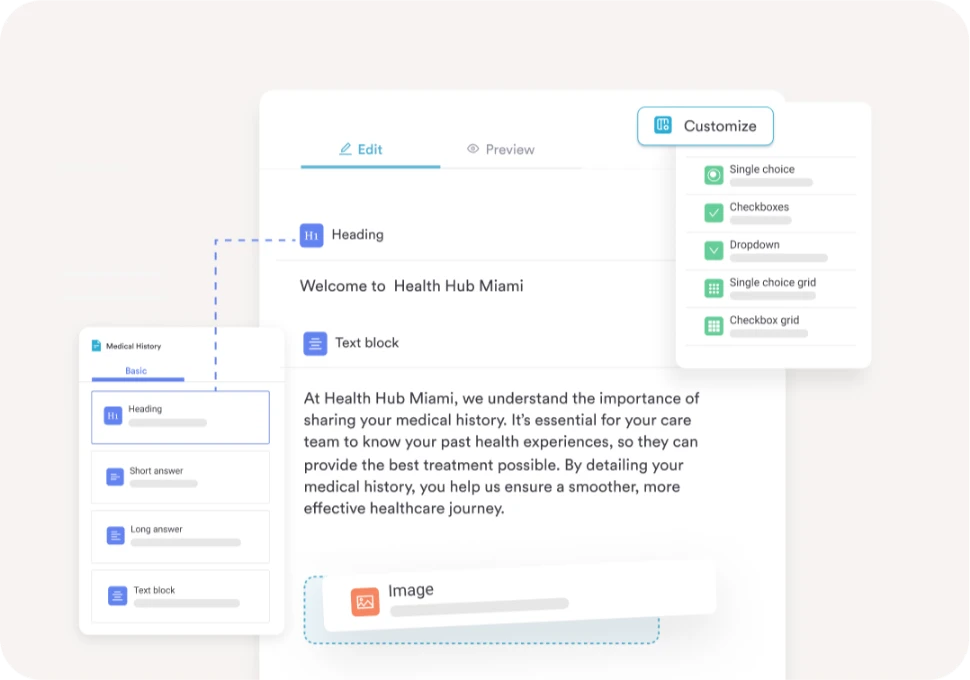
Errors in this family cluster around the anatomic series, the size tier, and confusion with neighboring code families. Each one maps to a documentation control that removes it. Build the control into the template and the error stops recurring.
Run a five-chart spot check before your next batch of shave removal claims. Pull five recent notes and confirm each one names the exact site, gives a pre-removal measurement in centimeters, describes the technique, and states the indication. If the same field is missing twice, it is a template problem rather than a coder problem. Fixing the template clears every future claim at once.
Most 11311 problems start before anyone builds a claim. The clinician records the procedure in one place. The coder then works from a summary that has lost the measurement or blurred the exact site.
Practice management software like Pabau removes that second copy. The note your coder reads is the note the clinician wrote.
The practical fix is a procedure template that will not close with a required field empty. Pabau’s skin clinic software lets you build a shave removal form with four required fields.
The form asks for the anatomic site, the pre-removal diameter in centimeters, the technique, and the indication. That turns the two variables 11311 depends on into a step nobody can skip.
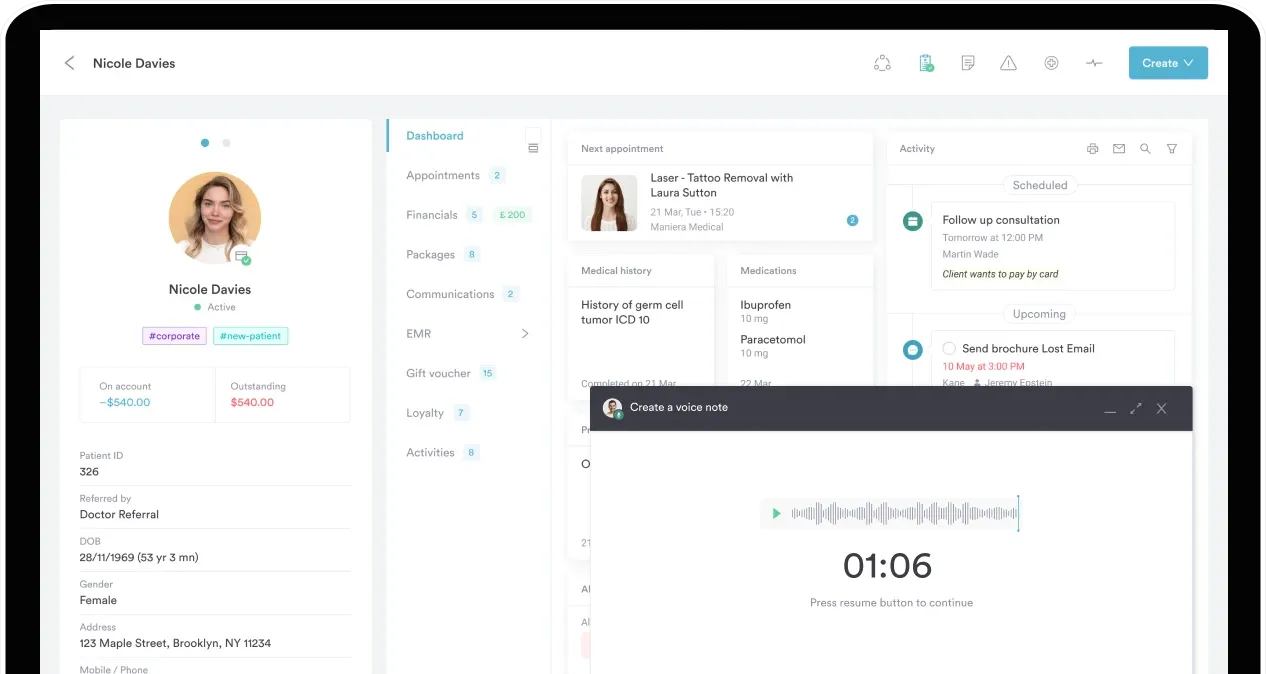
Pabau’s role in a US practice is the record rather than the clearinghouse. Your biller or billing service submits to Medicare, and what Pabau gives them is a complete, timestamped chart to code from.
That chart supplies the data your biller loads into the 837 claim file, the electronic format Medicare requires for professional claims.
When a reviewer requests support for a claim, everything comes out of one system. The procedure note, the photographs, the diagnosis codes, and the audit trail sit together rather than in three places.
For dermatology EMR software users, that consistency is what shortens an audit response. The documentation baseline is built into every encounter rather than added afterward.
Practices that combine Pabau’s patient record management with its compliance management tools spend less administrative time on records requests.
Practices still comparing platforms for this work can start with our review of medical billing software built for US practices.

Pabau keeps procedure notes, photographs, and lesion measurements in one patient record. Your coder never has to guess the site or the size behind a shave removal claim. Book a demo to see how dermatology practices set this up.

Getting 11311 right is a documentation habit more than a coding decision. Both conditions the code depends on are settled at the chairside, long before anyone opens a billing screen.
Almost every denial in this family traces back to a note that missed one of those two facts. The rest come from a coder defaulting to the scalp and neck series out of habit. Depth language the descriptors never asked for accounts for a few more.
Measure first, name the exact site, describe the technique, and say why the lesion had to go. On the eyelid, add a line about which structures were removed.
Pabau builds those habits into the encounter itself, so the documentation is right before the claim is ever created. To see how that works in a dermatology setting, book a demo with the Pabau team.

Is the facial lesion 0.5 cm or smaller? CPT code 11310 is the first tier of the same series, covering the face, ears, eyelids, nose, lips, and mucous membrane.
Does the lesion measure 1.1 to 2.0 cm? CPT code 11312 is the next tier up, with its own RVUs and payment amounts.
Is the facial lesion larger than 2.0 cm? CPT code 11313 is the top tier of the facial series.
Was the lesion excised rather than shaved? CPT code 11441 covers excision of a benign facial lesion in the same 0.6 to 1.0 cm band.
Was the intent diagnostic instead of therapeutic? CPT code 11102 is the tangential biopsy code that A57113 tells you to use instead.
CPT code 11311 bills the shaving of a single epidermal or dermal lesion measuring 0.6 to 1.0 cm. The listed sites are the face, ears, eyelids, nose, lips, and mucous membrane. It covers sharp removal with a blade or razor, without a full-thickness excision. The base heals by secondary intention rather than by suture closure.
Only the anatomic group differs. CPT 11311 covers the face, ears, eyelids, nose, lips, and mucous membrane, while 11306 covers the scalp, neck, hands, feet, and genitalia. Both take a lesion of 0.6 to 1.0 cm, and both use identical wording about epidermal or dermal tissue. Tissue depth never separates the two codes.
For 2026, CPT code 11311 carries a work RVU of 1.07 and a malpractice RVU of 0.11. The practice expense RVU is 2.78 in the non-facility setting and 0.34 in the facility setting. That gives 3.96 total non-facility RVUs and 1.52 total facility RVUs. At the 33.4009 dollar conversion factor, the national amounts are about 132.27 dollars and 50.77 dollars.
Medicare covers it only when the record documents medical necessity, per CMS billing and coding article A57113. Bleeding, itching, pain, repeated irritation, or a functional problem all qualify. Cosmetic removal of an asymptomatic lesion is not covered, and the patient signs an Advance Beneficiary Notice first. Your Medicare Administrative Contractor may add local criteria.



