ICD-10 code T87.52: Necrosis of amputation stump, left upper extremity
ICD-10 code T87.52 at a glance: Left arm, not left leg ICD-10 code T87.52 is the...

Last Updated: Oct 26, 2026
Billable Code Specific Code
T86.890 is the billable ICD-10-CM code for other transplanted tissue rejection. It reports rejection of a transplanted organ or tissue that has no T86 subcategory of its own, most often a pancreas graft.
The code is complete at six characters, takes no seventh character, and is valid for FY2027. It sits under the non-billable T86.89 group, beside separate codes for failure, infection and other complications. Assignment turns on two facts in the note. The graft has no dedicated subcategory, and the physician documents rejection. Miss either one and the claim belongs on a sibling code, so check both before you submit.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

T86.890 reports rejection of a transplanted organ or tissue that has no dedicated T86 subcategory, with pancreas graft rejection as the indexed example.
The code is billable at six characters and takes no seventh character, unlike most chapter 19 injury codes.
Failure, infection and other complications of the same tissue take T86.891, T86.892 and T86.898, so the physician’s complication word picks the sixth character.
Kidney, liver, heart, lung, skin, bone, cornea and intestine grafts have their own rejection codes, so T86.890 never applies to them.
Leave Z94 status codes off the claim, and sequence any GVHD, PTLD or transplant malignancy code after T86.890.
ICD-10 code T86.890 reports rejection of a transplanted organ or tissue that ICD-10-CM does not give its own subcategory. Its official descriptor is “Other transplanted tissue rejection.”
The Alphabetic Index sends pancreas transplant rejection straight here. The Tabular backs that up, listing “transplant failure or rejection of pancreas” as an inclusion term under the parent T86.89.
Code validity renews every October 1, so confirm T86.890 in the CDC ICD-10-CM browser tool after each annual release. Then check the graft against the map below before you settle on it.
The graft decides the subcategory before the complication decides the sixth character. Most transplanted organs have a dedicated rejection code, so T86.890 stays in play only when the graft has no named home.
The Index adds one more route. Under “Rejection, transplant,” the entry “specified NEC” also leads to T86.890. That covers a named graft with no subcategory, such as a hand or face allograft.
Two look-alikes trip coders. An intestine graft has its own T86.85 group, so its rejection is T86.850. A note that says “organ rejection” without naming the organ indexes to T86.91, not T86.890. Look up the alternative in our ICD-10-CM code library before you recode.
T86.89 is a non-billable parent, so every claim needs a sixth character. That character names what went wrong with the graft, and T86.890 is the one for rejection.
Rejection is the first branch, so T86.890 wins whenever the physician documents it and the graft still works. A documented failure moves the claim to T86.891. A graft infection moves it to T86.892, which also needs the organism code.
T86.898 is the catch-all for a named complication of other transplanted tissue that is not rejection, failure or infection. T86.890 is narrower. It applies only once the physician uses the word rejection, or a named rejection type.
So a pancreas graft thrombosis or an anastomotic leak goes to T86.898. Biopsy-proven acute cellular or antibody-mediated rejection of the same graft goes to T86.890. Picking T86.898 for rejection undercodes the encounter and hides the diagnosis from audit.
The quick test takes two steps. First, name the graft and check the map above. Then read the exact complication word the physician used, as the path below shows.
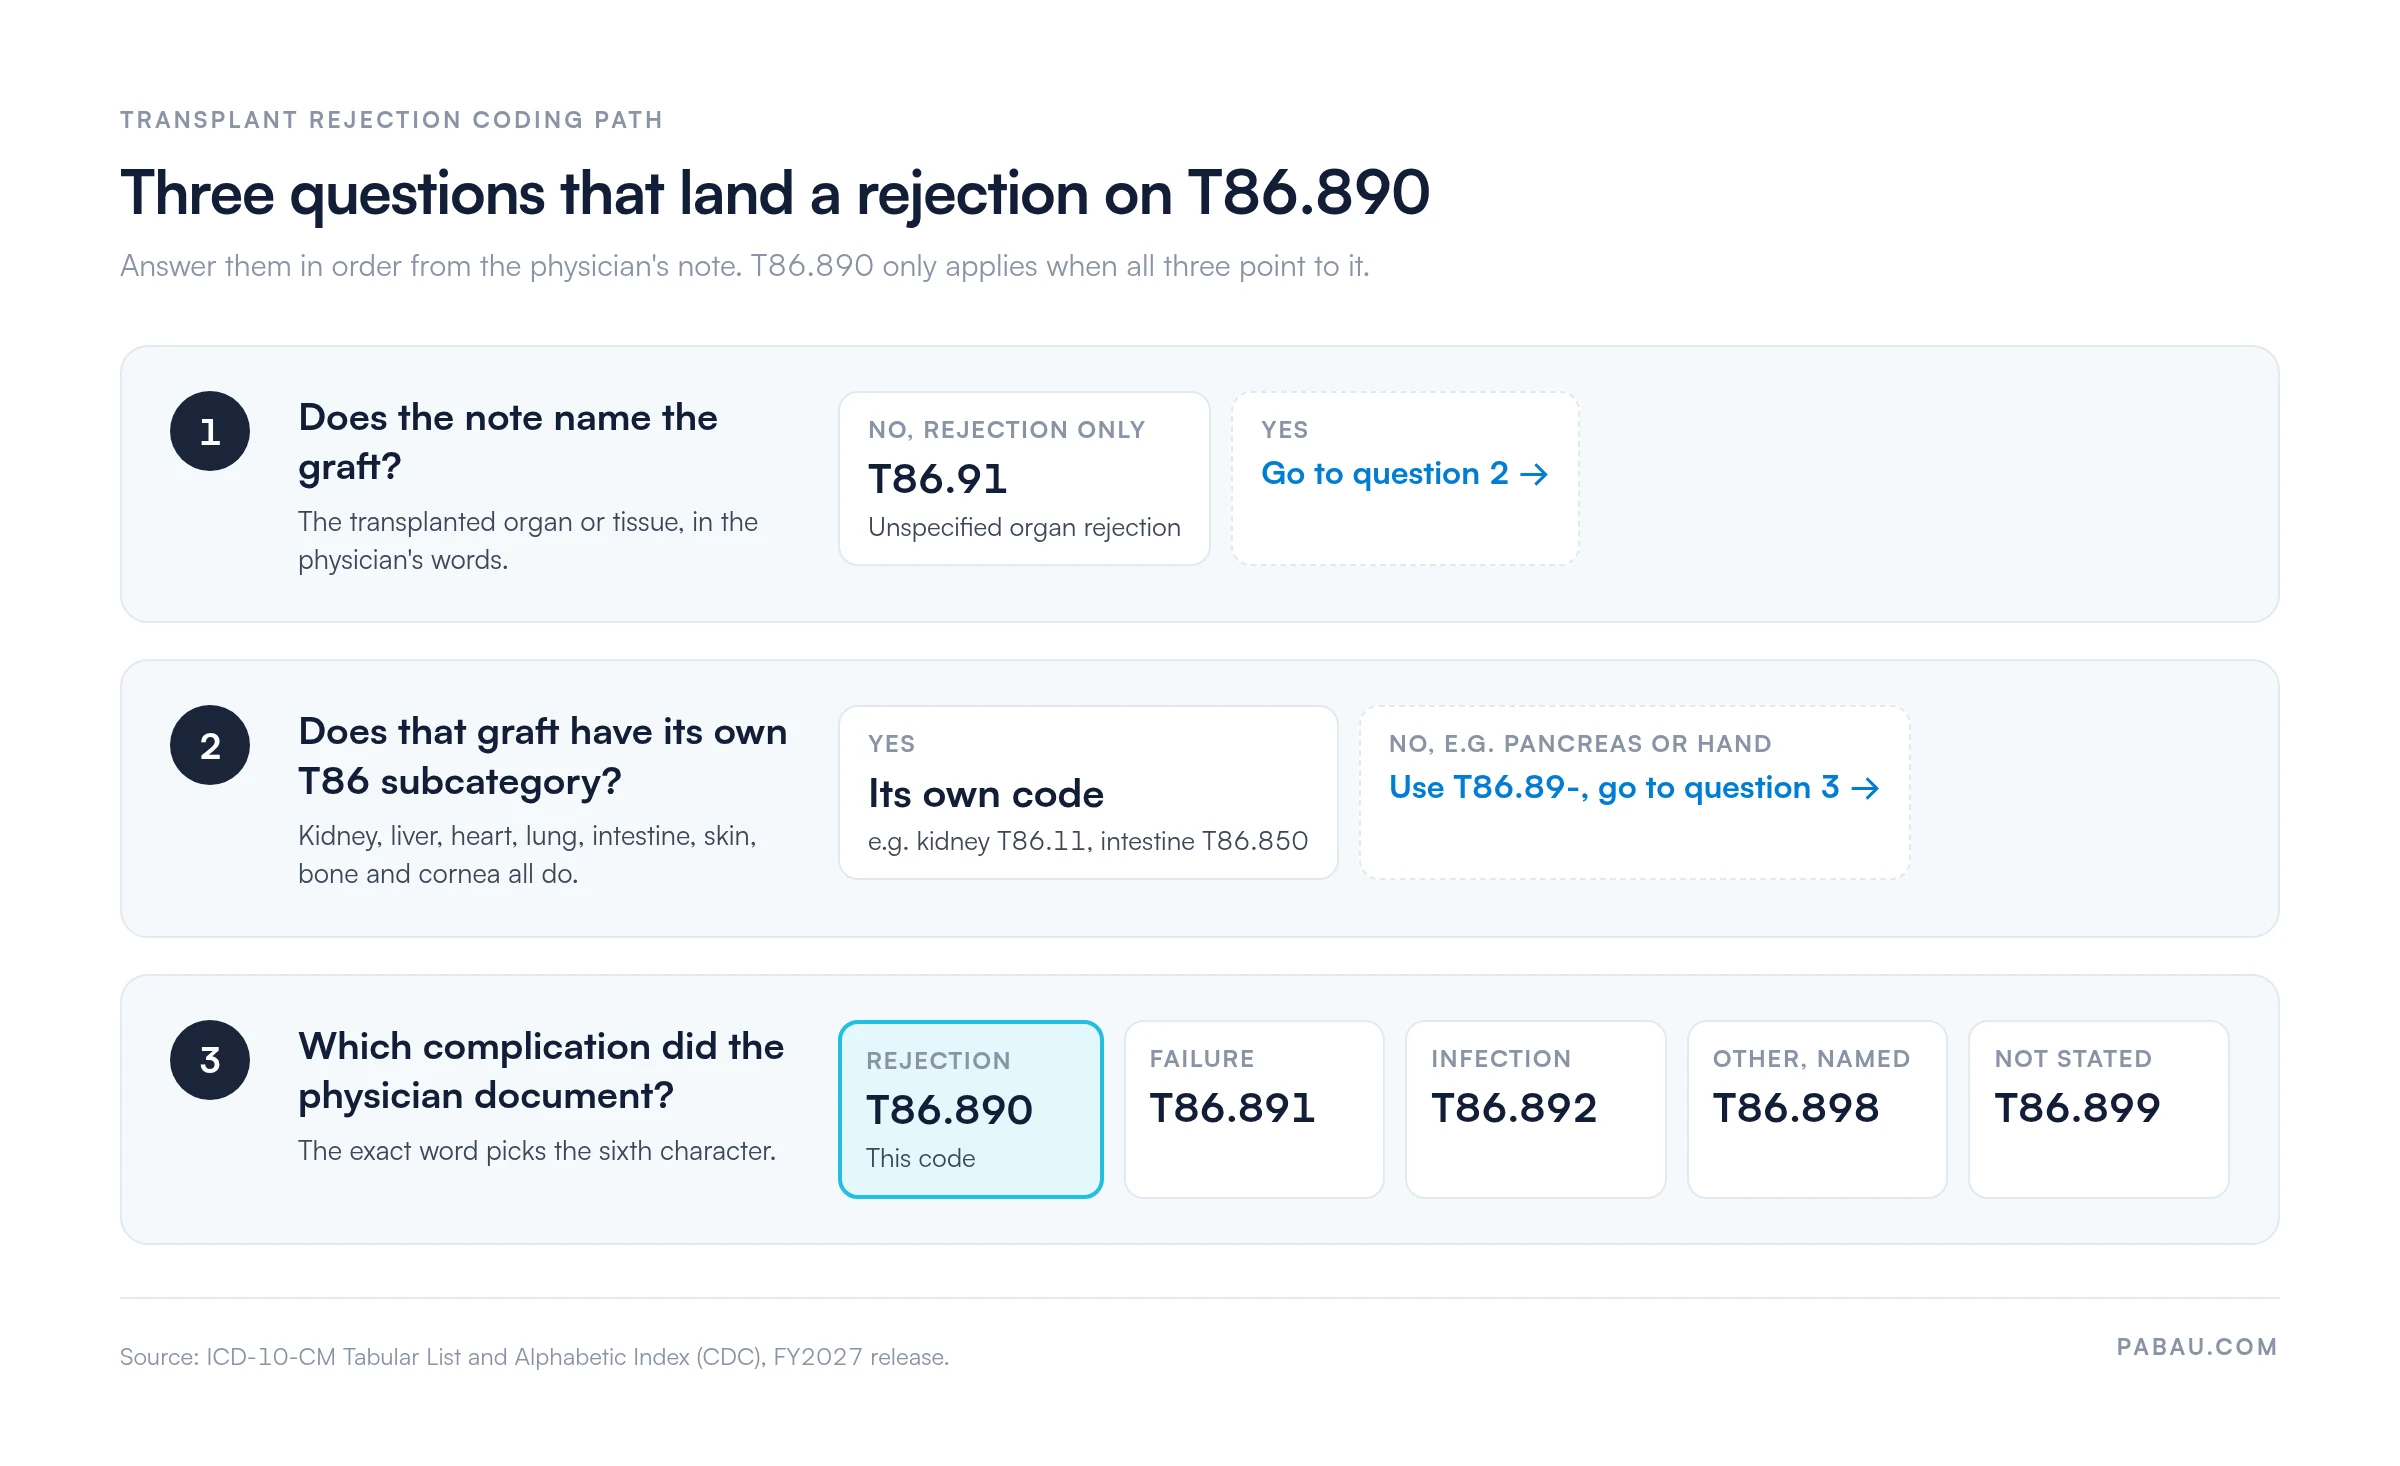
When a note says “transplant complication” and nothing more, send a short query before you code. Ask whether the graft was rejected, failed, became infected, or had another named problem. Each answer maps to a different T86.89 code, and the query doubles as your audit trail.
T86.89 and T86.890 carry no Excludes notes of their own. The instructions that bind T86.890 sit higher up, at the T86 category and the T80-T88 block, and on the codes that pair with it.
The Z94 note causes the most rework. T86.890 already tells the payer the patient has a transplant, so Z94.83, the pancreas transplant status code, stays off the claim.
Section I.C.19.g.3 of the ICD-10-CM Official Guidelines sets the rules for transplant complications. Download the current guidelines from the CMS ICD-10 codes page.
Under those rules, T86 codes cover both complications and rejection of transplanted organs. A T86 code applies only when the problem affects the function of the graft. Here is how that plays out for T86.890.
Check the organ ranges before you finalize the order. Kidney complications run through T86.1-, heart through T86.2- and liver through T86.4-, so none of those grafts belongs on T86.890.
Documentation decides whether T86.890 holds up at audit. Check the record for four elements, in line with medical billing compliance standards.
Abnormal labs alone do not support T86.890. If the note only says “rising lipase” or “transplant complication,” query the physician and get an addendum before the claim goes out.
Small changes in note wording change the code. These five charts show where the line falls. Search each code in the AAPC Codify lookup if your team wants the full Tabular notes beside it.
Take the first chart in detail. A patient had a simultaneous pancreas-kidney transplant in 2019. A biopsy now shows acute cellular rejection of the pancreas, while the kidney graft works normally.
Code T86.890 first, then any resulting condition as documented. Leave the T86.1- codes off, since the kidney graft has no complication. Z94.83 stays off the claim as well.
A T86.890 claim passes four stops on its way to payment. Each one stalls for a different reason.
Review clean claim requirements with your billing team before the first submission. Medicaid adds one more variable, since rules vary by state.
T86.890 denials tend to follow five patterns. Each has a fix you can make before you resubmit, and a steady denial management process stops them from repeating.
CARC 96 means the payer does not cover the charge at all, which a coding fix will not cure. CARC 4 points to a procedure code and modifier mismatch, not to the diagnosis.
Run this check against the note, not against memory. Each line maps to one of the denial patterns in the table above.
ICD-9-CM has no one-to-one match for T86.890. In the CMS General Equivalence Mappings, T86.890 maps to two legacy codes, and both matches are flagged as approximate.
Rejection had no code of its own in ICD-9-CM. The 996.8x codes covered rejection, failure and other complications together, so 996.86 also maps to T86.891 and T86.899. Use the crosswalk for audits of pre-October 2015 dates of service only.
A correct code is only half the job. The claim still has to reach the payer and come back paid. Many practices track that across a clearinghouse portal and a spreadsheet.
Pabau, the practice management platform we build, connects to Claim.MD for electronic claim submission in the US. With its claims tracking software, your team sends claims, checks eligibility and follows remittances in one place.
The coding decisions in this guide stay with your coders. Pabau handles the submission and follow-up, so your team can see which T86.890 claims are still open.


Pabau connects to Claim.MD, so your team can submit US claims electronically, check eligibility and track remittances without switching systems.

T86.890 is a narrow code, and that works in your favor. Once the graft has no named subcategory and the physician wrote “rejection,” the code choice is settled.
The risk sits in the codes around it. A stray Z94 code, a GVHD code sequenced first, or a note that never names the graft will sink a correct T86.890. Fix those before submission, and the claim has far fewer ways to fail.
For the wider picture, see how medical billing works from charge to payment. Then book a demo to see how Pabau submits and tracks those claims through Claim.MD.

Want to see how a clearinghouse checks your claims? Claim.MD clearinghouse overview explains how claims are screened and routed before they reach the payer.
Got a CARC on a T86.890 remittance? Denial codes in medical billing explains what the common denial codes mean and how to respond to each.
Sending transplant follow-up claims electronically? 837 file format guide covers the claim loops that carry your diagnosis codes and their order.
Physician documented graft failure instead? ICD-10 code T86.891 covers failure of other transplanted tissue and how it differs from rejection.
Note never says what went wrong with the graft? ICD-10 code T86.899 explains when an unspecified transplant complication code holds up.
T86.890 is the billable ICD-10-CM code for other transplanted tissue rejection. It reports rejection of a graft with no T86 subcategory of its own, most often a transplanted pancreas.
No. T86.890 is complete at six characters and billable as written. Unlike most chapter 19 injury codes, it takes no A, D or S encounter character.
T86.890 reports documented rejection of other transplanted tissue. T86.898 reports any other named complication of that tissue, such as graft thrombosis, that is not rejection, failure or infection.
Use T86.91, unspecified transplanted organ and tissue rejection. Query the physician first, since a named graft usually supports a more specific code such as T86.890 or T86.11.
ICD-9-CM has no exact match. The CMS mappings link T86.890 approximately to 996.86, complications of transplanted pancreas, and 996.89, complications of other specified transplanted organ.
Yes, on inpatient claims. T86.890 is not on the POA-exempt list, so it needs a Y, N, U or W indicator. Rejection present when the inpatient order was written takes Y.