

CPT code 63081: Vertebral corpectomy, cervical spine
CPT code 63081: official descriptor and procedure overview CPT code 63081 descri...

Last Updated: Oct 6, 2026
70547 is the CPT code for magnetic resonance angiography of the neck without contrast material. It covers a non-contrast MRA of the carotid and vertebral arteries, from their origins to the skull base.
It is the first of three neck MRA codes. 70548 is billed when contrast is given, and 70549 when the study is acquired both without and with contrast. Correct billing turns on the contrast protocol, the 26 or TC modifier, and a covered ICD-10 diagnosis.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CPT code 70547 covers MRA of the neck without contrast only, not a with-and-without sequence.
70547, 70548, and 70549 are mutually exclusive: Only one neck MRA code may be billed per session.
Modifier 26 is required when the radiologist bills the professional component separately from a facility.
In 2026, Medicare pays about $215 nationally for the global 70547 service, before locality adjustment.
Pabau’s claims management software runs validation checks before each claim is sent, so missing insurer details are caught before submission.
CPT code 70547 is the procedure code for Magnetic resonance angiography, neck; without contrast material(s), as defined by the American Medical Association’s CPT code set. The study images the neck’s extracranial vessels with time-of-flight (TOF) or phase-contrast (PC) MRA, without gadolinium or any other contrast agent. It captures the carotid arteries (common, internal, and external) and the vertebral arteries from their origin to the skull base.
This is the first study in the neck MRA family. It fits a clinical question such as carotid stenosis screening or pre-surgical mapping where contrast is best avoided. With no gadolinium, there is no contrast injection, no contrast timing sequence, and no post-contrast acquisition.
Billing 70547 for a study that included gadolinium is miscoding. Under Article A56775 (LCD L34424), which applies in some MAC regions, such a claim may be denied or audited.
“Neck” in CPT means the extracranial cervical vessels, not the intracranial circle of Willis. Intracranial MRA belongs to the head MRA family, where 70544 is the non-contrast equivalent. Mixing head and neck sites within one code is a common coder error, particularly when the requisition reads “MRA head and neck”.
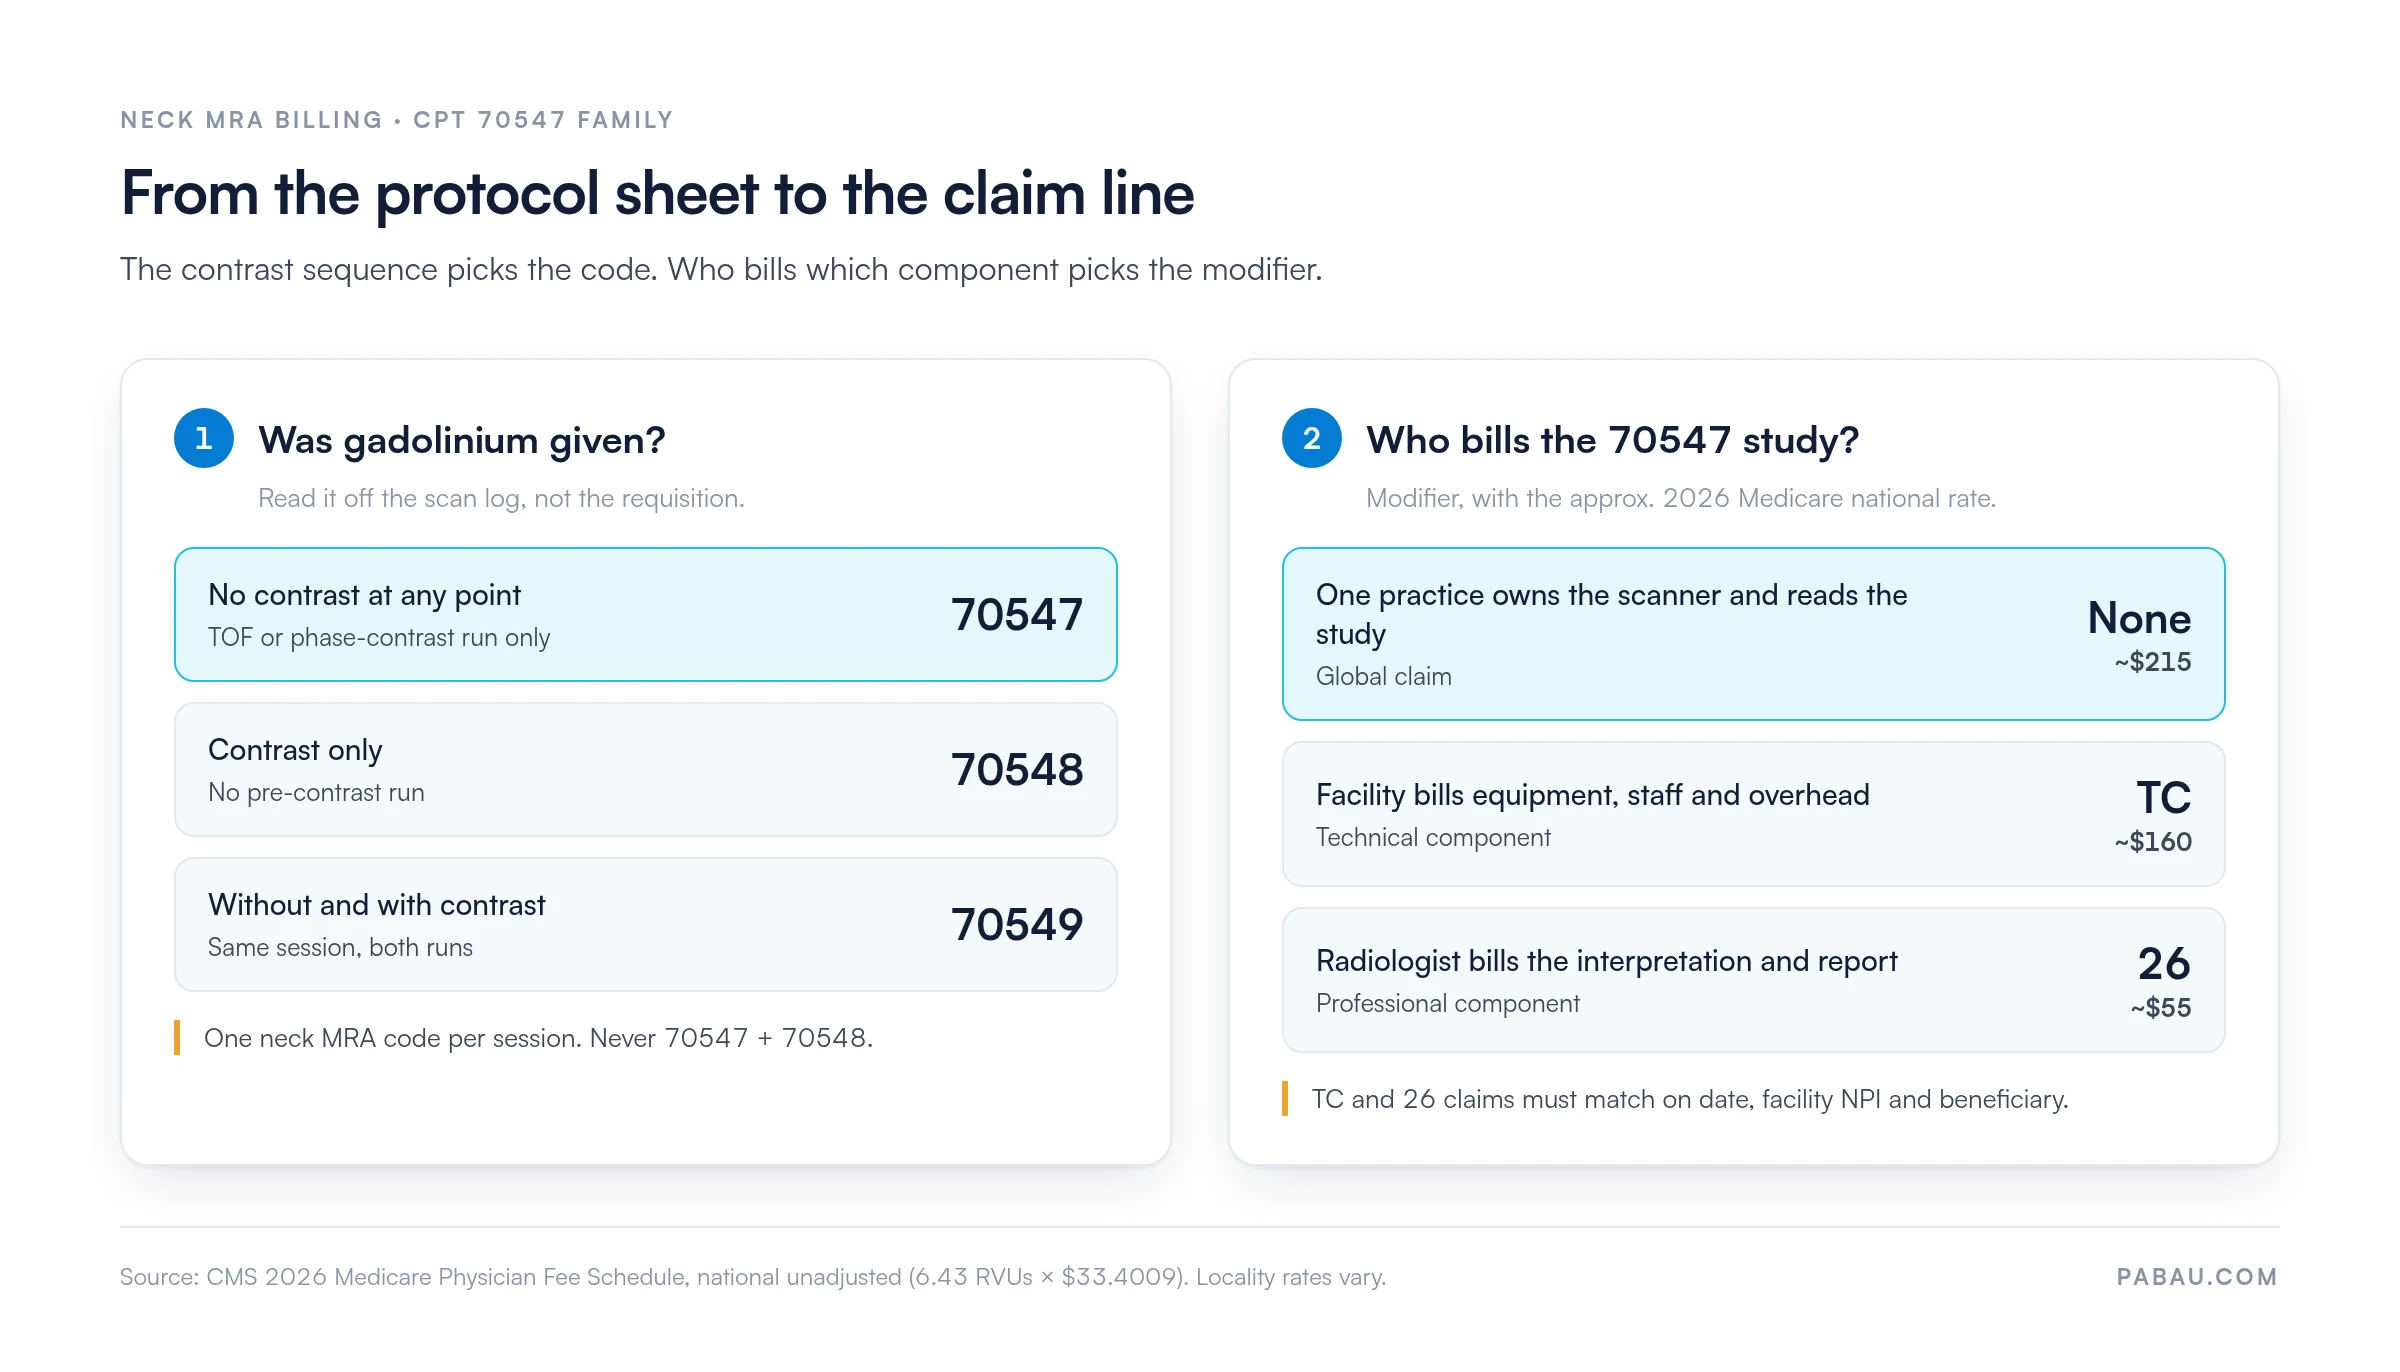
The three neck MRA codes share the same anatomy and technique and differ only by contrast sequence. All three image the same cervical vessels. The billing question is whether gadolinium was given, and if so, when.
A protocol that acquires a non-contrast TOF run and a gadolinium-enhanced sequence in the same session is billed as 70549, not as 70547 plus 70548. Billing both separately is an NCCI violation. The scan log or MRI protocol sheet must state which sequences were performed before the claim goes out.
The flow below takes a 70547 study from that protocol sheet to the claim line, with the modifier and its 2026 national rate.
A billable 70547 claim needs documentation at the ordering level and at the interpretation level. Missing either can trigger a CO-16 (missing information) or CO-50 denial.
Ordering documentation must include:
Radiology report must include:
Where Billing and Coding Article A56805 (LCD L34865) applies, covered 70547 claims typically carry one of these ICD-10 codes:
Pairing 70547 with a non-covered ICD-10 diagnosis is a frequent denial reason for this code.
Modifier selection for CPT code 70547 depends on where the service is performed and whether the radiologist bills globally or separately from the facility.
LT and RT modifiers (left and right) are not typically applied to MRA neck codes. The study evaluates both sides of the neck in one session. If a payer requests laterality, document that both sides were assessed and clarify it in an appeal.
Medicare payment rates for CPT code 70547 are published annually in the Medicare Physician Fee Schedule (MPFS) final rule. The CMS Physician Fee Schedule lookup tool gives the current year’s national unadjusted rates by modifier and place of service.
The global figure is 6.43 total RVUs multiplied by the 2026 conversion factor of $33.4009, which comes to $214.77. These are national amounts. Allowed amounts vary by Medicare Administrative Contractor (MAC) locality and the Geographic Practice Cost Index (GPCI) adjustment.
Use the FastRVU RVU lookup tool to find locality-adjusted rates for your practice’s ZIP code. Hospital outpatient departments billing under OPPS are paid under an APC grouping rather than the MPFS rates above.
Private payer contracted rates for 70547 depend on each payer contract and often differ from Medicare. To check payment accuracy, compare your electronic remittance advice against the allowed amount for the claim’s locality. A payment well below the expected MPFS rate often points to a modifier error or a payer-specific payment policy.
Medicare coverage for neck MRA is set by Local Coverage Determinations (LCDs), and the one that applies depends on your MAC region. In some regions, Billing and Coding Article A56805 (LCD L34865) governs covered indications. In others, Article A56775 (LCD L34424) applies.
Both are revised from time to time. Check the active version as part of your medical billing compliance routine before finalizing a denial appeal.
Covered indications under Article A56805 (representative, not exhaustive):
Non-covered uses include routine screening without documented symptoms or risk factors, and studies ordered without a supervising physician’s signature. Many commercial payers use Medicare LCD criteria as a baseline and add prior authorization on top. Confirm payer-specific coverage before you schedule the study.
Medicare fee-for-service does not require prior authorization for CPT code 70547. The CMS Appropriate Use Criteria program is currently paused. CMS rescinded its regulations in the CY2024 Physician Fee Schedule final rule, so it is not an active requirement.
The following payer classes typically require prior authorization for 70547:
Before submitting an auth request, confirm coverage with insurance eligibility verification for the specific date of service. An auth obtained for the wrong date or under the wrong NPI is treated as no auth at all at adjudication.
National Correct Coding Initiative (NCCI) edits for CPT code 70547 set which procedures cannot be billed together, and which pairs a modifier can separate. CMS updates the edit table quarterly. Confirm any bundling guidance here against the current quarter’s table, through the AAPC Codify platform or the CMS NCCI edit files.
Mutual exclusivity within the neck MRA family: 70547, 70548, and 70549 are mutually exclusive per session. Only one neck MRA code may appear on a claim for a given date of service. Billing 70547 and 70549 together is always an NCCI violation, and the second code is denied whichever modifier is appended.
Use CrossCoder’s procedure-to-diagnosis crosswalk tool to confirm active NCCI edits before billing 70547 alongside adjacent codes. Key bundling scenarios to verify:
Run NCCI edit checks against the current quarter’s table, not last year’s. CMS updates the CCI edit matrix four times per year. A bundle that required modifier 59 in Q1 may be a hard edit in Q3. Build a quarterly review of your top-10 billed code pairs into your revenue cycle calendar.
Most 70547 denials fall into six categories, and each is preventable with the right pre-submission workflow. The table pairs each one with its usual claim adjustment reason code (CARC), and our guide to medical billing denial codes explains the rest.
A pre-bill audit step built on clean claim submission principles catches most of these before the claim reaches the payer. A denial management workflow for radiology billing should include a weekly review of CO-50 and CO-167 denials. Both trace back to the diagnosis and documentation on the claim.
Without a check before submission, a 70547 error usually surfaces in the remittance, after the payer has denied the line. Fixing it then means a corrected claim, a resubmission, and another payment cycle.
Pabau, the practice management platform we build, includes claims software for practices that bill insurance. Pabau’s claims management software runs validation checks before each claim is sent, so missing insurer details are caught before submission. A missing membership number or authorization code gets fixed while the claim is still on your screen.

Claims then go out through Pabau’s Claim.MD clearinghouse integration, which reaches thousands of US payers. It supports real-time eligibility checks (270/271), CMS-1500 claim submission, and ERA matching, so payments post against the right claim line. Your billing team spends less time reworking neck MRA denials.

Pabau’s claims management software runs validation checks before each claim is sent, then submits clean claims to thousands of US payers through the Claim.MD integration. See how it works for your billing team.

CPT code 70547 is simple in clinical terms, yet each claim turns on three billing-layer decisions: Choosing the code, the modifier, and the diagnosis. Settle the protocol sheet, the 26/TC arrangement, and the ICD-10 pairing before submission, and the denials in the table above become avoidable. A few minutes of pre-bill review costs far less than weeks spent on an appeal.
Pabau’s claims management software runs validation checks before each claim is sent, so missing insurer details are caught before submission. Book a demo to see how that check fits your radiology billing workflow.

Need to understand how clearinghouse submissions work end to end? Medical claims clearinghouse guide explains how claims move from practice to payer and where edits are applied.
Dealing with 835 remittance files after payment? Claim.MD clearinghouse overview covers ERA parsing, CARC codes, and automated payment posting.
Want to understand the superbill behind the claim? Superbill billing guide walks through how the superbill feeds CPT and ICD-10 codes into the claim submission workflow.
Billing a brain MRI in the same session? CPT code 70553 covers MRI of the brain with and without contrast, which may be billed alongside 70547 when separately ordered.
Imaging the neck vessels with CT instead? CPT code 70498 explains how CT angiography of the neck is coded and billed.
CPT code 70547 covers magnetic resonance angiography of the neck without contrast, imaging the carotid and vertebral arteries with non-contrast TOF or PC MRA technique. It does not cover any study in which gadolinium or another contrast agent was administered. Those studies are reported with 70548 (with contrast) or 70549 (with and without contrast).
The difference is contrast sequence only. CPT 70547 is without contrast, 70548 is with contrast (gadolinium only), and 70549 is with and without contrast (a pre-contrast and a post-contrast acquisition). All three image the same cervical vessels. The code follows the protocol performed, not the ordering physician’s preference. The three codes are mutually exclusive: Only one may be billed per date of service.
Modifier 26 is appended when the radiologist bills only the professional component (interpretation and report) separately from a facility. Modifier TC is used by the facility billing equipment and staffing costs. No modifier (global billing) applies when a private practice owns the scanner and employs the technologist. Modifier 59 may be used when 70547 is billed alongside a cervical spine MRI on the same date. It requires a documented, distinct clinical indication and a current NCCI edit that permits it.
Under the 2026 national unadjusted MPFS rates, Medicare pays approximately $215 for the global service. The professional component (modifier 26) pays about $55, and the technical component (modifier TC) about $160. Payment varies by MAC locality and GPCI adjustment. Hospital outpatient departments are paid under OPPS APC rates, which differ from MPFS amounts. Use the CMS Physician Fee Schedule lookup tool or FastRVU for locality-specific figures.
Medicare fee-for-service does not require prior authorization for 70547. The CMS Appropriate Use Criteria program is paused, and CMS rescinded its regulations in the CY2024 Physician Fee Schedule final rule. Most Medicare Advantage and commercial plans do require prior authorization, and Medicaid managed care organizations frequently do. Requirements vary by plan, so verify with the specific payer before scheduling the study.
Yes, 70547 (MRA neck without contrast) and 70553 (MRI brain with and without contrast) may be billed together on the same date. Both must be separately ordered and documented with distinct clinical indications. They are different procedures imaging different anatomical regions. Confirm there is no active NCCI edit pairing them in the current quarter’s edit table before submitting both.
The six most common denial reasons are: Unsupported medical necessity (CO-50) and missing or expired prior authorization (CO-15, CO-197). The next is an incorrect modifier, such as billing global when a 26/TC split applies (CO-4). An NCCI bundling violation (CO-97) comes from billing 70547 with 70548 or 70549 on the same date. The last two are a non-covered ICD-10 pairing (CO-167, CO-11) and a place-of-service mismatch (CO-5).



