

HCPCS code P9058: Red blood cells, leukocytes reduced, CMV-negative, irradiated
HCPCS code P9058: Official descriptor and key attributes HCPCS code P9058 report...

Last Updated: Oct 26, 2026
62328 is the CPT code for spinal puncture, lumbar, diagnostic; with fluoroscopic or CT guidance. It covers a lumbar puncture done to collect cerebrospinal fluid for testing, with fluoroscopy or CT guiding the needle. The imaging guidance is included in the code.
A diagnostic lumbar puncture without that guidance is reported with 62270, and a guided therapeutic drainage is 62329. Ultrasound or MR guidance does not lead to 62328. Report 62270 with the matching guidance code instead.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CPT code 62328 reports a diagnostic lumbar puncture performed with fluoroscopic or CT guidance, and the imaging is included in the code.
Without fluoroscopy or CT, the same diagnostic puncture is 62270, while a therapeutic CSF drainage under that imaging is 62329.
Do not add 77003 or 77012 to 62328, and report an ultrasound- or MR-guided tap as 62270 plus 76942 or 77021.
In 2026, Medicare’s national rate for 62328 is $216.51 non-facility and $73.85 facility at the qualifying APM conversion factor.
Pabau’s practice software submits claims through Claim.MD and tracks eligibility and ERA remittance, so your team can follow each 62328 claim to payment.
CPT code 62328 describes a spinal puncture, lumbar, diagnostic; with fluoroscopic or CT guidance. The provider enters the subarachnoid space at a lumbar level and collects cerebrospinal fluid for laboratory testing. Fluoroscopy or CT guides the needle, and that guidance is part of the code.
The code arrived in CPT 2020, when 62270 and 62272 became parent codes for two image-guided child codes, 62328 and 62329. That is why the descriptor reads as the 62270 stem followed by “with fluoroscopic or CT guidance.”
62328 sits in the Surgery section of the CPT code set, under Nervous System. Within it, the code falls in the injection, drainage, or aspiration range for the spine and spinal cord (62263-62329). It has a 0-day global period. The American Medical Association’s CPT code set overview explains how the AMA maintains these descriptors.
Most diagnostic lumbar punctures are done at the bedside by landmark, and those are reported with 62270. Fluoroscopy or CT is usually requested when a landmark approach is likely to fail or already has. Common reasons include obesity, prior lumbar surgery or fusion, scoliosis and advanced degenerative change.
The patient typically lies prone on the fluoroscopy table or in the CT gantry. The provider localizes the interspace, advances the spinal needle under imaging and measures the opening pressure where ordered. CSF is then collected into numbered tubes for the requested tests.
Two questions pick the code: was the puncture diagnostic or therapeutic, and did fluoroscopy or CT guide it? 62328 is the diagnostic, image-guided answer. 62270 is the same diagnostic puncture without that guidance. 62329 is a guided therapeutic drainage, and 62272 is the unguided drainage.
Work RVUs come from the CMS 2026 PFS relative value file, October release.
Read the indication first and the imaging second. A guided tap to test CSF for suspected meningitis is 62328. A guided tap to lower pressure in idiopathic intracranial hypertension is 62329, even if some fluid goes to the lab. Without fluoroscopy or CT, the same two taps drop to 62270 and 62272. The map below lays out every route.
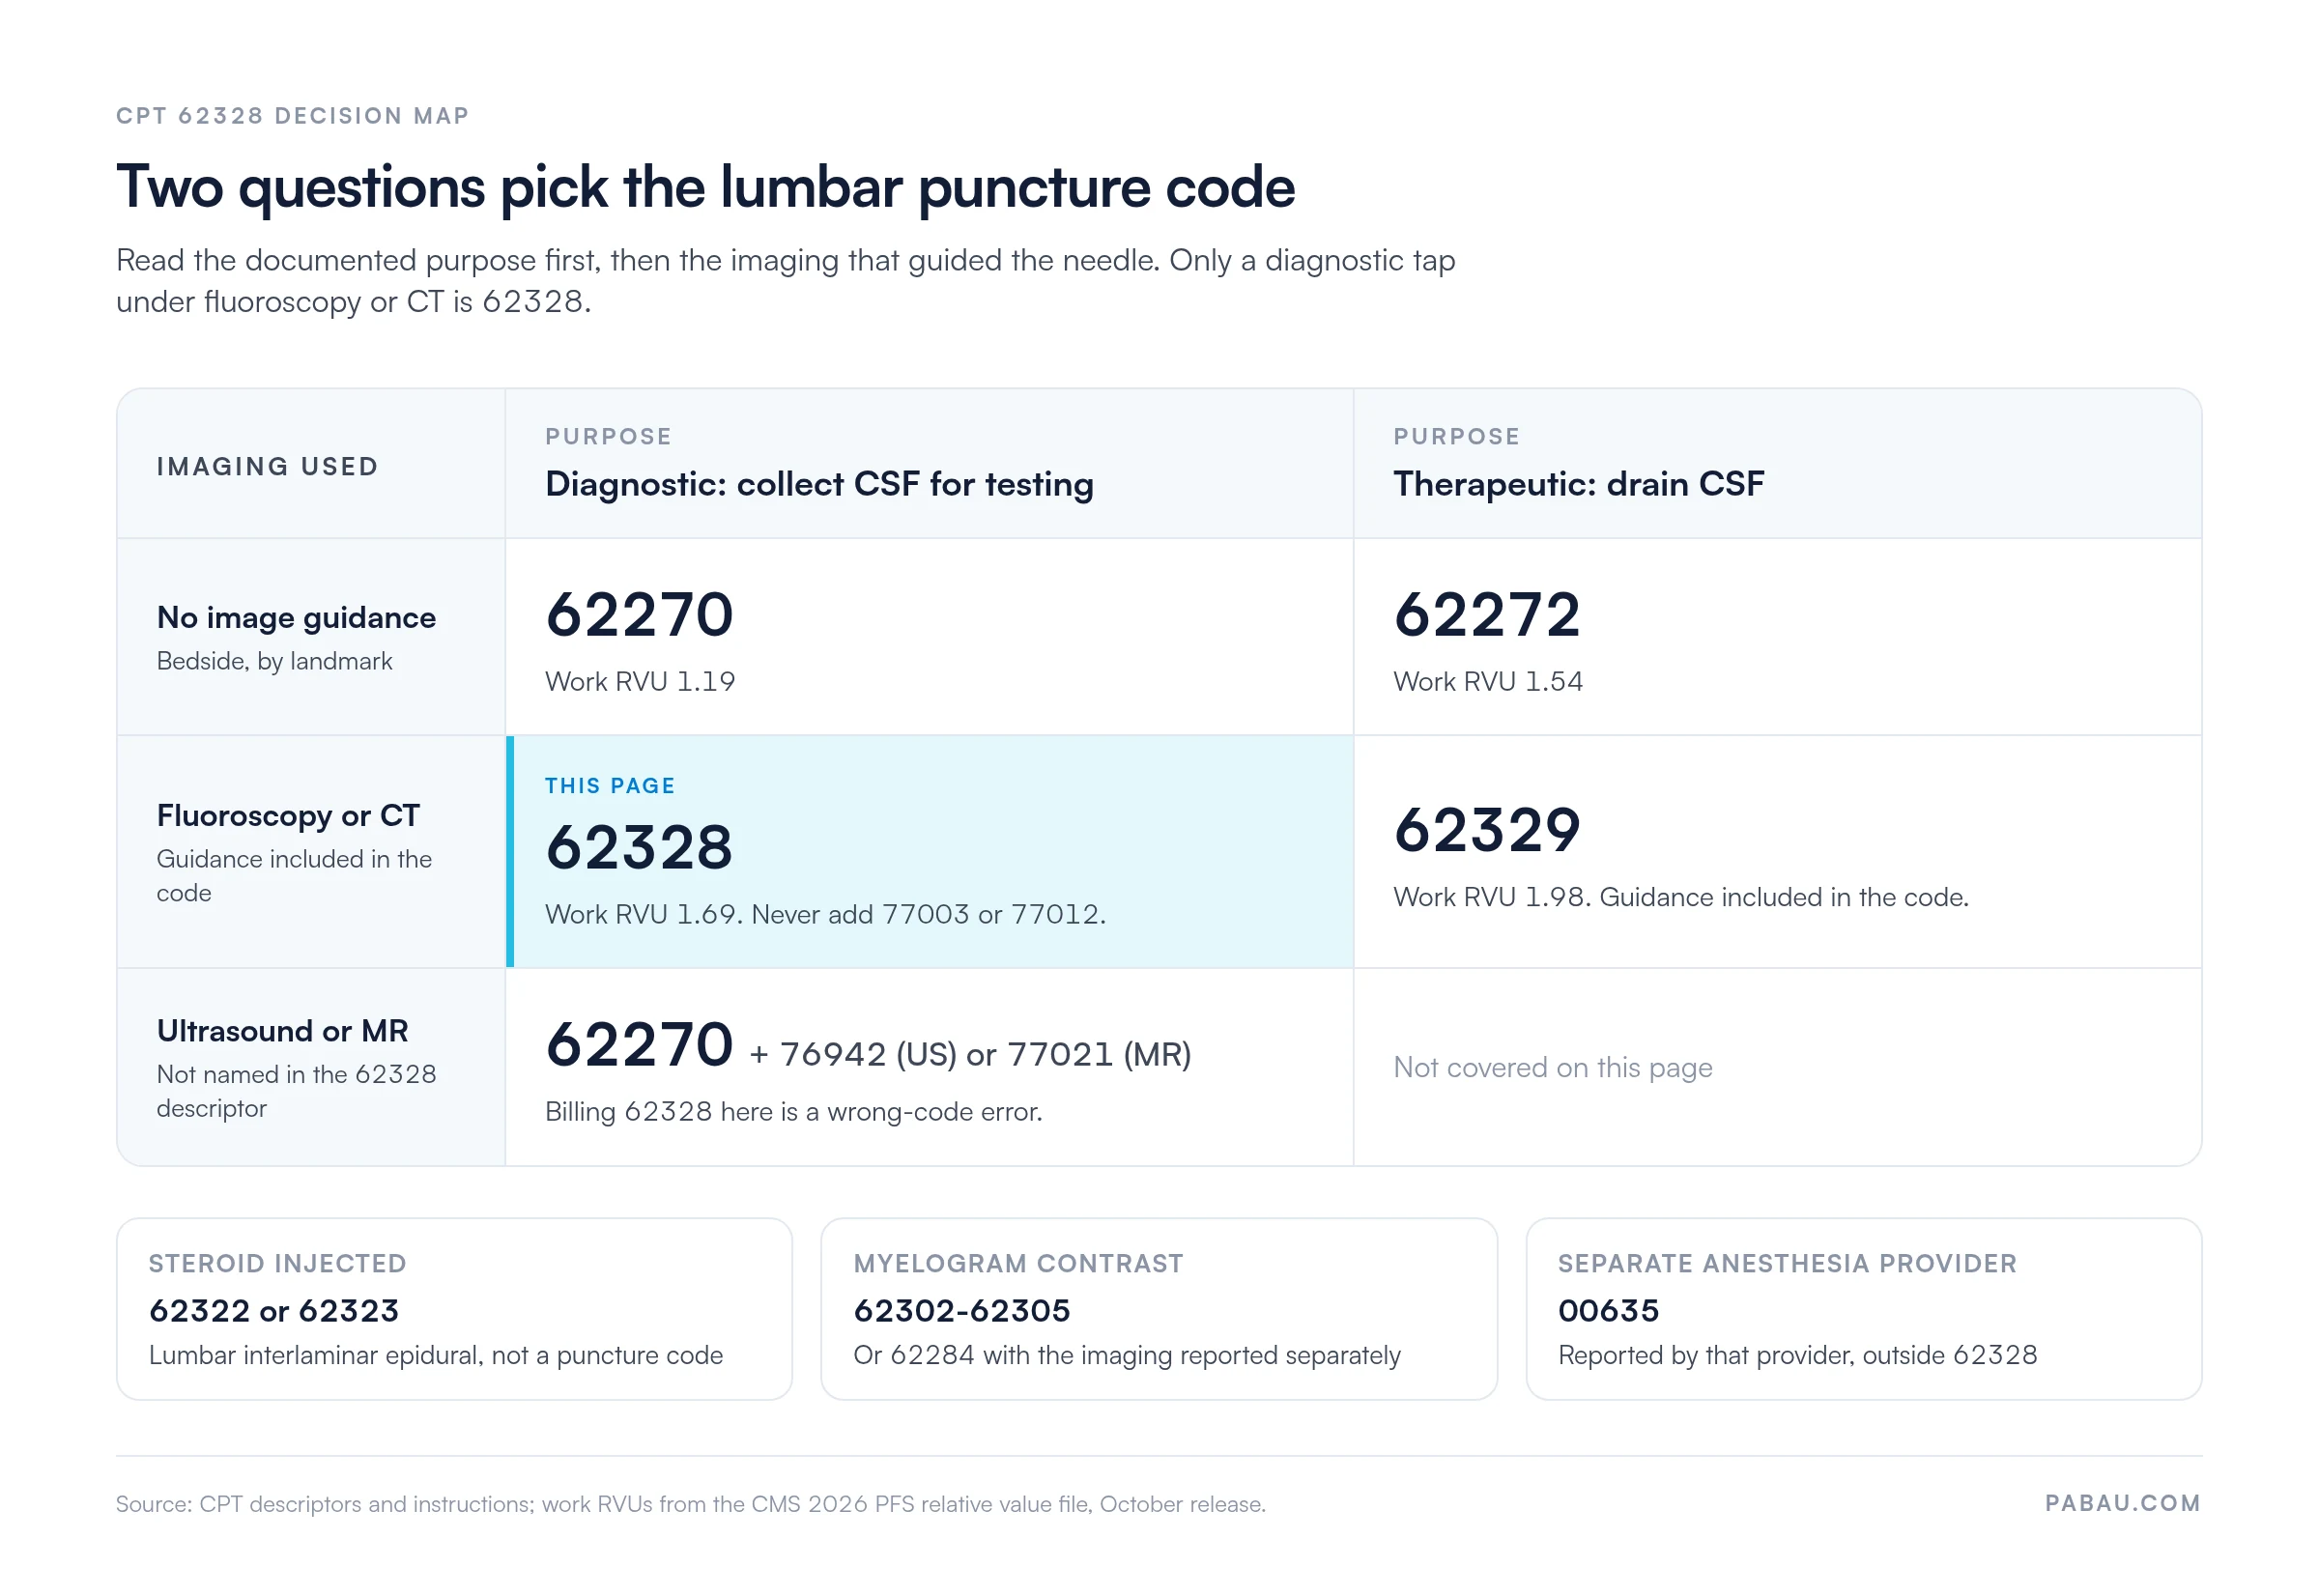
The 62328 descriptor names only fluoroscopy and CT. When ultrasound guides a diagnostic lumbar puncture, report 62270 with 76942. When MR guides it, report 62270 with 77021. Billing 62328 for an ultrasound-guided tap is a wrong-code error, and a payer that reviews the note can recode or deny it.
62328 is sometimes confused with the lumbar epidural codes, because both put a needle into the lumbar spine under fluoroscopy. An interlaminar epidural injection of steroid or anesthetic at a lumbar or sacral level is 62322 without imaging, or 62323 with it. Catheter-based epidural infusions at that level are 62326 and 62327.
62328 enters the subarachnoid space to collect CSF, and no therapeutic substance is delivered. If the note describes an injected steroid, the service does not belong on 62328.
62328 pays for the guided puncture as one service. Knowing what sits inside the code, and what moves to another code, prevents both unbundling and the wrong-code denials that follow.
Contrast injected for a myelogram moves the service out of 62328. Myelography via lumbar injection is reported with 62302-62305, or with the injection code 62284 when the injection and the imaging are reported separately.
Sedation or anesthesia from a separate anesthesia provider is not part of 62328 either. That provider reports the service with 00635.
No. CMS assigns 62328 a PC/TC indicator of 0, so modifiers 26 and TC do not apply. A radiologist used to billing 77003 with modifier 26 in the hospital reports 62328 without a modifier. Medicare pays the facility rate in that setting.
Medical necessity for 62328 rests on a diagnosis or set of signs that explains why CSF had to be tested. On outpatient claims, Section IV.H of the ICD-10-CM guidelines says not to code a diagnosis documented as suspected, probable or rule out. Code the presenting signs and symptoms instead, and the confirmed condition once results support it.
Codes and titles match the current ICD-10-CM code set from CMS. Since October 1, 2025, G35 has been a header code rather than a billable one. Report an MS subtype such as G35.A, or G35.D when the type is not documented.
When you code symptoms, code every documented sign that points to the concern behind the tap. Headache alone (R51.9) rarely explains why CSF was needed. Fever, neck stiffness and confusion together tell the payer why the puncture was done.
A large-volume tap to relieve normal pressure hydrocephalus is therapeutic drainage, so it belongs on 62329 when imaging guides it.
A clean 62328 claim starts with a procedure note that shows a diagnostic purpose and documents the imaging. If the note never mentions fluoroscopy or CT, a payer can recode the claim to 62270 or deny it.
The procedure note should record these elements:
Medicare pays 62328 at different rates in facility and non-facility settings, because the practice expense RVU changes with the setting. The figures below come from the CMS 2026 PFS relative value file, October release.
For 2026, CMS set two conversion factors: $33.5675 for qualifying APM participants and $33.4009 for everyone else.
Each payment is the total RVU multiplied by the conversion factor, before the locality adjustment. Confirm your local rate in the CMS Physician Fee Schedule Look-Up Tool. Commercial rates are negotiated separately.
The same file gives 62328 a multiple procedure indicator of 2. The standard reduction applies when it is billed with other procedures on the same day. Its bilateral indicator is 0, so the 150% bilateral adjustment does not apply.
Prior authorization rules for 62328 depend on the payer, so check the patient’s plan before an elective guided puncture. Build that check into scheduling so it runs for every elective case.
Urgent punctures, such as suspected meningitis or subarachnoid hemorrhage, usually go ahead before any authorization. Record the urgency in the note and follow the plan’s retro-authorization process.
Denials on 62328 follow a predictable set of patterns. Each one has a front-end fix, and good denial management workflows apply it before the claim goes out.
Before you submit a 62328 claim, check the note for three things. Look for a diagnostic purpose, fluoroscopic or CT guidance, and a diagnosis or set of signs that explains the tap. If ultrasound guided the needle, the claim belongs on 62270 with 76942.
Radiology and neurology practices billing 62328 often track eligibility, claim status and remittances across several payer portals. Pabau connects to Claim.MD, a US medical claims clearinghouse, to submit CMS-1500 and 837P claims.
Through that connection, your team can check a patient’s eligibility before the puncture is scheduled. After submission, Pabau tracks claim status and processes ERA (835) remittances, including the CARC reason codes on any denial. Your billers see why a 62328 claim came back without calling the payer.
Pabau’s medical claims management submits and tracks the claim data your team enters. Code selection and the procedure note stay with your providers and coders, so the documentation checks above still belong in your own pre-bill review.

Pabau submits CPT 62328 claims through Claim.MD, checks eligibility before the procedure, and tracks ERA remittance so your team can follow each claim to payment.

CPT code 62328 is the right code only when the note shows a diagnostic lumbar puncture guided by fluoroscopy or CT. Drop the imaging and the claim belongs on 62270. Change the purpose to drainage and it belongs on 62329.
Ultrasound and MR guidance sit outside 62328, so check the modality as well as the purpose before the claim goes out. Pair the puncture with the signs or diagnosis that justified the tap. Book a demo to see how Pabau submits and tracks your spinal procedure claims through Claim.MD.

Need to understand denial codes on returned claims? Denial codes in medical billing covers CARC and RARC code meanings and how to act on each.
Want to reduce your overall claim rejection rate? Medical claims clearinghouse guide explains how electronic clearinghouse submission reduces edit errors before claims reach payers.
Verifying patient coverage before scheduling? Insurance eligibility verification walks through real-time eligibility checks and what to confirm before a spinal procedure date.
CPT code 62328 covers a diagnostic lumbar puncture performed with fluoroscopic or CT guidance. The puncture collects CSF for testing, and the imaging guidance is included in the code.
Both codes report a diagnostic lumbar puncture. CPT 62270 applies when no fluoroscopy or CT guided the needle. CPT 62328 applies when fluoroscopy or CT did, and it includes that guidance.
CPT 62328 is a diagnostic puncture to collect CSF for testing. CPT 62329 is a therapeutic puncture to drain CSF. Both include fluoroscopic or CT guidance, so the documented purpose decides the code.
No. CPT instructs coders not to report 77003 or 77012 with 62328, because the fluoroscopic or CT guidance is already part of the code.
62328 covers only fluoroscopic or CT guidance. For a diagnostic tap under ultrasound, report 62270 with 76942. For MR guidance, report 62270 with 77021.
For 2026, 62328 carries 6.45 total RVUs in a non-facility setting and 2.20 in a facility setting. At the $33.5675 qualifying APM conversion factor, that is $216.51 and $73.85 nationally. At the $33.4009 non-qualifying factor, it is $215.44 and $73.48 before locality adjustment.
No. 62328 is a diagnostic lumbar puncture that collects CSF. A lumbar or sacral interlaminar epidural injection is reported with 62322 without imaging guidance, or 62323 with it.
Common pairings include G03.9 (meningitis, unspecified), I60.9 (nontraumatic subarachnoid hemorrhage, unspecified), G35.A (relapsing-remitting multiple sclerosis), G61.0 (Guillain-Barre syndrome) and G93.2 (benign intracranial hypertension). On an outpatient claim where the diagnosis is still suspected, code the presenting signs instead.




