

CPT code 14001: Adjacent tissue transfer on the trunk
CPT code 14001: Definition and official descriptor The American Medical Associat...

Last Updated: Nov 3, 2026
M2510 is the CCSD code for excision of a ureterocele on one side, with or without ureteric reimplantation. It covers open or laparoscopic removal of the ureterocele from the bladder wall. Any reimplantation done at the same sitting is bundled into the same code.
Endoscopic incision or puncture of a ureterocele is coded M3202, and excision on both sides is coded M2511. M2510 sits in Chapter 12 of the CCSD schedule, Urinary system and male reproductive organs. Most UK private insurers require pre-authorisation before the operation.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD Code M2510 covers excision of a ureterocele on one side, with or without ureteric reimplantation.
Endoscopic incision or puncture of a ureterocele is coded M3202, so billing M2510 for an endoscopic approach is up-coding.
Most UK private insurers require pre-authorisation for M2510 before surgery, and a claim without the reference is a primary denial cause.
Pair M2510 with ICD-10 code Q62.3, which includes congenital ureterocele, and add associated diagnoses such as vesicoureteral-reflux-associated uropathy (N13.7).
Pabau, the practice management software we build, tracks pre-authorisation status and flags incomplete claims before they reach the insurer.
CCSD Code M2510 is the Clinical Coding and Schedule Development (CCSD) procedure code for excision of ureterocele (with or without ureteric reimplantation), unilateral.
The official descriptor is published in the CCSD schedule. It applies only to open or laparoscopic surgical excision of the ureterocele, not to endoscopic treatment of the same lesion. You can compare it with the other Chapter 12 urology procedures in our CCSD code library.
The “+/- ureteric reimplantation” in the descriptor makes M2510 a bundled code. Whether or not the surgeon adds ureteric reimplantation (ureteroneocystostomy), the claim carries the single code M2510. Laterality is fixed, though. M2510 is unilateral only, so a procedure on both sides at the same sitting falls outside its scope.
A ureterocele is a cystic dilatation of the distal ureter at the point where it enters the bladder. The condition is predominantly paediatric and most often occurs with a duplex (duplicated) collecting system. There, two ureters drain into the bladder, and the upper-pole ureter inserts ectopically and forms the ureterocele.
Excision is indicated when the ureterocele causes ureteric obstruction, recurrent urinary tract infections, or vesicoureteric reflux (VUR) that has not responded to conservative management.
The operation removes the ureterocele from the bladder wall. Reflux into either ureter, or an inadequate ureteric orifice after excision, calls for concurrent ureteric reimplantation. That restores a competent ureterovesical junction.
Both variants fall within the M2510 descriptor. The surgical approach (open or laparoscopic) does not affect code selection either, because M2510 applies to both.
Knowing the code boundaries prevents both up-coding and under-coding errors. The table below maps the clinical scenarios that fall inside and outside M2510.
Several CCSD codes sit near M2510 in the urological chapter and are commonly confused with it. A wrong code usually comes from misreading the surgical approach (endoscopic or open excision) or the scope (unilateral or bilateral, with or without nephrectomy). The Bupa CCSD code schedule provides the insurer-specific fee against each code for comparison.
Key distinction: M3202 (endoscopic treatment of the ureteric orifice) and M2510 (surgical excision) are the most commonly confused pair. The operative report must state which approach was used. Coders must not default to M2510 when only a cystoscopic puncture or incision was performed.
Where reimplantation is the whole operation and no ureterocele is excised, the replantation codes apply instead: M2080 for one ureter and M2030 for both. The chart below maps each operative finding to the code it supports.
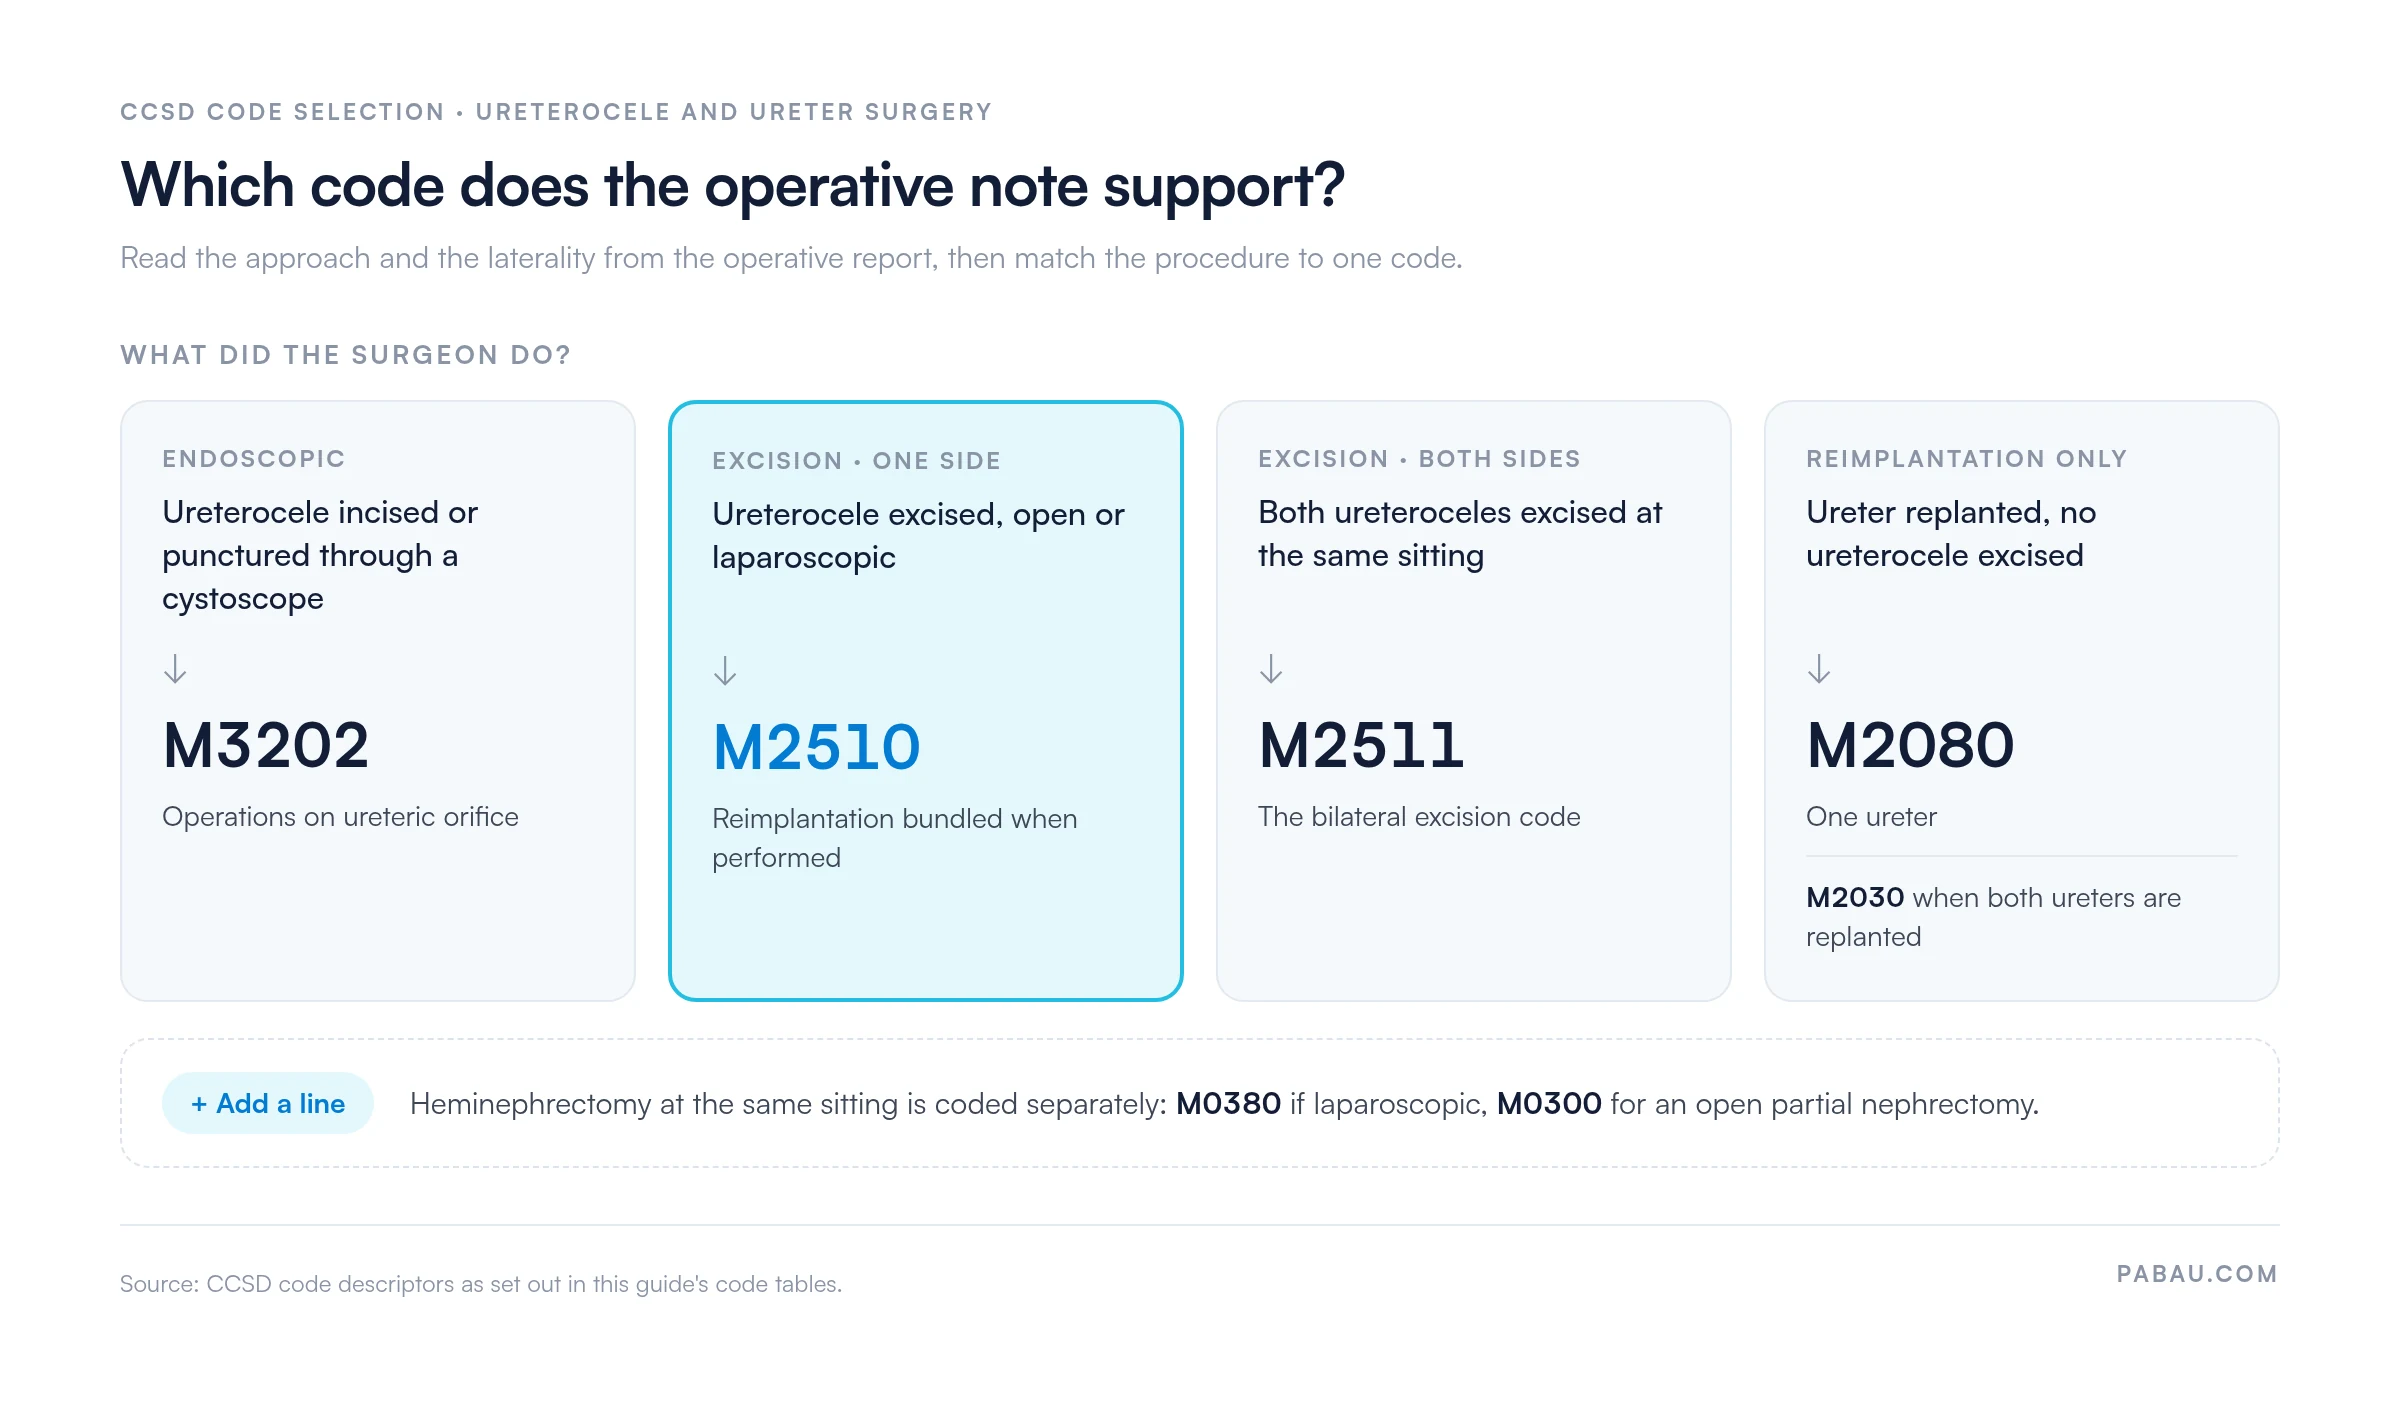
When a duplex system needs heminephrectomy and ureterocele excision at the same sitting, code the heminephrectomy and M2510 separately. Use M0380 for a laparoscopic heminephrectomy or M0300 for an open partial nephrectomy. Bundling both procedures into M2510 alone undercodes the claim and leaves legitimate surgical complexity unreimbursed. Document each procedure distinctly in the operative report and confirm the insurer’s unbundling rules before submission.
Every M2510 claim requires at least one ICD-10 diagnosis code identifying the pathology being treated. The NHS Classifications Browser carries the current UK ICD-10 5th Edition codes. Verify exact codes against the edition in use on the date of the procedure.
Q62.3 should appear as the principal diagnosis. UK ICD-10 stops at four characters, so the five-character ureterocele codes used in the US (ICD-10-CM) are not valid on a UK claim.
Supplementary codes for duplex anatomy (Q62.5), ectopic ureter (Q62.6) and VUR (N13.7) are not required on every claim. They strengthen the clinical case during pre-authorisation, and when VUR shaped the operative decision. Verify exact codes against the current NHS ICD-10 edition before submission.
An M2510 claim without adequate operative documentation is the most reliably preventable denial. The operative report must support every element of the code descriptor. Treat documentation capture as a step in the surgical workflow, completed before the patient is discharged.
The operative note must explicitly confirm the following:
Pre-operative imaging (ultrasound, MAG3 renogram, MCUG) is not submitted with the claim but should be retained in the patient record. Insurers may request these during post-payment audit or when authorisation is contested. A standard operative note template, used by the whole surgical team, keeps each note in line with insurer requirements.
CCSD Code M2510 is a major elective urological procedure. UK private insurers, including Bupa, AXA Health, Aviva and Vitality Health, typically require pre-authorisation before any elective surgery, and M2510 is no exception. A claim without an authorisation reference number is the most common reason M2510 claims are denied outright.
Pre-authorisation requests are submitted before the procedure date. The process typically follows these steps:
Refusals most often follow a referral that never makes the clinical case for excision over endoscopic incision. A letter documenting failed endoscopic treatment, or the anatomical reasons it is unsuitable, substantially reduces refusal rates.
If authorisation is refused and the clinician believes surgery is indicated, use the insurer’s formal appeals process. That beats operating without authorisation and absorbing the cost.
Insurer pre-authorisation policies change. Verify current requirements with each insurer rather than relying on past processes. The Bupa code search, Aviva fee schedule, and Vitality fee finder each carry current procedural guidance for their networks. Consultants new to private practice should secure insurer recognition and learn each pre-auth workflow early. That avoids cash-flow delays on the first surgical invoices.
M2510 claims are denied for a predictable set of reasons. Each one maps to a corrective action you can build into the billing workflow before submission.
A structured billing workflow reduces claim errors and pre-empts the denial categories above. The steps below apply to most UK private insurer submissions for M2510.
M2510 is performed under general anaesthesia, usually in children. In CCSD-based billing, the anaesthetist codes the anaesthesia separately with the relevant CCSD anaesthesia codes and bills it on their own invoice. The operating surgeon’s M2510 claim carries no anaesthesia element or code.
When concurrent procedures are performed at the same sitting, the general CCSD rule is to list and code each one separately. The key scenarios are treated as follows.
Confirm the insurer’s specific unbundling rules for CCSD surgical codes before any multi-procedure submission. Healix and Cigna, for example, publish their own unbundling guidelines within their fee schedules that go beyond the base CCSD rules. A claim that is correctly coded under CCSD may still be partially denied if it conflicts with an insurer-specific bundling policy.
An M2510 claim draws on three records: the insurer’s authorisation reference, the signed operative note, and the invoice. When those sit in an insurer portal, a shared drive and a spreadsheet, a missing field only shows up when the remittance comes back short.
In Pabau, all three sit on the patient record. Its claims management software tracks pre-authorisation status, flags missing fields before submission and monitors claim cycle times across insurers. Your team checks one screen instead of reviewing every claim by hand.
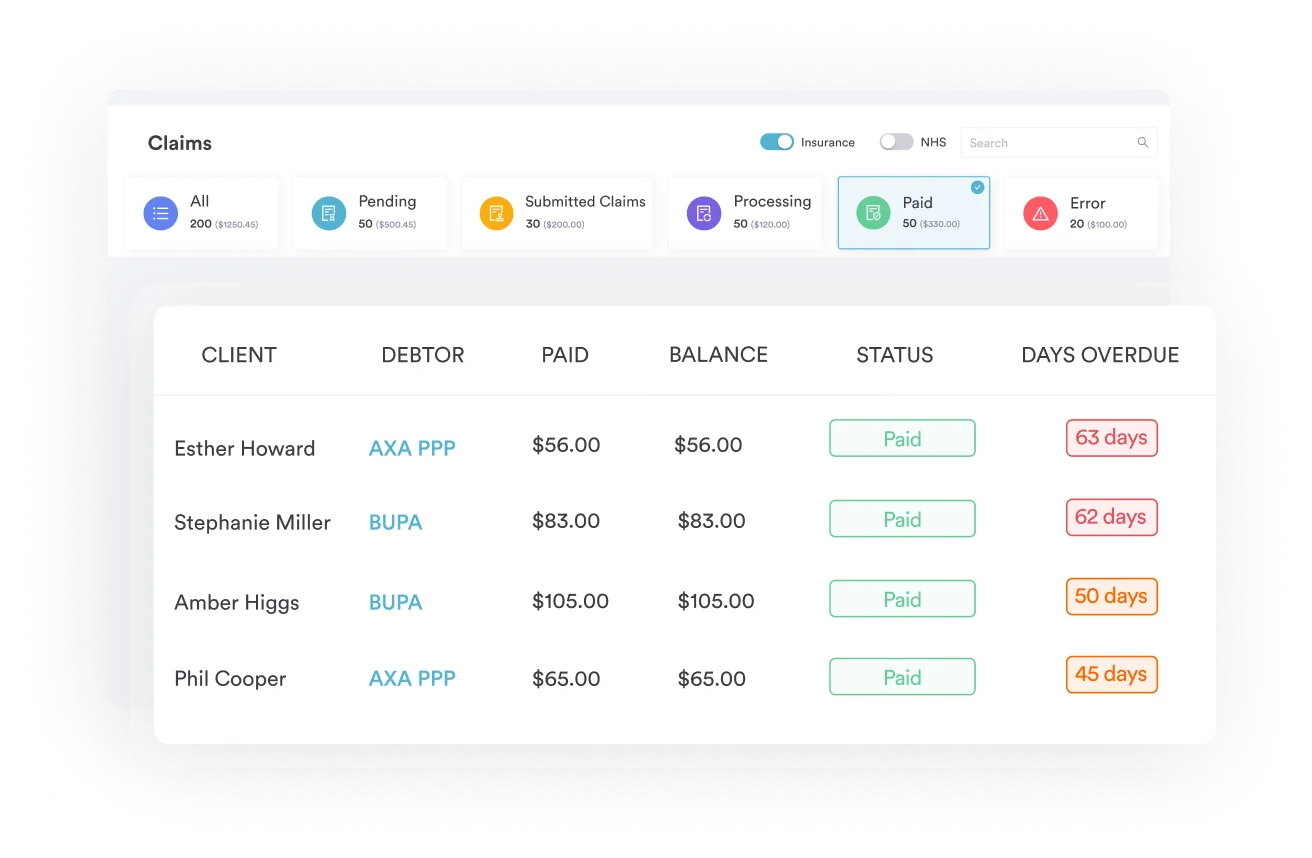

Pabau helps private surgical practices track pre-authorisation, capture operative documentation and submit CCSD-coded claims accurately. Your team spends less time chasing denials and more time on patient care.

Once the operative note confirms excision and names the side, M2510 is a straightforward code to assign. Claims fail on the paperwork around it: a missing authorisation reference, an unsigned note, or a heminephrectomy nobody pre-authorised.
So make pre-authorisation a condition of confirming the theatre date, and give surgeons a note template that asks for side, approach and reimplantation status. That adds a few minutes of admin before surgery. In return, far fewer M2510 claims come back for correction.
Book a demo to see how Pabau keeps authorisations and operative notes attached to every CCSD claim your practice submits.

Correcting reflux without a ureterocele? CCSD code M2210 covers open correction of vesico-ureteric reflux on one side, whichever open reimplantation technique the surgeon uses.
Operating on a transplant ureter? CCSD code M2160 covers reconstruction of the ureter that drains a transplanted kidney.
CCSD Code M2510 covers surgical excision of a ureterocele on one side only, with or without concurrent ureteric reimplantation. It applies to both open and laparoscopic excision approaches and bundles reimplantation into the same code when performed at the same sitting.
Endoscopic incision (cystoscopic puncture or incision of the ureterocele) is coded separately under M3202, not as M2510. M2510 applies only when the ureterocele is surgically excised via an open or laparoscopic approach. Using M2510 for an endoscopic procedure is up-coding, and the claim is typically denied once the insurer reviews the operative report.
The primary ICD-10 diagnosis code should be Q62.3, whose inclusion term is congenital ureterocele. Add Q62.5 (duplication of ureter) for a duplex system, Q62.6 for an ectopic ureter, and N13.7 when reflux influenced the operative decision. Verify exact code numbers against the current NHS ICD-10 edition before submission.
M2510 is unilateral only, as the descriptor states. When both ureteroceles are excised at the same operative sitting, the bilateral procedure code (M2511) applies instead. Submitting M2510 for a documented bilateral procedure will be identified as a scope mismatch during insurer review.
Most UK private insurers require the consultant’s outpatient letter, relevant imaging reports (ultrasound, MCUG), the proposed CCSD code and the ICD-10 diagnosis code. Clinical justification for surgical excision over endoscopic management strengthens the authorisation case and reduces the risk of refusal.
No. In CCSD-based UK private practice billing, the anaesthetist submits their own separate invoice using CCSD anaesthesia codes. The surgeon’s M2510 claim covers the surgical procedure only and should not contain an anaesthesia code.




