


Operative note: Required elements, templates and CMS rules
An operative note is the surgeon’s signed record of an operation, covering...

Last Updated: Nov 12, 2026
The Gaenslen test, also called Gaenslen’s test or Gaenslen’s maneuver, is a pain provocation test for the sacroiliac (SI) joint. One hip is flexed to the chest while the other hangs off the table into hyperextension, which twists the pelvis.
A positive result reproduces the patient’s familiar SI joint pain. On its own, the test catches only about half of SI joint cases, so it counts as one vote in a cluster of tests.
The sacroiliac joint accounts for an estimated 15 to 30% of low back pain cases. It is also one of the least examined structures in a routine assessment. A routine screen usually covers the lumbar spine and hip first, so the joint gets skipped.
This guide covers the technique, how to read a positive or negative result, and what the accuracy data supports. It also covers what goes into the note afterwards, with a worked example of a documented battery.
A test result only earns its keep once it is written down in a form another clinician can act on. Physical therapy, chiropractic, and sports medicine teams all need the same discipline here. Good physical therapy practice management software builds special tests straight into the note template.

The Gaenslen test is a sacroiliac joint provocation test that applies torsional stress across the SI joint. A positive result means the patient’s familiar pain is reproduced in the SI joint region.
No single SI joint test is diagnostic, so look for two positives among Laslett’s four tests, or three among five or six.
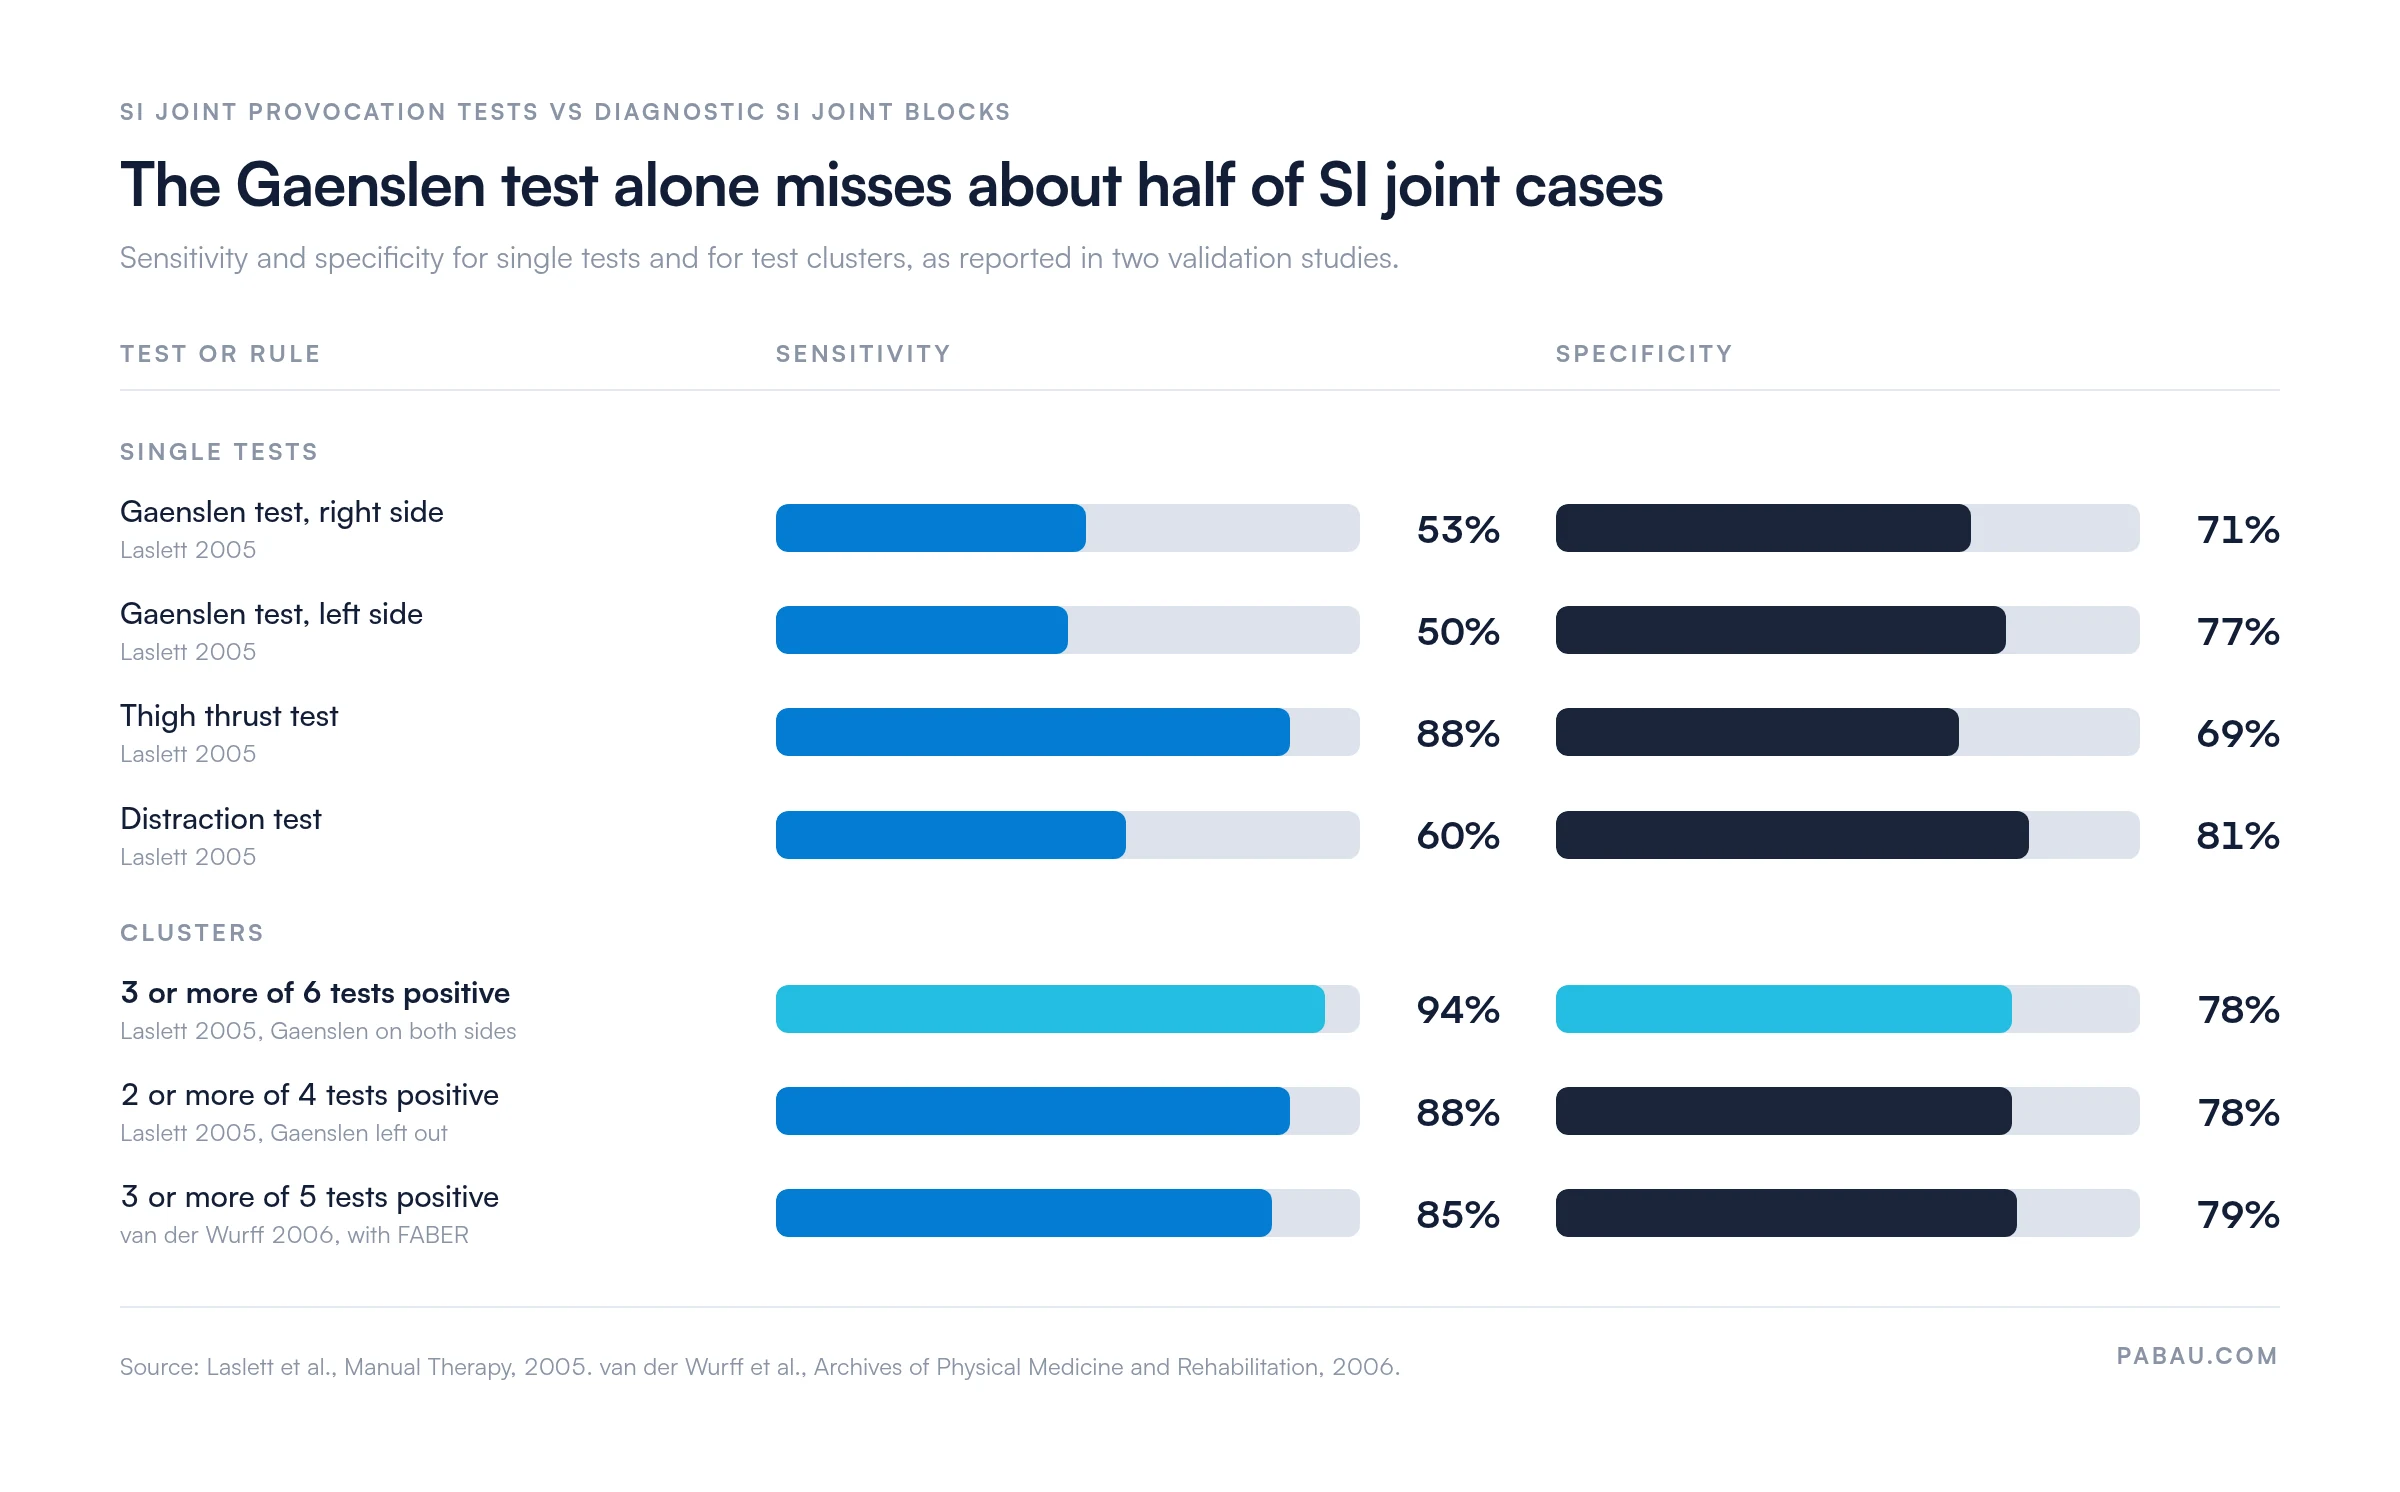
On its own, Gaenslen’s test misses about half of SI joint cases, while a full test cluster picks up 85 to 94% of them.
Your note has to record each test result, the composite score, and your clinical impression.
Pabau, the physical therapy EMR we build, keeps those findings and every reassessment in one patient record.
The Gaenslen test is a pain provocation test used to assess the sacroiliac joint. It works by putting that joint under torsional stress. Hip hyperextension on one side and hip flexion on the other create a force differential across the pelvis.
That differential shears the sacroiliac joint, so the maneuver reproduces the patient’s pain when that joint is the source. Frederick Julius Gaenslen described the test in 1927. It is the only test in the common SI joint clusters that loads the joint through torsion. Even so, Laslett’s best four-test rule leaves it out.
You will also see it written as Gaenslen’s test, Gaenslen’s maneuver, or Gaenslen’s sign. All four names describe the same maneuver.
The sacroiliac joint sits between the ilium and the sacrum. It is synovial at the front and fibrous at the back, which makes it partly mobile but heavily stabilized. Some of the thickest ligaments in the body hold it together.
Normal motion is minimal. Expect roughly 2 to 4 degrees of rotation and 1 to 2 mm of translation under load.
Pain from SI joint dysfunction usually refers to the posterior iliac region, the buttock, and the posterior thigh. It can spread below the knee, though. In one series of 50 injection-confirmed patients, 28% described leg pain past the knee, so distal pain does not rule the joint out.
The joint takes nerve supply from the ventral and dorsal rami of L4 to S3. That dual supply explains why referred pain can mimic lumbar disc pathology, and why imaging alone is unreliable.
Test the sacroiliac joint when SI joint pathology sits in the differential for low back, buttock, or posterior hip pain. These presentations should prompt it:
Chiropractors, physical therapists, and sports medicine clinicians all use the test routinely. Pregnancy-related pelvic girdle pain is a common referral route, so pelvic health practices see it more than most. A written rule for when SI joint testing starts cuts variation between clinicians and keeps notes comparable.
The test is less useful when active hip disease, such as hip osteoarthritis or a labral tear, is already suspected. Hip extension loads the hip joint as well, so a positive result is hard to trust.
Where the history points to an inflammatory cause, the sacroiliitis code you document is M46.1. Getting that on the record early matters, because it changes both the referral route and the imaging you request.
Technique is the biggest single variable in Gaenslen test reliability. Inconsistent patient positioning and inadequate overpressure are the two usual reasons a test comes back equivocal.
The bilateral variant is also common. Reposition the patient after testing one side, then repeat with the other leg hanging off the table. Comparing both sides adds clinical value and helps rule out hip joint pathology as a confounder.
The modified Gaenslen test uses a side-lying position instead of supine. The patient lies on the unaffected side, with the bottom hip and knee flexed to about 90 degrees for stability. The examiner then extends the top hip into hyperextension while stabilizing the pelvis.
This side-lying version is often called the Lewin-Gaenslen test. Use the supine version where you can, because its positioning is easier to repeat between sessions and clinicians.
Choose the side-lying position when a patient cannot tolerate lying supine, whether from lumbar pain, obesity, or late pregnancy. The mechanism and the positive criterion are identical to the supine version.
A positive Gaenslen test reproduces the patient’s concordant pain in the sacroiliac region. The pain has to feel the same as the presenting complaint. Discomfort from the stretch position on its own does not count.
Location matters. Pain that is clearly posterior and lateral to the posterior superior iliac spine, or PSIS, supports SI joint involvement. Pain that centralizes to the lumbar spine, or radiates down the anterior thigh, points elsewhere. Document the location, the quality, and whether the patient confirmed it as their familiar pain.
A positive result, especially inside a positive cluster, raises suspicion of several conditions. It confirms none of them, but it shapes the next step, from imaging to referral.
The Gaenslen test has moderate accuracy on its own. The figures below come from Laslett and colleagues’ 2005 validation study, which compared each test against a diagnostic SI joint injection:
Sensitivity of 50 to 53% means the test misses about half of SI joint cases when used alone. A negative result cannot rule the joint out. Specificity of 71 to 77% means a positive result alone cannot rule it in either.
That pattern holds across the board, because every SI joint provocation test performs poorly in isolation. The clinical power comes from combining them.
Results vary between studies. In an earlier study, Dreyfuss and colleagues checked 12 SI joint tests against joint injections. None of them, alone or combined, showed worthwhile diagnostic value. Later studies, including Laslett’s, moved to test clusters with a familiar-pain criterion.
Current evidence recommends a cluster of tests for SI joint diagnosis, and two clusters are widely cited. In the Laslett validity study, three or more positives out of six tests gave 94% sensitivity and 78% specificity. The six were distraction, thigh thrust, compression, sacral thrust, and the Gaenslen test on each side.
Laslett also found that the Gaenslen test added little to that cluster. Two or more positives among the other four tests gave 88% sensitivity and 78% specificity. The authors concluded the Gaenslen test can be left out without losing diagnostic confidence.
The same study found that when all six tests were negative, the SI joint could be ruled out as the pain source.
The van der Wurff regimen keeps the Gaenslen test and uses FABER in place of sacral thrust. Three or more positives out of five gave 85% sensitivity and 79% specificity against double SI joint blocks. In practice, that makes the Gaenslen test more useful as a tiebreaker than as a first test.
The chart below sets the single tests against the clusters.
Recording composite battery results as a structured field, rather than free text, lets you audit diagnostic patterns later. The five tests in the van der Wurff cluster, plus Laslett’s sacral thrust, are:
At three of five positives, van der Wurff reported a positive likelihood ratio of 4.02 for SI joint involvement. That makes a diagnostic injection or targeted treatment far easier to defend. No single test, the Gaenslen test included, confirms or rules out SI joint dysfunction on its own.
Both tests appear in the same battery, which raises a fair question about overlap. The answer is mechanism. They stress the joint in different ways, so a joint that is positive on one may be negative on the other.
Because FABER also screens the hip, it gives you differential information the Gaenslen test cannot. When both are positive in the posterior SI region, confidence in SI joint involvement climbs. When FABER is positive in the groin and Gaenslen is negative, look at the hip joint first.
The Gaenslen test carries a few clinical pitfalls. Knowing them prevents misdiagnosis and guides referral. The usual confounders are:
Adjacent tests help narrow the picture. Ober’s test separates lateral hip and iliotibial band tightness from posterior pelvic pain. Getting the SI joint call right also protects the loading plan that later rehab phases depend on.
When the picture is still unclear after the full battery, refer for a diagnostic SI joint injection under fluoroscopic guidance. That procedure is billed as 27096 and remains the gold standard for confirmation.
Run the full five-test SI joint battery in a fixed order every session, starting with distraction and finishing with Gaenslen. A fixed sequence reduces the chance of skipping a test under time pressure. It also makes your composite score directly comparable across reassessments.
Documentation of the Gaenslen test and the composite battery is a clinical and medicolegal requirement. Clinicians working in a physical therapy EMR should capture five things for every test session.
Here is what that looks like in the objective section of a note for a right-sided positive:
That level of detail takes about 30 extra seconds and settles two questions later. A reviewer can see why you treated the SI joint. Your next reassessment also has a number to compare against. The same documentation habit transfers to upper-limb work like the lift-off test, where positioning details decide interpretation.
A structured template is what makes this repeatable, and safer clinical notes start there. If your team prefers a narrative format, a DAP note template still leaves room for the composite score and the impression.
Track reassessment with a validated measure rather than a free-text impression. The global rating of change scale gives you a comparable score at every follow-up. Teams opening a new physical therapy practice should build both habits in from week one.
A battery like this often ends up in free text, or split across two systems. The composite score lives in a paragraph, and the intake answers sit in a paper form. The reassessment then ends up in a separate spreadsheet.
That setup makes a simple question hard. Nobody can say whether a patient scored three of five in March without reading the whole file.
Pabau’s physical therapy EMR brings those pieces into one place. Its Client records let musculoskeletal (MSK) clinicians log every provocation test inside a single SOAP note. You can then link the findings to a treatment plan and track each reassessment against them.
Digital intake forms handle the screening side. Add red flag questions on recent pregnancy, inflammatory conditions, and trauma history, so the test gets ordered when it is warranted. A standardized chiropractic intake form does the same job at the triage stage.

Pabau gives physical therapists and MSK clinicians structured SOAP note templates, digital intake forms, and treatment records built for musculoskeletal assessment. See how it fits your practice.

Used on its own, the Gaenslen test will miss about half the SI joint dysfunction in front of you. Run it inside the five-test battery, hold the three-of-five threshold, and it becomes part of one of the more reliable protocols in musculoskeletal examination.
The judgment worth carrying away is that the note decides what the examination is worth. A positive test that never reaches the record cannot justify a treatment plan or survive a review.
Fix the documentation habit first, because the battery is only as good as what you write down. Book a demo to see how Pabau standardizes special test documentation for physical therapy and chiropractic teams.

Need another special test for the same patient? Ober’s test covers iliotibial band and tensor fasciae latae tightness, a common lateral hip confounder.
Want the most sensitive SI joint test? Thigh thrust test covers the technique and why it leads the cluster.
Need to rule out the hip first? Hip quadrant test (scour test) covers the technique and what an intra-articular hip finding looks like.
Completing Laslett’s four-test rule? Sacral thrust test explains the prone technique and how to read it.
Buttock pain with leg symptoms? Crossed straight leg raise test explains how to screen for lumbar nerve root involvement.
The Gaenslen test is a sacroiliac joint provocation test used to detect SI joint dysfunction. It applies torsional shear force through hip hyperextension on one side and hip flexion on the other. It is part of the standard five-test SI joint battery used in physical therapy, chiropractic, and sports medicine.
Yes. Gaenslen’s test, the Gaenslen test, Gaenslen’s maneuver, and Gaenslen’s sign all name the same SI joint provocation test. It is named after Frederick Julius Gaenslen, who described it in 1927.
A positive Gaenslen test means the patient’s familiar pain was reproduced in the sacroiliac region. It suggests possible SI joint involvement, but one positive test is not diagnostic. A validated test cluster decides whether the finding points to SI joint dysfunction. Common causes include SI joint dysfunction, sacroiliitis, and pelvic girdle pain.
Laslett and colleagues reported sensitivity of 50 to 53% and specificity of 71 to 77% for the Gaenslen test alone. Those values are moderate, which is why the test is best used inside a composite battery. The thigh thrust test has higher sensitivity at about 88%, and is generally the most useful single test.
Yes. Hip joint problems, hip flexor tightness, lumbar facet irritation, piriformis syndrome, and lumbar radiculopathy can all cause pain during the maneuver. Note exactly where the pain sits, and run hip and lumbar screens alongside the SI joint cluster.
Three or more positive tests from a validated cluster point to SI joint involvement. The van der Wurff cluster uses five tests: Gaenslen, thigh thrust, FABER, distraction, and compression. Laslett’s six-test cluster swaps FABER for sacral thrust. His shorter rule needs two positives among distraction, thigh thrust, compression, and sacral thrust.
The Gaenslen test applies torsional shear through hip hyperextension and contralateral flexion, targeting the posterior sacroiliac ligaments. The FABER test stresses both the anterior SI joint and the hip joint itself. That makes FABER useful for separating SI pathology from hip pathology. A positive FABER with groin pain suggests the hip, while posterior SI pain points to the sacroiliac joint.
The modified Gaenslen test is a side-lying variant used when a patient cannot tolerate lying supine. The patient lies on the unaffected side with the bottom hip and knee flexed. The examiner then extends the top hip into hyperextension. This side-lying version is often called the Lewin-Gaenslen test. The positive criterion and interpretation are identical to the supine technique.





