

HCPCS Code L0472: Hyperextension TLSO billing guide
HCPCS code L0472: Official descriptor and device definition HCPCS code L0472 des...

Last Updated: Nov 5, 2026
J0641 is the HCPCS Level II code for injection, levoleucovorin, not otherwise specified, 0.5 mg. It covers Fusilev and generic levoleucovorin, while Khapzory bills under its own code, J0642.
Each unit is 0.5 mg, so a 200 mg dose bills as 400 units. J0641 is separate from J0640, which covers racemic leucovorin calcium at 50 mg per unit. NDC reporting is required by Medicaid and many commercial payers.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

HCPCS code J0641 covers injection, levoleucovorin, not otherwise specified, at 0.5 mg per unit, for Fusilev and generic levoleucovorin.
Khapzory bills under its own code, J0642, and racemic leucovorin calcium bills under J0640.
Unit calculation is a frequent error source, because a 200 mg dose equals 400 units of J0641.
NDC reporting is required by Medicaid and many commercial payers, so check each payer before you submit.
Pabau, the practice software we build, scrubs drug claims for missing or invalid details and carries prior authorization codes through to the claim.
HCPCS code J0641 is the code for injection, levoleucovorin, not otherwise specified, 0.5 mg. Each billable unit equals 0.5 mg of levoleucovorin given by injection. The code covers Fusilev and generic levoleucovorin products. Khapzory has its own code, J0642, so it never bills under J0641.
J0641 covers injectable levoleucovorin in two clinical roles. The first is rescue after high-dose methotrexate, including treatment of methotrexate toxicity. The second is combination therapy with fluorouracil in metastatic colorectal cancer, such as the FOLFOX and FOLFIRI regimens. These are the FDA-approved indications for Fusilev and its generic equivalents.
The following are excluded from J0641:
Levoleucovorin bills under J0641 and racemic leucovorin under J0640, and the two codes are not interchangeable. Levoleucovorin is the pharmacologically active L-isomer. Leucovorin is the racemic mixture of the L and D isomers. They are distinct drugs with different dosing conventions, different ASP-based payment rates, and different payer coverage policies.
The unit difference is the most common billing error. J0640 bills at 50 mg per unit, while J0641 bills at 0.5 mg per unit.
Swap the code on a 100-unit J0640 claim without recalculating, and the quantity is wrong by a factor of 100. Payers catch this with a claim edit and deny the whole line. Here is the same 200 mg dose under each code:
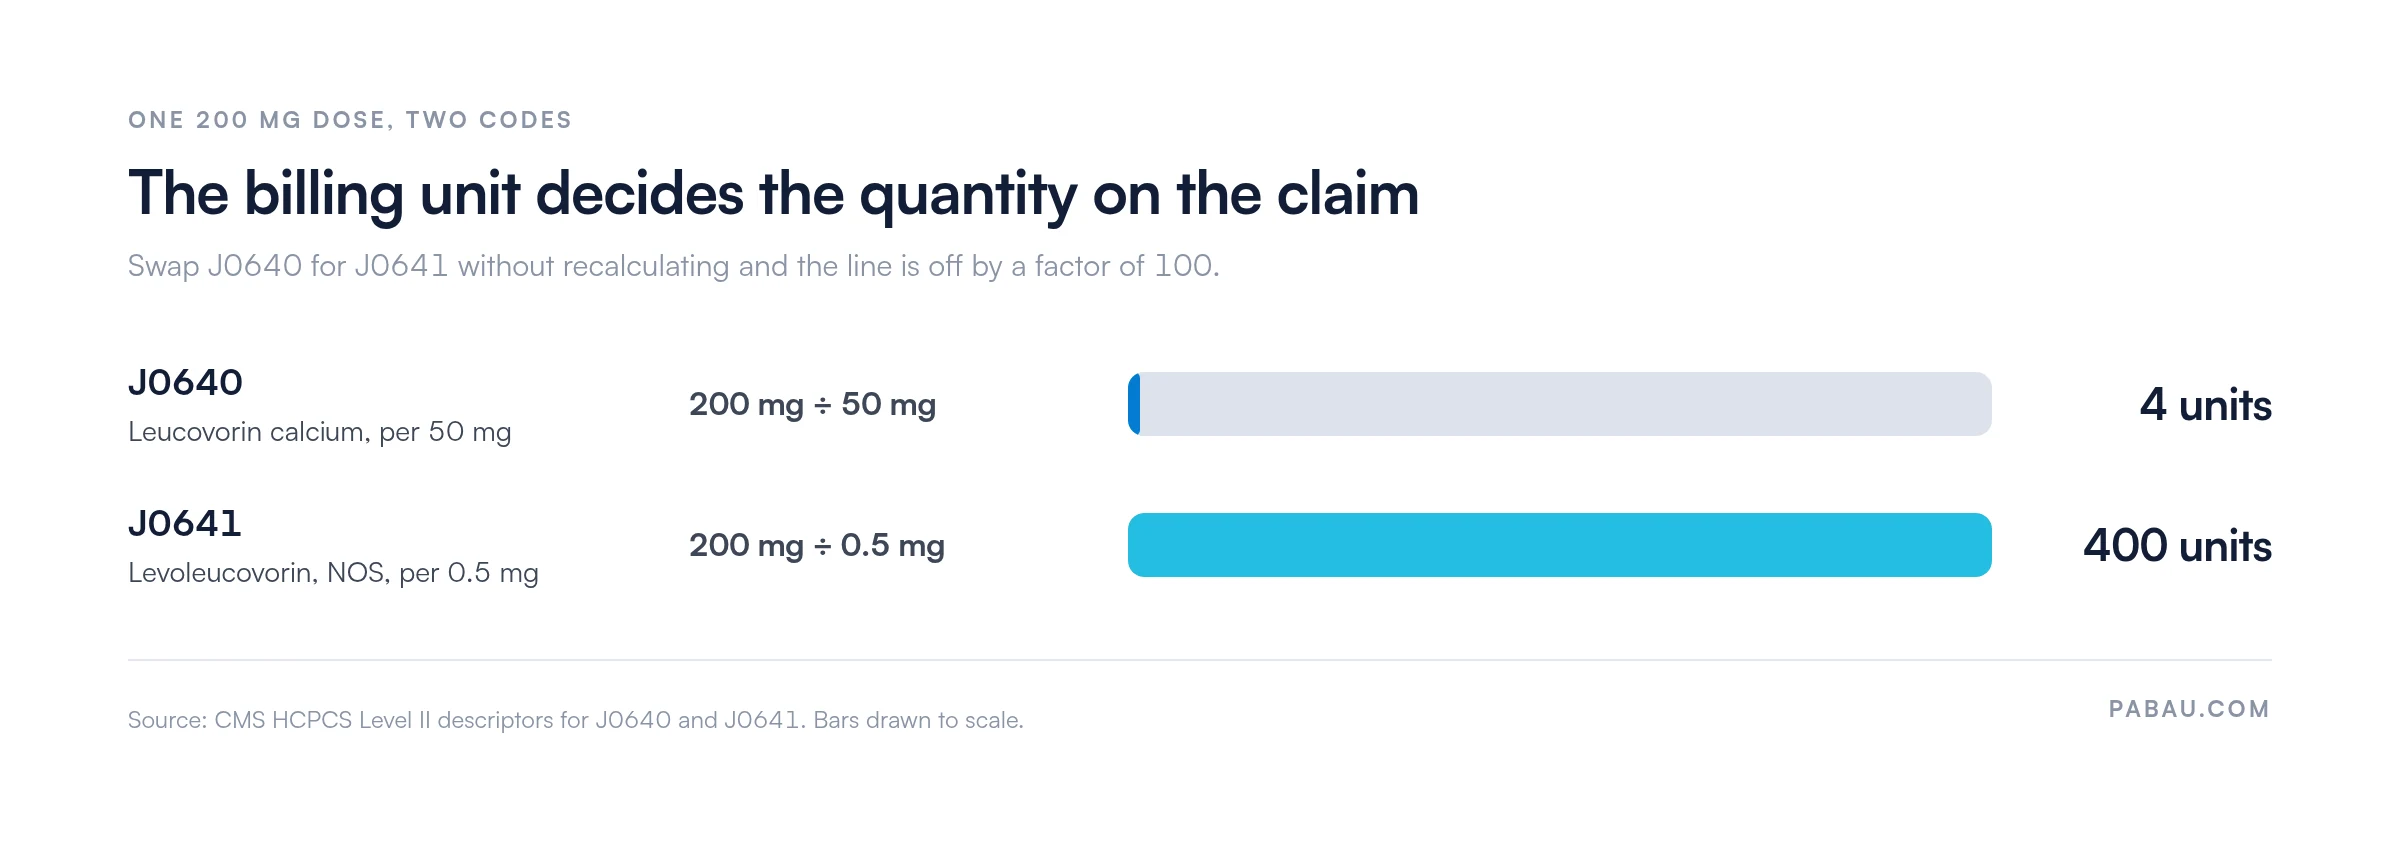
J0641 billing units are calculated by dividing the dose administered in milligrams by 0.5 mg. Each unit equals 0.5 mg of levoleucovorin. For a 200 mg infusion, the unit count is 400. For a 100 mg dose, it is 200 units.
Drug wastage: Medicare pays for the discarded portion of a single-dose vial. The record must show the amount drawn, the amount given, and the amount wasted. Under the CMS Medicare Claims Processing Manual, Chapter 17, §40, the claim reports both the administered units and the wasted units. The wasted units go on their own line with the JW modifier.
When none of a single-dose vial is wasted, add the JZ modifier to the administered line instead. CMS has required JZ on those claims since July 2023. Check commercial payers separately, since many exclude wastage billing by contract.
National Drug Code (NDC) reporting on J0641 is required by Medicaid and many commercial payers, so check each payer’s rules. Medicare Part B does not generally require an NDC on J-code claims. A payer that does require one will deny a claim that arrives without it.
When submitting on a CMS-1500 paper claim or 837P electronic transaction, report the NDC in the following format:
Each labeler assigns the NDCs for Fusilev and generic levoleucovorin, and they change with packaging updates. Always verify current NDCs against the FDA’s DailyMed database before submitting a claim. Never hardcode NDC numbers into billing templates. A stale NDC triggers a denial at any payer that checks it, and the appeal can take weeks.
An unsupported or missing diagnosis code is a leading cause of J0641 claim denial. The ICD-10-CM codes below represent the most common medical necessity pairings for levoleucovorin injection. Verify each code against the current CMS ICD-10-CM tabular list before submission, as code structures change annually.
Payer local coverage determinations (LCDs) may specify a narrower list of acceptable diagnosis codes. Check the applicable LCD on the CMS HCPCS coding and billing resource page and your payer’s coverage policy. Do it before submitting claims with less common pairings such as E53.8.
Before submitting a J0641 claim, run the diagnosis code through the payer’s LCD or coverage policy lookup. If the physician’s order does not specify the sub-site, C18.9 (colon cancer, unspecified) is more likely to pass initial edits. A site-specific code the record cannot support is riskier. Use the most specific code the documentation supports, but do not code more specifically than the record allows.
Medicare Part B reimburses J0641 at Average Sales Price (ASP) plus 6% in non-OPPS settings, such as a physician office. Hospital outpatient departments billing under OPPS receive a different payment rate based on the applicable Ambulatory Payment Classification (APC). The ASP+6% rate changes every quarter when CMS releases updated ASP pricing files.
Why no dollar figure is published here: ASP-based rates for J0641 change with each quarterly CMS update. Hardcoding a payment figure into billing documentation or system templates is a compliance risk, because teams keep billing the old rate after it changes.
Always retrieve the current quarter’s rate from the CMS Physician Fee Schedule search tool or the quarterly ASP drug pricing file published at cms.gov.
Prior authorization requirements for J0641 vary by payer and plan year. Medicare fee-for-service (traditional Medicare) does not require prior authorization for J0641, but Medicare Advantage plans and commercial payers frequently do. Some payers also impose step therapy: The patient must have failed or been documented as intolerant of leucovorin (J0640) before J0641 will be authorized.
Step therapy is not a universal requirement. Patients with documented intolerance to leucovorin, or clinical scenarios where leucovorin is contraindicated, may qualify for a step-therapy exception. The documentation to support an exception typically includes:
Always verify prior authorization requirements directly with the specific payer and plan before the date of service. Requirements change with plan year updates. A J0641 claim submitted without a required authorization is denied on first pass, and an appeal is the only way back. Tracking prior authorization status alongside medical billing compliance workflows reduces this exposure significantly.
J0641 denials follow predictable patterns. Most trace back to four root causes: Missing NDC, wrong units, unsupported diagnosis, and missing prior authorization. The table below maps each denial type to its resolution action. The reason codes on the remittance tell you which row applies, and our guide to medical billing denial codes explains each one.
Structured denial management processes catch these patterns before they pile up. Route J0641 denials into their own oncology drug workflow, separate from general claim denials. Resolution cycles shorten because each denial type has a fixed resolution path.
Complete documentation in the medical record is what separates a payable J0641 claim from one that gets pulled in a post-payment audit. Every element below should be present in the record and consistent with what appears on the claim.
Consistent clean claim submission practices mean the documentation is complete before the claim is generated, not assembled after a denial. A pre-submission checklist in the clinical workflow reduces audit exposure for high-dollar oncology drug codes like J0641. A well-prepared superbill that captures NDC, units, and diagnosis at the point of service is the most reliable starting point.
J0641 is a drug code only, so it does not include the administration service. Bill a separate CPT administration code for the infusion or injection on the same date of service. Levoleucovorin is a rescue and modulating agent, not chemotherapy, so the default is the therapeutic infusion code 96365.
NCCI (National Correct Coding Initiative) edits govern bundling between J0641 and administration codes, so confirm current edits before billing both.
When levoleucovorin is infused as part of a multi-drug chemotherapy session, sequence the administration codes by the infusion hierarchy rules. The primary (highest-level) infusion is reported first, then add-on codes for drugs given in sequence or at the same time.
Check current NCCI edits through the AAPC HCPCS code lookup to see whether a J0641 and administration pair is bundled in your billing setting.
When levoleucovorin runs alongside fluorouracil (5-FU) in a FOLFOX or FOLFIRI regimen, the chemotherapy infusion is the primary service. The levoleucovorin infusion then reports as a sequential (96367) or concurrent (96368) therapeutic infusion add-on, depending on overlap. Confirm the current NCCI edit pair before submitting.
Most oncology billing teams check J0641 claims by hand. Someone converts the dose to units, looks up the NDC, and confirms the prior authorization number before the claim goes out. A missed step shows up weeks later as a denial.
Pabau moves those checks into the claim itself. Its infusion practice claims software scrubs every claim for missing or invalid details before it leaves Pabau. US claims then go out as CMS-1500s through Claim.MD to thousands of payers.
Prior authorizations are stored as cases, so the authorization code follows the appointment through to the claim. Any claim still missing a code gets flagged before submission. Your team fixes one field and resubmits, instead of building an appeal weeks later.

Pabau checks each claim for missing or invalid details before it goes to the payer. Prior authorization codes follow the appointment through to the claim, so fewer drug lines come back denied.

J0641 claims fail on arithmetic and paperwork far more often than on clinical grounds. Bill units at 0.5 mg each, and confirm the product is Fusilev or a generic rather than Khapzory. Then check each payer’s NDC and wastage rules before the claim goes out.
The trade-off is a few minutes at the front of the process. A pre-submission check takes minutes, while a denied oncology drug line can take weeks of appeals to recover. Book a demo to see how Pabau checks drug claims for missing details before they reach the payer.

Need a denial resolution framework for drug claims? Denial management in healthcare covers root-cause analysis and appeal strategies for common payer rejections.
Need to decode the reason code on a J0641 denial? Denial codes in medical billing explains common CARC and RARC codes that appear on drug-claim EOBs.
Billing racemic leucovorin instead? HCPCS code J0640 covers leucovorin calcium units, coverage, and documentation.
Want to understand the broader claim lifecycle for Part B drugs? What is revenue cycle management maps the full journey from physician order to payment posting.
HCPCS code J0641 represents injection, levoleucovorin, not otherwise specified, billed at 0.5 mg per unit. It covers Fusilev and generic levoleucovorin. Khapzory bills under its own code, J0642. J0641 is not interchangeable with J0640, which covers leucovorin calcium (the racemic mixture).
Divide the total dose administered in milligrams by 0.5 to get the units to bill. A 200 mg dose is 400 units, and a 100 mg dose is 200 units. Applying J0640’s 50 mg unit to a J0641 claim is a frequent and easily corrected coding error.
J0640 covers leucovorin calcium, the racemic mixture of L and D isomers, billed at 50 mg per unit. J0641 covers levoleucovorin, the active L-isomer only, billed at 0.5 mg per unit. They are different drugs, different codes, and different ASP payment rates. Billing one under the other generates a denial.
Medicaid and many commercial payers require an NDC on J0641 claims, so check each payer. Medicare Part B does not generally require one on J-code claims. Where it is required, report it with the N4 qualifier, in 11-digit format, with the UN unit qualifier. Verify the current NDC for Fusilev or the generic product on FDA DailyMed, since NDCs change with packaging updates.
Step therapy applies under many commercial payers and some Medicare Advantage plans. They require documented failure of or intolerance to leucovorin (J0640) before J0641 is authorized. Traditional Medicare fee-for-service does not impose step therapy for J0641. Verify requirements with the specific payer and plan year before the date of service.
Yes. Under the CMS Claims Processing Manual, Chapter 17, §40, Medicare pays for the discarded portion of a single-dose vial. The record must document the amount drawn, given, and wasted. Report the wasted units on their own line with the JW modifier. When none of the vial is wasted, add the JZ modifier, which CMS has required since July 2023. Many commercial payers exclude wastage billing by contract, so verify their policy first.
CMS updates ASP pricing for J0641 quarterly. Never use a hardcoded dollar figure in billing templates. Retrieve the current rate from the CMS ASP drug pricing file published at cms.gov at the start of each quarter.



