

HCPCS Code J1110: Dihydroergotamine mesylate injection billing guide
HCPCS Code J1110: Official descriptor and drug overview HCPCS Code J1110 is the ...

Last Updated: Oct 29, 2026
B4103 is the HCPCS Level II code for enteral formula, for pediatrics, used to replace fluids and electrolytes (e.g., clear liquids), 500 ml = 1 unit. Medicare treats it as non-covered, no benefit, so Medicare claims for B4103 will not be paid.
Payment depends on Medicaid or a commercial plan, each with its own fee schedule, prior authorization and documentation rules. Most avoidable errors come from billing the adult code B4102, miscounting the 500 mL unit, or skipping a plan's prior authorization.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

B4103 describes pediatric enteral formula that replaces fluids and electrolytes, such as clear liquids, billed at one unit per 500 mL.
Medicare treats B4102 and B4103 as non-covered, no benefit, so Medicare claims for B4103 will not be paid.
Payment depends on Medicaid or a commercial plan, so check the fee schedule, prior authorization and documentation rules before dispensing.
On Medicare claims, the GY modifier marks B4103 as having no Medicare benefit, so the denial can move on to the next payer.
Pabau’s claims management software tracks each B4103 claim’s status and payer follow-up, so an expected denial moves on to the next payer.
HCPCS code B4103 is an active Level II HCPCS B-series code for 2026. It covers enteral formula that replaces fluids and electrolytes (such as clear liquids) for pediatric patients, billed per 500 mL.
The Centers for Medicare and Medicaid Services (CMS) maintains the HCPCS Level II code set. B4103 sits in the B4100 series of enteral nutrition supply codes, one block of the wider HCPCS code set.
Medicare classes B4103 as non-covered, no benefit, so payment has to come from Medicaid, a commercial plan or the patient. Three parameters decide whether B4103 is the right code for a product, and Medicare status decides who you bill.
The scope of B4103 is narrow. The formula must replace fluids and electrolytes for a pediatric patient. Formulas whose main job is calories or nutritional support belong to other B41xx codes.
Fitting the code does not make a product payable. Medicare pays for none of these products, whether the child takes them by mouth or through a feeding tube. Medicaid and commercial coverage depends on the state or the plan.
The B4100 series groups enteral nutrition HCPCS codes by formula type, patient population, and caloric density. Picking the wrong code in this series is a common reason for rejected claims.
The AAPC HCPCS Level II code database provides full descriptors and coding guidance for each code in this series. B4103 needs both criteria at once: A pediatric patient and a fluid and electrolyte replacement purpose.
An adult receiving the same electrolyte fluid is billed under B4102 instead. A child receiving a high-calorie nutritional formula falls under a different B-series code.
Billing a covered formula code such as B4158 for an electrolyte fluid, so that Medicare pays, is miscoding. Auditors look for exactly that swap.
Medicare does not cover HCPCS code B4103. The DME MAC Enteral Nutrition Policy Article A58833, which accompanies LCD L38955 in every DME MAC jurisdiction, names it directly. It states that “electrolyte-containing fluids (B4102 and B4103) are not indicated for the maintenance of weight and strength and are therefore non-covered, no benefit.”
“No benefit” means the denial comes from the benefit category, so the paperwork cannot change it. That has three practical consequences:
The DME Information Form (DIF), CMS-10126, has not been required since January 1, 2023. Older guidance that ties B4103 coverage to a certificate of medical necessity is out of date.
Medicaid and commercial coverage for B4103 depends on the state or payer. Wisconsin ForwardHealth and Minnesota DHS both publish enteral formula procedure code coverage policies. Their eligibility thresholds, quantity limits, and prior authorization rules differ from each other.
Before the first delivery, confirm these points with each plan:
Where Medicare is primary, tell the patient or family in writing that Medicare will not pay. An Advance Beneficiary Notice (ABN) is not required for a no-benefit item. A voluntary written notice of the expected cost still prevents a billing dispute later.
Run insurance eligibility verification before dispensing, so you know which plan is primary and what it covers.
Documentation will not change a Medicare denial for B4103, but Medicaid and commercial plans rely on it. Their reviewers expect records that support medical necessity at every level. That means the clinical need, the order, the formula type and quantity dispensed, and the supplier’s records.
Required documentation for a compliant B4103 claim includes:
The order is the single most audited document. An order that says “enteral formula as needed” without a formula type and quantity will not satisfy most payers.
B4103 billing follows the standard DMEPOS claim workflow. The key billing decisions are unit calculation, modifier selection, and claim routing.
One unit of B4103 equals 500 mL. For a 30-day supply, divide the total monthly volume in mL by 500 to get the units to bill. A pediatric patient receiving 1,000 mL per day for 30 days requires 60 units (30,000 mL / 500 = 60). Bill the exact units dispensed, not a rounded estimate.
On Medicare claims, GY is the modifier that matters for B4103. Medicaid and commercial payers may want BO, a different modifier, or none at all.
Verify modifier requirements against each payer’s DME policy before submitting. Once the claim is out, Pabau’s claims management software tracks its status through to payment. A denied line is then easy to spot and follow up.

DMEPOS claims for B4103 use the CMS-1500 claim form or its 837P electronic equivalent. Place of service code 12 (Home) applies when the formula is dispensed for home use, which is the most common scenario.
For Medicare, the supplier submits to the DME MAC for the beneficiary’s state, not to the local Medicare Administrative Contractor (MAC). The supplier then forwards the Medicare denial to Medicaid or the secondary plan, as the flow below shows.
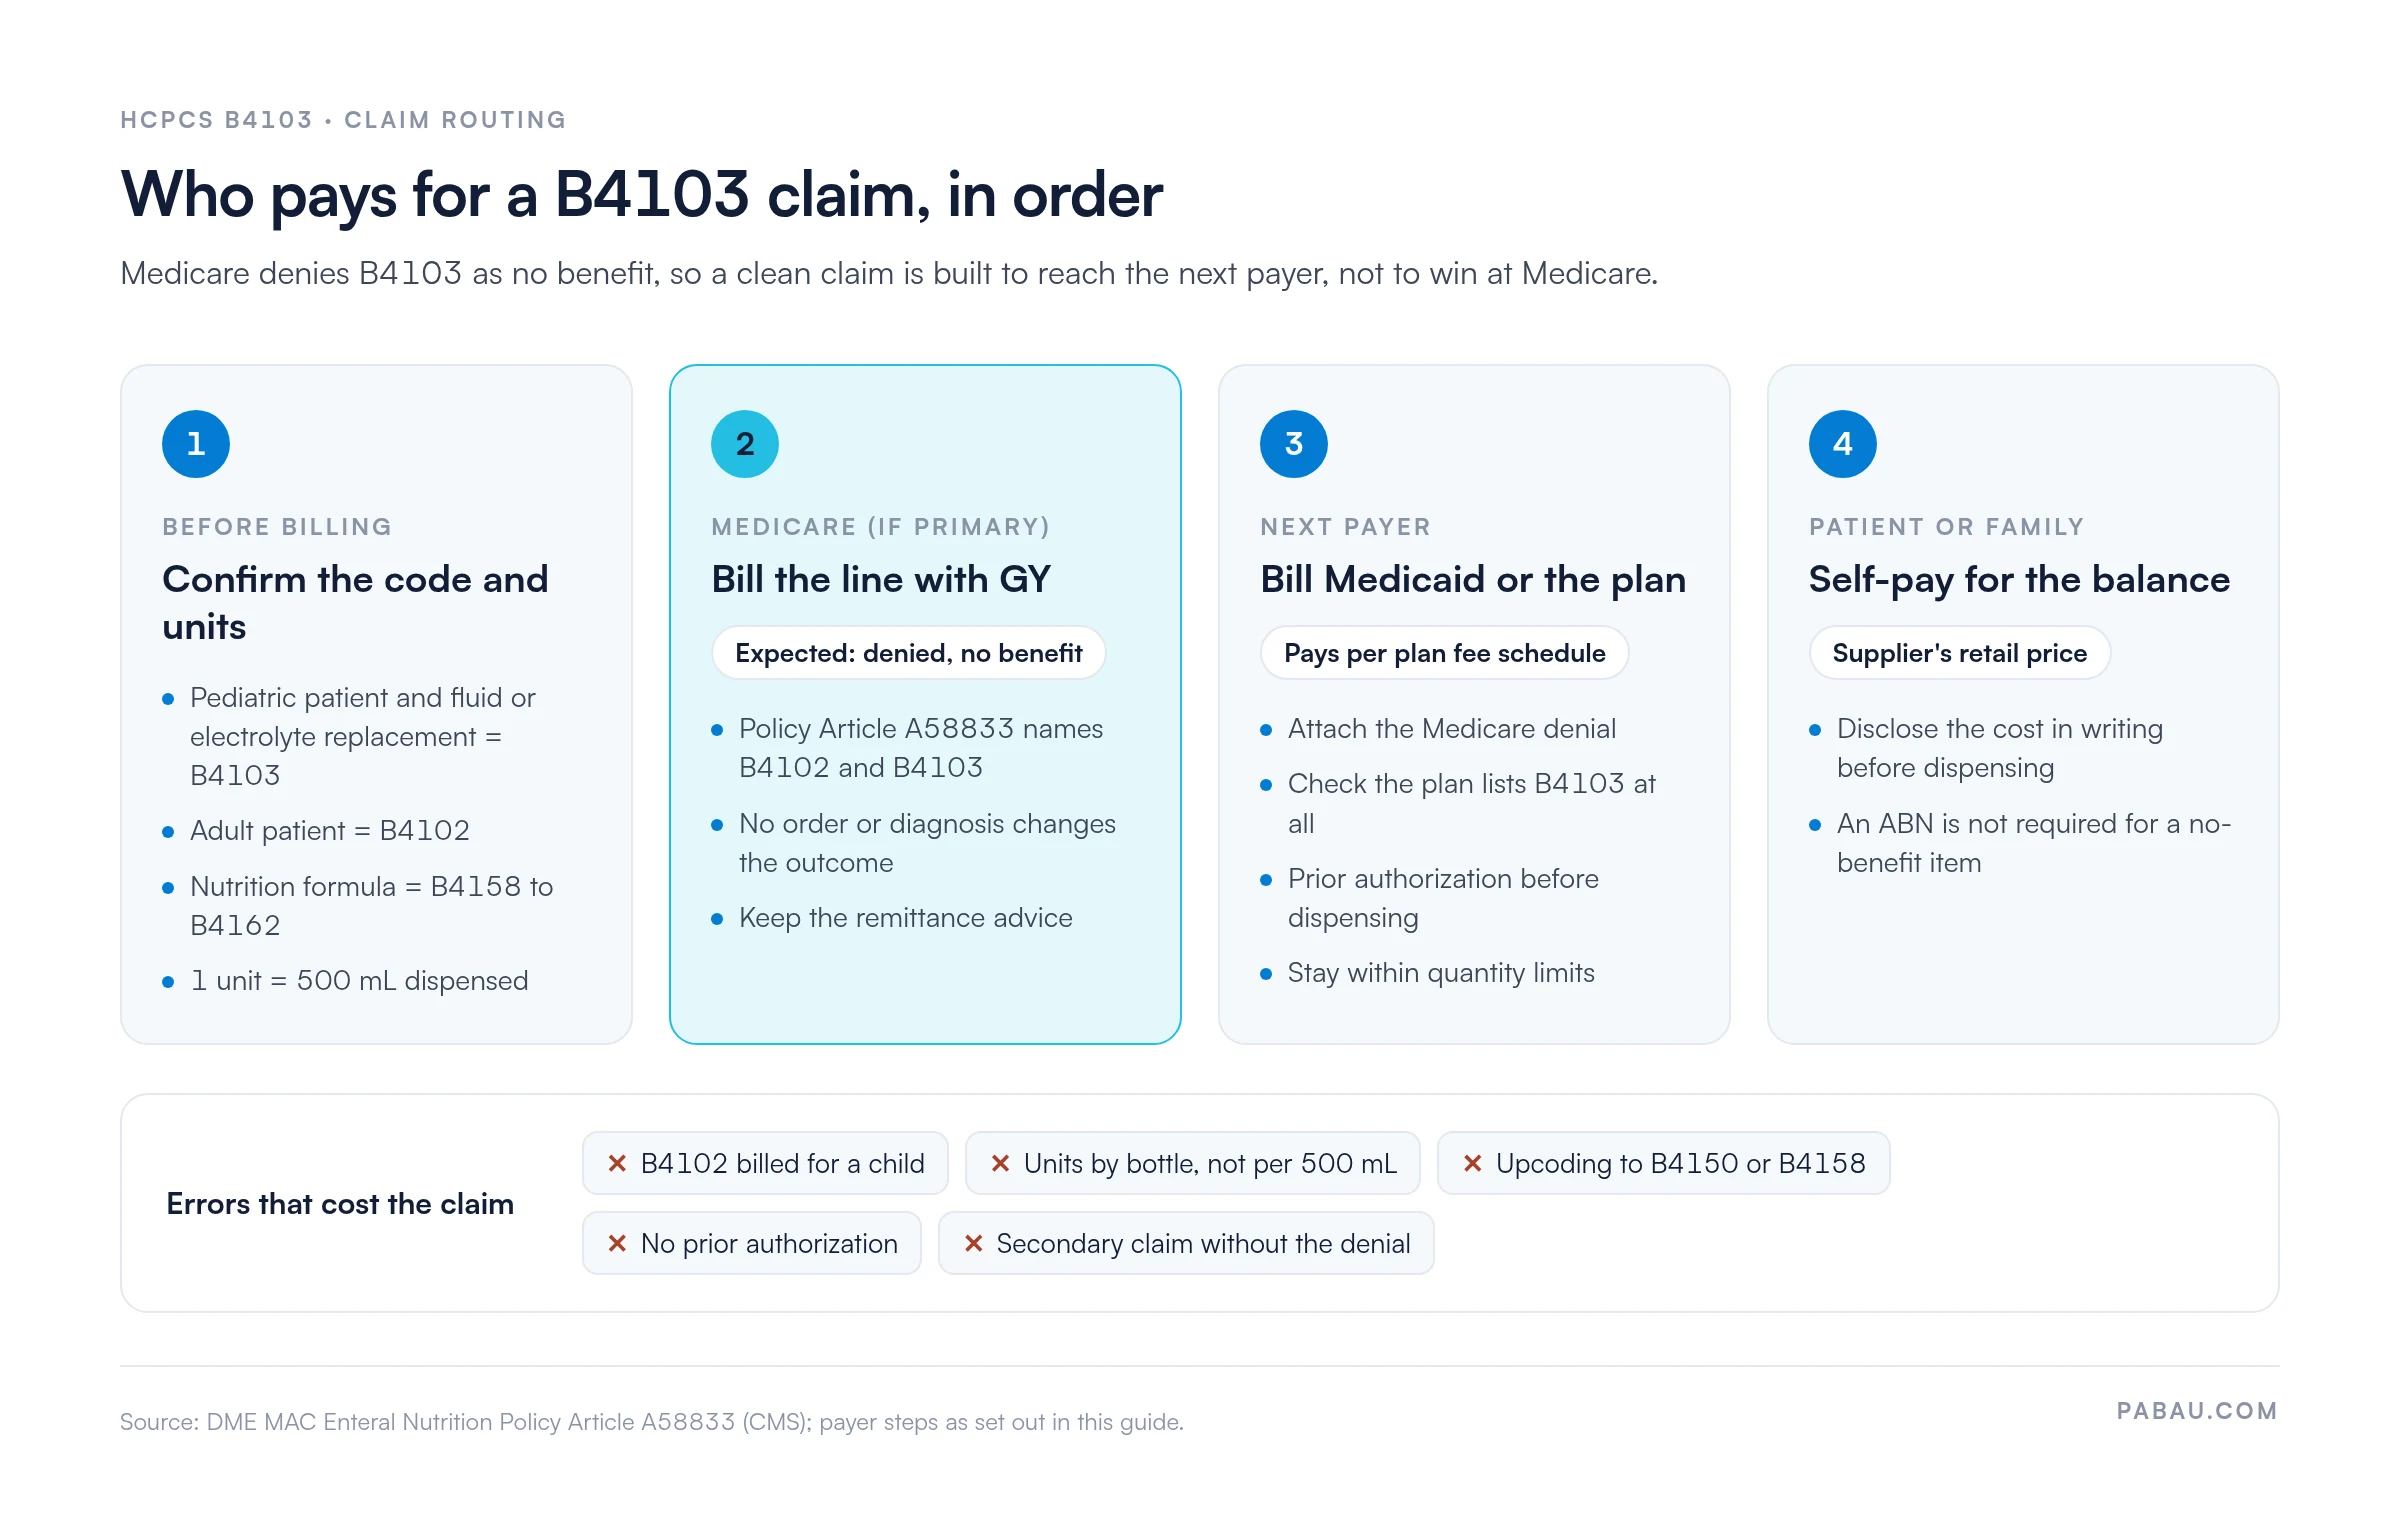
Medicare does not pay for B4103, because claims deny as no benefit. Reimbursement comes from Medicaid, a commercial plan or the patient:
Review each state and commercial fee schedule annually for budget planning. A revenue cycle management process that tracks payer rates shows when a change is big enough to affect margin on enteral nutrition products.
A Medicare denial on B4103 is expected, so the goal there is a clean denial and a correct bill to the next payer. The other reasons below are errors you can prevent.
Structured denial management workflows separate expected no-benefit denials from errors you can fix, and route the fixable ones before filing deadlines expire. Wrong-code denials go through a corrected claim. Documentation denials need an appeal with supporting records attached.
Enteral nutrition HCPCS codes, including B4103, carry heightened OIG and Recovery Audit Contractor (RAC) scrutiny. The Office of Inspector General has historically flagged enteral nutrition as a high-error category in DME billing. Documentation problems and upcoding were the primary findings.
The patterns that attract audit attention for B-series enteral codes include:
Noridian Healthcare Solutions, the DME MAC for Jurisdictions A and D, publishes an “Enteral Nutrition Correct Coding and Billing” article at med.noridianmedicare.com. It outlines specific compliance expectations for B-series codes. Review it against your internal billing procedures at least annually.
Sound medical billing compliance for enteral nutrition means auditing claims before they go out. Check order dates, prior authorization approvals, unit calculations, and dispensing records.
A clean claim submission for B4103 has five elements in order before it leaves the supplier:
When one element is missing, the claim denies on the first pass. The cost of rework (appeal prep, refiling, delayed payment) often exceeds the value of the claim itself.
Run a monthly pre-submission audit on B4103 claims. Pull every claim billed in the prior 30 days and check three fields. Compare units billed with the mL totals in the dispensing records, and prior authorization dates with the claim period. Then confirm GY sits on every line sent to Medicare. Catching an error before submission costs minutes, while a denial costs far more.
Most of the work on a B4103 claim happens after Medicare says no. Your team posts the expected denial, attaches it to the Medicaid or secondary claim, and chases that claim to payment.
Pabau’s claims management software keeps that chain in one place. Each claim moves through clear statuses, from Pending and Submitted to Paid or Error, so a denied claim stands out. The Chase Invoice action handles payer follow-up from the same dashboard.
Orders, patient records and signed forms live in the same platform. When a Medicaid plan asks for documentation, your team can pull it without searching shared drives.

Pabau’s claims management tools track every claim’s status and payer follow-up, so B4103 claims reach the right payer with the right paperwork. See how it works for your practice.

HCPCS code B4103 is a narrow, well-defined code. Its three parameters (pediatric patient, fluid and electrolyte replacement, 500 mL per unit) are clear once you know them. The harder fact is financial: Medicare will not pay for it, whatever the file contains.
Plan for that from intake. Add GY to the Medicare line, collect the denial, and send the claim to Medicaid, the commercial plan or the family. The claims that lose money are the ones sent to the wrong payer or upcoded to a covered formula code.
Check each plan’s coverage and prior authorization before the first delivery, and tell the family about likely costs early. Book a demo to see how Pabau tracks claim status, payer follow-up and denials for enteral nutrition claims.

Need a structured approach to managing claim denials? Denial management in healthcare covers the end-to-end workflow for tracking, appealing, and preventing claim rejections.
Want to understand how enteral billing fits into the broader revenue cycle? Revenue cycle management fundamentals explains how DME and enteral nutrition claims connect to payment posting and accounts receivable.
Looking for guidance on clean claim requirements? Clean claim submission best practices outlines what payers check before processing a DMEPOS claim.
Billing the formula that Medicare does cover? HCPCS code B4150 explains coverage and units for nutritionally complete tube-feeding formula.
Coding a pediatric formula for an inherited metabolic disease? HCPCS code B4162 covers the special metabolic formula code in the same series.
HCPCS code B4103 describes pediatric enteral formula used to replace fluids and electrolytes, such as clear liquids, billed per 500 mL unit. It applies only to pediatric patients and excludes calorically dense formulas and adult electrolyte products. Medicare does not pay for it, so payment depends on Medicaid or a commercial plan.
Units for B4103 are billed in 500 mL increments. Divide the total volume dispensed in the billing period by 500 to determine units. A patient receiving 1,000 mL per day for 30 days generates 60 billable units. Bill the units dispensed, as recorded in the supplier’s delivery records.
B4102 is the adult code for electrolyte and fluid replacement formula, and B4103 is the pediatric code. Both are billed at 500 mL per unit, and Medicare treats both as non-covered, no benefit. Billing B4102 for a pediatric patient is a coding error that Medicaid and commercial plans will reject.
On Medicare claims, add the GY modifier to show that B4103 has no Medicare benefit. GA and GZ do not apply, because they cover items expected to be denied as not reasonable and necessary. Medicaid and commercial plans may ask for BO or other modifiers, so check each plan’s billing manual.
No. Medicare treats B4103 as non-covered, no benefit, so Medicare claims for it will not be paid. CMS Policy Article A58833 says electrolyte-containing fluids (B4102 and B4103) are non-covered. There is no exception for tube feeding, a physician order or a certificate of medical necessity. Coverage under Medicaid or a commercial plan depends on the state or payer.
A Medicare claim for B4103 always denies as no benefit, so that denial is expected. With Medicaid and commercial plans, the usual causes are a wrong code, a unit miscount, missing prior authorization, or a diagnosis outside the plan’s policy. A secondary claim sent without the Medicare denial attached also tends to reject.




