

HCPCS Code J2547: Peramivir units, NDC, and billing guide
HCPCS Code J2547: What it covers and when to use it HCPCS Code J2547 covers inje...

Last Updated: Nov 2, 2026
J3000 is the CCSD code for anastomosis of common bile duct, an operation that joins the common bile duct to the jejunum or duodenum. UK private medical insurers such as Bupa, AXA Health and Aviva use it to price and pay surgical claims.
J3000 sits in CCSD chapter 11.0.0 (Abdomen) under sub-chapter 11.7.0, with CCSD reference Fk.139. A join made at the hepatic duct is coded J2900 instead. Excision of a bile duct segment with anastomosis to the bowel is J2720.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD code J3000 covers anastomosis of the common bile duct, a major hepatobiliary operation billed to UK private medical insurers.
The code sits in CCSD chapter 11.0.0 (Abdomen) under sub-chapter 11.7.0, with CCSD reference Fk.139.
An anastomosis at the hepatic duct is J2900, and excision of a bile duct segment with anastomosis to the bowel is J2720.
Bupa, AXA Health, Aviva and other UK insurers expect pre-authorization and an operative note that names the technique and the level of the join.
Pabau, the practice management platform we build, sends private medical insurance claims through Healthcode and keeps each authorization with the patient record.
CCSD code J3000 is the procedure code for anastomosis of the common bile duct in UK private healthcare billing. It describes an operation that joins the common bile duct (CBD) to another structure to restore bile flow. The partner is usually a loop of jejunum or the duodenum. The code is maintained by the Clinical Coding & Schedule Development (CCSD) Group, and UK private medical insurers use it to price and pay surgical claims.
J3000 is a surgeon’s code for an open or specialist hepatobiliary operation. It does not cover endoscopic stenting, balloon dilatation or percutaneous drainage of the bile duct, which have their own CCSD codes. Where the anastomosis is one step of a larger operation, CCSD coding principles decide whether J3000 can be added. The section on billing alongside other procedures covers this below.
J3000 sits in CCSD chapter 11.0.0, which covers the abdomen excluding urinary and reproductive organs. Its sub-chapter is 11.7.0, other organs (mainly digestive), and its CCSD reference is Fk.139. Within the CCSD procedure codes, the bile duct operations run in sequence:
Anastomosis of the common bile duct is a major abdominal operation. The surgeon creates a new connection between the CBD and the gut so bile can drain past a blockage or injury. The two techniques most often billed under J3000 are choledochojejunostomy and choledochoduodenostomy.
The approach is almost always open, though some specialist centers perform the operation laparoscopically. The J3000 descriptor does not name an approach. Before claiming a laparoscopic case, check the current CCSD schedule and the insurer’s own rules.
Coders need the clinical context behind J3000 to pair it with the correct ICD-10 diagnosis code. Most cases fall into one of five groups:
The documented indication drives the diagnosis code. Each scenario maps to a different ICD-10 group, and a mismatch between the two is a common reason insurers query a claim.
UK insurers expect a WHO ICD-10 diagnosis code alongside the CCSD procedure code. The principal diagnosis should reflect the condition that made the operation necessary. Confirm each code in the WHO ICD-10 browser before submission.
These are WHO ICD-10 codes, not the US ICD-10-CM variants, so K91.8 and T81.8 stop at four characters. The treating surgeon’s documented diagnosis is the authoritative source for the final choice. A malignancy code such as C24.0 may prompt the insurer to ask for oncology or multidisciplinary team notes before authorizing surgery.
J3000 is straightforward when the operation is an isolated CBD anastomosis. Confusion starts when the join sits at the hepatic duct or part of the duct is removed. It also arises when the duct is repaired rather than rerouted. The table below maps the codes most often mixed up with J3000.
Work through the operative note in a fixed order. The first question it answers with a yes settles the code.
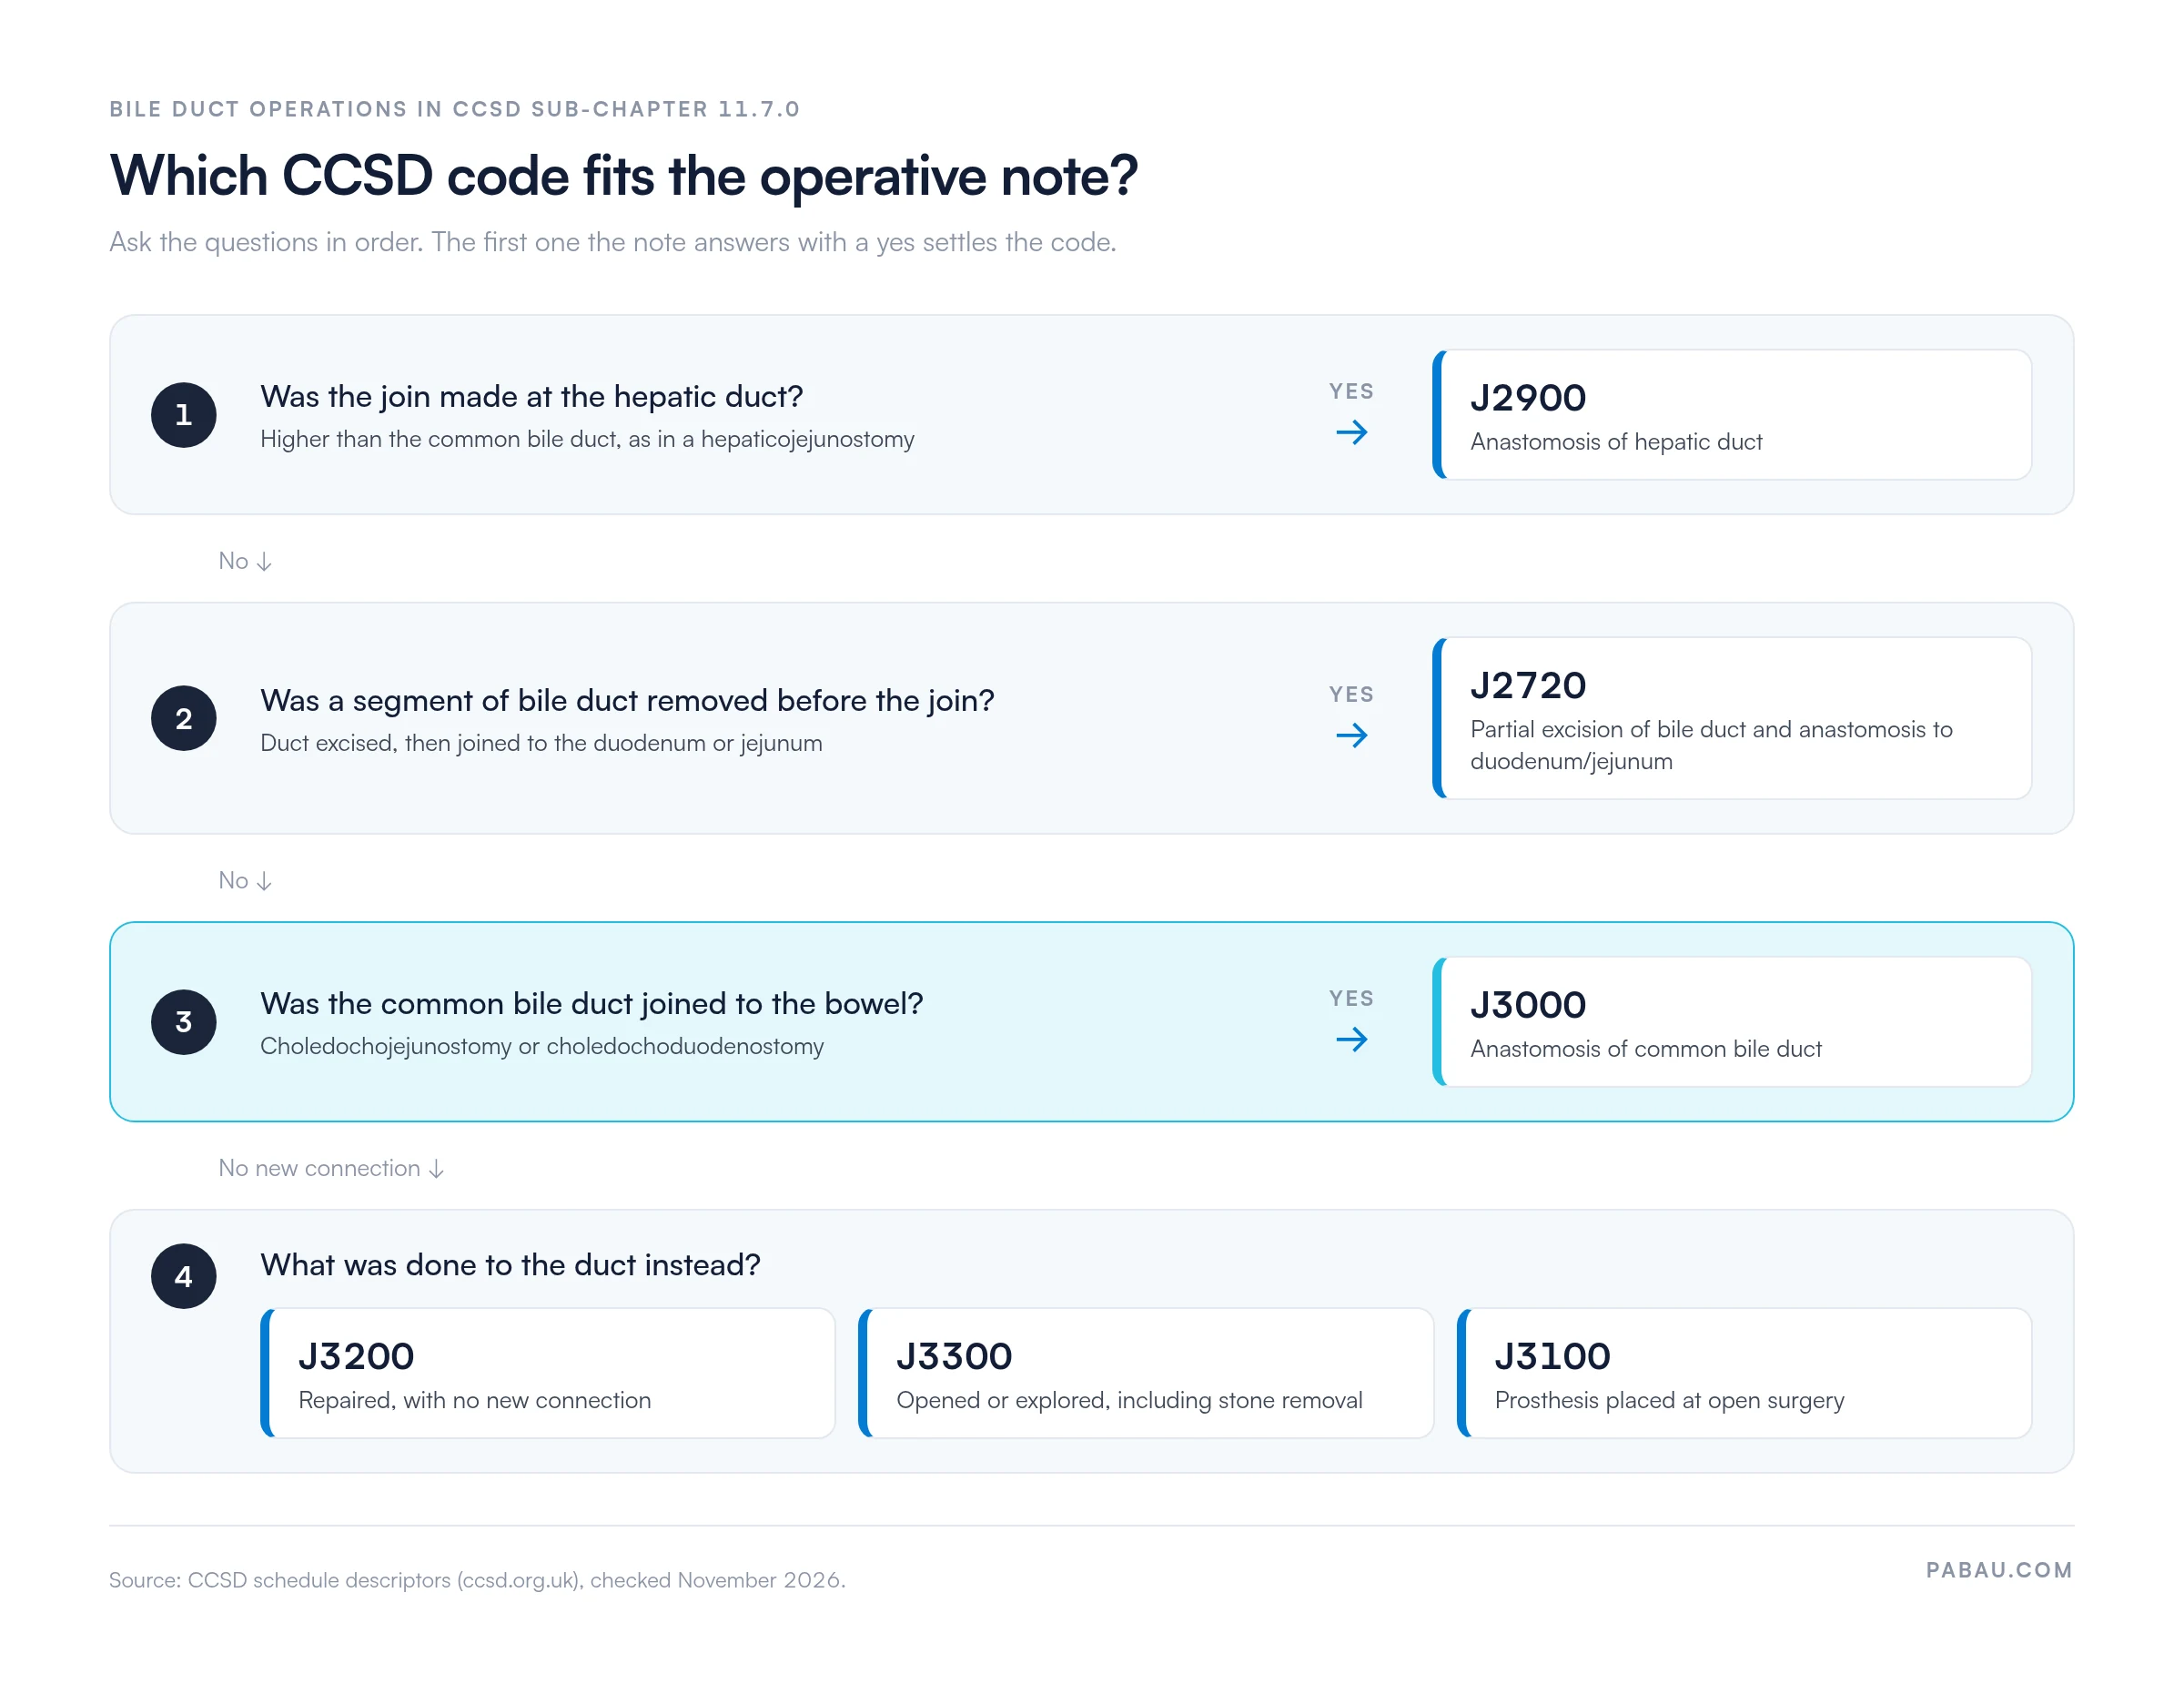
Always read the operative report before coding. If the note says hepaticojejunostomy rather than choledochojejunostomy, confirm where the join was made. A hepatic duct join is J2900, not J3000. Coding from the procedure title alone is a leading cause of code mismatches.
Insurers routinely query a note that says only “CBD anastomosis performed.” The operative report, and the pre-authorization request where relevant, should cover these points:
Contemporaneous notes are easier to defend than a letter written months later to explain the case. Keep the imaging that supported the decision, such as MRCP, ERCP or CT findings, with the operative note.
UK private medical insurers expect the patient to get pre-authorization before elective surgery like J3000. The Bupa CCSD code schedule and equivalent guides from other insurers set out the fee for each code and what they expect at submission. Requirements vary by insurer:
Fee schedules change, so never rely on a prior-year figure. Check the current J3000 fee with the relevant insurer before invoicing. Emergency cases, such as bile duct repair after trauma, cannot wait for authorization. Contact the insurer as soon as possible afterward and follow its process for urgent admissions.
Insurers query or decline J3000 claims for a predictable set of reasons. Knowing them before submission costs less than managing appeals afterward:
Anastomosis of the common bile duct often forms one part of a larger hepatobiliary operation. Whether J3000 can be added depends on the principal procedure and on the CCSD coding principles in the CCSD Technical Guide. Check the insurer’s own rules as well, since they can differ.
Pancreaticoduodenectomy (Whipple procedure): A biliary anastomosis is a standard part of the Whipple reconstruction. Code the principal operation, and check CCSD coding principles before adding J3000 to it. Adding J3000 without that check risks an unbundling query.
Liver resection with biliary reconstruction: When a resection needs a bile duct join, the insurer’s multiple-procedure rules decide how the second code is paid. Document a separate indication for each procedure in the operative note.
Cholecystectomy in the same session: A gallbladder removal performed alongside the anastomosis may carry its own code. When the CBD was explored during gallbladder surgery without a new connection, CCSD code J1820 may fit better than J3000.
When J3000 is performed alongside a more complex procedure, identify the principal procedure first. Then record each procedure’s own surgical indication in the operative report. That lets the insurer’s clinical reviewer see why more than one code is on the claim.
Billing teams should follow the same steps on every J3000 claim to avoid the common query triggers. They apply whatever portal or system the practice uses:

Many billing teams build a J3000 claim from several places. The operative note sits in one system, the pre-authorization letter in an inbox, and the fee schedule in an insurer portal. Each handoff is a chance for the wrong code or a missing number to slip through.
Pabau keeps the clinical notes, the insurer authorization and the claim together in the patient record. It stores each pre-authorization as a case, so the authorization code follows the appointment through to the claim. The claim then goes through Healthcode to insurers such as Bupa, AXA Health and Vitality.
When an insurer queries the claim months later, the documentation is already in that record. Your team can answer without switching systems. Insurance claiming is included in every Pabau subscription.

Pabau keeps operative notes, insurer authorizations and Healthcode claim submission in one patient record. Your team can submit J3000 and related claims to UK insurers without switching systems.

Code J3000 only after the operative note settles two questions. Was the join made at the common bile duct rather than the hepatic duct? Was the duct joined without removing a segment first? Two clear answers make J3000 the right code, and the note should state both in plain words.
That small amount of extra documentation pays off when an insurer reviews the claim. It keeps an authorized major operation from coming back as a query months later.
Pabau keeps the code, the diagnosis and the authorization number in one record. Book a demo to see how your team can get J3000 claims right the first time.

Billing other CCSD codes for the same insurer? Bupa CCSD code schedule covers the Bupa-recognized procedure codes and fee lookups.
Need to tighten up your claims workflow? Claims management software for private practices explains how Pabau sends claims through Healthcode and tracks their status.
Explored the bile duct during gallbladder surgery? CCSD code J1820: Cholecystectomy with bile duct exploration covers the code for that combined operation.
Coding a gallbladder removal on its own? CCSD code J1830: Laparoscopic cholecystectomy billing guide walks through a neighboring code in sub-chapter 11.7.0.
Coding other procedures in sub-chapter 11.7.0? CCSD code J1300: Percutaneous biopsy of lesion of liver covers another code from the same part of the schedule.
CCSD code J3000 covers anastomosis of the common bile duct. The surgeon creates a new connection between the duct and the jejunum or duodenum to restore bile drainage. Choledochojejunostomy and choledochoduodenostomy are the usual techniques. Endoscopic stenting and hepatic duct anastomosis have their own CCSD codes.
UK private medical insurers such as Bupa, AXA Health, Aviva and Vitality use CCSD codes to price and pay claims. The schedule is maintained by the Clinical Coding & Schedule Development Group. Surgeons and their billing teams put J3000 on the invoice for a common bile duct anastomosis.
J3000 applies when the join is made at the common bile duct. J2900, anastomosis of hepatic duct, applies when the join sits higher, at the hepatic duct. A hepaticojejunostomy is usually a J2900 case, so confirm the level in the operative note before choosing.
Common pairings are K83.1 (obstruction of bile duct) and K91.8 (other postprocedural disorders of digestive system). C24.0 (malignant neoplasm of extrahepatic bile duct) and K86.1 (other chronic pancreatitis) are also common. Match the code to the surgeon’s documented diagnosis. Confirm it in the WHO ICD-10 browser before submission.
Yes, UK private medical insurers expect pre-authorization before elective surgery like J3000. Emergency operations cannot wait, so contact the insurer as soon as possible afterward. Check each insurer’s current rules, since they vary.
The usual reasons are a missing pre-authorization number and a diagnosis code that does not match the indication. Others include an operative note too thin to confirm the descriptor, or J3000 claimed for a hepatic duct join. Separate claims for bundled steps also draw queries.




