

HCPCS Code P9612: Catheterization for urine specimen collection
HCPCS Code P9612: Definition and code attributes HCPCS Code P9612 is the HCPCS L...

Last Updated: Oct 26, 2026
H1880 is the CCSD code for laparoscopically assisted left colon resection. UK private medical insurers such as Bupa and AXA Health pay the surgeon's fee against it.
H1880 sits in section 11.5.0 Large Intestine of the CCSD Schedule, under reference Fk.073. The open operation is coded H0900, and a robotic-assisted left hemicolectomy is coded H1882.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD code H1880 covers a laparoscopically assisted left colon resection in UK private healthcare, under CCSD reference Fk.073.
The approach picks the code: H0900 for open excision of the left hemicolon, H1880 laparoscopic, and H1882 robotic-assisted.
UK private medical insurers such as Bupa and AXA Health expect pre-authorization, and the authorization number belongs on the invoice.
Pair H1880 with an ICD-10 diagnosis that matches the segment removed, such as C18.6 for a descending colon tumor.
CCSD code H1880 is the UK private healthcare code for a laparoscopically assisted left colon resection. It sits in section 11.5.0 Large Intestine, within chapter 11.0.0 Abdomen (Excl. Urinary & Reproductive Organs) of the CCSD Schedule. Its CCSD reference is Fk.073.
CCSD stands for Clinical Coding and Schedule Development. The CCSD Group maintains the codes UK private consultants quote on their invoices. Private medical insurers such as Bupa and AXA Health use them to identify the procedure they are paying for.
The current descriptor is “Laparoscopically assisted left colon resection.” CCSD records that it replaced an older description, “Laparoscopic colonic resection.” Quote the current wording on invoices and correspondence, not the old one.
The CCSD Group does not set fees or decide reimbursement. Each insurer applies its own fee schedule and benefit rules to H1880. For Bupa patients, check how Bupa uses CCSD codes before you quote a fee.
Read the operation note against the technique before you assign H1880. The descriptor depends on how the operation was done, not only on which segment came out.
A laparoscopically assisted left colon resection usually follows this sequence:
Laparoscopic work followed by a small open incision is what “laparoscopically assisted” describes. Record each stage in the operation note, so the note supports the code on the claim.
The CCSD Schedule separates left colon resection by surgical approach. Code from the approach recorded in the operation note, never from the booking or the theatre list.
Some laparoscopic operations are converted to open surgery. CCSD’s coding principles and each insurer’s rules decide which code applies after a conversion. Check both before you submit, and record the conversion and its reason in the operation note.
The same applies when the anastomosis is completed fully inside the abdomen. Confirm the code with the CCSD entry and the insurer before you invoice.
The anatomy matters as much as the approach. These codes sit near H1880 in the schedule and describe different segments or extents of resection.
Each descriptor above is quoted from the CCSD Schedule. When an operation goes beyond a standard left colon resection, look for the code that describes the larger procedure.
The chart below puts both checks in order, with the segment first and the approach second. If the note shows only the sigmoid colon came out, H1000 is the code to check instead.
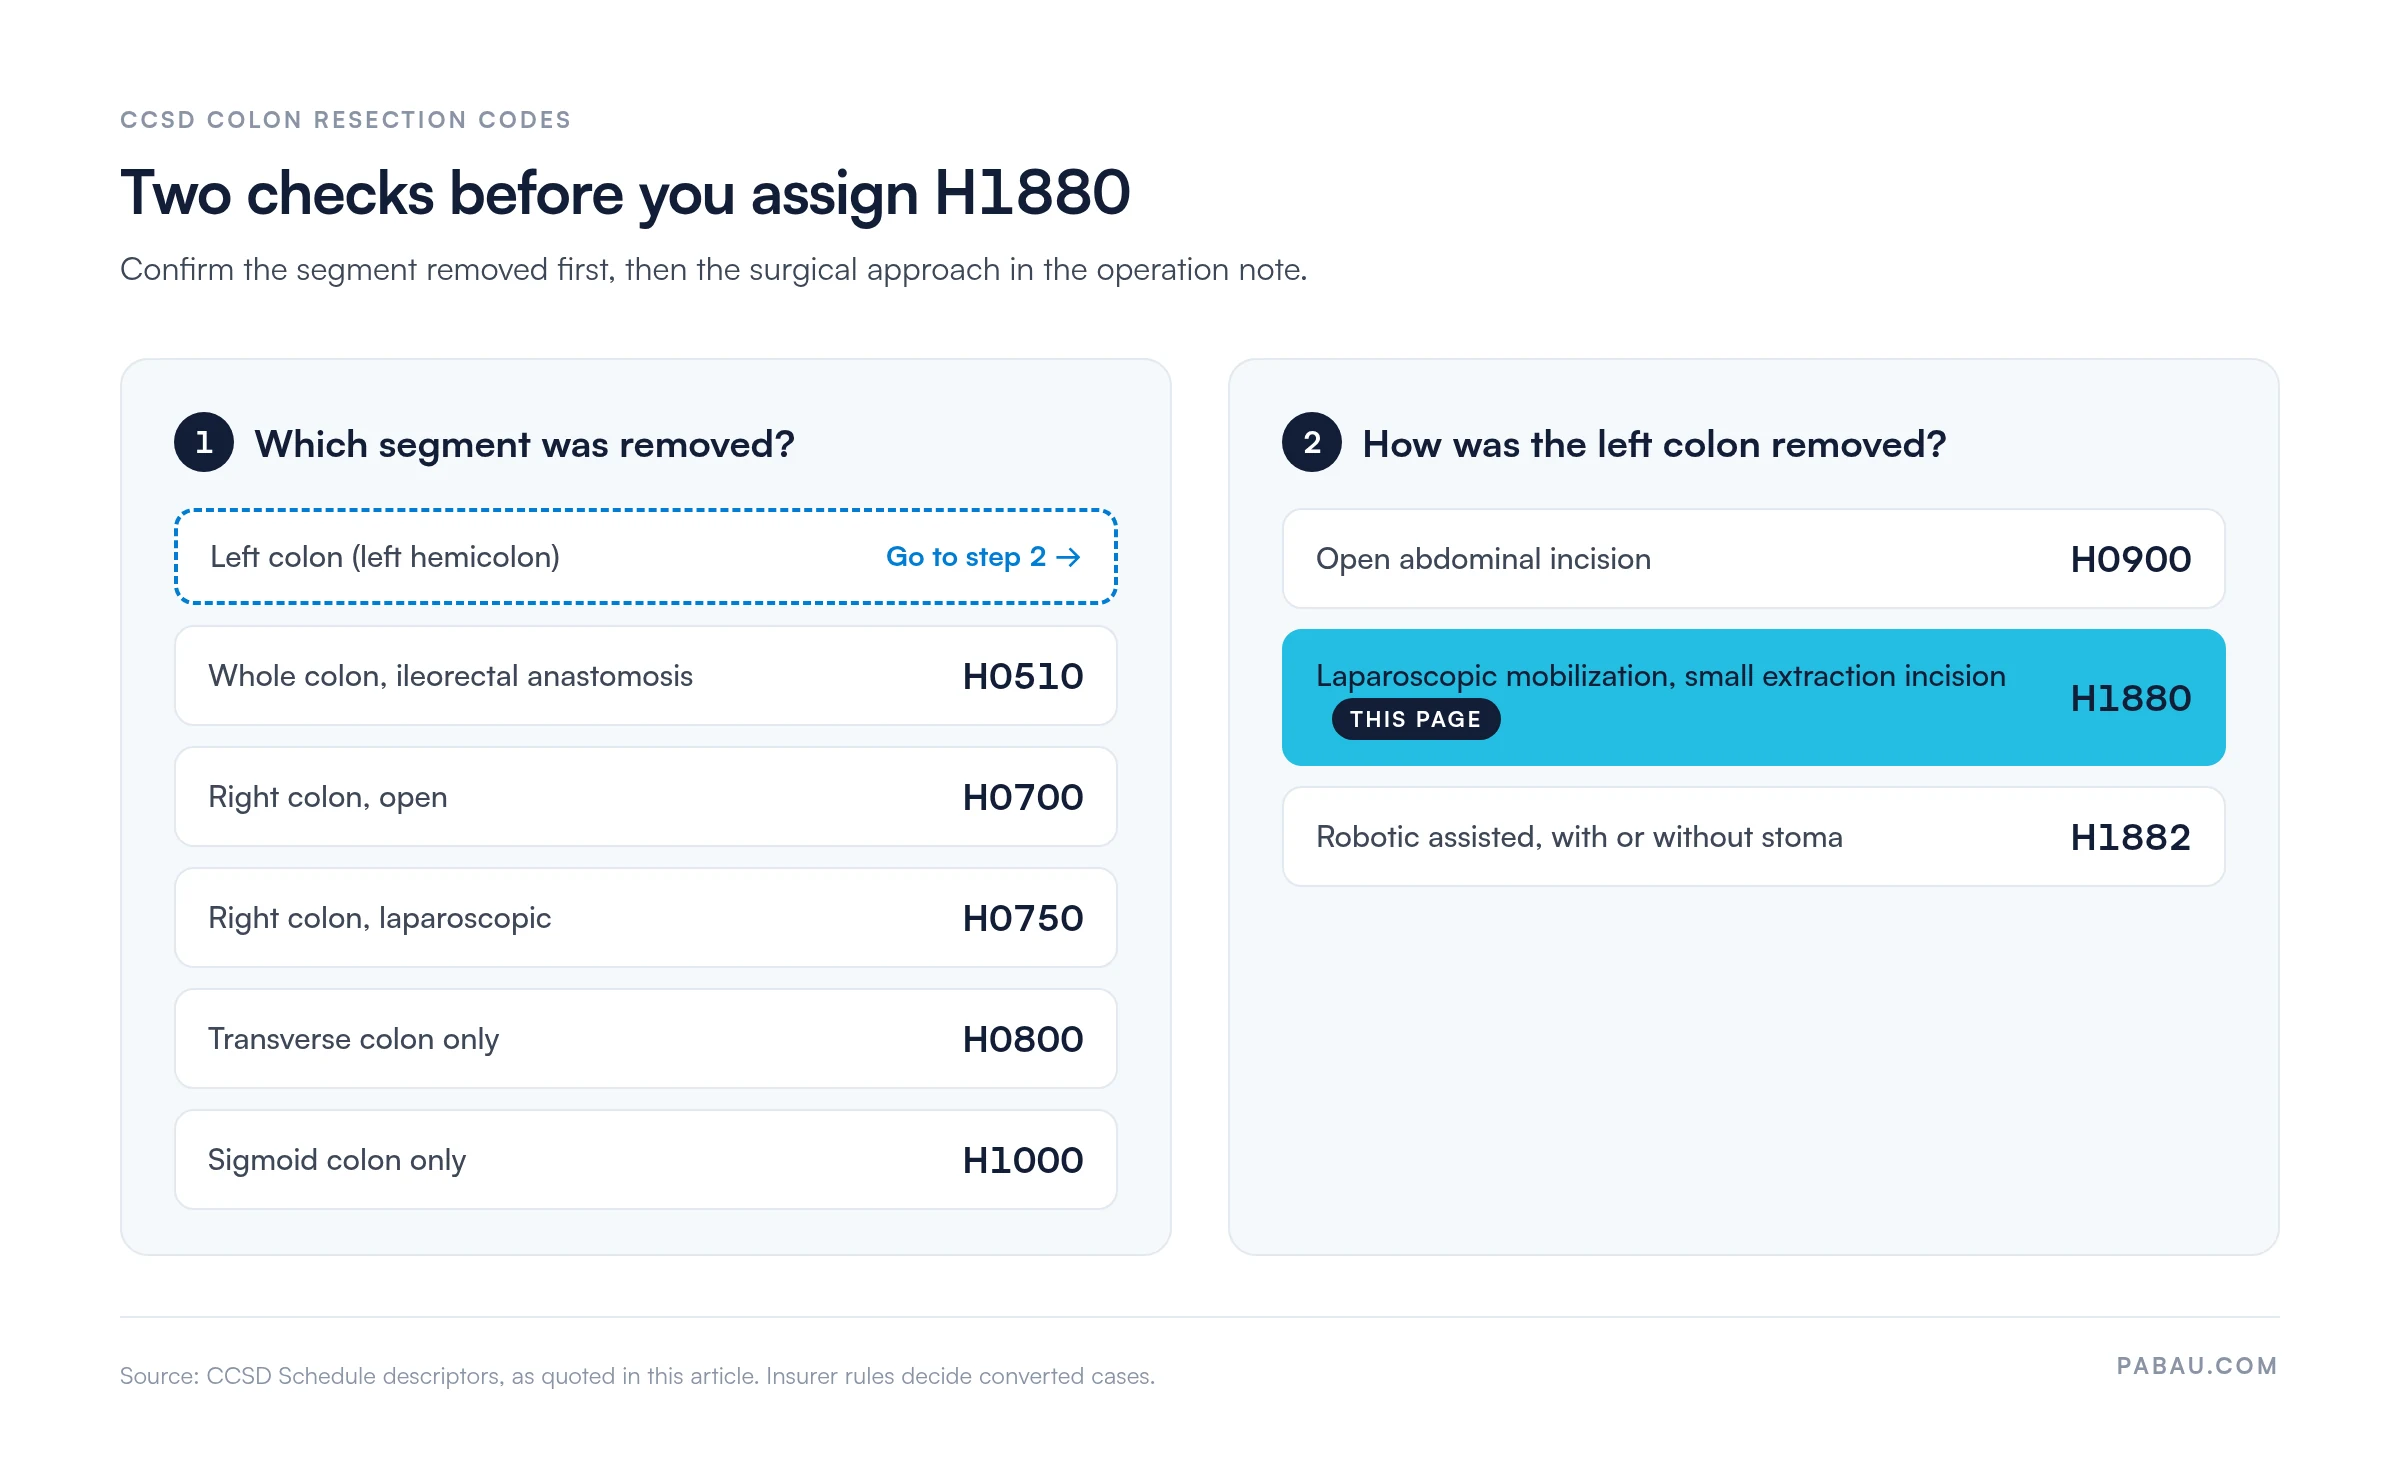
Before you assign H1880, confirm two points in the operation note. First, the left colon and splenic flexure were mobilized laparoscopically. Second, the note states how the specimen was removed and the anastomosis formed.
H1880 fits pathology in the left colon, from the splenic flexure through the descending colon to the sigmoid. Insurers ask for the diagnosis at pre-authorization, and the ICD-10 code should match the segment removed.
The WHO ICD-10 browser gives the official description for each code. For cancer cases, include the staging in the pre-authorization request. A diagnosis that points elsewhere in the colon, such as C18.3 for the hepatic flexure, does not support H1880.
Insurers can ask for clinical records before they pay a surgical claim. Keep this set on file for every H1880 operation:
A missing operation note or authorization number causes avoidable delays. A short checklist for each code, part of everyday medical billing compliance, confirms both are on file before the claim goes out.
Patients with private medical insurance normally need their insurer’s authorization before planned treatment. A left colon resection is major elective surgery, so contact the insurer well before the operation date.
Insurers set their own rules, and those rules change. Confirm the current process with the patient’s insurer rather than relying on what applied last year. A typical request includes:
The insurer confirms what the policy covers and issues an authorization number. Check whether the consultant’s fee sits within the insurer’s fee schedule. Otherwise, tell the patient in writing about any shortfall they may have to pay.
H1880 describes the surgeon’s procedure. Other clinicians and the hospital invoice for their own part of the same admission.
Steps that are part of the resection, such as routine wound closure or washout, belong inside H1880. Adding a code for an incidental step that H1880 already includes invites an unbundling query.
H1880 rejections follow a predictable pattern, and most can be prevented before submission. Effective denial management in healthcare starts with knowing why claims fail.
Start with the cause on the rejection notice. An administrative error, such as a missing authorization number, usually needs a corrected claim rather than a complaint.
The Financial Ombudsman Service is free for consumers. Each insurer publishes its own complaints process, so follow the steps on its website.
Paperwork for a colon resection often ends up in several places. The operation note sits in one system, the invoice in another, and the claim is re-keyed for the insurer. Each hand-off risks a wrong approach code or a lost authorization number.
Pabau, our practice management and billing platform, keeps those steps in one place. Its claims management software sends private medical insurance claims through Healthcode to insurers such as Bupa, AXA Health and Vitality. Pabau stores each pre-authorization as a case linked to the appointment.
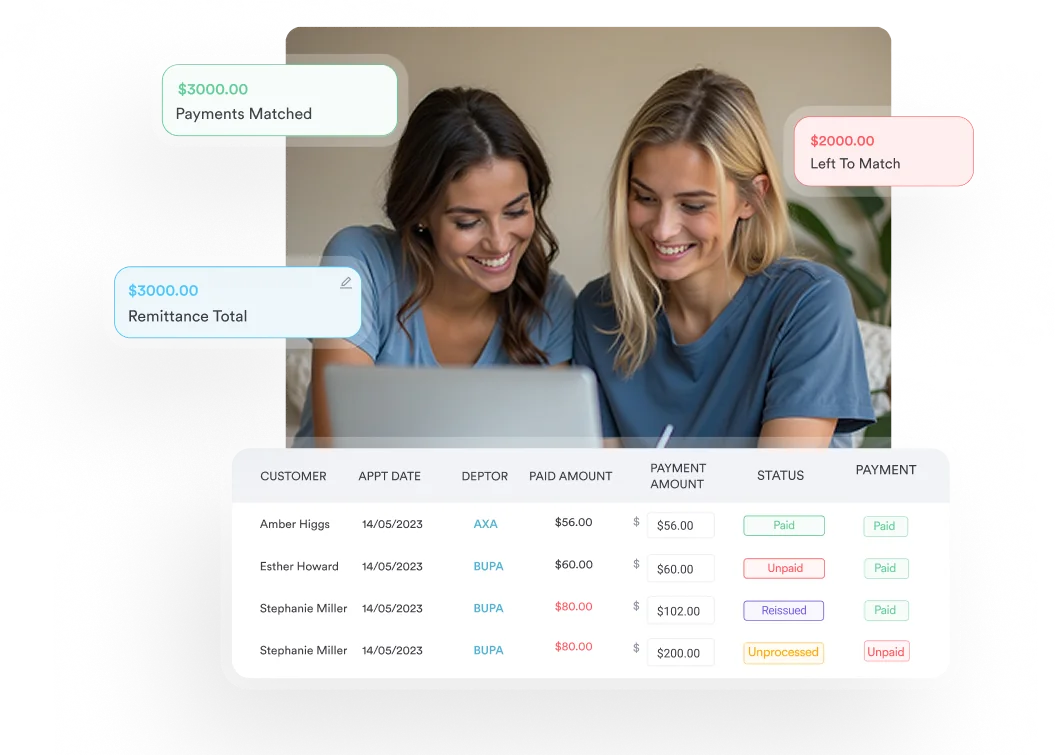
Your team still chooses the code, and Pabau checks the claim for missing or invalid details before it is sent. The operation note, consent form and histology report sit on the same patient record. The claims dashboard then tracks each H1880 claim from Pending to Paid.

Pabau sends private medical insurance claims through Healthcode, stores each pre-authorization as a case, and shows every claim from Pending to Paid.

Code H1880 only when the left colon was resected with laparoscopic assistance. An open operation goes on H0900 and a robotic-assisted one on H1882, so the operation note decides the code.
Before you submit, confirm three facts. The note states the approach, the authorization number is on the invoice, and the ICD-10 code matches the left colon. A short check costs less than a rejection and a resubmission.
To see how Pabau turns surgical invoices into Healthcode claims you can track, book a demo.

Looking for a structured CCSD code reference for private insurers? Pabau’s Bupa CCSD code guide explains how Bupa applies the CCSD Schedule.
Want to understand the CCSD Schedule as a whole? Pabau’s guide to CCSD codes covers how UK private consultants use them.
Managing billing compliance across a surgical practice? Medical billing compliance covers the documentation and process controls that reduce rejections.
Was only the sigmoid colon removed? CCSD code H1000 covers excision of the sigmoid colon on its own.
Billing the colonoscopy that came before surgery? CCSD code H2002 explains how to bill a diagnostic colonoscopy.
CCSD code H1880 covers a laparoscopically assisted left colon resection. The surgeon mobilizes the left colon laparoscopically and usually removes it through a small incision. The open operation is coded H0900 instead.
H1880 covers the left colon, including the descending colon and splenic flexure. Right hemicolectomy is coded H0700, and its laparoscopic version is H0750. The anatomy and blood supply differ, so the codes are not interchangeable.
Patients normally need their insurer’s authorization before planned private treatment, and a left colon resection is major elective surgery. Each insurer sets its own process, so confirm it with the patient’s insurer before the operation.
H0900, excision of left hemicolon, is the open operation on the same segment. H1882 is the robotic-assisted version. H1000 covers excision of the sigmoid colon alone, so check the anatomy in the operation note.
Yes. H1880 covers the surgeon’s procedure, and the anesthetist invoices the insurer for their own fee. Whether an insurer pays a separate assistant fee depends on its rules, so check before the operation.
The usual causes are a missing authorization number and a code that does not match the recorded approach or segment. A mismatched ICD-10 code, unbundled steps and policy limits cause rejections too. A checklist before submission prevents most of them.




