

ICD-10 code S61.201A: Open wound of left index finger without nail damage
ICD-10 code S61.201A covers a left index finger wound of unstated type ICD-10 co...

Last Updated: Oct 16, 2026
Billable Code Specific Code
S52.233F is the billable ICD-10-CM code for displaced oblique fracture of shaft of unspecified ulna, subsequent encounter for open fracture type IIIA, IIIB, or IIIC with routine healing.
That grade is the part billers get wrong. Coders reach for E, which covers milder type I and II wounds, and the claim stops matching the trauma record.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

ICD-10 code S52.233F describes a displaced oblique fracture of the shaft of an unspecified ulna. The bone is the ulna, not the radius.
The 7th character F means a subsequent encounter for an open type IIIA, IIIB, or IIIC fracture with routine healing. Type I and II wounds take E instead.
The 6th character 3 carries both displacement and laterality. It means displaced, side not documented, so S52.231- and S52.232- are the right and left options.
Radial shaft fractures sit in a separate family at S52.3-. Picking the wrong bone puts the claim at odds with the operative report.
Practice management software like Pabau seeds the diagnosis into the claim form from the record, then submits it through Claim.MD in the US.
According to the CDC/NCHS ICD-10-CM web tool, S52.233F is a valid, billable code.
The official description spells out every element. Displaced oblique fracture of shaft of unspecified ulna, subsequent encounter for open fracture type IIIA, IIIB, or IIIC with routine healing.
Two details in that descriptor do most of the work. The fracture is oblique and displaced, in an ulna whose side was never documented. The wound was also graded Gustilo type III, above the milder type I and type II range. Each of those facts lives in its own character position.
Read the code from left to right and it travels from body region to wound grade in seven steps. Misreading any one position produces an invalid or incorrect code.
Here is what each position encodes.
Within S52.2, the 5th character names the shape of the break. A 3 means oblique, so the fracture line runs at an angle across the shaft. The neighboring values cover the other patterns a radiologist might describe.
This is the position coders underestimate. In S52.23, one digit encodes displacement and laterality at the same time. Change the side and you also change the digit that proves displacement.
An unspecified-side code is legitimate when the record genuinely never names an arm. It is not a shortcut for a chart that says “left forearm” in the operative note.
The 7th character is where most coding errors for ICD-10 code S52.233F occur. Character F does not simply mean “follow-up visit.” According to CMS ICD-10-CM guidelines, F designates a subsequent encounter for an open fracture graded Gustilo type IIIA, IIIB, or IIIC. The wound must be healing without complication.
The S52 category runs a full 7th character table, and it moves on two axes at once. One axis is the healing status. The other is the severity of the open wound. The grid below shows where every letter lands.
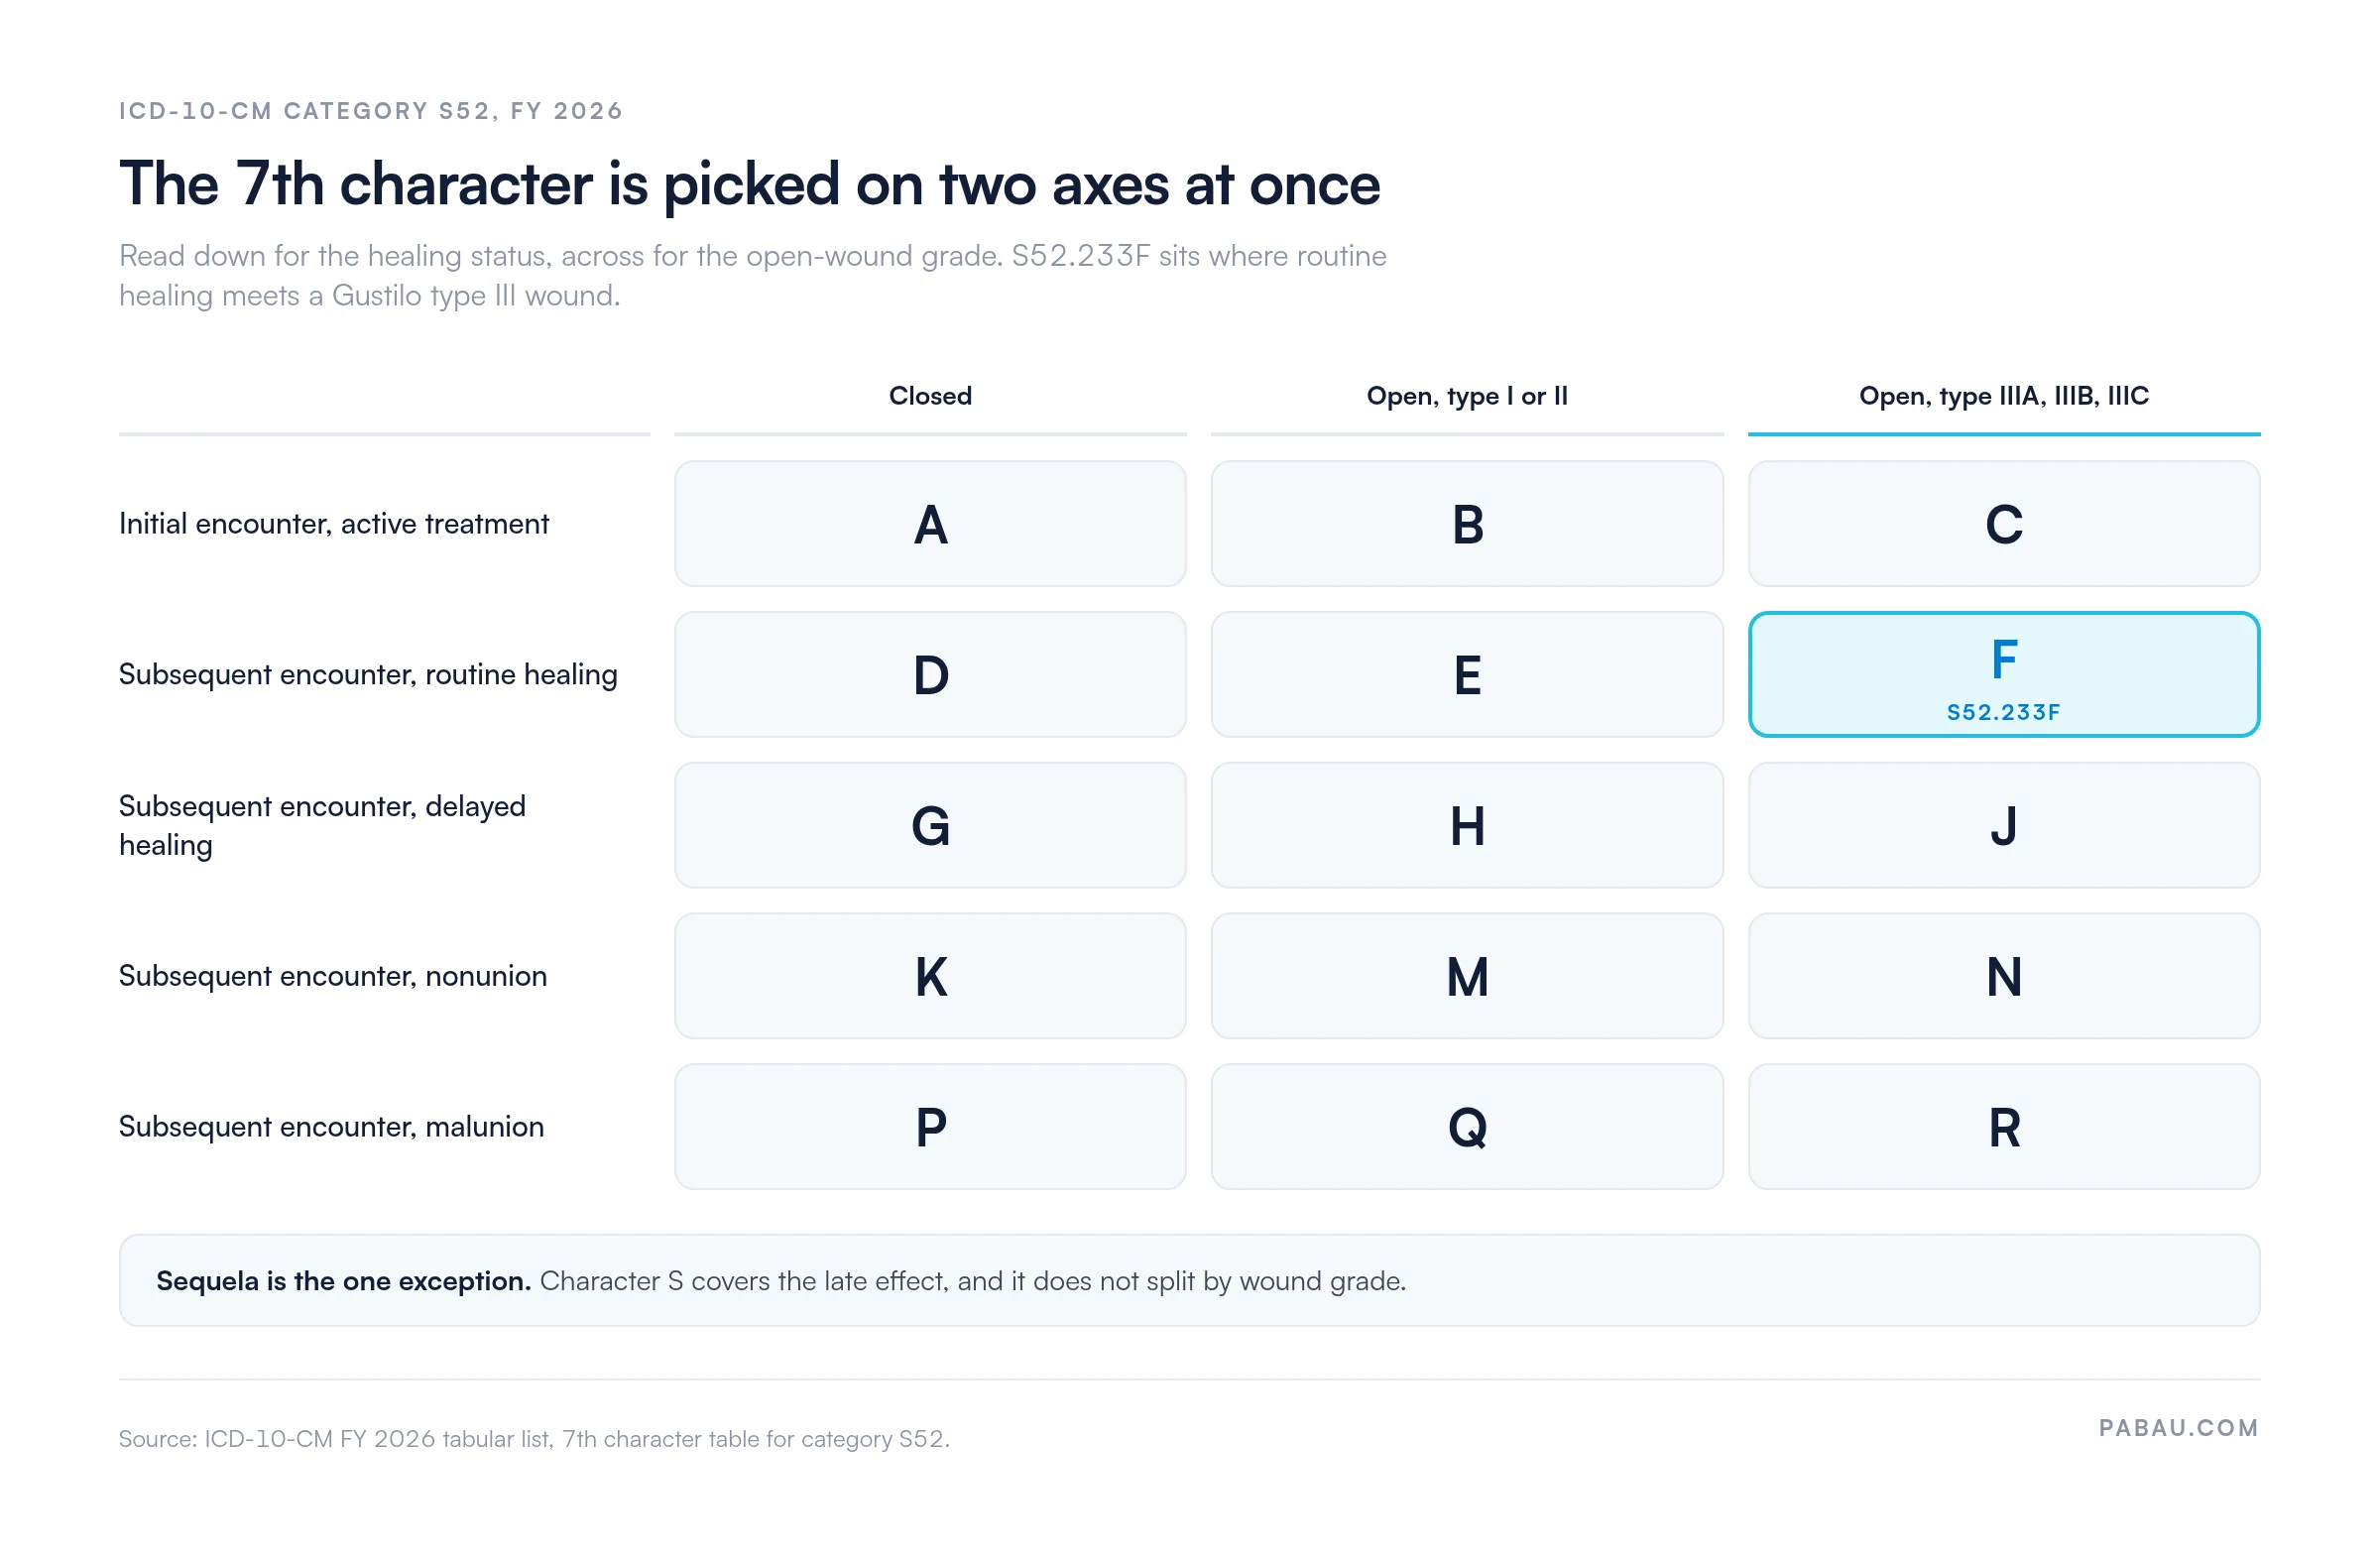
The tabular list spells out the same 16 options one letter at a time.
Character F versus character E. Both describe a subsequent encounter with routine healing. The only difference is the Gustilo grade recorded at the initial encounter. E covers type I and type II wounds. F covers type IIIA, IIIB, and IIIC. Verify the grade in the original emergency or operative note before you pick between them.
ICD-10 code S52.233F covers one narrow clinical scenario. Every condition below has to be present at the same time for the code to be appropriate.
A type III ulnar shaft fracture usually arrives through trauma surgery and then moves into orthopedic follow-up. Wound care and rehabilitation run for months afterward, so this code turns up repeatedly on the same patient.
Copy the Gustilo grade out of the original operative note and into the problem list the day the patient transfers into follow-up care. Payers auditing fracture claims look for agreement between the initial encounter code and the 7th character used later. When the grade only lives in a scanned trauma record, coders default to the milder letter and the claim stops matching the chart.
A patient reaches the emergency department with an open forearm injury after a motorcycle crash. The trauma surgeon documents a displaced oblique fracture of the ulnar shaft. The wound is graded Gustilo type IIIB. That encounter codes to S52.233C.
Six weeks later the patient turns up at an orthopedic office working from outside trauma records. Imaging shows callus forming, and the wound is closing without infection. No note in the file names the injured arm. That visit codes to S52.233F, and a note saying left would have made it S52.232F.
If the left-arm wound had been graded type I or II instead, the visit would code to ICD-10 code S52.232E.
S52.233F sits inside the S52.23 subcategory. Seeing the neighbors side by side makes it easier to pick correctly when the side, the pattern, or the healing status is different.
The last row is the one worth bookmarking. S52.233F and S52.333F differ by a single digit, yet they describe fractures in two different bones. Confirm the subcategory against the current fiscal year tabular list in the AAPC Codify ICD-10-CM lookup before you submit.
S52.233F is a valid, billable ICD-10-CM code for HIPAA-covered transactions. Payment, though, depends on a record that supports every element of the code. Thin documentation is the main reason payers deny or downcode fracture follow-up claims.
The path from note to payment has five stops. A fracture claim can stall at any of them, and two of them cause most of the trouble.
Step one fails when the Gustilo grade sits in a scanned outside record that nobody opens. Step three fails when the claim still carries an initial encounter character months after active treatment ended. Both are cheap to catch internally and expensive to fix after a denial.
ICD-10 code S52.233F is a diagnosis code, so it needs a CPT procedure code on the claim line. Which one belongs there depends on the service delivered that day.
Note the imaging row. CPT 73100 covers the wrist, which is the wrong region for a shaft fracture, so forearm views under 73090 are the anatomically correct pairing. Wound care also keeps running alongside the fracture, so CPT 97597 shows up on many of these follow-up claims.
Global periods matter here too. Surgical fracture codes such as 25545 carry a 90-day global period, so routine follow-up visits inside that window are usually not separately payable. Check the payer’s local and national coverage determinations, because rules on fracture aftercare vary by contract.
Those determinations can outrank the diagnosis. Under LCD L33370, compounded inhalation solutions billed as HCPCS code J7604 are denied against every ICD-10 code, so a sharper diagnosis cannot rescue them.
Forearm fracture codes generate more errors than most coders expect. Two bones, six pattern options, and sixteen 7th characters all intersect in one category.
These are the errors that show up most often in audits and denial reviews.
This is the error that costs the most. S52.2- is the shaft of the ulna and S52.3- is the shaft of the radius, and the two families mirror each other digit for digit. S52.233F and S52.333F look almost identical in a code list. Read the bone name in the descriptor before you copy a code across.
Both letters mean a subsequent encounter with routine healing for an open fracture. The difference is the Gustilo grade. E is for type I and type II wounds, and F is for the type III wounds that involve extensive soft-tissue damage. Coding F on a type II injury overstates severity, and coding E on a type III understates it.
S52.233- exists for records that never say which arm was injured. The ICD-10-CM Official Guidelines still expect coding to the highest level of specificity available. Payers increasingly treat unspecified laterality as a quality flag, so query the provider rather than defaulting to the unspecified digit.
Character A applies only to the encounter where active treatment happens for the first time. Every later visit, including therapy check-ins and healing assessments, needs a subsequent encounter character. Submitting A again after the initial treatment has already been billed reads as a duplicate encounter.
If the provider documents delayed healing, nonunion, or malunion, the 7th character has to move with it. For a type III open ulnar shaft fracture, that means J, N, or R instead of F at follow-up. Always code what this visit documents, not what the last visit documented.
Build a forearm fracture audit into the quarterly billing review. Pull every claim carrying an S52.2- or S52.3- code. Check that the bone in the descriptor matches the operative report. Check that the 7th character matches the healing status documented that day. Then check the laterality digit against the chart. Catching these internally costs far less than answering a payer audit.
A type III ulnar shaft fracture generates claims for months. In most practices, someone retypes the diagnosis at every visit. That person also digs the Gustilo grade out of a scanned trauma record and rekeys it into the claim form. Each retype is another chance to land on the radius family or the wrong 7th character.
Practice management software like Pabau takes the retyping out. The claim form fills from the record. The CPT code attached to the service lands on the charge line, and the ICD-10 slots seed from the client’s recorded problem list. Built-in ICD-10-CM and CPT lookup libraries sit behind a search icon, so coders confirm a descriptor without leaving the claim.
Pabau’s approach to cleaner claims management is to check the required fields before the send button unlocks. US claims route through Claim.MD, our clearinghouse partner, for eligibility checks and claim status tracking.
When a payer pushes back, the denial codes that come back name the element that failed. Fixes then happen at the code level rather than through a blind resubmission.


Pabau fills the claim form from the record and keeps ICD-10-CM and CPT lookups a click away. US claims go out through Claim.MD, with eligibility checks and electronic remittance advice built in.

The letter at the end of S52.233F deserves more attention than the six characters in front of it. Those six come straight off the imaging report. The seventh depends on a grade recorded weeks earlier, by a different clinician, in a record the follow-up practice may never open.
Fixing that is a workflow job. Move the Gustilo grade into the problem list the day the patient transfers into follow-up care, and the 7th character stops being a guess.
Practices that keep the diagnosis attached to the record spend far less time answering payer questions about fracture claims. Book a demo to see how Pabau carries a fracture diagnosis from the first encounter through to the last follow-up claim.

Coding an open fracture outside the forearm? ICD-10 code S92.311B works through the same encounter and open-fracture logic on a displaced first metatarsal fracture.
Managing denials across a long run of follow-up visits? Denial management in healthcare explains how to build a review process that catches repeat coding errors before they become write-offs.
Wondering what a clearinghouse does with a claim before the payer sees it? How Claim.MD clearinghouse works walks through submission, tracking, and remittance for US practices.
Yes. Add a code from the V00 to Y99 range describing how the injury happened. An external cause code is never sequenced first. Federal reporting is not mandated, though many payers and state registries expect it.
No. The ICD-10-CM guidelines keep aftercare Z codes off injury follow-up. Report the acute fracture code with the 7th character for a subsequent encounter, which is exactly what S52.233F is.
There is no time limit. The 7th character follows the type of care, not the calendar. Once active treatment ends and the patient enters the healing phase, subsequent encounter characters apply for as long as that runs.
Yes. When fracture follow-up is the reason for the visit, S52.233F leads the claim. An external cause code, or a code for a coexisting condition also treated that day, is sequenced after it.
No. The 7th character already reports the open wound at the fracture site and its Gustilo grade. Adding a separate wound code for that site double-reports the same injury.



