









Gillet test: Procedure, interpretation, and reliability
A positive Gillet test means the PSIS fails to drop during hip flexion. Reliabil...

Last Updated: Sep 17, 2026

The cross arm test is an orthopedic provocation test for acromioclavicular (AC) joint pathology. You perform it by passively adducting the patient’s arm across the body at 90 degrees of shoulder flexion.
A peer-reviewed study published in PubMed Central reported 67% sensitivity in its own prospective series, tested against diagnostic injection. Earlier retrospective data from Chronopoulos et al., quoted in that paper, put sensitivity at 77% and overall accuracy at 79%.
For physical therapists, chiropractors, and sports medicine clinicians, technique is what separates an accurate provisional diagnosis from a missed AC joint injury. This guide covers how to perform the test and how to read the result. It also covers what the accuracy figures mean and where the test sits in a full shoulder assessment.

The cross arm test, also called the scarf test or cross body adduction test, compresses the AC joint through passive horizontal adduction.
A positive cross arm test is pain localized to the AC joint, so pain felt elsewhere does not count.
Published sensitivity runs from 67% to 77% depending on the study, so pair the test with the O’Brien or Paxinos test.
Pabau’s patient record software helps physical therapy and sports medicine practices document shoulder assessments, SOAP notes, and follow-up findings in one place.
The cross arm test is a passive orthopedic provocation test that compresses the acromioclavicular joint to reproduce pain arising from AC joint pathology. It is one of the most widely used AC joint special tests in shoulder examination.
The test is known by several names in clinical literature. All refer to the same technique:
The anatomical rationale is straightforward. Horizontal adduction at 90 degrees of shoulder flexion approximates the clavicle and acromion. That compresses the AC joint capsule, the meniscoid disc, and the surrounding ligaments. When pathology is present, the compression reproduces the patient’s symptoms at the joint line.
The cross arm test assesses acromioclavicular joint pathology, not the rotator cuff, the glenohumeral joint, or the subacromial space. Clinicians use it to provoke symptoms in patients suspected of having one or more of the following conditions:
The anatomy explains why the test works. The AC joint holds a small intra-articular fibrocartilaginous disc that degenerates with age and repetitive loading. Passive horizontal adduction compresses that disc and the structures around it, so pain reproduced there points to the AC joint.
The cross arm test takes under 30 seconds to perform. It demands precise arm positioning and a controlled passive force. Rushing, or applying force at the wrong angle, accounts for most inaccurate findings.
Seat the patient upright on a treatment table or chair with their back supported. The arm being tested rests comfortably at their side, shoulder relaxed, elbow in full extension. Ask the patient to point to the area of pain before you begin. That establishes a baseline, so you can confirm whether the pain reproduced during the test sits at the AC joint.
The patient should hold a neutral cervical spine position. Cervical pathology can refer pain to the shoulder girdle, and a neutral neck reduces the risk of confounding symptoms during the test.
Stand on the ipsilateral (same) side as the shoulder being tested. Use one hand to stabilize the shoulder girdle at the acromion and superior trapezius, which prevents compensatory scapular movement during adduction. The other hand cups the patient’s elbow or distal humerus.
Raise the patient’s arm passively to 90 degrees of shoulder flexion, with the elbow in extension. From there, apply a steady, controlled passive adduction force. Move the arm horizontally across the midline of the body toward the opposite shoulder.
The endpoint is either the onset of concordant pain at the AC joint or the natural end of passive range. That is typically around 90 degrees of horizontal adduction. Do not force through resistance or pain.
Maintain stabilization of the shoulder throughout. If the stabilizing hand lets go, the scapula protracts, which offloads the AC joint and can produce a false negative.
A positive cross arm test is pain reproduced at the AC joint during passive horizontal adduction. The patient localizes it to the joint line at the top of the shoulder, where the clavicle meets the acromion. Concordant pain reproduction there is what makes the finding clinically meaningful.
Pain elsewhere does not count as a positive AC joint finding. Clinicians working in chiropractic software or physical therapy platforms record this distinction in SOAP notes, so the clinical record leaves no ambiguity. Three scenarios to distinguish:
End-range stiffness and crepitus are worth noting, though they are secondary findings. The primary interpretive criterion is always where the reproduced pain sits.
Always ask the patient to point with one finger to where they feel the pain during the test, rather than asking a yes/no question. Patients often report generalized shoulder pain when the sensation sits at the AC joint. Specific localization changes the clinical interpretation completely.
The cross arm test has moderate diagnostic accuracy for AC joint pathology, and the numbers you see quoted come from two different datasets. A study indexed on PubMed Central compared several AC joint provocation tests against diagnostic injection as the reference standard.
That paper’s own prospective series reported 67% sensitivity for the cross arm test. It also quotes earlier retrospective data from Chronopoulos et al., which reported 77% sensitivity and 79% overall accuracy. The 79% figure describes overall accuracy. No specificity value was published for the test in either dataset.
No single shoulder special test is accurate enough to confirm or exclude AC joint pathology on its own. The cross arm test works as a screening and provocation tool. A positive finding raises suspicion, and a negative finding lowers it. Clinical decisions should still draw on patient history, palpation findings, and imaging where indicated.
Figures also vary across study populations. Both datasets describe AC joint arthritis confirmed by diagnostic injection. Accuracy for AC joint sprains or distal clavicular osteolysis may well differ.
A positive-looking cross arm test does not confirm AC joint pathology on its own. Several other conditions produce shoulder pain during passive horizontal adduction. Telling them apart takes careful pain localization and supplementary testing.
The practical rule is to ask the patient to point with one finger to exactly where the pain sits. AC joint pain sits squarely at the joint line, usually described as sharp or pinching at the top of the shoulder. Pain radiating down the arm, across the chest, or into the neck is unlikely to be AC joint pathology and warrants further investigation.
No single test gives enough diagnostic confidence for AC joint assessment. The cross arm test earns its place inside a broader shoulder special test cluster, where each test adds to the diagnostic probability.
The Journal of Orthopaedic and Sports Physical Therapy consistently supports multi-test approaches over single-test interpretation in shoulder examination.
Tests commonly used alongside the cross arm test:
The AC joint cluster does not stop at this test. The AC resisted extension test template gives you a recording sheet for the confirmatory test that usually follows it.
Sports medicine practices running sports medicine software can attach cluster results directly to a patient’s rehabilitation record, tracking findings across serial assessments.
Knowing what the test does and knowing when to reach for it are two different skills, and the second one rarely gets taught after graduation. The sequence below places the cross arm test inside a full shoulder examination, so you can see what has to happen before it.
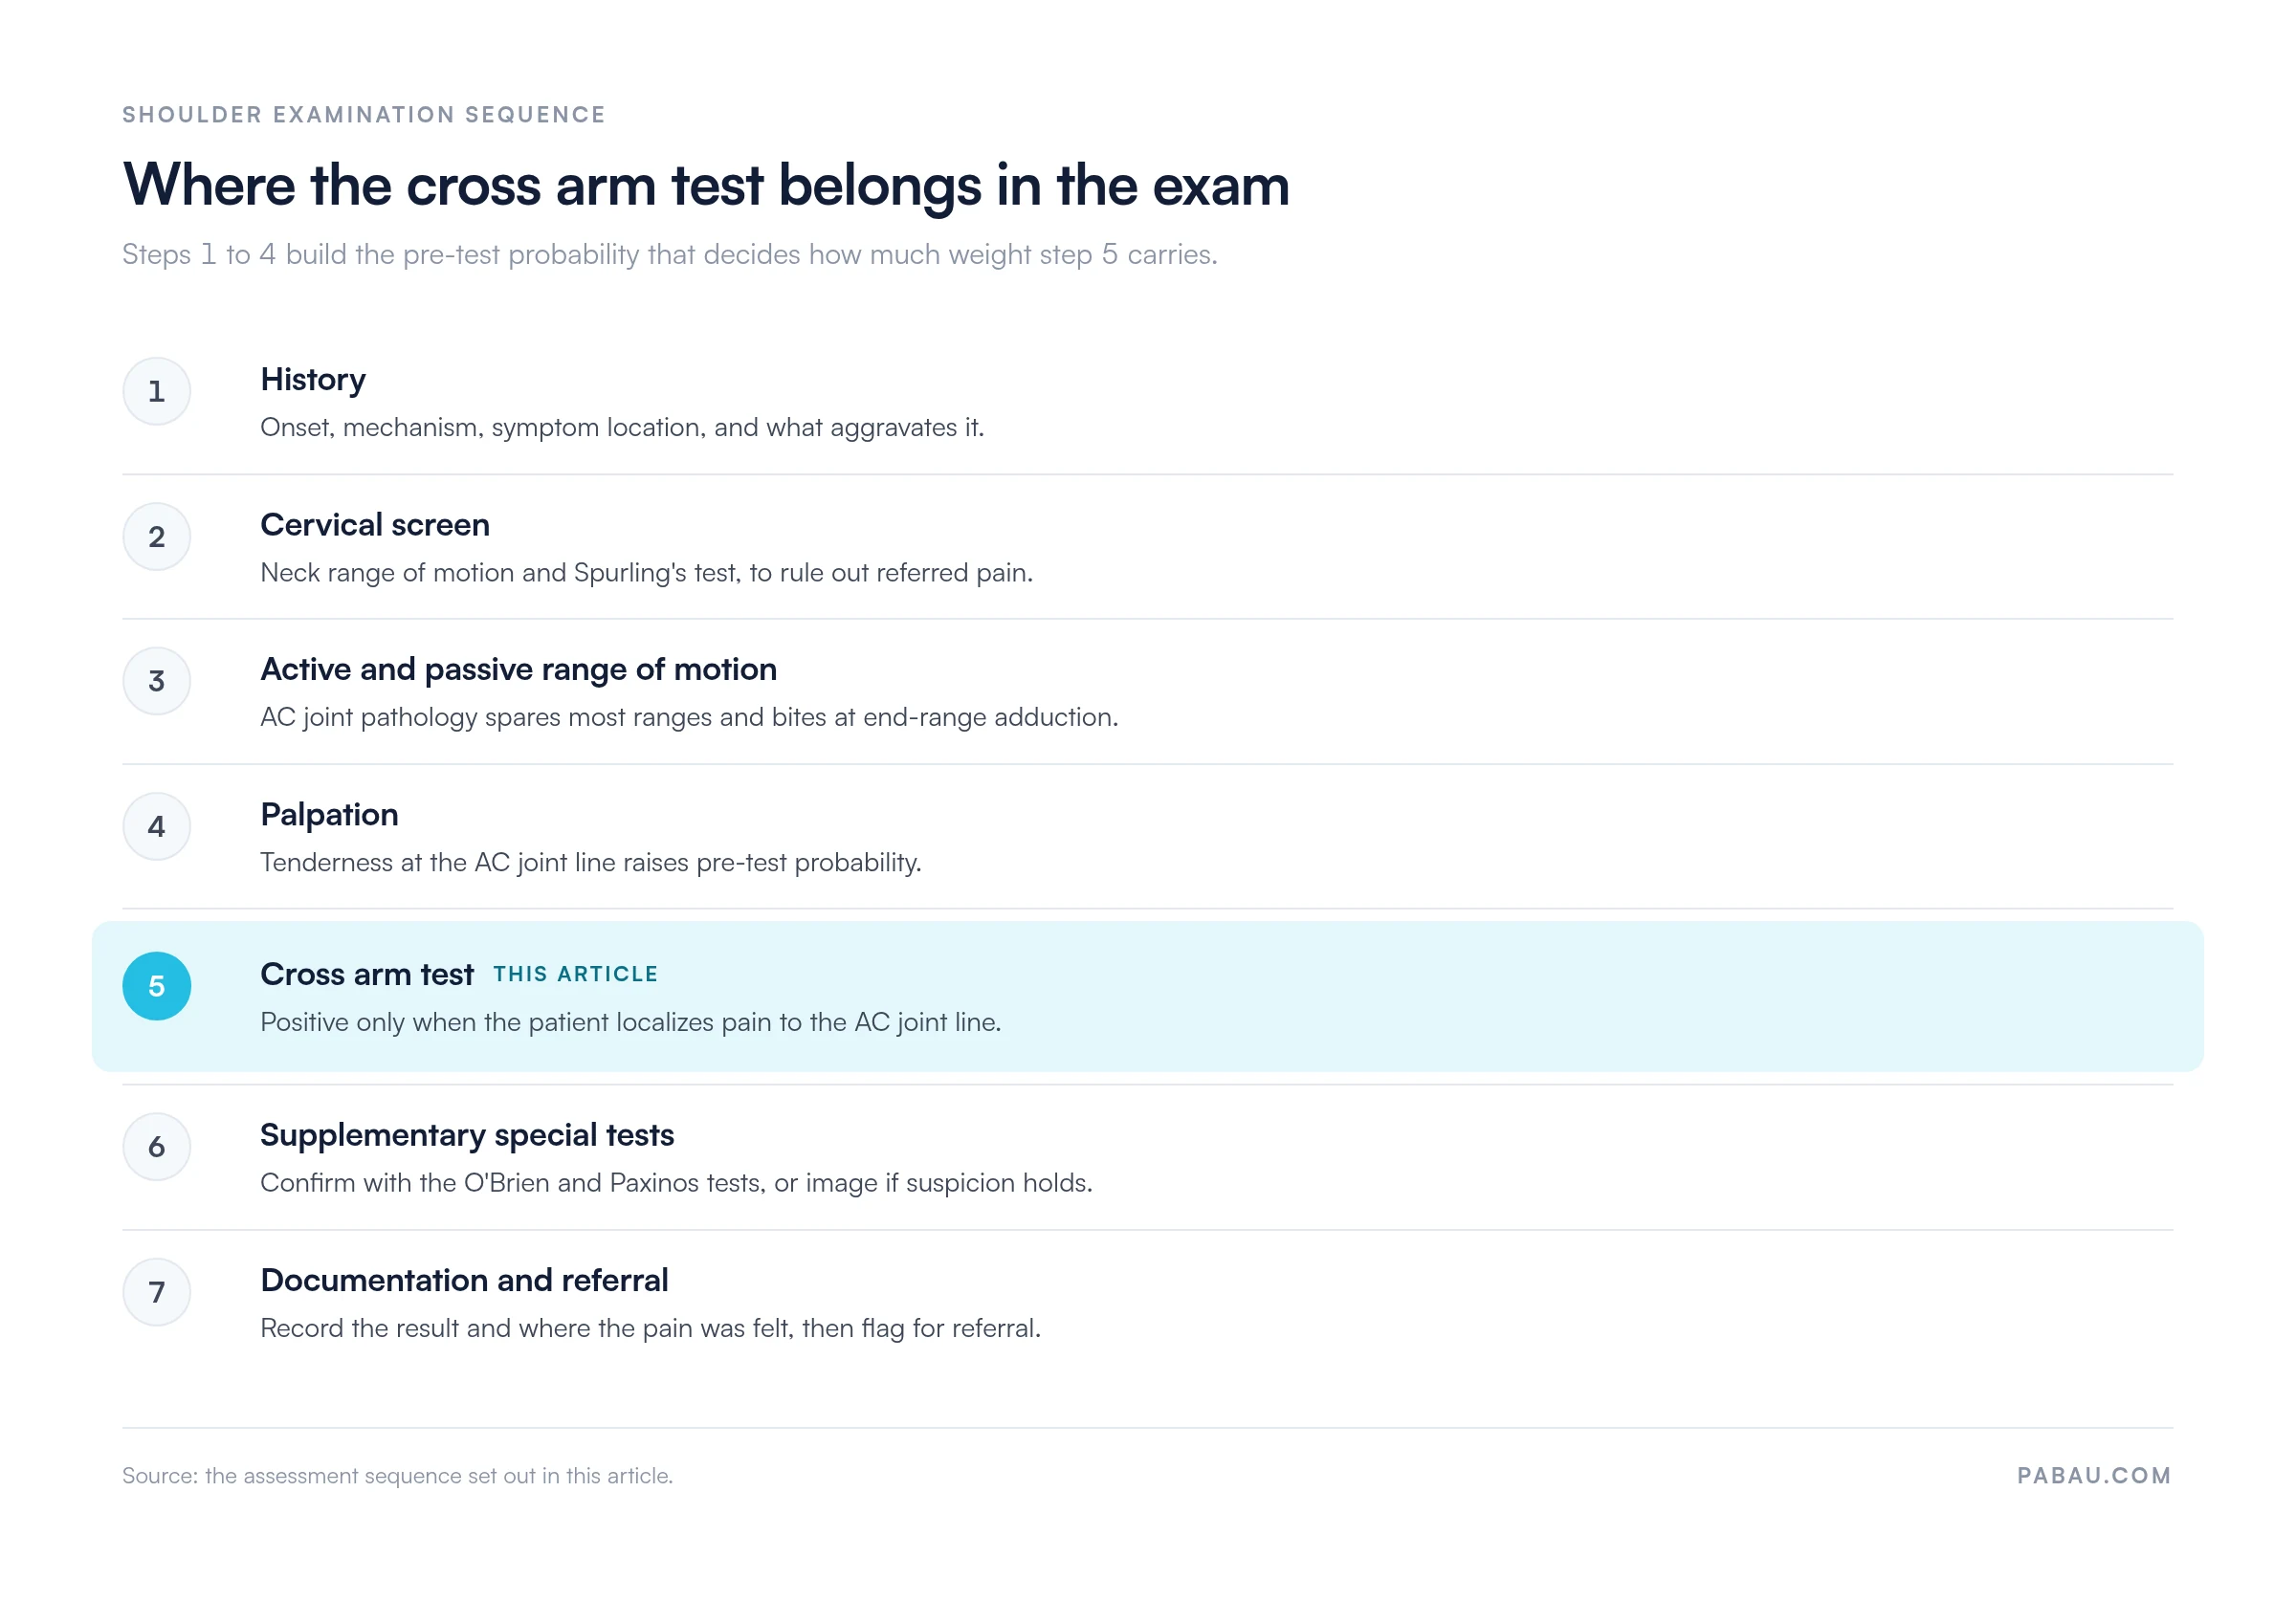
Practices seeing higher volumes of musculoskeletal patients benefit from structured assessment forms. A form that prompts each stage in this sequence lowers the risk of skipping a step under time pressure.
The cross arm test looks simple. In practice, five technique errors account for most inaccurate results, and clinicians rarely get direct feedback on them once they have graduated.
For documentation, record whether the test was positive or negative and where the patient localized the pain. Capturing the patient’s own words about the provocation matters if they are referred on, or if the findings are reviewed months later.
Practices working to physiotherapy compliance requirements will find that detailed test documentation supports audit readiness and professional indemnity records. Digital clinical forms can prompt specific fields for provocation test findings, which cuts documentation time and improves completeness.
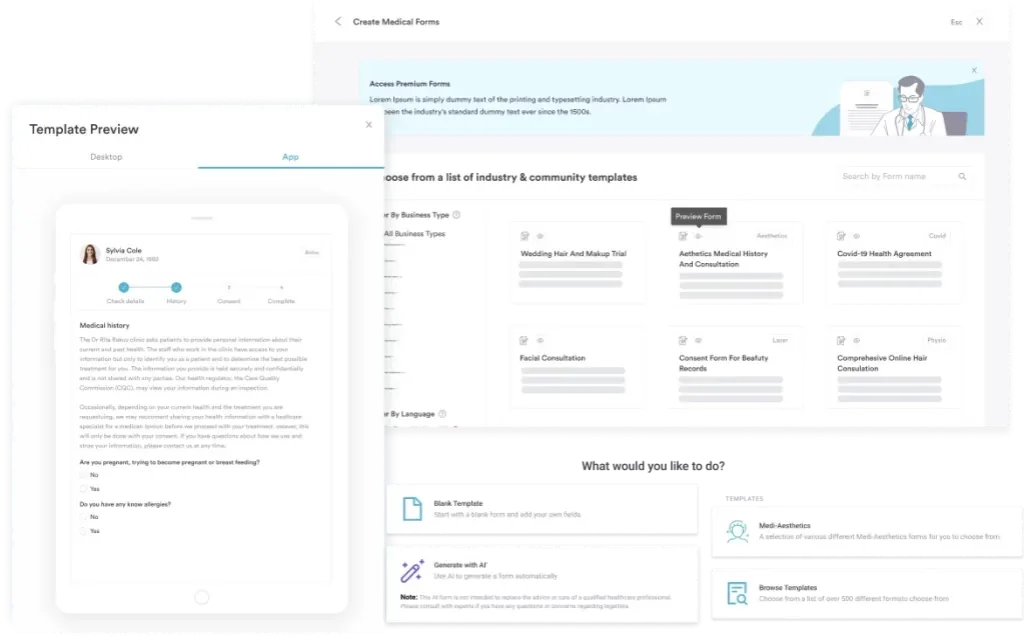
Build a short AC joint test cluster into a saved assessment template: Cross arm test, O’Brien test, Paxinos test. Running all three takes under two minutes and gives you a combined diagnostic picture rather than one isolated result. Document each result with the patient’s exact pain localization.
Most practices record a provocation test twice. The clinician writes it on a paper assessment sheet during the appointment, then re-keys the result into the patient record afterward. The pain-location detail that decides the interpretation is usually the part that drops out.
Practice management software like Pabau removes the second step. You build the shoulder assessment as a digital form, with its own fields for test result and pain localization. The completed form attaches straight to the patient record.
Serial assessments then sit side by side on one timeline. A six-week review shows what changed, rather than what someone remembered. Pabau GO, our iOS app, lets you complete the form at the treatment table instead of at the front desk an hour later.
You end up with a record that holds up under audit, under referral, and under an indemnity review. It costs the clinician no extra admin at the end of the day.
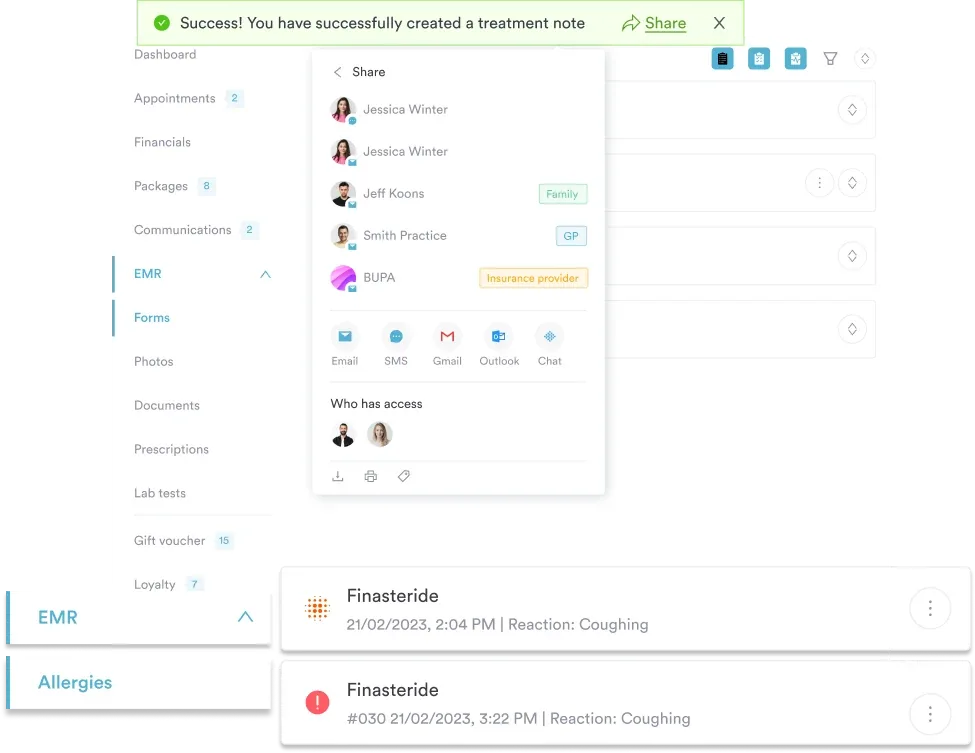

Pabau gives physical therapy and sports medicine practices digital assessment forms, structured SOAP notes, and serial findings in one patient record. See how it fits the way you already work.

The cross arm test earns its place as a first-line AC joint provocation test. That depends on performing it at 90 degrees, stabilizing the scapula, and insisting on pain localization. Reported sensitivity runs from 67% to 77% depending on the dataset, so treat it as a screening tool inside a cluster.
The trade-off worth remembering is that a negative result lowers probability without excluding the diagnosis. If the history and palpation still point at the AC joint, keep investigating rather than closing the question.
Assessment findings are only as useful as the record they land in. Pabau’s physical therapy EMR holds configurable shoulder assessment templates, structured SOAP notes, and digital consent forms in one platform.
Book a demo to see how your shoulder assessment findings get recorded once and stay findable months later.

Opening a new physical therapy practice? Opening a physiotherapy clinic covers the regulatory steps, equipment costs, and workflow setup you need from day one.
Building out your shoulder test cluster? Lift-off test walks through the subscapularis screen that pairs with the cross arm test in a complex shoulder presentation.
Managing a multi-clinician physical therapy team? Physiotherapy clinic management software explains the features that reduce admin overhead across shared patient records and scheduling.
The cross arm test assesses acromioclavicular (AC) joint pathology, including AC joint arthritis, post-traumatic osteolysis of the distal clavicle, AC joint sprains, and synovitis. It works by passively adducting the arm at 90 degrees of shoulder flexion, which compresses the AC joint and reproduces the patient’s symptoms. It does not assess the rotator cuff, glenohumeral joint, or subacromial space.
A positive cross arm test indicates pain reproduced specifically at the AC joint line during passive horizontal adduction. The patient has to localize the pain to the AC joint for the test to count as positive. Generalized shoulder pain, or pain at other sites during the test, does not indicate AC joint pathology.
Two figures circulate, and they come from different datasets. The prospective series in the most-cited PubMed Central paper reported 67% sensitivity against diagnostic injection. Earlier retrospective data from Chronopoulos et al., quoted in that same paper, reported 77% sensitivity and 79% overall accuracy. The 79% figure is overall accuracy, and no specificity value was published for the test. Either way the accuracy is moderate, so combine the test with the O’Brien and Paxinos tests.
The cross arm test uses pure passive horizontal adduction to compress the AC joint. The O’Brien test, or active compression test, holds the arm at 90 degrees of flexion and 10 to 15 degrees of horizontal adduction. The examiner then applies a downward force, first with the forearm pronated and then supinated. Both tests can provoke AC joint symptoms, but the O’Brien test also screens for SLAP labral lesions. Pain on top of the shoulder in the O’Brien test supports AC pathology, while pain deep in the shoulder suggests a labral source.
No. The cross arm test is not designed to assess the rotator cuff. It targets the AC joint through compression during horizontal adduction. Rotator cuff assessment needs separate tests: The empty can test for supraspinatus, the lift-off test for subscapularis, and the drop arm test for cuff integrity. If rotator cuff pathology is suspected alongside AC joint involvement, perform and document both clusters separately.
The patient sits upright with the arm resting at the side, shoulder relaxed, and elbow in full extension. The examiner raises the arm passively to 90 degrees of shoulder flexion. A steady passive horizontal adduction force is then applied across the body. The examiner’s other hand stabilizes the shoulder girdle at the acromion, which prevents scapular compensation during the movement.




