HCPCS code G0257: Unscheduled or emergency dialysis billing guide
HCPCS code G0257: Official descriptor and code overview HCPCS code G0257 is defi...

Last Updated: Oct 27, 2026
F2310 is the CCSD code for excision/destruction of lesion of tongue. It covers cutting out or destroying a lesion on the tongue, by scalpel, electrocautery, laser or cryotherapy. The code sits in Chapter 6 of the CCSD schedule, Face, Mouth, Salivary and Thyroid, under sub-chapter 6.5.0 Mouth cavity.
UK private insurers such as Bupa, AXA Health and Aviva use the schedule, but each sets its own fees and pre-authorization rules. CCSD lists F3810 and F4210 as unacceptable combinations with F2310, so neither is billed for the same lesion.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD code F2310 covers excision or destruction of a lesion of the tongue, in Chapter 6 of the CCSD schedule.
Excision produces a specimen for histology, while destruction ablates the lesion in place, so the note must say which method was used.
CCSD lists F3810 and F4210 as unacceptable combinations with F2310, so do not bill them for the same lesion.
Where the insurer asks for a diagnosis, use WHO ICD-10 codes such as K13.2 or D10.1, not US ICD-10-CM codes.
Each UK insurer sets its own pre-authorization rules and fees, so confirm cover with the patient’s insurer before the procedure.
CCSD code F2310 is the CCSD procedure code for excision/destruction of lesion of tongue.
It sits in Chapter 6 of the schedule, Face, Mouth, Salivary and Thyroid, under sub-chapter 6.5.0 Mouth cavity. You bill it when the clinician removes or ablates a pathological lesion on the tongue.
The descriptor covers two routes to the same outcome. The clinician either cuts the lesion out with a scalpel or destroys it in place. Destruction may use electrocautery, laser or cryotherapy. Both routes are billed as F2310, provided the lesion sits on the tongue.
The Clinical Coding and Schedule Development (CCSD) Group publishes the schedule used by UK private medical insurers. It sets the codes and their descriptors, while each insurer sets its own fees and rules. As a result, the same F2310 procedure can pay differently under Bupa, AXA Health, Aviva or VitalityHealth. The CCSD technical guide explains how the schedule is organized.
Descriptors can change between schedule releases. So before you bill, check the current entry in the insurer’s code search or your CCSD login.
Excision means removing the lesion surgically with a scalpel or similar instrument. It produces a tissue specimen that goes to a laboratory for histology. Destruction means ablating the lesion in place with electrocautery, laser energy or cryotherapy, so no specimen is produced.
Both methods sit under the same code, but the note has to say which one was used. Where excision was performed, the insurer may ask for the histology report during a query or clinical review. Requirements vary, so check the insurer’s guidance before you submit.
F2310 fits when a pathological lesion on the tongue needs removal or ablation. The most common indications fall into three groups: Benign lesions, premalignant lesions, and inflammatory or reactive lesions.
The clinical picture decides the method. Small, benign-looking lesions may suit laser or electrocautery ablation. Any lesion where malignancy cannot be ruled out clinically should be excised and sent for histology, not destroyed.
UK healthcare records diagnoses in the WHO edition of ICD-10. Where the insurer or claim form asks for a diagnosis, use a WHO ICD-10 code that matches the clinical note. US ICD-10-CM codes such as K13.21 and K13.29 do not exist in the WHO edition, so leave them off UK claims.
When the nature of the lesion is unclear before excision, code to the best clinical description available at the time. If the histology report changes the diagnosis, update the record and tell the insurer if the claim is still open.
F2310 fits a lesion on the tongue. Neighboring sites in the mouth have codes of their own, and a mismatch between note and code invites a query. Two questions settle the choice, as the chart below shows.
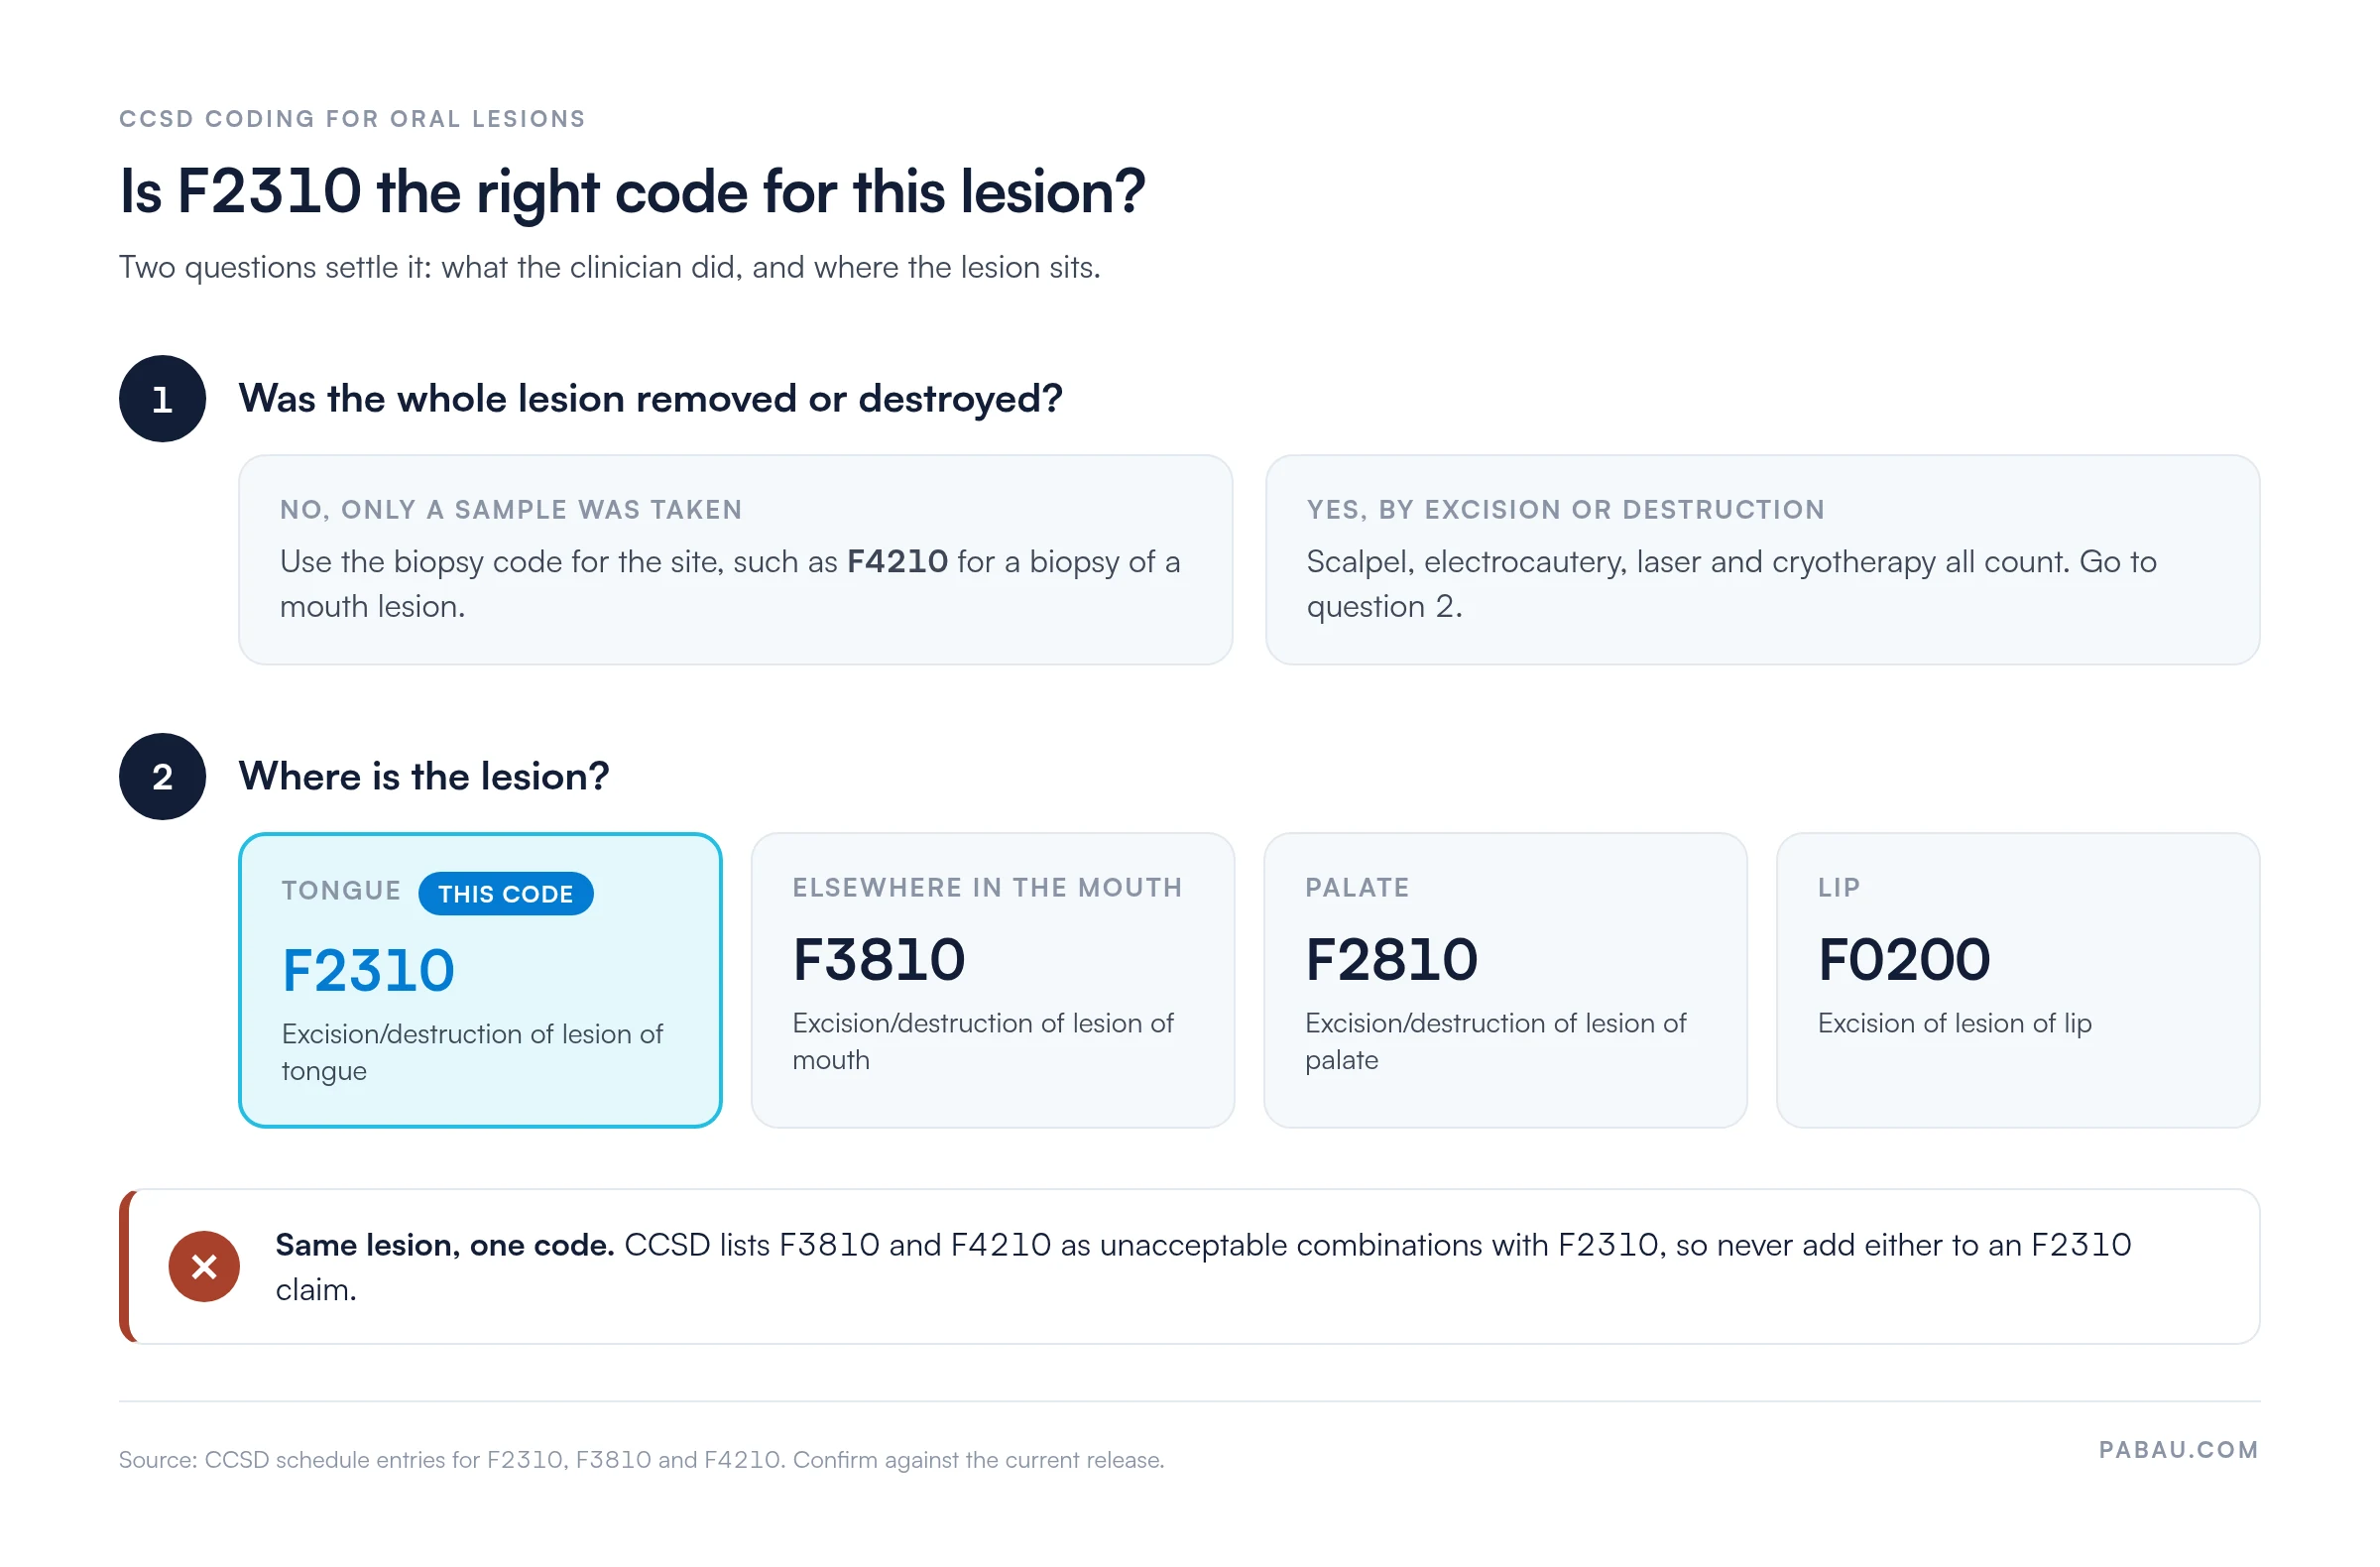
Work through these checks before you settle on F2310.
If the note leaves the site unclear, ask the clinician before you code. When none of these fit, browse our CCSD code library for a closer match.
Unbundling risk: CCSD lists F2310 as an unacceptable combination with F3810 and with F4210. In practice, do not add a mouth-lesion or mouth-biopsy code for the same lesion. When the plan from the start is complete removal, bill F2310 alone. CCSD principles are guidance, and each insurer decides whether to adopt them.
Insurers review records to check that the code matches the procedure performed. Thin notes are a common reason for queries and delayed payment. Digital clinical forms that capture these fields at the point of care keep the record complete.
The clinical record for every F2310 claim should include these elements:
The GMC and the GDC both expect clinical records to be clear, accurate and made at the time of care. That standard also protects the claim.
Keep a pre-populated note template for F2310 that prompts for all seven elements above. A missing anesthetic type or lesion size is enough for some insurers to query the claim, which can delay payment by weeks.
Pre-authorization is the insurer’s approval before treatment goes ahead. For surgical codes such as F2310, most UK insurers expect it. A claim without a required authorization is likely to be rejected, however sound the clinical case.
Requirements vary by insurer and by policy. The table below is a starting point only, so verify each case with the insurer.
When the insurer needs a pre-authorization request, include these details:
When in doubt, treat pre-authorization as required. A call before the procedure date costs far less than an appeal afterward. Our guide to Bupa CCSD codes covers that insurer’s process in more detail.
Some charges sit outside F2310 and may still be billed separately, while others overlap with it. Whether a combination pays depends on CCSD’s principles and the insurer’s own rules.
Most rejections trace back to a short list of avoidable errors. Each one below comes with its fix.
F2310 is performed by clinicians who treat oral lesions, such as oral and maxillofacial surgeons, ENT surgeons and dentists. In the UK, doctors register with the GMC and dentists with the GDC. Oral and maxillofacial surgeons usually hold both registrations.
Registration alone does not guarantee payment. Each insurer decides which clinicians it recognizes for which procedures, and that can vary by policy. Before billing, confirm these points:
Check the insurer’s provider portal or call provider services to confirm cover before you schedule the procedure. A five-minute check costs far less than a rejected claim.
Many practices still copy procedure details from the clinical note into a separate claim form. Each re-keyed field is another chance for the site, date or policy number to drift.
Pabau keeps the note, the invoice and the insurer claim on one patient record. Its claims management software pre-fills each claim with patient, treatment and insurer details. In the UK, claims then go to Healthcode electronically, without double entry.
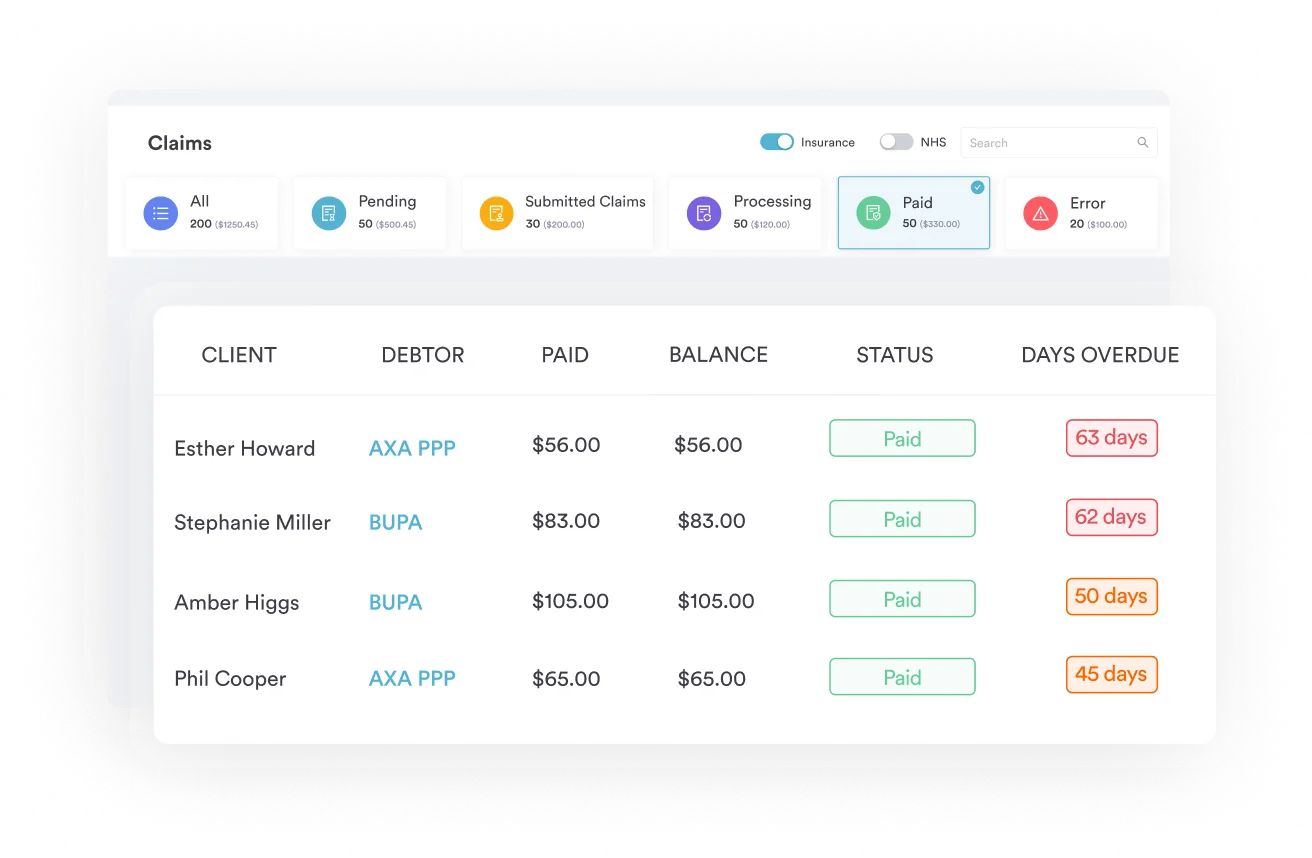
Before a claim is sent, background checks confirm that details such as membership numbers and authorization codes are filled in. So when an insurer queries an F2310 claim, your team can see where it stands and why.

Pabau pre-fills insurer claims from the patient record and submits them to Healthcode, so your team stops re-keying details. Validation checks flag missing membership numbers and authorization codes before a claim goes out.

Choosing F2310 is the easy part. The claim succeeds or fails on three details settled before billing: The site, the method and the authorization.
So build those checks into the booking and the procedure note, not the billing desk. A tongue lesion recorded clearly at the chair turns into a claim that needs no follow-up.
Book a demo to see how Pabau links the note, invoice and insurer claim, so your F2310 claims go out complete.

Billing Bupa patients for oral procedures? Bupa CCSD codes explains how Bupa uses the schedule and what it expects from providers.
Removing a lesion elsewhere in the mouth? CCSD code F3810: excision/destruction of lesion of mouth covers the neighboring mouth code.
Taking a sample before deciding on removal? CCSD code F4210: biopsy of lesion of mouth explains when the biopsy code applies.
Treating a lip lesion instead? CCSD code F0200: excision of lesion of lip covers the lip equivalent.
Looking for another CCSD code? The CCSD code library lists every CCSD code guide we publish.
CCSD Code F2310 covers the excision or destruction of a lesion of the tongue. That includes surgical removal and ablation by electrocautery, laser or cryotherapy. Use it when the aim is to remove or ablate the whole lesion, and only when the lesion sits on the tongue.
Excision removes the lesion surgically and sends a specimen for histology. Destruction ablates the lesion in place, so no specimen is produced. Both are billed under F2310, but the note must state which method was used.
Common WHO ICD-10 pairings include K13.2 for leukoplakia, including the tongue, and K13.7 for other lesions of oral mucosa. D10.1 covers a benign neoplasm of the tongue, and K14.0 covers glossitis. K13.4 covers granuloma of oral mucosa, and D37.0 a neoplasm of uncertain behavior in the oral cavity. Use the WHO edition, not US ICD-10-CM.
Not routinely. For excision, the specimen goes to the laboratory, and the insurer may ask for the histology report during a query or clinical review. For destruction, no specimen exists. Check the insurer’s guidance before you submit.
The most common causes are a missing pre-authorization or the wrong site code. Another is a blocked pairing, such as F3810 or F4210 billed for the same lesion. A thin note or a diagnosis that does not match the record can also cause rejections. Read the stated reason and fix that cause before resubmitting.
Clinicians who treat oral lesions, such as oral and maxillofacial surgeons and dentists, may bill F2310 if the insurer recognizes them. Each insurer sets its own recognition rules, which can vary by policy. Confirm recognition and cover with the insurer before the procedure.