ICD-10 Code S42.444P: Medial epicondyle fracture, right humerus
ICD-10 Code S42.444P: full descriptor and code validity ICD-10 Code S42.444P car...

Last Updated: Oct 13, 2026
Billable Code Specific Code
M45.7 is the billable ICD-10-CM code for ankylosing spondylitis of lumbosacral region.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

ICD-10 Code M45.7 describes ankylosing spondylitis of the lumbosacral region, a billable ICD-10-CM diagnosis code valid for FY2026.
M45.7 became effective October 1, 2025 and belongs to the M45 parent category covering ankylosing spondylitis by anatomical site.
Coders must specify the lumbosacral region explicitly in clinical documentation to justify M45.7 over unspecified code M45.9.
Pabau’s claims management software supports accurate diagnostic code entry, reducing claim errors for rheumatology and musculoskeletal practices.
The table below captures the key reference data for M45.7. Coders and billing staff can use this as a quick-check before claim submission.
Ankylosing spondylitis (AS) is a chronic inflammatory arthritis that primarily affects the spine and sacroiliac joints, causing progressive stiffness and, over time, vertebral fusion. The lumbosacral region encompasses the junction between the lumbar spine (L1-L5) and the sacrum, including the sacroiliac joints.
This is typically where AS begins clinically, making M45.7 one of the most commonly used AS subcodes in rheumatology and musculoskeletal billing.
AS is strongly associated with the HLA-B27 antigen, according to clinical guidance from the American College of Rheumatology (ACR) and the WHO ICD-10 classification. The condition typically presents in adults under 45 with insidious inflammatory back pain that improves with exercise and worsens with rest.
For coders, the critical point is that lumbosacral-region involvement must be explicitly stated in the clinical record.
The following terms appear in clinical notes and documentation and map to ICD-10 Code M45.7. Coders should recognize these synonyms to ensure correct code assignment when physician language varies.
Note that “axial spondyloarthritis” (axSpA) is the broader clinical umbrella that includes both radiographic AS (coded as M45) and non-radiographic axSpA. When the clinical record specifically confirms radiographic AS affecting the lumbosacral region, M45.7 is the appropriate code. Good clinical documentation practices should capture these distinctions at the point of care.
Recording these codes is quicker in osteopathy practice software that links diagnoses to treatment plans.
The includes and excludes notes at the M45 parent level apply to all subcodes, including M45.7. Misreading these notes is a common source of coding errors and claim denials. The CMS ICD-10 coding guidelines require coders to apply parent-level notes when assigning any subcode.
M45 is not itself a billable code. Payers require the site-specific subcode. The table below maps the complete M45 subcode set so coders can confirm the correct anatomical region before submission. Practices using claims management software can validate subcode specificity during the coding workflow rather than at the denial stage.

When a patient presents with AS involving both the lumbar region (M45.6) and lumbosacral region (M45.7), the lumbosacral code captures the more inclusive anatomical zone. Review the physician’s note for explicit regional language before selecting between adjacent subcodes.
Auditors reviewing AS claims look for three things: a confirmed diagnosis, a specified anatomical site, and supporting clinical evidence. Missing any one of these gives payers grounds to deny or downcode the claim.
Rheumatology practices apply this same specificity standard to other rheumatic diagnoses. Specificity at the point of care is always easier than querying physicians after the visit.
The checklist below reflects what must appear in the clinical record to support M45.7 during an audit or payer review.
Their documentation of functional limitations in the lumbosacral region can support the physician’s diagnosis code. Use digital intake and forms to standardize the capture of anatomical site and symptom history at every visit, reducing the back-and-forth of physician queries.
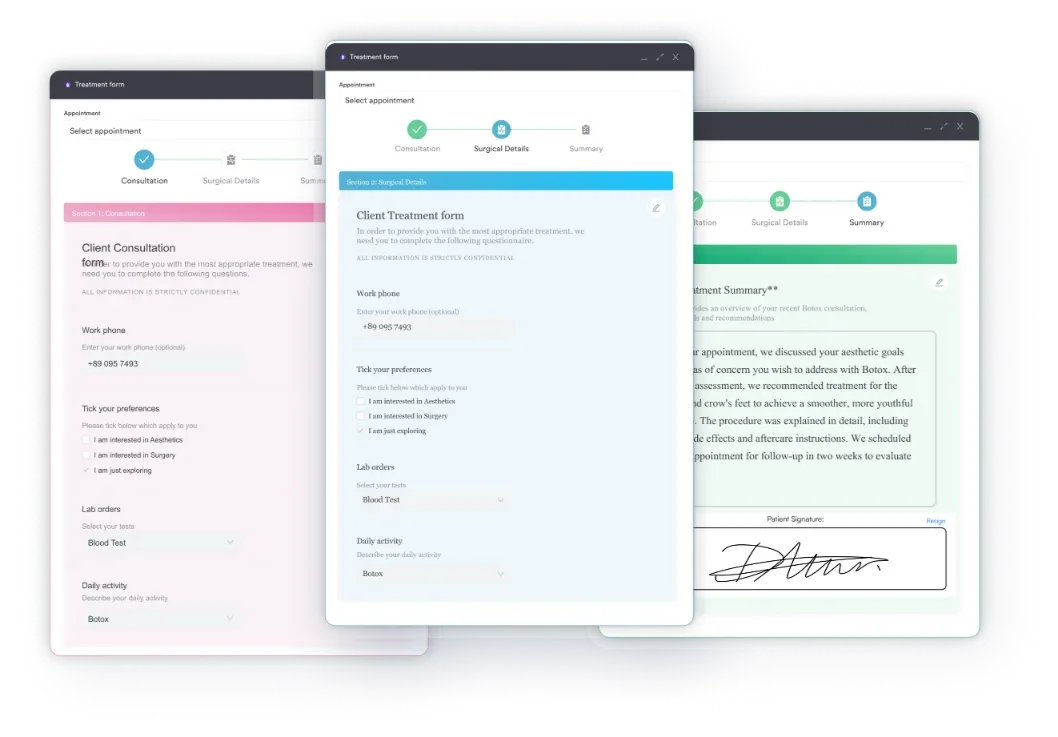

Pabau helps musculoskeletal and rheumatology practices manage patient records, streamline claims workflows, and capture the clinical documentation detail that supports accurate ICD-10 coding from the first submission.

AS rarely presents in isolation. Coders working on rheumatology claims regularly encounter the diagnoses below alongside M45.7. The AAPC ICD-10-CM code reference notes comorbidity patterns for inflammatory spondylopathies that billing staff should recognize. Practices supporting chiropractic and spinal management encounter several of these secondary codes routinely.
This is where the most preventable coding errors occur. The lumbosacral spine is coded under several overlapping categories depending on the nature of inflammation, patient age, and underlying etiology. The comparison below addresses the cases coders find most ambiguous. A chiropractic billing cheat sheet covering CPT and ICD-10 codes can help coders build the same pattern recognition across other musculoskeletal condition families. Australian MBS billing changes descriptors and fees periodically, so last year printout is not a safe reference. Revenue cycle management treats coding, submission and collection as one process rather than three handoffs.
The most frequent error is using M45.9 when the physician has documented the lumbosacral region but the coder defaults to unspecified. The same specificity rule applies well beyond musculoskeletal codes:
If the site is documented, it must be coded. Equip your team with patient records and notes tools that surface this information at the point of coding.
Run a monthly audit of your M45.9 claims. Any case where the physician note documents a specific spinal region is a candidate for query and potential code correction to the appropriate site-specific subcode. Reducing unspecified code usage improves audit defensibility and often increases reimbursement.
M45.7 has been a stable, valid code across recent ICD-10-CM fiscal years. No description changes or retirements have been recorded for this subcode in the annual CMS update files. Its current status is confirmed for FY2026 by the CDC/NCHS ICD-10-CM web tool.
Practices coding AS claims should verify the annual CMS ICD-10-CM update files each October. While M45.7 has remained stable, adjacent codes in the M46 and M47 blocks have seen periodic revisions. Clinical exam references like the Noble compression test guide can help support the physical findings documented for related musculoskeletal conditions.
Ankylosing spondylitis claims fail when the lumbosacral site is documented but not coded. ICD-10 Code M45.7 is the correct, billable code for confirmed AS affecting the lumbosacral region, valid through FY2026 and unchanged from prior years. The M45.7 vs M45.9 choice comes down to a single question: did the physician specify the anatomical region?
Pabau, practice management software for rheumatology and musculoskeletal teams, helps capture anatomical site data at the point of care, closing the missing documentation details that cause avoidable denials. Book a demo to see how Pabau supports accurate diagnostic coding workflows.

Coding a puncture wound with a retained object? Ear puncture with foreign body coding guide covers S01.341A, the code for an initial encounter with a retained right ear foreign body.
Coding a facial injury case? Facial laceration ICD-10 codes covers the S01 code family for open wounds of the head and face.
Looking for another musculoskeletal billing reference? CPT 11047 covers the add-on billing rules for bone debridement procedures.
ICD-10 Code M45.7 is a billable ICD-10-CM diagnosis code for ankylosing spondylitis of the lumbosacral region. It is a site-specific subcode of the M45 parent category (ankylosing spondylitis), valid for FY2026 with an effective date of October 1, 2025. Clinicians and coders use it when a confirmed AS diagnosis specifically involves the lumbosacral spine.
Yes, M45.7 is a billable, specific ICD-10-CM code valid for reimbursement purposes. The parent code M45 is not billable on its own; payers require a site-specific subcode such as M45.7 to process claims for ankylosing spondylitis.
M45.7 specifies ankylosing spondylitis of the lumbosacral region, while M45.9 is used when the anatomical site is unspecified. If the physician’s note identifies the lumbosacral region, M45.7 is the correct and more specific code. M45.9 should only be used when no spinal region is documented.
Ankylosing spondylitis (AS) is the radiographic form of axial spondyloarthritis (axSpA), confirmed by imaging evidence of sacroiliitis, and is coded within the M45 category. Non-radiographic axSpA has its own dedicated subcategory, M45.A, with site-specific billable subcodes such as M45.A7 for the lumbosacral region. It is not coded to M45.9 or M46.9. The M45.A subcodes coexist alongside the radiographic AS codes in the M45 family that this article covers.
The M45 category excludes juvenile ankylosing spondylitis (M08.1), arthropathy in Reiter’s disease (M02.3), and Behcet’s disease (M35.2). These are coded to their own specific categories and must not be coded under M45 or any of its subcodes including M45.7.
ICD-10 Code M45.7 became effective October 1, 2025 under the FY2026 edition of ICD-10-CM. The code has been valid in prior fiscal years as well, with no description changes recorded in recent annual updates.