HCPCS code L0638: Custom fabricated LSO billing guide
HCPCS code L0638 is a brace built for one patient HCPCS code L0638 is the Level ...

Last Updated: Nov 2, 2026
C4630 is the CCSD code for a perforating graft (keratoplasty) to the cornea, a full-thickness corneal transplant. The surgeon removes a disc of the patient's cornea and replaces it with a donor button. UK private medical insurers use the code to identify the surgeon's fee for penetrating keratoplasty.
Lamellar grafts (C4620) and endothelial keratoplasty (C4640) have their own codes. C4630 sits in CCSD chapter 4.0.0 Eye & Orbital Contents, sub-chapter 4.6.0 Cornea, with CCSD reference Fd.060.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

C4630 covers full-thickness corneal transplant only, so lamellar grafts (C4620) and endothelial grafts (C4640) are billed under their own codes.
Virtually all major UK private medical insurers require prior authorization before the procedure takes place.
The operative note must record trephine size, graft source, suture technique, and laterality to support the claim.
Pabau, the practice management platform we build, lets ophthalmology practices link each C4630 invoice to its pre-authorization reference before the claim goes out.
CCSD code C4630 is the Clinical Coding and Schedule Development (CCSD) procedure code for a perforating graft (keratoplasty) to the cornea. It describes a full-thickness replacement of the patient’s diseased cornea with a donor corneal button.
UK private medical insurers (PMIs) and independent hospitals use the CCSD schedule to identify surgical procedures for reimbursement. C4630 sits within chapter 4.0.0 Eye & Orbital Contents (sub-chapter 4.6.0 Cornea), and its CCSD reference is Fd.060. The CCSD working group maintains the schedule.
The code applies only when the surgeon performs a perforating (penetrating) keratoplasty. Partial-thickness procedures have separate CCSD entries and must not be billed as C4630. That includes deep anterior lamellar keratoplasty (DALK) and endothelial keratoplasty techniques (DSAEK, DMEK).
Penetrating keratoplasty is a full-thickness corneal transplant. The surgeon removes a disc of the patient’s cornea with a trephine. A size-matched donor button from NHS Blood and Transplant (NHSBT) replaces it. Interrupted or running nylon sutures then secure the graft.
Each step matters for coding. The operative note must reflect every stage, so the biller can confirm C4630 is correct and the insurer can verify the claim.
C4630 is appropriate when penetrating keratoplasty is clinically indicated and documented. UK PMIs expect the clinical notes to record the underlying diagnosis that made a full-thickness graft necessary. The most commonly accepted indications are listed below.
Keratoconus patients may already have had corneal ring implants, billed as C4690, or corneal cross-linking. Record any earlier treatment in the notes, because its failure supports the case for a full-thickness graft.
The CCSD technical guide sets out the conventions that apply to all CCSD codes, including C4630. The key rules for billing a perforating keratoplasty under the CCSD schedule are summarized below.
Perforating keratoplasty is one of several corneal graft techniques, and each has its own entry in CCSD sub-chapter 4.6.0 Cornea. Picking the wrong one is a frequent coding error in corneal surgery billing. The table below sets out the distinctions, and our CCSD codes index lists the rest of the schedule.
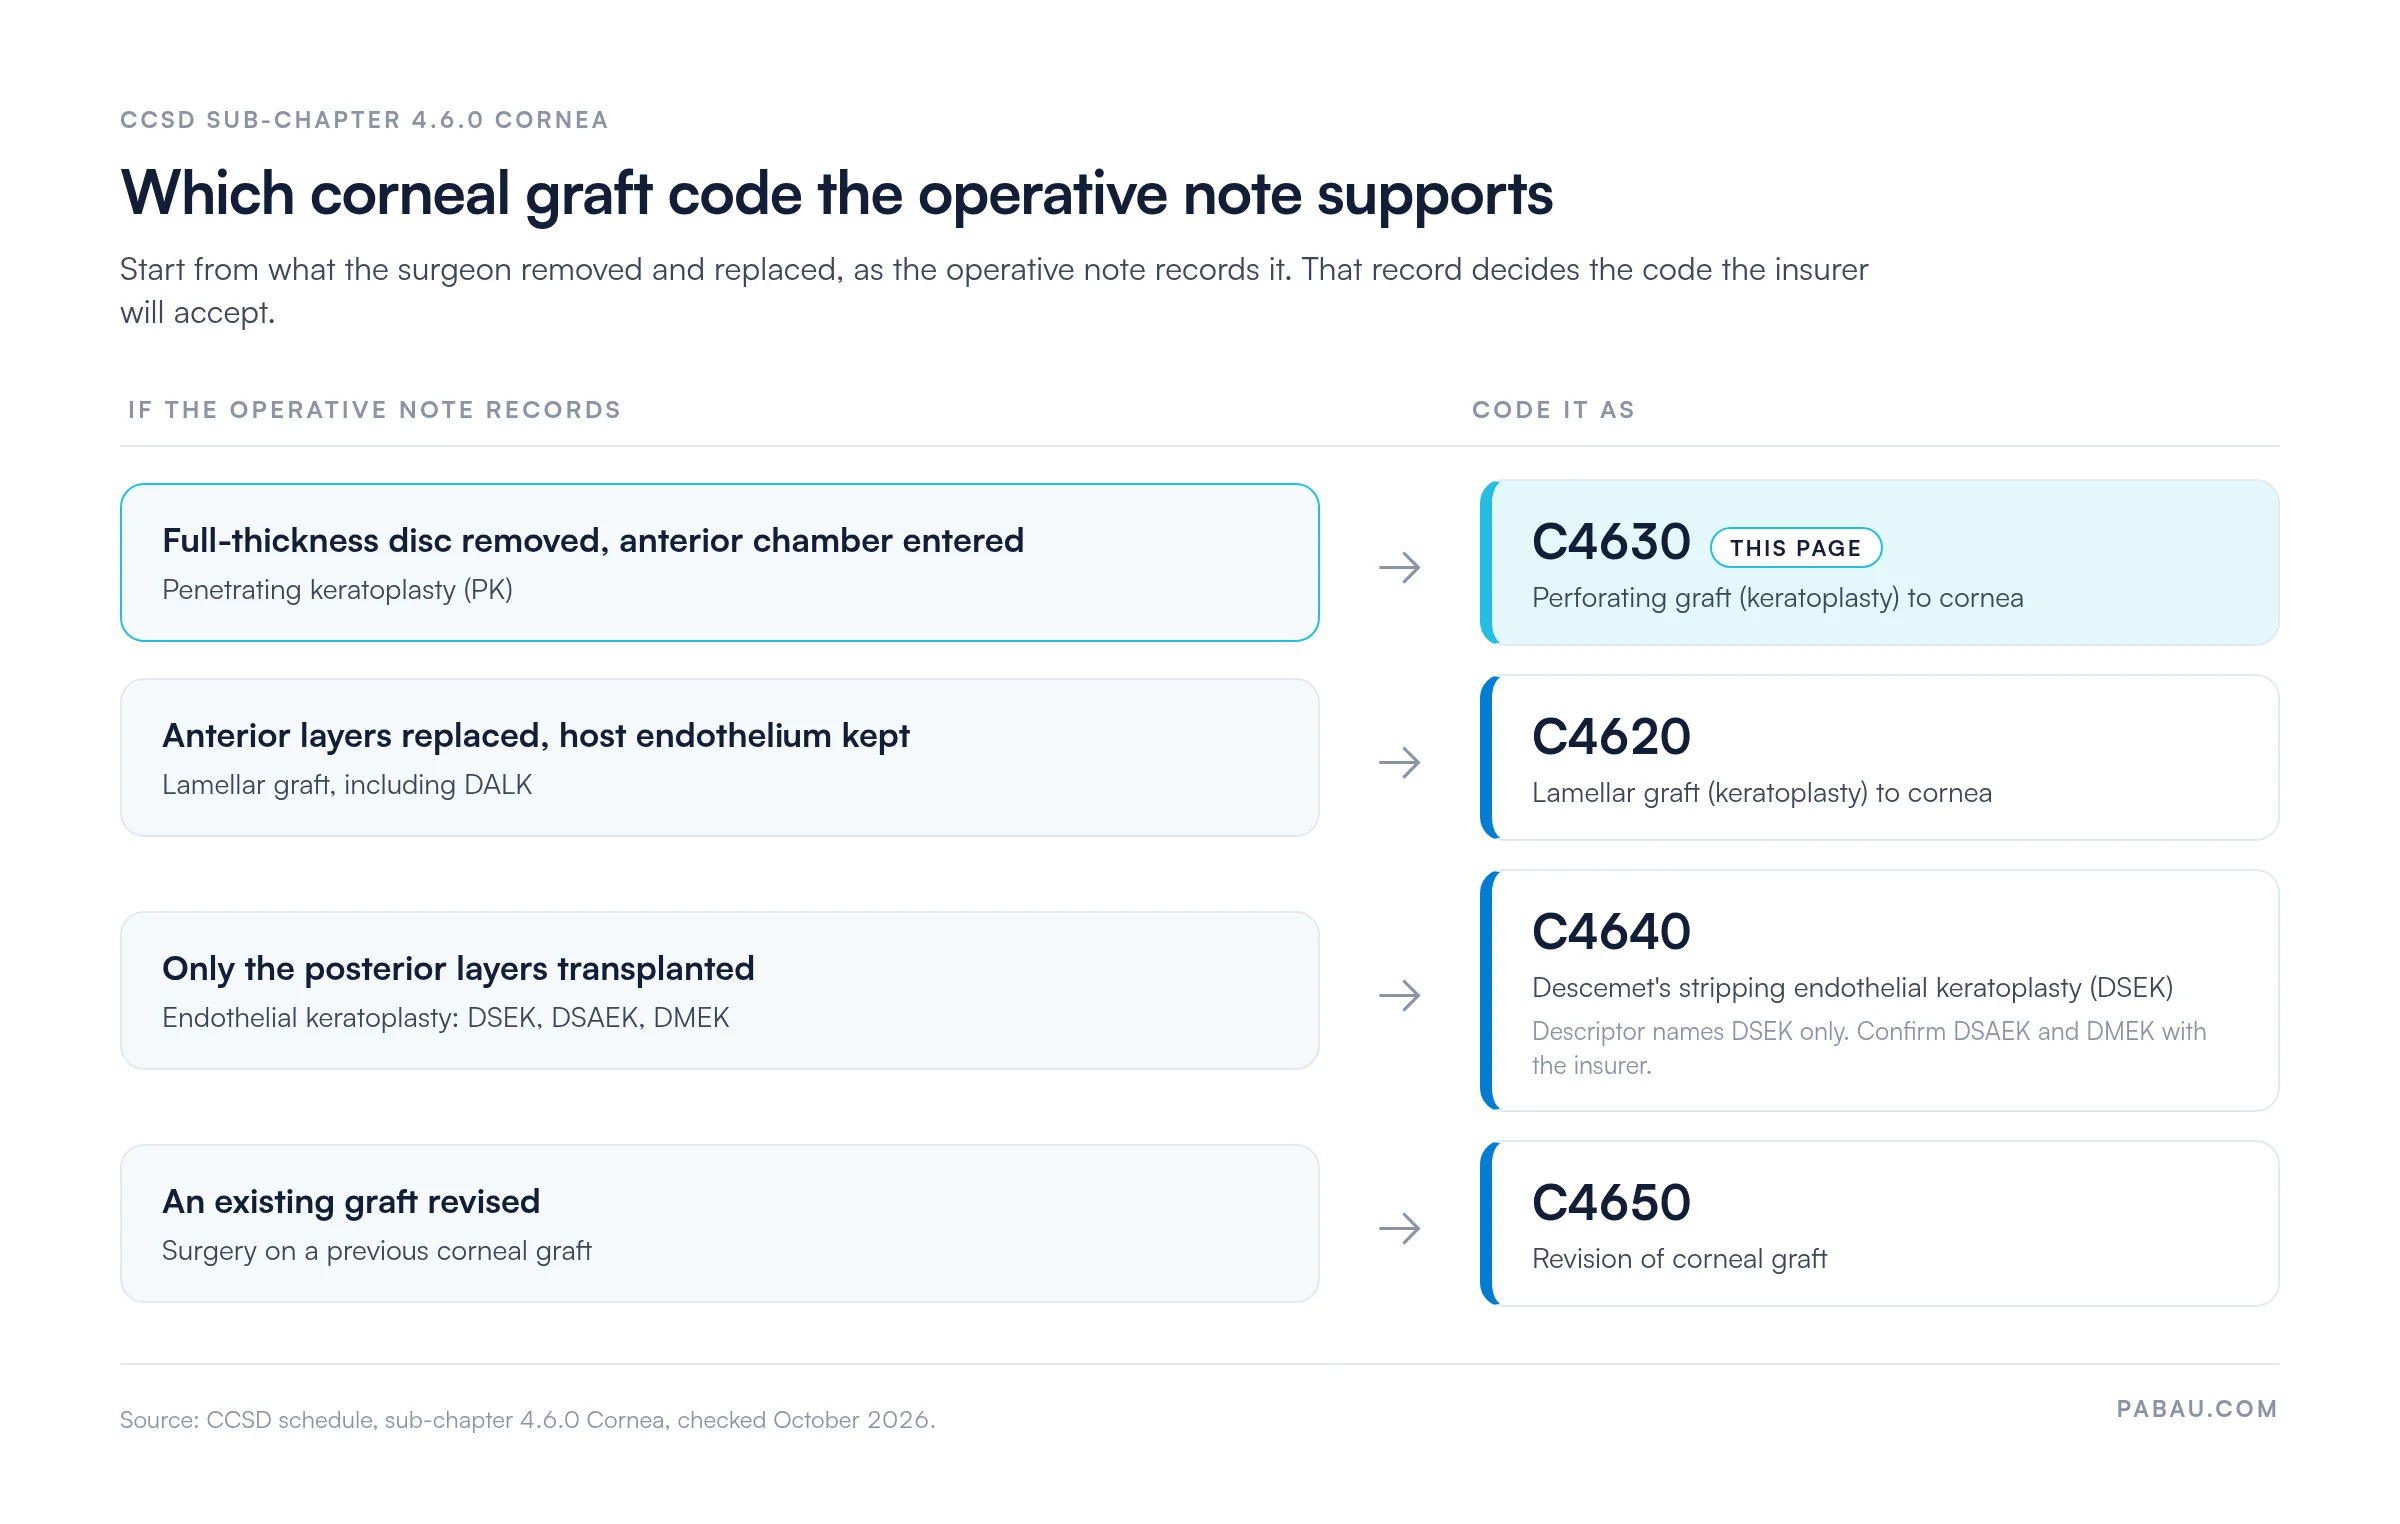
Decision rule: If the anterior chamber was opened and a full-thickness corneal disc was removed, the procedure is C4630. If the host endothelium was preserved, it is a lamellar graft under C4620. If only the posterior layers were transplanted, C4640 applies. The diagram below maps each operative finding to its code.
Clear documentation is the foundation of a clean C4630 claim. Insurers and auditors check the operative note against the code descriptor. Any ambiguity about whether a full-thickness graft was performed gives the payer grounds to query or reject the claim.
The operative note for a C4630 claim should include the following elements.
Attach the NHSBT tissue reference number to the patient record at the point of surgery, not retrospectively. If the insurer audits the claim, the tissue governance trail must be unbroken. Pabau’s digital forms let theatre staff capture graft reference numbers during the procedure and link them directly to the clinical record.
Penetrating keratoplasty is major elective surgery, and UK private medical insurers consistently require prior authorization before the operation. Submitting a C4630 claim without a valid pre-authorization reference number is a near-certain cause of denial. Check the process on each insurer’s provider portal. The major payers work as follows.
For Bupa patients, check the code against our Bupa CCSD procedure codes reference before you request authorization. Approval timelines vary by insurer and clinical urgency.
Emergency keratoplasty for a perforated ulcer should be notified to the insurer as soon as possible after surgery, with retrospective authorization requested promptly. Most PMIs accept retrospective notification for genuine surgical emergencies. Confirm this in writing with the insurer’s provider relations team.
Your practice may be new to billing private eye surgery, or adding corneal grafts to its list. Either way, these denial patterns are where C4630 rework usually starts. The most commonly reported reasons are listed below.
Bilateral penetrating keratoplasty on the same date is uncommon. Surgeons and anesthetists rarely operate on both eyes in one session, because the risks of bilateral intraocular surgery generally outweigh the logistical benefit. When both eyes need a perforating graft, the procedures are almost always staged as separate episodes.
For staged bilateral keratoplasty, each eye generates a separate invoice with its own C4630 code and pre-authorization reference. The insurer will typically require a new pre-authorization request before the second eye is operated on, even if the first authorization is still current. Don’t submit a single C4630 invoice for both eyes, because the mismatch triggers a review.
Where both eyes are operated on in the same session (exceptionally rare), submit two C4630 lines on the same invoice, clearly differentiated by laterality. Confirm in advance whether the insurer pays the full rate for both eyes or applies a bilateral reduction. Most UK PMIs apply their standard bilateral surgery convention, which typically pays the second procedure at a reduced percentage of the scheduled fee.
In many ophthalmology practices, the parts of a C4630 claim live in different places. The pre-authorization number sits in an email, the NHSBT tissue reference on a theatre sheet, and the invoice in a billing tool. Every hand-off is a chance to lose the laterality or the reference the insurer asks for.
Pabau keeps those parts on one patient record. With its medical claims management tools, your team attaches C4630 at the point of invoicing and links the pre-authorization reference. The claim then goes to the insurer without manual re-keying.
Theatre staff can record the graft reference, trephine size, and operated eye on digital forms during surgery. Your billing team sees a complete operative record before the claim leaves, so fewer C4630 invoices come back with queries.


Pabau helps ophthalmology practices build CCSD code sets, attach pre-authorization references, and submit insurer claims without manual re-keying. See how it works for surgical eye care.

C4630 is an easy code to choose and an easy one to lose money on. Its descriptor is narrow, so the claim stands or falls on whether the operative note proves a full-thickness graft in a named eye.
Build four checks into your pre-surgery routine: Authorization, laterality, the NHSBT tissue reference, and the full-thickness statement. They add a few minutes per case, which is far less than the rework a queried claim brings.
Do those checks still live on paper and in inboxes? Book a demo to see how Pabau ties each C4630 claim to its authorization and operative record.

Coding a partial-thickness graft instead? CCSD code C4620 explains how to bill a lamellar graft to the cornea.
Treating keratoconus before a graft? CCSD code C4690 covers billing for synthetic corneal ring implantation.
Repairing a corneal injury? CCSD code C4710 explains billing for corneal wound repair.
Seeing minor corneal trauma in clinic? CCSD code C4810 covers removal of a superficial corneal foreign body.
Want a broader guide to CCSD codes under Bupa? Bupa CCSD codes reference covers the full schedule structure, chapter navigation, and how Bupa applies CCSD codes to surgical procedures.
CCSD code C4630 is the procedure code for a perforating graft (keratoplasty) to the cornea. It describes a full-thickness corneal transplant, in which the patient’s corneal disc is removed and replaced with a donor button. It does not cover lamellar (DALK) or endothelial (DSAEK, DMEK) grafts.
Yes. Virtually all major UK PMIs, including Bupa, AXA Health, Aviva and Vitality, require prior authorization before a penetrating keratoplasty goes ahead. A C4630 claim without a pre-authorization reference is one of the most common causes of rejection. In genuine surgical emergencies, insurers usually accept retrospective notification if you request it promptly.
The operative note must record the treated eye, the trephine size for both recipient and donor, and explicit confirmation of full-thickness excision. It also needs the NHSBT donor tissue reference, the suture technique and material, any intraoperative complications, and the surgeon’s name and date. Missing any of these gives the insurer grounds to query the claim.
Submit one C4630 code per eye per surgical episode, with the laterality, the pre-authorization reference, and the surgeon’s fee. The anesthetist, surgical assistant, and facility each submit separate invoices. Don’t bundle tissue costs, theatre charges, or anesthetic fees into the surgeon’s C4630 line unless your insurer contract explicitly allows it.
Penetrating keratoplasty (C4630) removes the full thickness of the cornea and opens the anterior chamber. Lamellar techniques such as DALK are coded C4620, and endothelial grafts such as DSEK fall under C4640. The coding test is whether the anterior chamber was entered and a full-thickness disc excised. If not, C4630 does not apply.
The most common reasons are using C4630 for a lamellar or endothelial procedure, missing pre-authorization, and coding the wrong eye. Insurers also reject operative notes that don’t confirm full-thickness excision, and invoices that bundle anesthetist or facility fees. Checking each of these before submission prevents most rejections.