HCPCS code L0638: Custom fabricated LSO billing guide
HCPCS code L0638 is a brace built for one patient HCPCS code L0638 is the Level ...

Last Updated: Nov 2, 2026
A2730 is the CCSD code for highly selective vagotomy, also called parietal cell vagotomy. The surgeon divides only the vagal branches to the acid-secreting fundus and body of the stomach. The nerves of Latarjet to the antrum and pylorus stay intact, so no drainage procedure is needed.
Surgeons bill A2730 to UK private medical insurers such as Bupa, AXA Health and Aviva. The CCSD schedule lists it under 11.2.0 Stomach, and also under 8.11.0 Other. Proximal gastric vagotomy has its own code, A2720.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

CCSD code A2730 covers highly selective vagotomy, also documented as parietal cell vagotomy, in UK private practice billing.
Proximal gastric vagotomy has its own CCSD code, A2720, so an operative note that uses that term is not billed as A2730.
HSV preserves pyloric function, so no drainage procedure is routinely needed. A vagotomy performed with a pyloroplasty is billed under the combined code A2780.
Laparoscopic vagotomy has its own CCSD code, A2781, so check the recorded approach before you assign A2730.
Valid A2730 claims need a pre-authorization reference, an operative note that names the procedure, and a linked ICD-10 peptic ulcer diagnosis.
Pabau, the practice management platform we build, raises CCSD-coded invoices through Healthcode and tracks A2730 claim status in one system.
CCSD code A2730 covers highly selective vagotomy within the UK private healthcare procedure schedule maintained by CCSD (Clinical Coding and Schedule Development). The code sits within the Abdomen chapter of the CCSD schedule, under Stomach (11.2.0), and is also listed under 8.11.0 Other in the thorax chapter.
It is the correct billing code when the operative note describes division of only the vagal branches serving the gastric fundus and body. The nerve of Latarjet and the antral branches stay intact.
The CCSD schedule is distinct from NHS coding systems. NHS trusts use OPCS-4 procedure codes for clinical coding and HRG grouping. CCSD codes are used only in UK private practice billing, submitted to private medical insurers such as Bupa, AXA Health, Aviva, and WPA. Coders working across both sectors must take care not to apply OPCS-4 logic to CCSD invoicing.
Parietal cell vagotomy is an accepted equivalent term and maps to A2730 as well. Proximal gastric vagotomy does not. Surgical texts often treat it as a synonym, but the CCSD schedule gives it its own code, A2720.
Highly selective vagotomy reduces gastric acid output by denervating only the parietal cells responsible for hydrochloric acid secretion. The key operative steps distinguish it from the broader vagotomy types that appear in adjacent CCSD codes:
For a coder, the operative note must clearly describe these distinguishing features. An operative note that simply states “vagotomy performed” without specifying the type is insufficient for confident assignment of A2730 and creates grounds for insurer queries.
Highly selective vagotomy was developed mainly for refractory peptic ulcer disease. That remains the indication most insurers expect to see documented when A2730 is claimed.
The procedure is rare in current practice. Proton pump inhibitors (PPIs) and Helicobacter pylori eradication therapy resolve the vast majority of duodenal ulcers without surgery. When HSV does appear on a private billing schedule, the clinical context is almost always one of the following:
The ICD-10 diagnosis codes most commonly linked to A2730 claims are K25 (gastric ulcer), K26 (duodenal ulcer), and K27 (peptic ulcer, site unspecified). Insurers expect the diagnosis code on the invoice to match the documented indication.
An A2730 claim whose diagnosis code shows neither peptic ulcer disease nor another recognized surgical indication is likely to trigger a medical review or rejection.
Surgeons use different terminology in operative notes depending on their training, institution, and the era of their surgical education. Only two of the terms below map to CCSD code A2730. The others belong to separate codes, even where the surgery sounds similar.
If the operative note uses “vagotomy” without qualification, the coder must query the surgeon before assigning A2730. Assigning a more specific code without explicit documentation is a coding error that insurers may treat as upcoding.
The CCSD schedule holds four vagotomy codes that sit close to A2730. Picking the wrong one is a frequent reason A2730 claims are queried on first submission. The table below sets out how to tell them apart. For procedures outside the vagotomy group, see our CCSD procedure code guides.
The critical distinction for A2730 is pyloric preservation. HSV leaves the pylorus working, so it is billed without a drainage code. If the operative note records a pyloroplasty in the same sitting, the CCSD route is the combined code A2780. Do not bill A2730 plus a separate pyloroplasty code.
A pyloroplasty performed on its own, with no vagotomy, sits outside the vagotomy group. CCSD code G4030 covers that operation.
Run the checks in the order below. A2730 is the code left standing once the other three are ruled out.
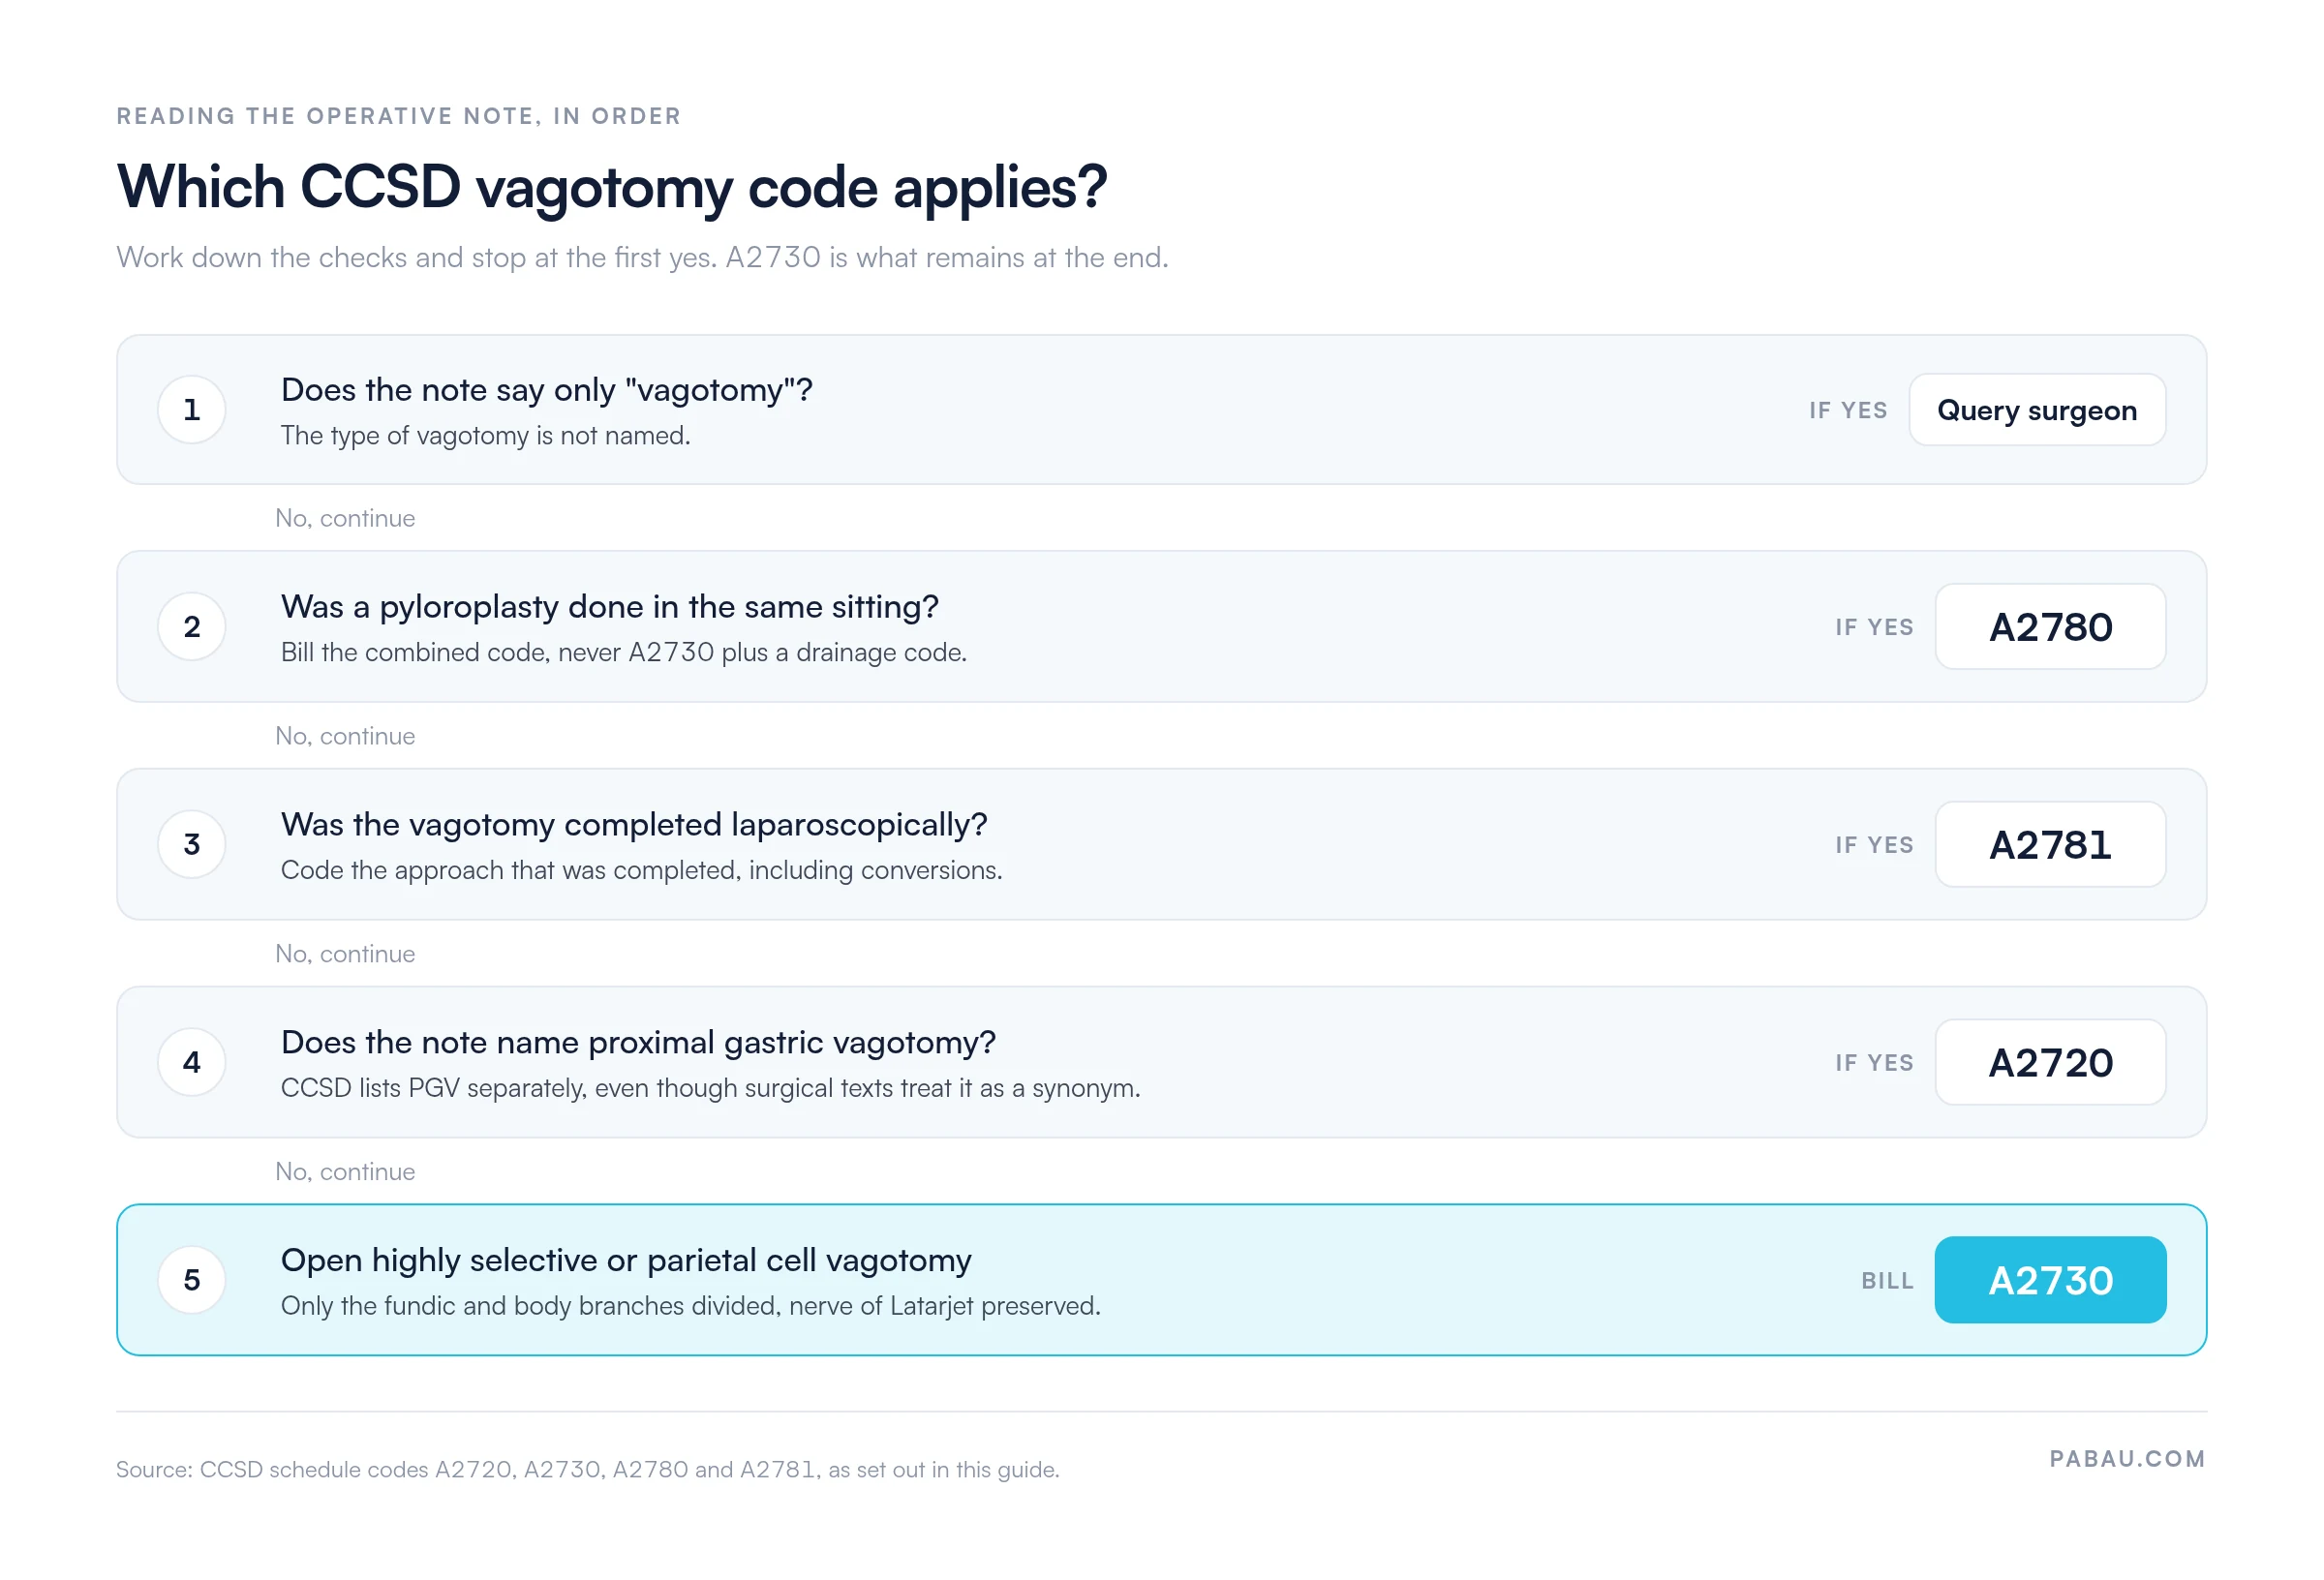
Yes. The CCSD schedule has a separate code for laparoscopic vagotomy, A2781 (Laparoscopic vagotomy/seromyotomy). When the surgeon completes the vagotomy laparoscopically, bill A2781 and keep A2730 for the open operation.
The operative note therefore has to record the approach explicitly. Write “laparoscopic highly selective vagotomy” rather than leaving the insurer to infer the approach from operating time or port sites.
If the surgeon starts laparoscopically and converts to open, code the approach that was completed. The note should state why the conversion happened and at what stage. Insurers look closely at conversion cases.
Confirm the current CCSD schedule edition is in use before submitting any claim, as CCSD updates codes and coding rules periodically.
A complete claim for CCSD code A2730 needs four elements in place before submission.
Claims are typically submitted electronically via Healthcode, the primary billing platform for UK private medical insurance. Some insurers also accept direct portal submission, but Healthcode remains the most widely used route and provides a submission audit trail useful in dispute resolution.
Pre-authorization for highly selective vagotomy is not automatic. Insurers assess the clinical case before approving elective upper GI surgery under a CCSD code A2730 claim, and they typically request a defined evidence package. Practices that gather this documentation before the pre-auth request avoid the most common delay. Insurer requests for additional information can stall the process.
The supporting evidence most major UK PMIs expect includes:
For Bupa code search and Bupa pre-authorization, clinicians and secretaries can verify the specific pre-auth requirements and fee schedule directly. Aviva’s fee schedule for practitioners sets out its CCSD-based reimbursement and documentation expectations.
Check each schedule at the time of invoicing rather than relying on memory. Insurer requirements change, and undocumented assumptions are a leading cause of avoidable claim failures.
For further information on Bupa’s CCSD procedure code requirements, see Pabau’s dedicated Bupa CCSD procedure codes reference.
Request the pre-authorization reference number before the procedure takes place, not after. Most UK PMIs will not issue a reference retrospectively for elective surgery. A missing pre-auth number is one of the most preventable reasons an A2730 claim is rejected at first submission.
Claim denials for CCSD code A2730 cluster around a predictable set of documentation and process failures. Most are avoidable with a pre-submission checklist.
Work through these steps before you raise a CCSD code A2730 invoice. Each one closes off a denial reason from the list above.
Private practices billing CCSD code A2730 need a system that holds the correct code, produces a compliant invoice, and tracks the claim through to payment. Pabau’s claims management software supports CCSD-coded invoicing and integrates with Healthcode. Billing coordinators can submit A2730 claims and monitor their status without leaving the practice management system.

Clinical documentation sits alongside billing in the same record, so the operative note and invoice reference the same patient encounter. This matters for CCSD claims. An insurer that requests supporting documentation for an A2730 clinical review gets one coherent paper trail, not documents pulled from separate systems. The result is faster review resolution and fewer supplementary information requests.

Pabau supports CCSD code invoicing, Healthcode submission, and claim tracking for UK private practices, so billing and clinical notes stay on one platform.

An A2730 claim is usually won or lost before the coder sees it. If the operative note names the vagotomy type, the approach and any drainage step, the code chooses itself. Agree that wording with your surgeons once, and the coder no longer has to send queries back to the surgeon.
The trade-off is more admin before the procedure date. Pre-authorization, the evidence pack and the diagnosis code all have to be settled up front. Insurers will not issue a pre-auth reference retrospectively for elective surgery.
Pabau’s CCSD billing tools and Healthcode integration give private practices a single place to hold clinical notes, generate compliant invoices, and track claim outcomes. To see how it fits your upper GI billing workflow, book a demo.

Billing CCSD codes for Bupa patients? Bupa CCSD procedure codes covers Bupa’s code structure, fee schedule, and pre-auth requirements for private practice billers.
Coding a proximal gastric vagotomy? CCSD code A2720 explains how PGV is billed and documented separately from A2730.
Want to reduce claim rejections across your practice? Claims management software from Pabau supports CCSD invoicing, Healthcode integration, and claim status tracking in one system.
CCSD code A2730 covers highly selective vagotomy. The surgeon divides the vagal branches supplying the acid-secreting fundus and body of the stomach while preserving antral innervation. The code also applies when the operative note uses the equivalent term parietal cell vagotomy. Proximal gastric vagotomy has its own code, A2720.
No. Surgical texts often use the two terms interchangeably, but the CCSD schedule lists proximal gastric vagotomy as a separate code, A2720. Highly selective vagotomy and its equivalent term, parietal cell vagotomy, map to A2730. Code the procedure the operative note names.
Laparoscopic vagotomy has its own CCSD code, A2781 (Laparoscopic vagotomy/seromyotomy). Use it when the vagotomy is completed laparoscopically, and keep A2730 for the open operation. The operative note must state the approach explicitly.
No. Highly selective vagotomy does not routinely need a drainage procedure because pyloric function is preserved. If the operative note records a vagotomy with pyloroplasty, bill the combined CCSD code A2780. Do not bill A2730 plus a separate pyloroplasty code.
Insurers typically require an operative note that names the procedure, a pre-authorization reference number, and a linked ICD-10 diagnosis code, usually K25, K26 or K27. They also expect evidence of failed conservative management, including H. pylori eradication attempts and PPI therapy.
The most common reasons are a missing pre-authorization reference and an operative note that does not identify the vagotomy type. A diagnosis code that changes between pre-auth and invoice causes rejections too, as does late submission outside the insurer’s claim window.