HCPCS code L0638: Custom fabricated LSO billing guide
HCPCS code L0638 is a brace built for one patient HCPCS code L0638 is the Level ...

Last Updated: Nov 2, 2026
A4708 is the HCPCS Level II code for acetate concentrate solution, for hemodialysis, per gallon.
It reports the acetate concentrate that a dialysis machine mixes with treated water to make dialysate for patients with end-stage renal disease (ESRD). Bicarbonate and acid concentrates take separate codes (A4706, A4707, A4709). Medicare pays for A4708 inside the ESRD Prospective Payment System (PPS) bundle, for in-center and home dialysis alike.
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

HCPCS code A4708 reports acetate concentrate solution for hemodialysis, per gallon.
Bicarbonate concentrate (A4706, A4707) and acid concentrate (A4709) have their own codes, so the product label decides which one you bill.
A4708 is on the CMS ESRD PPS consolidated billing list, so it is bundled into the facility’s payment for in-center and home dialysis alike.
A4714 is treated water for peritoneal dialysis, not a dialysate concentrate, and is never interchangeable with A4708.
Pabau’s claims management software checks each claim for missing details before it goes out and tracks its status through to payment.
The Centers for Medicare and Medicaid Services (CMS) defines HCPCS code A4708 as “Acetate concentrate solution, for hemodialysis, per gallon.” The code sits within the HCPCS Level II alphanumeric system, which CMS maintains for products, supplies, and services that CPT codes do not describe.
Check the descriptor against the current CMS HCPCS Alpha-Numeric file before billing. Wording and status can change with each annual HCPCS update.
The code falls in the A4000-A4999 series, which covers medical and surgical supplies. The dialysis machine mixes concentrate with treated water to make the dialysate that passes through the dialyzer. A4708 covers the acetate form of that concentrate, and one unit equals one gallon.
A4708 covers acetate concentrate solution for hemodialysis, reported per gallon. It does not cover bicarbonate concentrate, acid concentrate, or any peritoneal dialysis supply, since each of those has its own HCPCS code.
The table below sets out what falls inside and outside A4708, line by line.
Four HCPCS codes describe hemodialysis concentrate, and they split on two variables: Concentrate type and billing unit. A4708 is the only one for acetate concentrate. Bicarbonate concentrate takes A4706 as a solution or A4707 as a powder. The product label and the delivery record decide the code, whether dialysis runs in-center or at home.
A4714 sits close by in the A47xx range, so coders sometimes treat it as a dialysate code. It is not interchangeable with A4708, because A4714 reports treated water (deionized, distilled, or reverse osmosis) for peritoneal dialysis, per gallon.
Match the code to the concentrate named on the product label and the delivery record. Bicarbonate dialysis normally runs on two concentrates, acid plus bicarbonate, which map to A4709 plus A4706 or A4707, not to A4708. Never report A4714 for a hemodialysis concentrate, because it describes peritoneal dialysis water.
The chart below puts both decisions in one place: Which code the label points to, and which claim carries it for an ESRD patient.
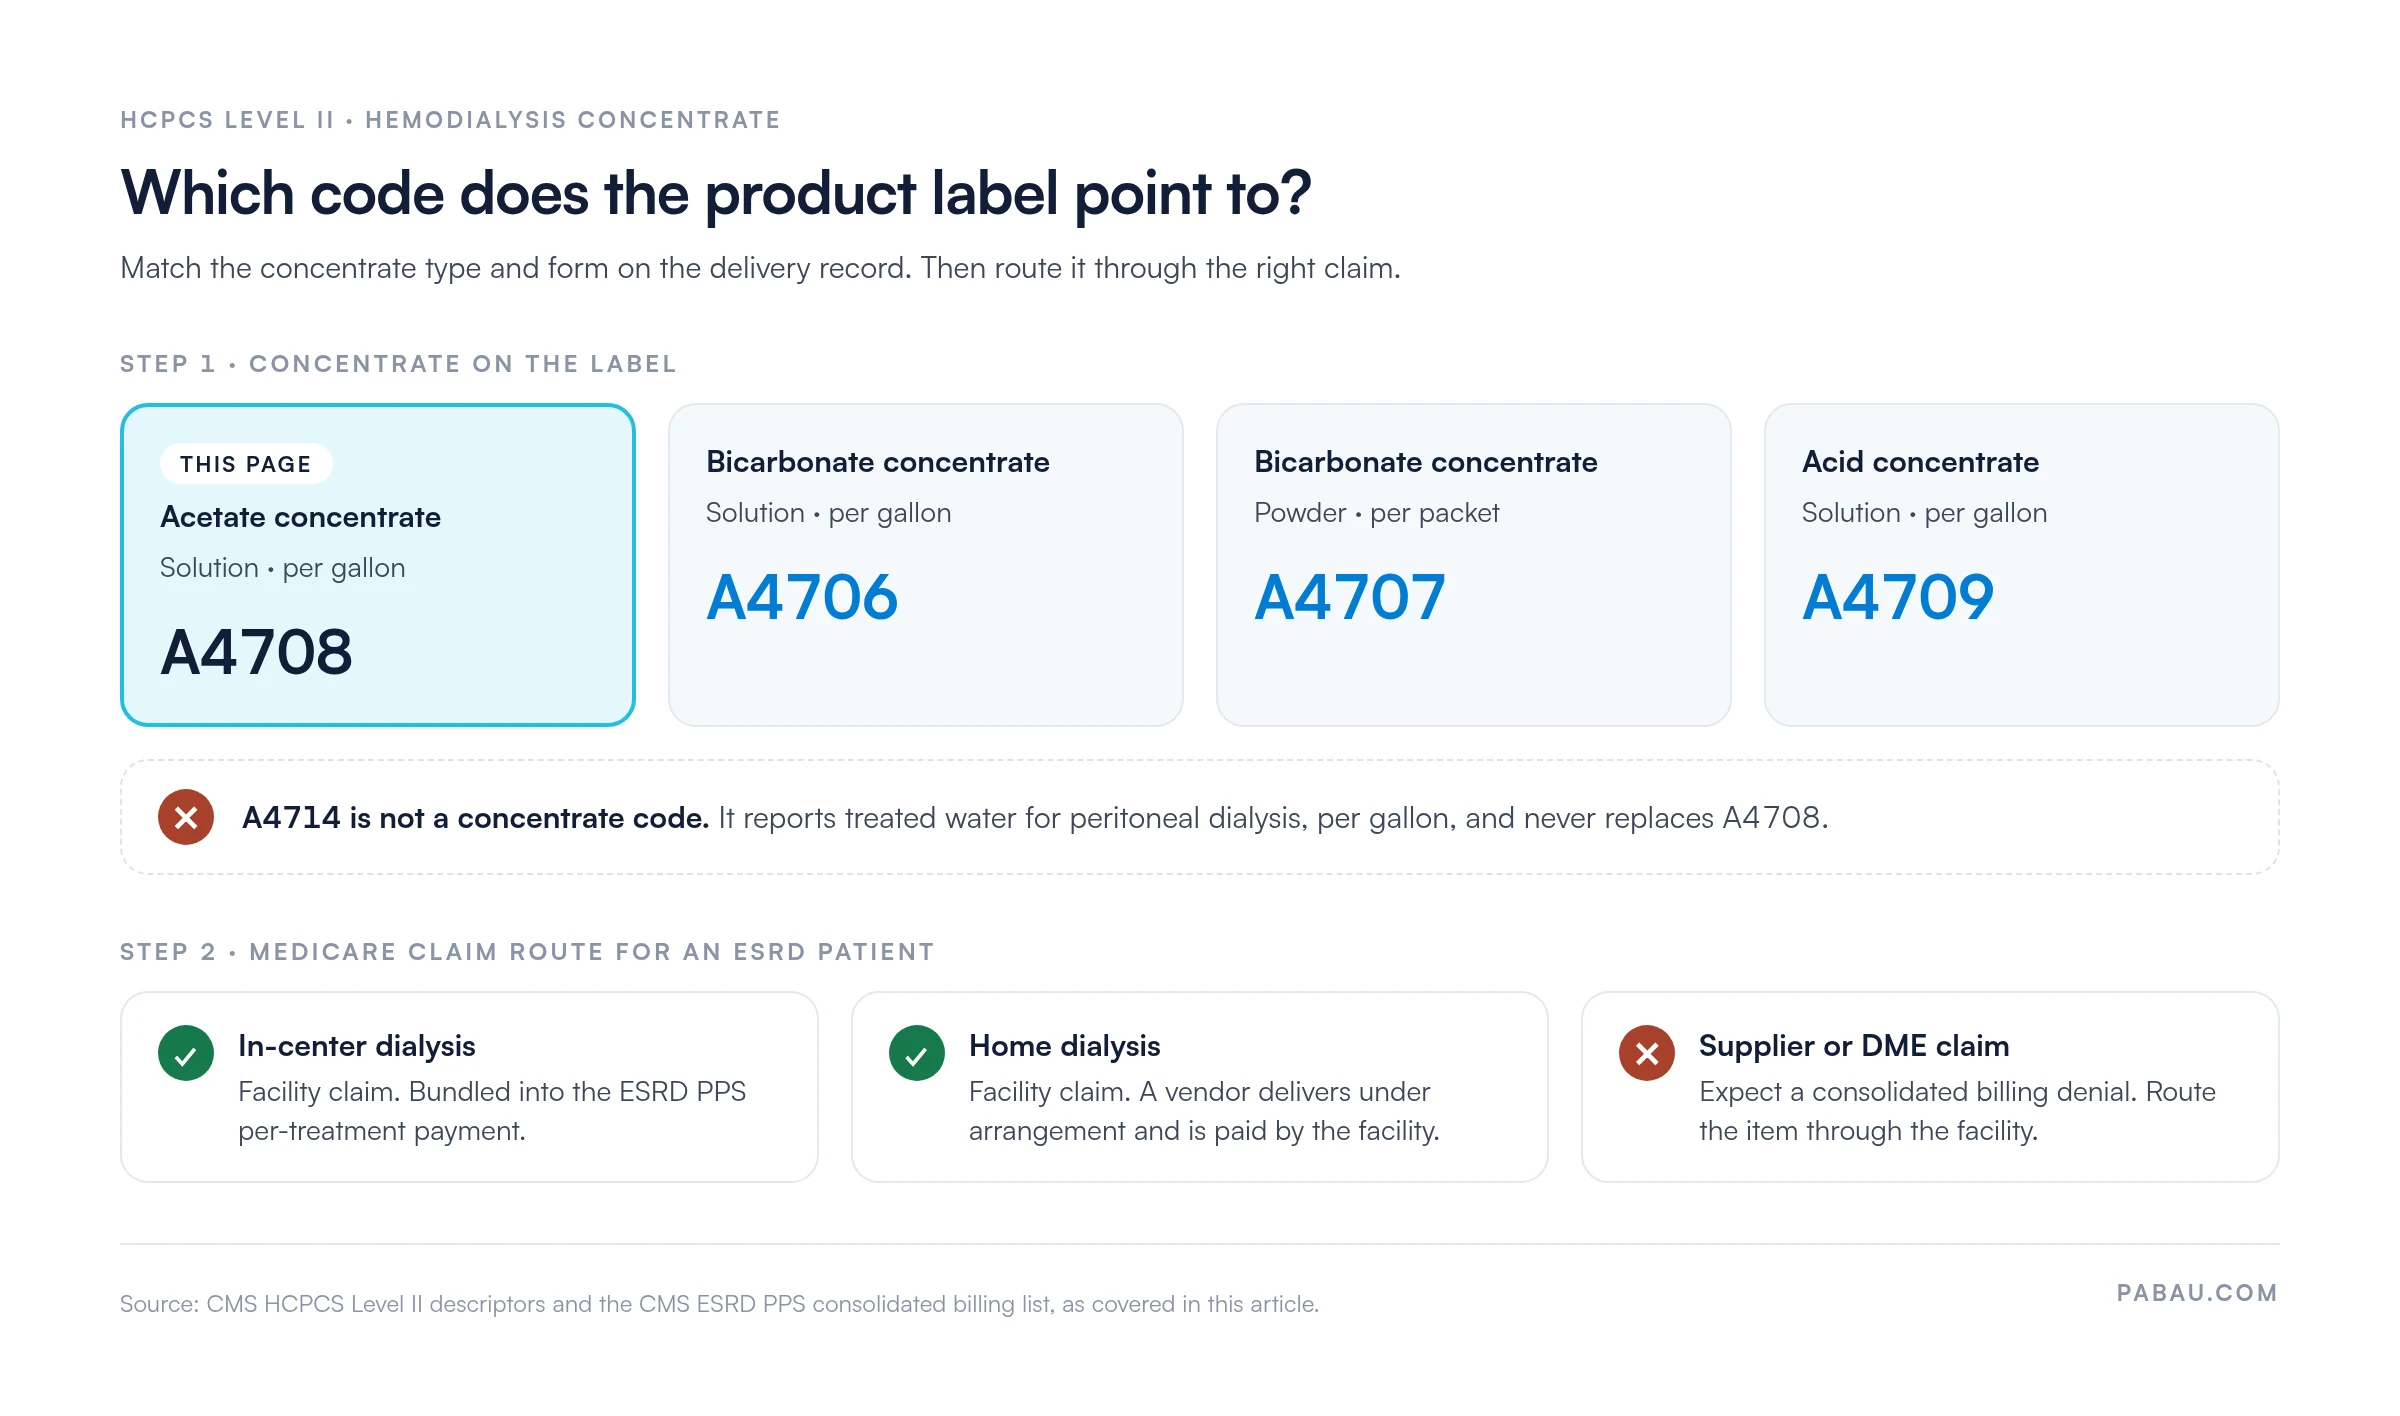
A4708 appears on the CMS ESRD Prospective Payment System (PPS) consolidated billing list. Medicare pays for acetate concentrate through the ESRD facility’s bundled per-treatment payment, not as a separate line item.
The bundle covers home dialysis too. Since the ESRD PPS began in 2011, the ESRD facility is responsible for home dialysis supplies. The separate supplier route (Method II) no longer exists. A vendor that delivers concentrate to a home patient is paid by the facility under arrangement, not by Medicare.
Because Medicare bundles A4708, there is no separate fee schedule amount to collect for an ESRD patient. CMS updates the ESRD PPS consolidated billing list regularly, so check it each payment year.
Consolidated billing works the same way for A4770, the vacuum tubes used to draw blood samples from dialysis patients. Medicare does not price those tubes separately either.
Home hemodialysis changes who delivers the concentrate. Responsibility stays with the ESRD facility that manages the patient’s home program, which keeps the supply inside its bundled payment under consolidated billing.
Because Medicare bundles A4708, documentation protects the facility on audit rather than unlocking a separate payment. Commercial and Medicaid payers that pay the code separately will also ask for these records. Assemble them before submission, not after a denial arrives.
Strong medical billing compliance practice for A4708 requires the following documentation on file:
Keep documentation organized in the patient’s supply file, as payers may request records on post-payment audit. Tracking which home dialysis patients still lack an order or a delivery record is easier in claims management software than in a spreadsheet.

Because the ESRD facility reports A4708 inside its bundled payment, the line rarely needs a modifier. The modifiers below are the ones that come up when a payer or a claim edit questions the item.
DMEPOS modifiers such as KX, NU, RR, and UE do not apply to a consumable billed under the ESRD bundle. Adding them to an A4708 line signals a supplier claim that Medicare does not expect.
Modifier applicability varies by MAC jurisdiction and payer. Confirm current requirements against your billing MAC’s local coverage determination (LCD) and AAPC’s HCPCS code reference before submitting.
Most A4708 denials trace back to the six causes below. Structured denial management catches each one before submission, which cuts the rework cycle.
To stop repeat supply code denials, map each rejection to its denial codes and track which root cause keeps coming back.
Payers expect A4708 claims to carry diagnosis codes that document the underlying ESRD and the patient’s dependence on dialysis. The codes below are those most commonly accepted alongside A4708. Medical necessity criteria vary by MAC jurisdiction, so confirm the applicable local coverage determination before billing.
ICD-10 pairing requirements are payer-specific and can change when CMS issues new Local Coverage Determinations. Review applicable LCDs through the Medicare Informatics HCPCS tables or your MAC’s coverage database to confirm accepted diagnosis codes for A4708 in your region.
N18.6 (End-stage renal disease) and Z99.2 (Dependence on renal dialysis) together form the strongest diagnosis pair for A4708 claims. Submitting A4708 with only a CKD stage 1-4 code is a near-certain denial. Check that your billing system’s claim scrubber flags ESRD supply codes that lack N18.6 or Z99.2 before they reach the payer.
Many dialysis billing teams track concentrate deliveries, physician orders, and payer rules in separate spreadsheets. That split is how a vendor ends up billing A4708 directly, or a delivery record goes missing before an audit.
Pabau, the practice management platform we build, keeps claims beside the calendar, patient records, and invoices. In the US it connects to Claim.MD, so you can check eligibility, submit claims electronically, and post ERA remittances from one dashboard.
Validation checks run every time you send a claim, flagging missing details such as membership numbers or authorization codes. Each claim then moves through clear stages, from pending to paid or error, so a rejected supply line surfaces the day it comes back.

Pabau checks each claim for missing details before it goes out and tracks its status through to payment. Your team can fix a rejected A4708 line the day it comes back.

Code A4708 from the product label every time. Acetate concentrate is A4708, bicarbonate and acid concentrates go to A4706, A4707, or A4709, and A4714 water never belongs in this decision.
For a Medicare patient with ESRD, the claim route matters more than the code. Every gallon belongs on the facility’s claim, in-center or at home, so keep vendor arrangements and delivery records ready for the audit that eventually comes.
Book a demo to see how Pabau keeps dialysis supply claims, invoices, and patient records in one place for your billing team.

Want to understand how denials are categorized across your claims? Denial codes in medical billing explains how CARC and RARC codes map to denial root causes, helping billing teams fix patterns rather than individual claims.
Looking for a structured billing compliance checklist? Medical billing compliance covers the documentation, auditing, and payer-specific requirements that keep dialysis supply claims clean.
Need to understand the full revenue cycle behind supply code billing? What is medical billing walks through how HCPCS supply codes move from clinical documentation to collected payment.
HCPCS code A4708 covers acetate concentrate solution for hemodialysis, reported per gallon. It does not cover bicarbonate concentrate (A4706, A4707), acid concentrate (A4709), peritoneal dialysis water (A4714), dialysis equipment, or facility services.
A4708 is acetate concentrate solution, per gallon. A4706 is bicarbonate concentrate solution, per gallon, and A4707 is bicarbonate concentrate powder, per packet. A4709 is acid concentrate solution, per gallon. A4714 is treated water for peritoneal dialysis, per gallon, and is never interchangeable with A4708.
A4708 is on the CMS ESRD PPS consolidated billing list, so Medicare pays for it through the ESRD facility’s bundled payment. That applies to in-center and home hemodialysis alike. A separate claim for the concentrate from a supplier or another provider is expected to deny.
Keep a signed physician order that names the concentrate and an ESRD ICD-10 diagnosis code (typically N18.6 with Z99.2). Delivery records must match the units reported. For home patients, also keep the facility’s arrangement with any vendor that delivers the concentrate.
Most A4708 lines need no modifier, because the ESRD facility reports them inside its bundled payment. AY applies only to items unrelated to ESRD treatment, which rarely fits dialysate concentrate. GA, GY, and GZ come up when a payer may deny the item. DMEPOS modifiers such as KX, NU, RR, and UE do not apply.
Medicare pays for A4708 inside the ESRD PPS bundle, so prior authorization does not arise for it on Medicare claims. Medicaid state plans and commercial payers may impose their own requirements. Always verify prior authorization obligations with the specific payer before delivering the supply.
The most common cause is billing A4708 outside the ESRD PPS bundle. Others include confusing it with A4706, A4707, A4709, or A4714, and missing orders or delivery records. Incorrect units, misused modifiers, and a CKD stage 1-4 code in place of N18.6 also cause denials.
The ESRD facility that manages the patient’s home program is responsible for the concentrate under consolidated billing. It may use a vendor to deliver it, but it pays that vendor under arrangement. Medicare does not expect a separate DMEPOS claim for A4708.