









ICD-10 code Y63.1: Incorrect dilution of fluid used during infusion
ICD-10 code Y63.1 is the billable ICD-10-CM diagnosis code for incorrect dilutio...

Last Updated: Sep 14, 2026

ICD-10 code T86.290 is the billable diagnosis code for cardiac allograft vasculopathy, the accelerated coronary artery disease that develops in a transplanted heart.
It sits under subcategory T86.29, which has exactly two billable children. T86.290 covers the vasculopathy itself, and T86.298 covers other heart transplant complications.
The code most often used in its place is T86.20, the unspecified complication of heart transplant. T86.20 sits one level up in the tree, as a sibling of T86.29 rather than a child of it.
ICD-10-CM also restricts what may travel with a T86.2- code. Z94.1, heart transplant status, should not be reported with a code from subcategory T86.2. The complication code already tells the payer that the patient has a transplanted heart. The sequencing section below quotes the guideline in full.

T86.290 is the billable ICD-10-CM code for cardiac allograft vasculopathy, and it carries into the FY2026 edition unchanged.
Subcategory T86.29 has exactly two billable children, T86.290 and T86.298, and the subcategory itself is never submitted.
T86.20 covers an unspecified complication of heart transplant and sits one level up, as a sibling of T86.29.
Z94.1 should not be reported with any T86.2- code, and the official guidelines use that exact pairing as their example.
An Excludes1 note blocks T86.290 from being coded with the coronary atherosclerosis codes I25.75-, I25.76-, and I25.81-.
Practice management software like Pabau keeps the chosen diagnosis code attached to the note and to the claim.
T86.290 is a complete five-character code, so it can go on a claim as it stands. Its parent, T86.29, is a four-character subcategory heading and is never submitted. The table below sets out the attributes a coder or biller usually needs to confirm.
The Centers for Medicare and Medicaid Services and the National Center for Health Statistics publish the code set each fiscal year.
You can confirm the current wording in the CDC ICD-10-CM browser tool or through the CMS ICD-10 code files. T86.290 has been in the US code set since ICD-10-CM took effect on October 1, 2015, and the FY2026 edition carries it forward unchanged.
Cardiac allograft vasculopathy, or CAV, is a diffuse narrowing of the coronary arteries inside a transplanted heart. Immune injury to the graft vessels drives it, and non-immune factors such as ischemia at the time of transplant add to the damage.
Native coronary disease tends to form discrete plaques. CAV instead thickens the vessel wall along the whole length of the coronary tree. That makes it hard to spot on standard angiography and hard to treat with stenting or bypass.
Transplanted hearts are denervated, so recipients often feel no angina as the disease progresses. Programs therefore screen on a fixed schedule with coronary angiography or intravascular ultrasound rather than waiting for symptoms. CAV remains one of the main reasons a graft fails in the years after transplant.
For coding, the line that matters is the one between vasculopathy and rejection. Rejection is an immune attack on the myocardium and maps to T86.21. Loss of graft function maps to T86.22. Vasculopathy of the graft coronaries maps to T86.290, and the physician’s wording decides which of them applies.
T86.290 occupies the fourth level of the tree, inside the injury and poisoning chapter. Seeing the whole T86.2 subcategory at once is what prevents the common mistakes. T86.20 looks like a child of T86.29, and it is not. T86.20 is a sibling of T86.29, one level above T86.290.
Two details in that table do most of the work. T86.29 has exactly two children, and neither T86.2 nor T86.29 may appear on a claim. Where the record supports a named complication, drill down to the five-character code and leave the headings alone. Our guide to denial codes covers how a specificity denial gets worked when one slips through.
The alphabetic index settles most of these calls in about ten seconds. Look up Complication, then transplant, then heart, and read the subterms before you pick.
T86.298 and T86.20 are both legitimate codes, and neither one is a fallback for a documented vasculopathy. T86.298 records that the physician named a specific complication. T86.20 records that nobody did. The map below pairs each wording a transplant note might carry with the code it supports.
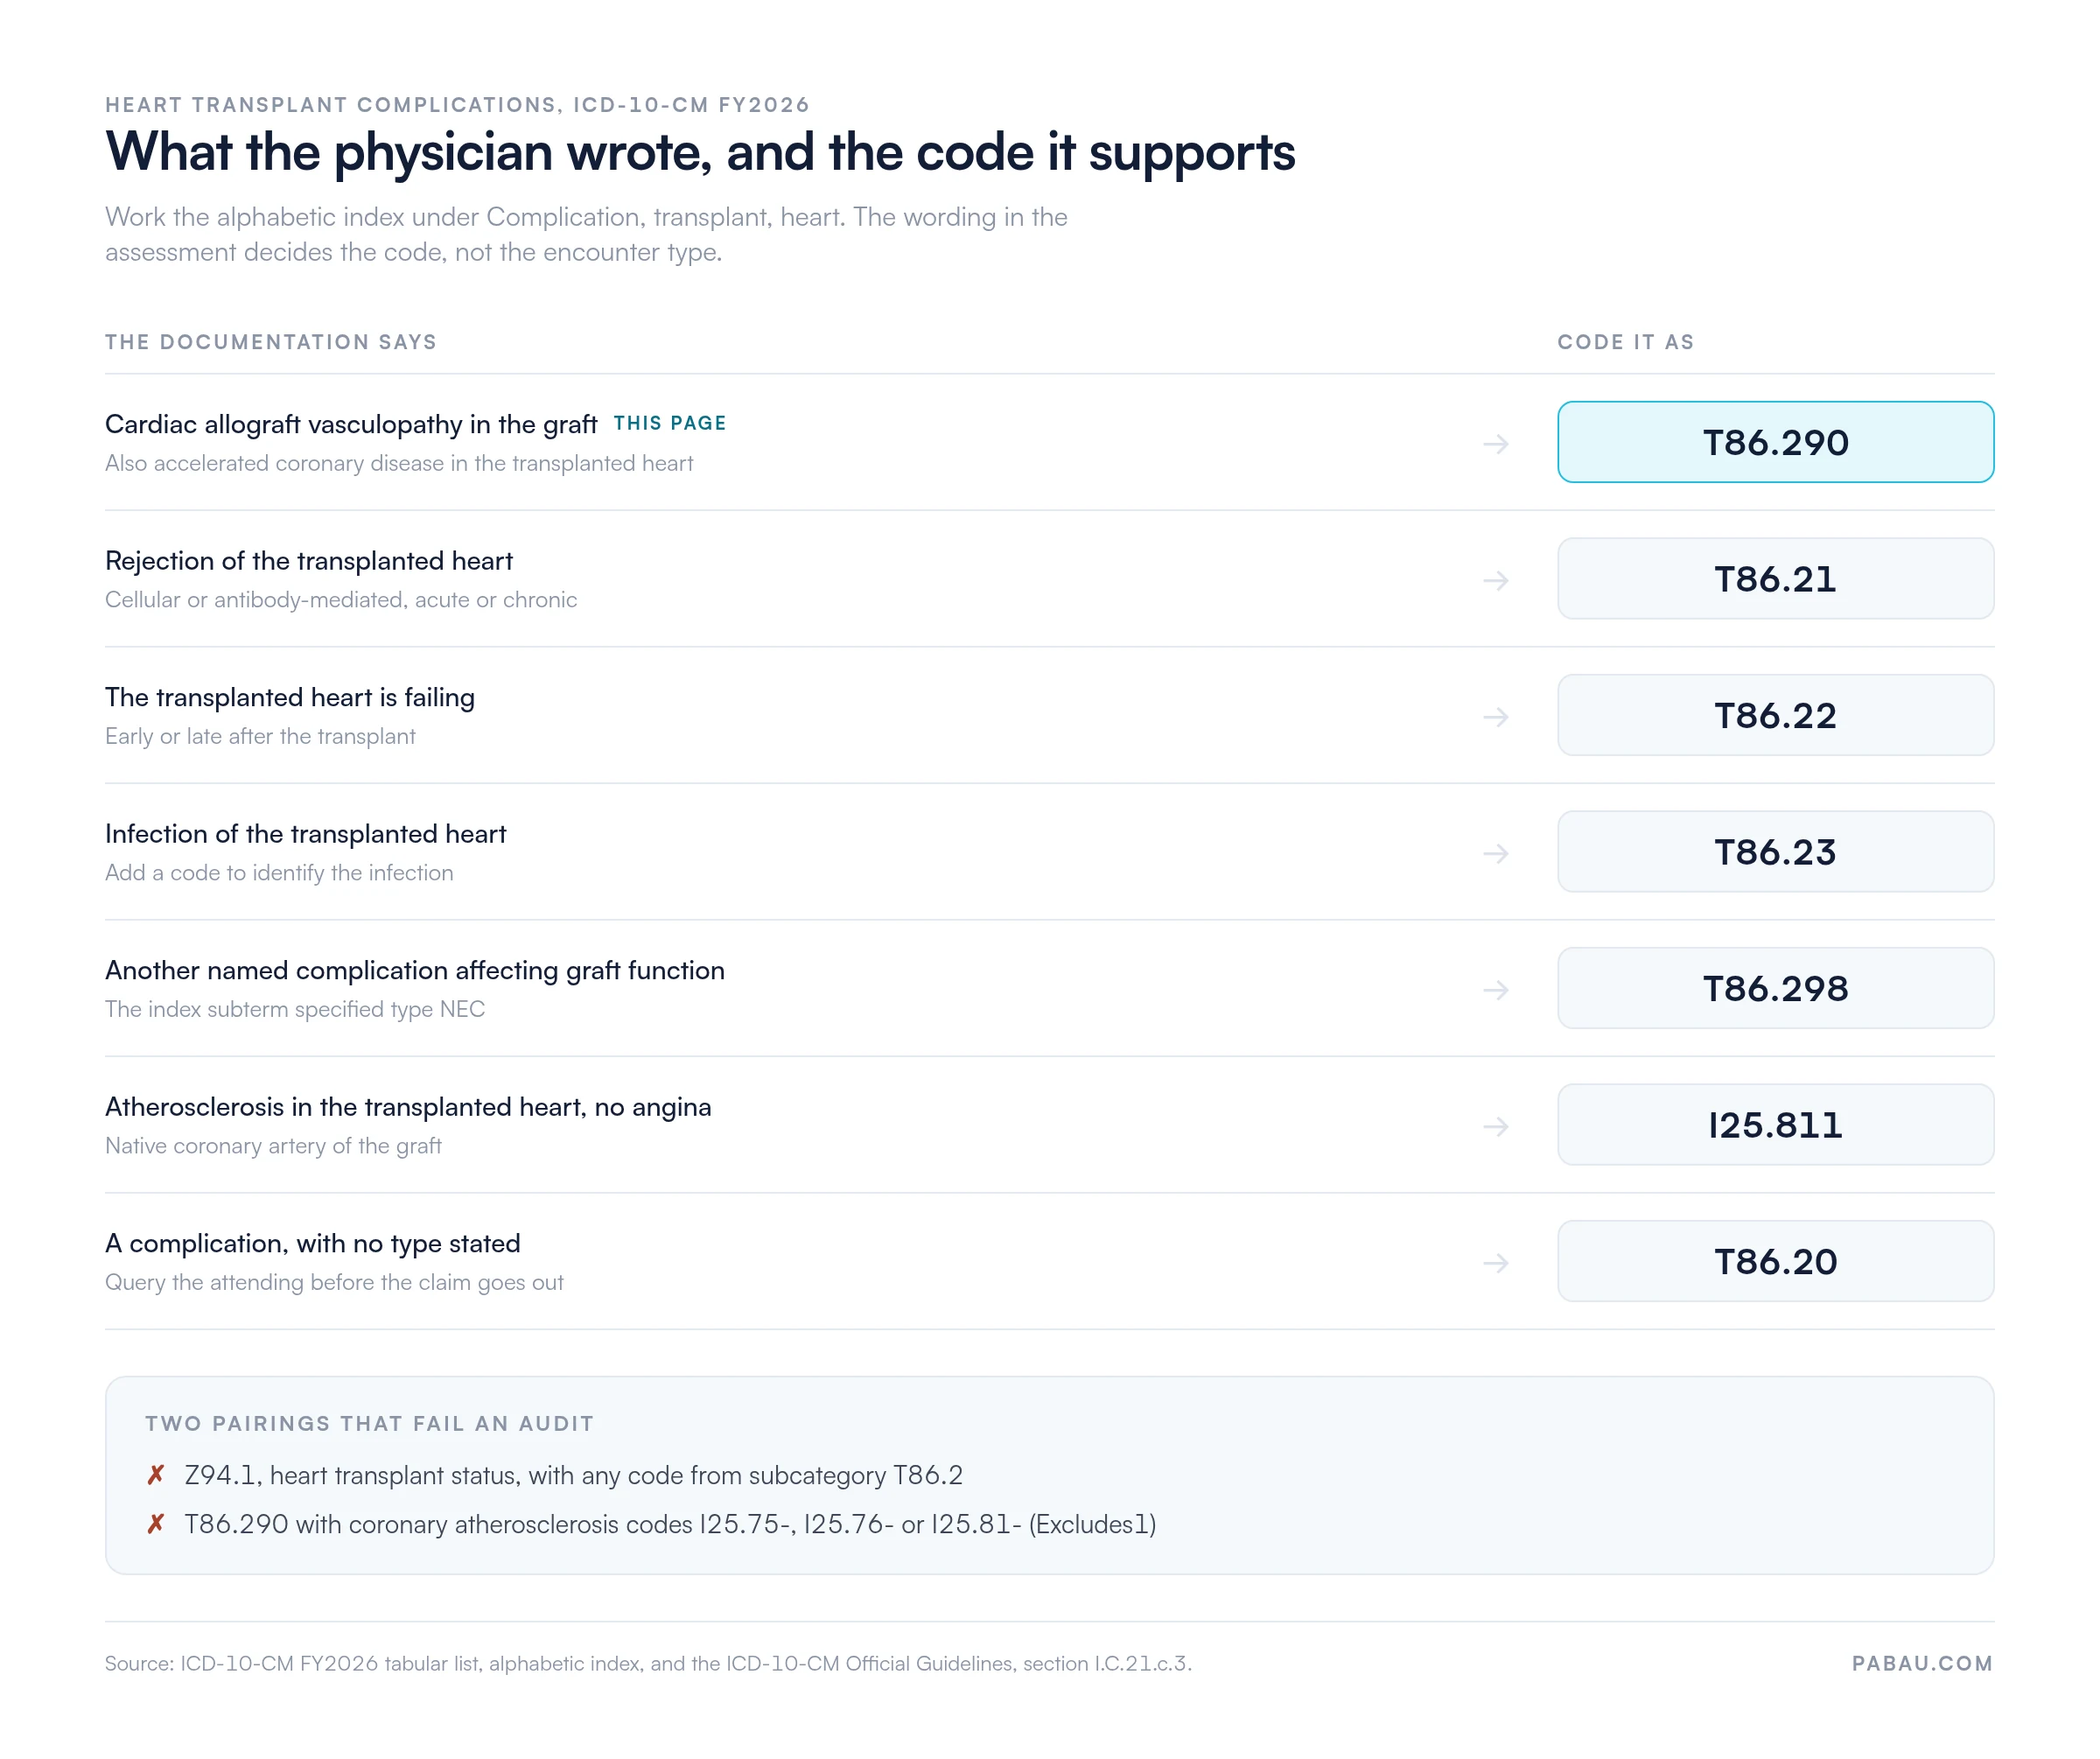
Work the index before you reach for a code. Under Complication, transplant, heart, the subterm cardiac allograft vasculopathy takes you to T86.290, and specified type NEC takes you to T86.298. If the note does not get you past the main term, you have a physician query rather than a code.
Two Excludes1 notes govern this code. An Excludes1 means the two conditions are never reported together for the same encounter, so these notes decide the code rather than decorate it.
The first note sits directly under T86.290 and excludes atherosclerosis of coronary arteries, listing I25.75-, I25.76-, and I25.81-. Those are not generic coronary disease codes. Several of them describe the transplanted heart specifically.
The coder’s job here is to follow the physician’s words. Documented allograft vasculopathy goes to T86.290. Documented atherosclerosis in the transplanted heart goes to the matching I25 code. Reporting both on one claim breaks the Excludes1 rule.
The second note sits under T86.2 and excludes complications of an artificial heart device (T82.5-) and of a heart-lung transplant (T86.3-). A combined heart-lung recipient is coded in T86.3-, never in T86.2-.
Chapter 19 of the official guidelines sets two conditions before any T86 code is assigned. Both are worth reading before the sequencing rules.
Section I.C.21.c.3 of the FY2026 ICD-10-CM Official Guidelines for Coding and Reporting puts it plainly. The guideline reads: “code Z94.1, Heart transplant status, should not be used with a code from subcategory T86.2, Complications of heart transplant.”
Category Z94 carries a matching Excludes1 note for complications of a transplanted organ. Plenty of transplant coding cheat sheets still list Z94.1 as a required companion code, and that advice will not survive an audit.
A coder cannot assign T86.290 unless the physician names the condition. On a transplant claim, a problem-list entry will not carry the code on its own.
Where the wording is ambiguous, query the physician. A good query asks whether the coronary findings represent allograft vasculopathy or atherosclerosis in the transplanted heart. It never asks which code to use.
Our guide to ICD-10 code T86.298 works through the same query pattern for complications that are named but not classified elsewhere.
Print a one-page card for the transplant coding desk. List T86.290, T86.298, T86.20, T86.21, T86.22, T86.23, and I25.811 with a one-line rule each. Add the two pairings that fail an audit. Z94.1 never rides along with a T86.2- code, and an I25 coronary atherosclerosis code never rides along with T86.290.
The table below is the short list a transplant cardiology coder reaches for most days.
The AAPC ICD-10-CM code lookup is a reasonable cross-check across the whole T86 range. For the code set itself, the CDC browser tool linked above is the primary source, and it is free to use.
Most of this gets caught before submission, when the claim passes through front-end edits. A scrubber that flags the Z94.1 pairing saves the billing team an appeal it would otherwise have to write.
A heart transplant recipient attends the yearly surveillance angiogram. The report describes diffuse distal narrowing, and the cardiologist documents cardiac allograft vasculopathy affecting graft perfusion. Report T86.290 for the encounter, and leave Z94.1 off the claim.
The same patient returns a year later with a focal lesion in a native coronary artery of the transplanted heart. The cardiologist documents atherosclerosis and records no angina. The Excludes1 note under T86.290 sends this encounter to I25.811 instead.
A discharge summary lists a complication of heart transplant with no further detail. The index main term on its own gives T86.20, so query the attending before the claim goes out. If the query comes back naming the vasculopathy, the encounter is coded T86.290.
Transplant coding usually goes wrong in the handoff between the clinical note and the claim. The cardiologist writes allograft vasculopathy, and somewhere between the letter and the billing screen it becomes an unspecified code.
Practice management software like Pabau shortens that journey by holding the diagnosis code on the patient record instead of in a separate billing queue.
Pabau’s claims management software lets the coder attach the diagnosis code to the encounter as the note is finalized. The invoice and the claim are then built from that same record. For US practices, the Claim.MD integration submits electronic CMS-1500 claims to thousands of US payers and checks eligibility before submission.
Claim statuses and electronic remittance advice come back into Pabau against the original claim. A denied transplant claim surfaces in one place rather than a spreadsheet.
Reporting then shows denial rates by code, which is how a team spots a specificity problem with T86.290 while it is still small. The same view holds across every specialty the practice bills.


Pabau links the diagnosis code to the clinical note and submits the claim through Claim.MD, so a specific code like T86.290 reaches the payer intact.

T86.290 is the specific, billable code for cardiac allograft vasculopathy, and it has been in ICD-10-CM since the code set took effect in 2015. Getting it right comes down to three habits. Work the alphabetic index instead of memory, respect the two Excludes1 notes, and keep Z94.1 off any claim that carries a T86.2- code.
Those habits cost a few seconds per encounter. The alternative is a transplant claim held for specificity review, on a stay the hospital has already paid for.
Practice management software like Pabau keeps the code the cardiologist supported attached to the claim the payer receives. To see how that works across transplant and cardiology billing, book a demo.

Need the code for a graft that is failing rather than narrowing? ICD-10 code T86.22 covers heart transplant failure and how it is sequenced.
Want the full picture of how billing runs end to end? Revenue cycle management explained walks through every stage from code assignment to payment posting.
Worried about denials on transplant claims? Denial management in healthcare covers root-cause analysis and appeals.
T86.290 is the billable ICD-10-CM diagnosis code for cardiac allograft vasculopathy, the accelerated coronary artery disease that develops in a transplanted heart. It is one of the two five-character codes under subcategory T86.29, and it is valid for claim submission in the FY2026 edition.
Yes. T86.290 is a complete five-character code and can be submitted on a claim. It has been part of ICD-10-CM since the code set took effect in the US on October 1, 2015. The FY2026 edition carries it forward unchanged. Its parent subcategory, T86.29, is a heading and is never submitted.
T86.290 is reserved for cardiac allograft vasculopathy. T86.298 covers a heart transplant complication that is documented and affects graft function, but is not vasculopathy, rejection, failure, or infection. In the alphabetic index, T86.298 is the specified type NEC entry under Complication, transplant, heart.
Use T86.20 only where the record documents a complication of the heart transplant without saying what it is. T86.20 sits one level above T86.29 in the hierarchy, as a sibling rather than a child. If the note names cardiac allograft vasculopathy, T86.290 is the correct code and T86.20 risks a specificity denial.
No. The ICD-10-CM Official Guidelines state that Z94.1, heart transplant status, should not be used with a code from subcategory T86.2. The complication code already tells the payer that the patient has a transplanted heart. Category Z94 carries a matching Excludes1 note for complications of a transplanted organ.
No. An Excludes1 note under T86.290 bars coding it with I25.75-, I25.76-, or I25.81-. Those codes describe atherosclerosis in a transplanted heart. Follow the physician’s wording, so documented vasculopathy goes to T86.290 and documented atherosclerosis goes to the matching I25 code.
Where cardiac allograft vasculopathy is the condition chiefly responsible for an admission, T86.290 is the principal diagnosis. On a routine surveillance visit, code the reason for the encounter first and report T86.290 as an additional diagnosis. The guidelines also ask for a secondary code identifying any separately documented condition.
The physician must name cardiac allograft vasculopathy, allograft vasculopathy, or accelerated coronary artery disease in the graft. The record also needs the heart transplant history, the study supporting the diagnosis, and evidence that graft function is affected. A problem-list entry on its own will not hold up on audit.



