

HCPCS Code E0272: Foam rubber mattress billing guide
HCPCS Code E0272: official descriptor and code overview HCPCS Code E0272 is the ...

Last Updated: Nov 6, 2026
B2984 is the CCSD code for reconstruction of breast using pedicled TRAM (including delayed reconstruction).
Let Pabau's smart automation suggest the right codes, reduce claim denials, and keep your practice compliant—effortlessly.
Automate repetitive tasks and focus on what matters most—your patients.
Reduce coding errors and ensure compliance with the latest regulations.
Clean claims, fewer denials, and faster reimbursements.
Powerful insights and reporting to help your practice thrive.
HIPAA compliant SOC 2 certified GDPR-compliant Trusted by 4,000+ clinics worldwide

B2984 covers pedicled TRAM flap breast reconstruction, whether it is performed at the time of mastectomy or as a delayed procedure.
The pedicled flap keeps its superior epigastric blood supply, which separates it from the free TRAM and DIEP flaps and their own CCSD codes.
Major UK private insurers require pre-authorization before a B2984 procedure, and claims without a valid authorization reference are routinely denied.
Pabau’s claims management tools help private hospitals and practice teams document operative details and track authorization status for CCSD claims.
CCSD code B2984 covers pedicled TRAM flap breast reconstruction after mastectomy, performed as a single stage or in stages. The CCSD schedule defines its scope as “Reconstruction of breast using pedicled TRAM (including delayed reconstruction).”
This is the code for the main reconstructive episode only. Ancillary procedures, including nipple-areola complex (NAC) reconstruction and contralateral symmetrization, carry their own separate CCSD codes and may be co-billed where insurer rules allow.
B2984 sits in chapter 7 (Breast) of the CCSD codes schedule, alongside the other autologous and implant-based reconstruction codes. Chapter numbering is revised periodically, so confirm the reference against the CCSD edition you use. For Bupa CCSD procedure codes specifically, Bupa’s own code-search portal confirms which codes it accepts by episode type.
The pedicled TRAM flap uses a horizontal ellipse of lower abdominal skin and fat. Its blood supply comes from the superior epigastric vessels, which run through the rectus abdominis muscle. Unlike a free flap, the tissue island is never completely detached: The surgeon tunnels it under the skin and rotates it onto the chest wall. The intact muscle pedicle keeps the flap supplied with blood throughout.
Understanding the surgical steps matters for documentation. A complete operative note for B2984 should reflect all of the following stages:
Each of these steps should be legible in the operative note. Missing or vague documentation of the pedicle type is the most common trigger for insurer coding queries.
B2984 applies to both immediate and delayed pedicled TRAM flap reconstruction, as stated in the official CCSD descriptor. Timing changes what you document and what the authorization must cover, while the code stays the same.
The patient may have had the mastectomy under a different insurer or as an NHS patient. In that case, obtain the original oncology correspondence and include it when you request authorization for the delayed reconstruction. Insurers may downcode or query a B2984 claim if the clinical pathway from cancer diagnosis to reconstruction is not traceable in the supporting documentation.
The CCSD breast reconstruction chapter contains several autologous flap codes that are frequently confused. Free TRAM reconstruction, for example, is billed under B2985 rather than B2984. In US billing, the same single-pedicle TRAM operation is reported with CPT code 19367. The table below shows the key coding distinctions for the most common alternatives to B2984.
The pedicled TRAM and DIEP flap are the pair most commonly miscoded. Both harvest abdominal tissue for breast reconstruction. The operative distinction is anatomical: The pedicled TRAM retains the rectus abdominis muscle as the vascular conduit, sacrificing or significantly weakening it. The DIEP flap dissects individual perforator vessels through the muscle and leaves the muscle itself largely intact.
A coder cannot tell which code applies if the note fails to state whether the rectus was sacrificed or spared. Billing staff should return vague notes to the surgeon for clarification before submitting, rather than defaulting to the higher-value DIEP code. Upcoding from B2984 to a DIEP code is a common audit target for insurers processing high-volume reconstructive claims.
Each flap technique leaves its own phrases in the operative note, and the panel below matches those phrases to the code they support.
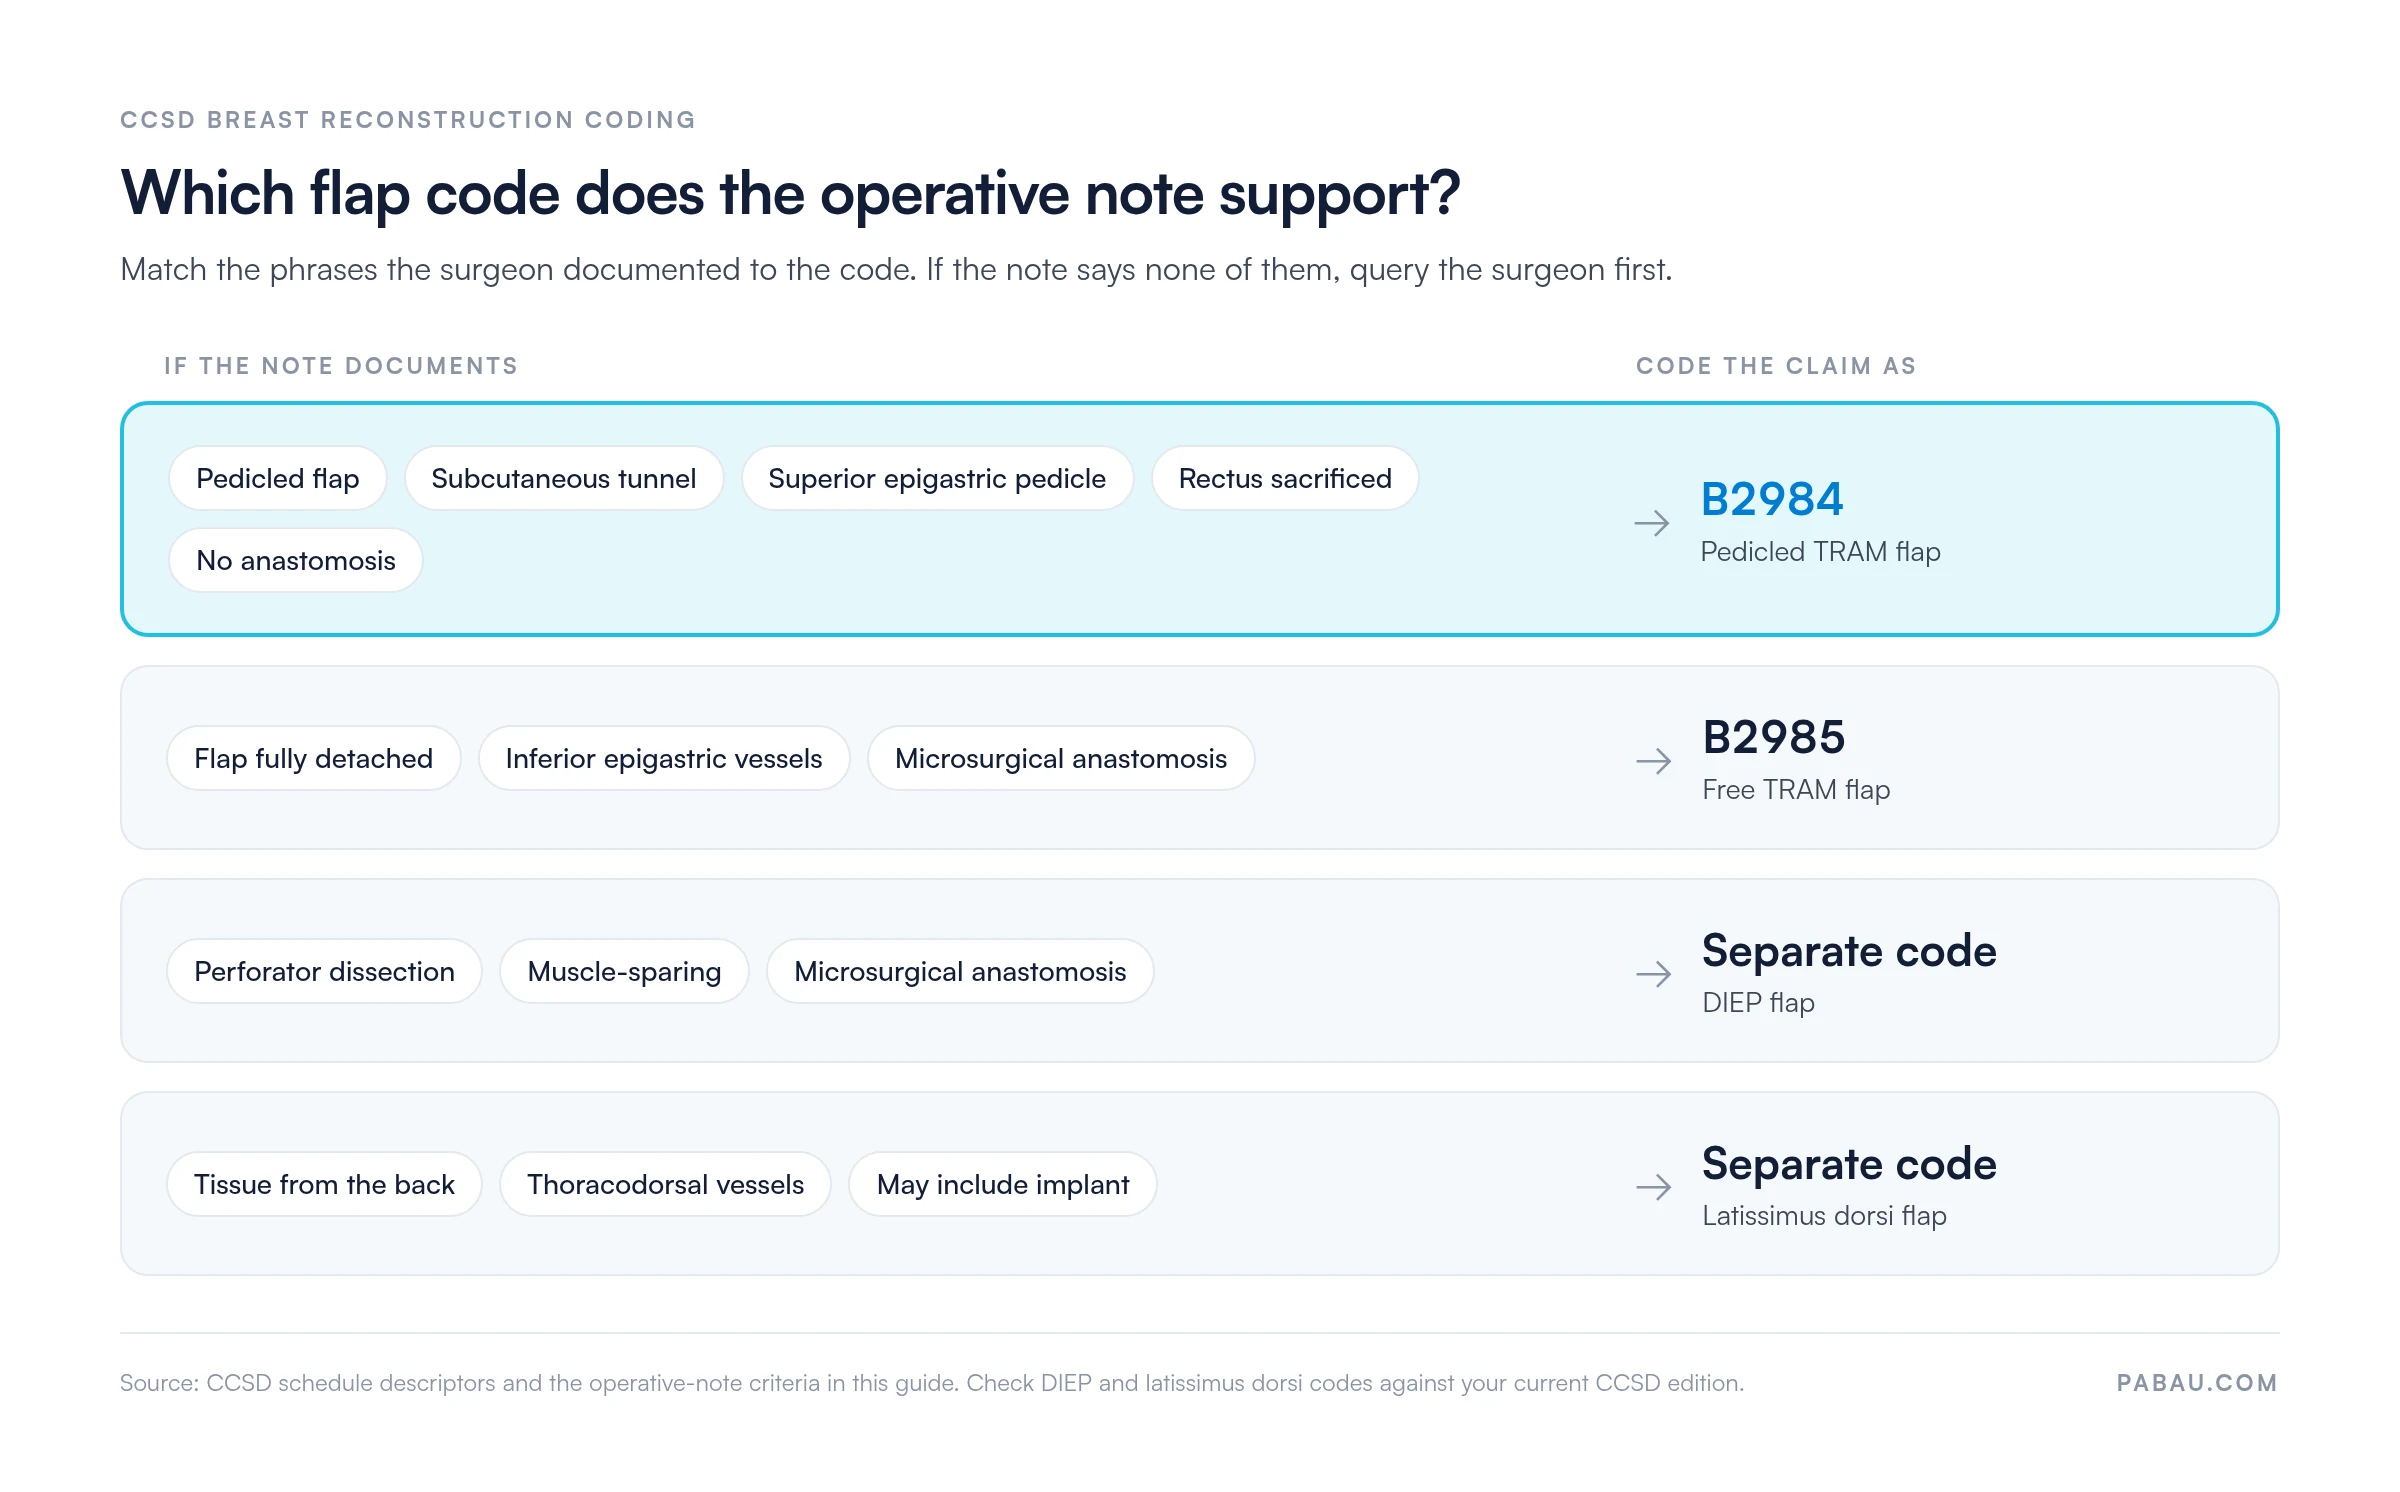
Before coding, check that the operative note uses the phrases ‘pedicled,’ ‘tunnel,’ and ‘muscle sacrifice’ or ‘rectus sacrificed.’ A correctly documented B2984 case contains all three. If the note instead documents ‘microsurgical anastomosis,’ ‘perforator dissection,’ or ‘muscle-sparing,’ stop and query the surgeon before assigning B2984.
Insurers assess B2984 claims primarily against the operative note and the pre-authorization correspondence. Digital operative forms with structured fields for flap type, pedicle status and reconstruction timing stop vague narrative notes from reaching the billing team.
The operative note should include all of the following to support a clean B2984 claim:
The patient record should also hold supporting documentation from the referring oncologist or breast surgeon. That includes the multidisciplinary team (MDT) decision and the original cancer diagnosis, ready for the insurer on request.
Every major UK private health insurer treats B2984 as a major elective procedure that requires pre-authorization. A claim submitted without a valid authorization reference is denied automatically in most cases.
The authorization request typically needs to include:
Insurer-specific requirements vary, and Bupa, AXA Health, Aviva, and Vitality each publish their own provider guidance. Check the Bupa code search portal, the Aviva fee schedule, and the Vitality fee finder directly. Criteria are updated periodically, and the most current version always governs.
Practices handling a high volume of reconstructive authorization requests benefit from medical claims management software. It tracks authorization reference numbers against individual patient episodes and keeps supporting documentation in one place for audits.
B2984 covers the pedicled TRAM reconstruction episode only. Other procedures performed in the same or later surgical episodes carry separate CCSD codes and may be co-billed, subject to insurer unbundling rules.
Where multiple procedures are planned for the same episode, list all intended CCSD codes in the pre-authorization request. Adding a co-procedure after authorization has been granted, without notifying the insurer, is a frequent cause of post-claim disputes.
Claims submitted under CCSD code B2984 are denied for a predictable set of reasons. Correct documentation and authorization practice prevent most of them. The table below maps the most common denial triggers to their corrective actions.
A pre-submission checklist that tests each of these denial triggers before the claim leaves the practice cuts avoidable rework.
Track B2984 authorization reference numbers against the surgical date in your practice management system, not just the patient record. Timing-mismatch denials usually start with an authorization number kept only in a paper file and missed when the procedure date changes. A digital audit trail makes appeal evidence immediately accessible.
Billing a B2984 case often means authorization numbers in an inbox, operative notes in the hospital system and claim status on a spreadsheet. When the surgery date moves, nobody rechecks the authorization until the denial arrives.
Pabau, the practice management platform we build for private practices, keeps those pieces on one patient record. Structured operative forms capture flap type, pedicle status and timing. The authorization reference sits against the booked procedure, and claims go to insurers through Healthcode.

Your billing team then checks one record before submission instead of three systems. Fewer claims come back for a missing reference or a vague note, and appeals start from evidence already on file.

Pabau helps private hospitals and practice teams track pre-authorization references, store operative documentation and submit CCSD claims through Healthcode from one system.

Choosing B2984 is rarely the hard part of a pedicled TRAM claim. The code is well defined, so payment turns on whether the paperwork proves which flap the surgeon raised and when.
Make two checks before every submission. Confirm that the operative note names the pedicled technique and the superior epigastric pedicle. Then confirm that the authorization still matches the surgery date, because a rescheduled operation is where clean claims most often go wrong.
To see how Pabau keeps CCSD authorizations and operative notes on the same patient record, book a demo.

Need a full reference for Bupa’s CCSD procedure codes? Bupa CCSD procedure codes covers the complete Bupa CCSD schedule including breast surgery chapter codes and billing guidance.
Want to understand how private healthcare claims management works end to end? Private healthcare claims management explains how Pabau helps track authorizations and submit CCSD claims through Healthcode.
Coding a free TRAM instead? CCSD code B2985 covers free TRAM flap breast reconstruction and the microsurgical documentation insurers expect.
Was the free TRAM done at the time of mastectomy? CCSD code B2983 covers immediate free TRAM breast reconstruction and how to bill it.
Billing the same operation in the US? CPT code 19367 explains TRAM flap breast reconstruction billing under the CPT system.
CCSD code B2984 covers breast reconstruction using a pedicled transverse rectus abdominis myocutaneous (TRAM) flap, either immediate or delayed. It applies to the main reconstructive episode. Nipple reconstruction and contralateral symmetrization carry separate CCSD codes.
A pedicled TRAM flap keeps its blood supply from the superior epigastric vessels through the intact rectus abdominis muscle. The flap is tunneled under the skin to the chest without being fully detached. A free TRAM flap is completely detached, and its blood supply is restored through microsurgical anastomosis to chest vessels. Free TRAM carries a different CCSD code, B2985.
Yes. The official CCSD descriptor for B2984 explicitly includes delayed reconstruction. Claims for delayed reconstruction should include oncology correspondence and the original mastectomy date so the insurer can verify the clinical pathway.
The most common denial reasons are: Missing or expired pre-authorization, a vague operative note, and a procedure date outside the authorized window. A note is vague when it does not say whether the flap was pedicled or free. Claims also fail when routine donor-site closure is coded separately, because it is bundled into B2984. Each reason has a corrective action in the denial table above.
Yes. Nipple-areola complex reconstruction and contralateral symmetrization carry their own CCSD codes and may be co-billed with B2984, subject to the insurer’s unbundling rules. List every intended co-procedure in the pre-authorization request before any of them is performed.
Insurers typically require the consultant surgeon’s recognized provider number, the intended CCSD code and procedure description, and the proposed hospital. They also want oncology correspondence confirming the cancer diagnosis and the MDT recommendation for reconstruction. State the intended timing, immediate or delayed, with the original mastectomy date for delayed cases. Requirements vary by insurer, so verify current criteria with each payer before submitting.




